

Form DB-450 at a glance
What it is: This is the New York State Notice and Proof of Claim for Disability Benefits. How to request Disability Benefits.
Where and when to file: Do not submit this form prior to your first date of disability. You must submit your completed claim form within 30 calendar days of your first day of disability to avoid losing benefits. Keep a copy of all forms and documentations for your records. 1. If you are using this form because you became disabled while employed or you became disabled within four (4) weeks after termination of employment, your completed claim should be submitted to your employer or your last employer's insurance carrier. You may find your employer's disability insurance carrier on the Workers' Compensation Board's website, www.wcb.ny.gov, using Employer Coverage Search. 2. If you are using this form because you became disabled after having been unemployed for more than four (4) weeks after termination of employment, your completed claim MUST be mailed to: Workers' Compensation Board, Disability Benefits Bureau, PO Box 9029, Endicott, NY 13761-9029. If you answered "Yes" to question 13.B.4., please complete and attach Form DB-450.1. Note: This form has a section to be filled out by your healthcare provider, and a section to be completed by your employer. Before providing the form to your employer, fill out your section and make a copy to keep.
Who signs: An individual may sign on behalf of the claimant only if they are legally authorized to do so and the claimant is a minor, mentally incompetent or incapacitated. I certify that I am a: (Physician, Chiropractor, Dentist, Podiatrist, Psychologist, Nurse-Midwife) Licensed or Certified in the State of, License Number, Health Care Provider's Printed Name, Health Care Provider's Signature, Date. Part C, Employer Information, is to be completed by the employer.
A filled-in Form DB-450 example: an employee who hurt an ankle at home fills out Part A
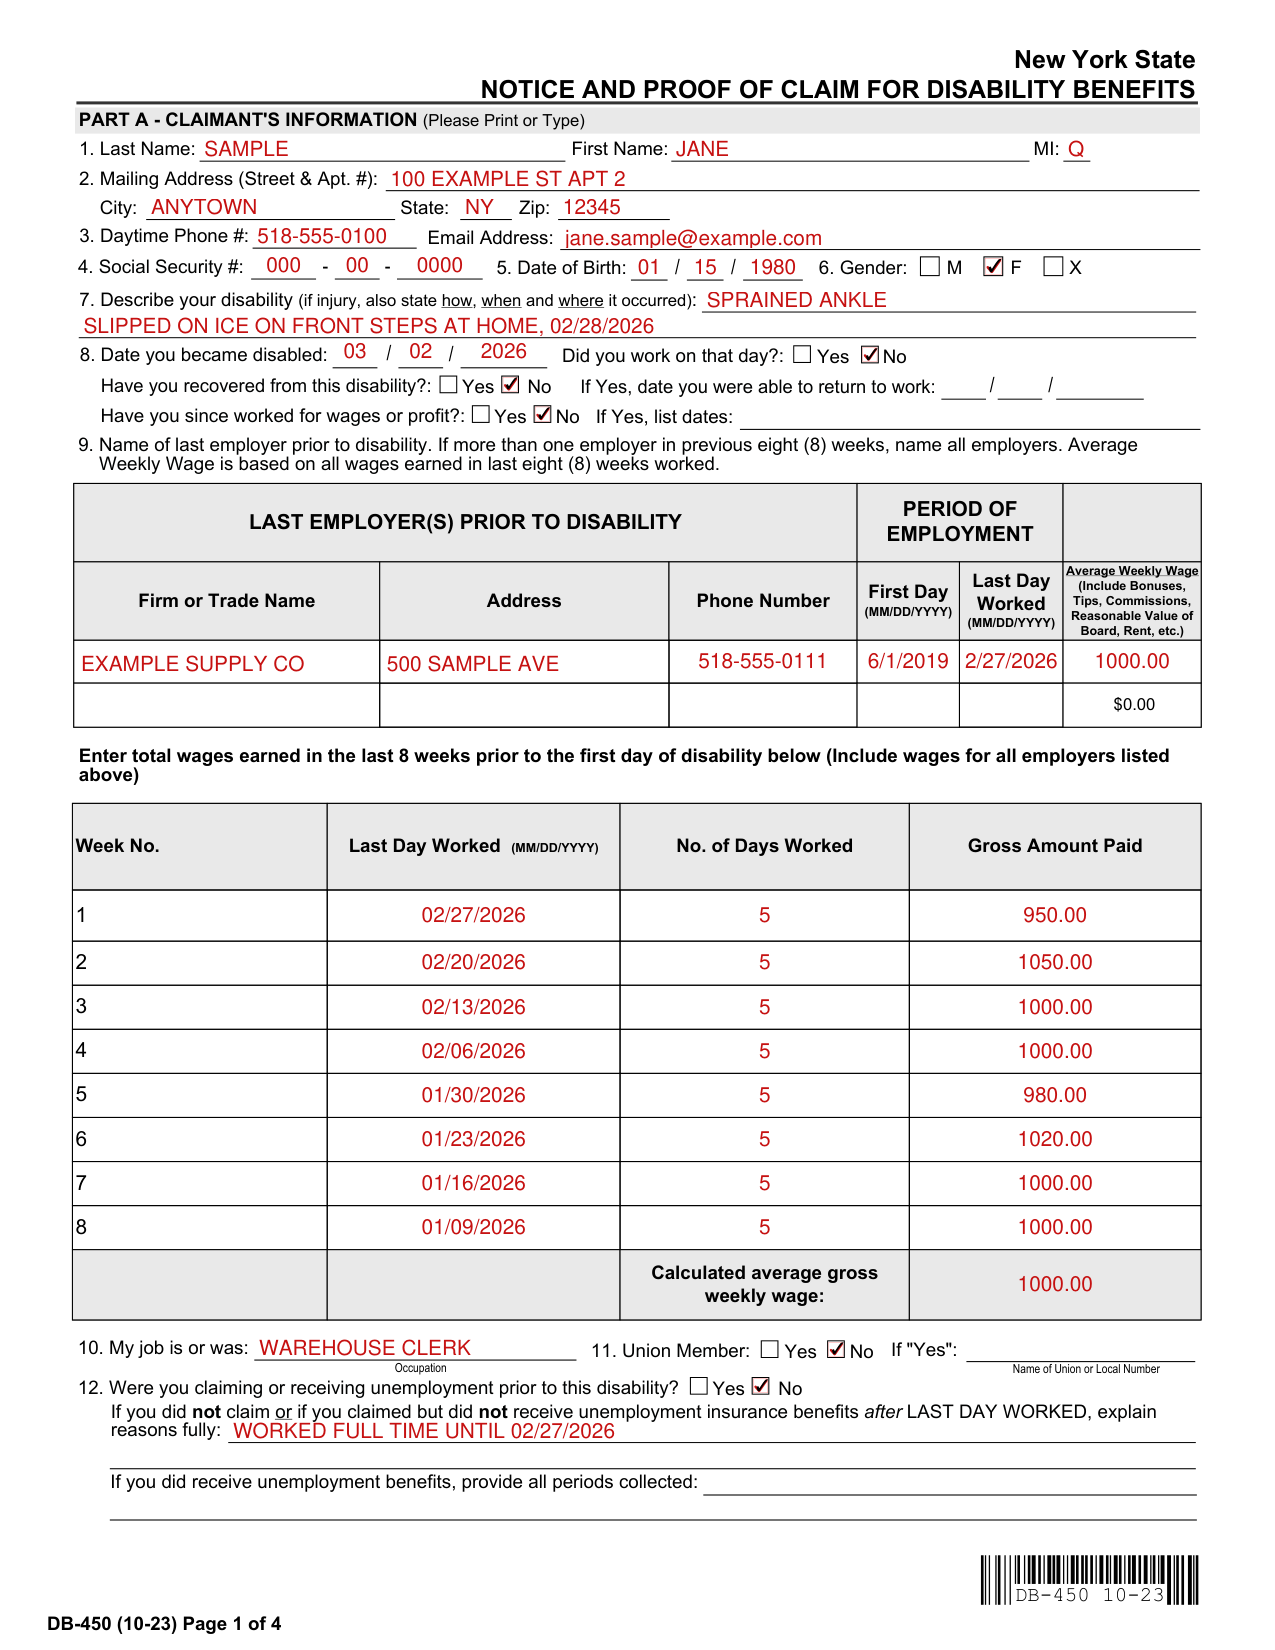
How to fill out Form DB-450, box by box
Tap a group of boxes to open it, and a picture to see it full size.
When to submit and where to mail the claim
Do not submit this form prior to your first date of disability. You must submit your completed claim form within 30 calendar days of your first day of disability to avoid losing benefits. Keep a copy of all forms and documentations for your records.
1. If you are using this form because you became disabled while employed or you became disabled within four (4) weeks after termination of employment, your completed claim should be submitted to your employer or your last employer's insurance carrier. You may find your employer's disability insurance carrier on the Workers' Compensation Board's website, www.wcb.ny.gov, using Employer Coverage Search. 2. If you are using this form because you became disabled after having been unemployed for more than four (4) weeks after termination of employment, your completed claim MUST be mailed to: Workers' Compensation Board, Disability Benefits Bureau, PO Box 9029, Endicott, NY 13761-9029. If you answered "Yes" to question 13.B.4., please complete and attach Form DB-450.1. Note: This form has a section to be filled out by your healthcare provider, and a section to be completed by your employer. Before providing the form to your employer, fill out your section and make a copy to keep.
Part A, the claimant: questions 1 to 16
Part A, Employee Information (Claimant's Information on the form), is to be completed by the employee. Please Print or Type.
Have you since worked for wages or profit?: Yes No If Yes, list dates: 9.
Name of last employer prior to disability. If more than one employer in previous eight (8) weeks, name all employers. Average Weekly Wage is based on all wages earned in last eight (8) weeks worked.
You must answer all questions in this part. Question 9: Enter the best estimate of average gross weekly wage. Fill out the table using your gross wages from your last employer prior to disability. If you had more than one employer in the previous 8 weeks prior to your disability, include all wage information from those employer(s) as well.
Step 1: Add all gross wages received (before any deductions) over the last eight weeks prior to the first day of disability, including overtime and tips earned. (See Step 3 for instructions for calculating bonuses and/or commissions.) Step 2: Divide the gross wages calculated in step one by eight (or the number of weeks worked if less than eight) to calculate the average weekly wage. Step 3: If you received bonuses and/or commissions during the 52 weeks preceding the first day of disability, add the prorated weekly amount to the average weekly wage. To determine the prorated weekly amount, add all bonuses/commissions earned in the preceding 52 weeks and then divide by 52.
Providing your social security number to the Board is voluntary. There is no penalty for failure to provide your social security number on this form; it will not result in a denial of your claim or a reduction in benefits.
If you did not claim or if you claimed but did not receive unemployment insurance benefits after LAST DAY WORKED, explain reasons fully.
If you did receive unemployment benefits, provide all periods collected.
Part A, the claimant: signing the claim
I hereby claim Disability Benefits and certify that for the period covered by this claim I was disabled.
I have read the instructions of this form and certify that the foregoing statements, including any accompanying statements are, to the best of my knowledge, true and complete.
An individual may sign on behalf of the claimant only if they are legally authorized to do so and the claimant is a minor, mentally incompetent or incapacitated.
If signed by other than claimant, print information (On behalf of Claimant, Address, Relationship to Claimant) and complete and submit Form OC-110A, Claimant's Authorization to Disclose Workers' Compensation Records.
Part B, the health care provider's statement
Part B, Health Care Provider's Statement, is to be completed by the health care provider. Please Print or Type.
The health care provider must fill in this statement completely and return it within seven (7) days of receipt of this form.
Incomplete answers may delay payment of benefits.
If disability is caused by or arising in connection with pregnancy, enter estimated delivery date in item 7-e.
Box 6, Operation indicated? Yes No. a. Type. b. Date.
Box 7: Enter dates for the following: month, day, year. a. Date of the Health Care Provider's first treatment for this disability.
b. Date of the Health Care Provider's most recent treatment for this disability.
c. Date Claimant was unable to work because of this disability.
d. Date Claimant will again be able to perform work (Even if considerable question exists, estimate date. Avoid use of terms such as unknown or undetermined.)
I certify that I am a: (Physician, Chiropractor, Dentist, Podiatrist, Psychologist, Nurse-Midwife) Licensed or Certified in the State of, License Number, Health Care Provider's Printed Name, Health Care Provider's Signature, Date.
Part C, the employer's information and signature
Part C, Employer Information, is to be completed by the employer.
The employer must complete and return to the employee within three business days of receipt. Question 6: If wages were continued during disability, specify how wages were paid - through salary continuation, use of paid time off, sick time, etc. Question 8: Enter the wages earned by the employee during the last eight weeks preceding the first day of disability. The gross amount paid is the employee's gross weekly pay, including any overtime and tips earned for that week, plus the weekly prorated amount of any bonus or commission received during the preceding 52 weeks. (For detailed steps, see Question 9 in the Part A instructions). Calculate the gross average weekly wage by adding up the gross amounts paid, and then dividing the total by eight (or number of weeks worked if less than eight).
If yes, is reimbursement requested by employer? Yes No. Reimbursement is only available if employer continued salary during disability or employee used sick time.
I have read and acknowledge the fraud information below and affirm that to the best of my knowledge and belief, the information I have provided is true and accurate.
FRAUD ACKNOWLEDGEMENT: An employer or insurer, or any employee, agent, or person acting on behalf of an employer or insurer, who KNOWINGLY MAKES A FALSE STATEMENT OR REPRESENTATION as to a material fact in the course of reporting, investigation of, or adjusting a claim for any benefit or payment under this chapter for the purpose of avoiding provision of such payment or benefit SHALL BE GUILTY OF A CRIME AND SUBJECT TO SUBSTANTIAL FINES AND IMPRISONMENT.
Authorizing disclosure
Common questions about Form DB-450
How do I get my doctor to fill out disability forms?
The health care provider must fill in this statement completely and return it within seven (7) days of receipt of this form.
What is a DB 450 form?
This is the New York State Notice and Proof of Claim for Disability Benefits. How to request Disability Benefits.
Is there a deadline?
Do not submit this form prior to your first date of disability. You must submit your completed claim form within 30 calendar days of your first day of disability to avoid losing benefits. Keep a copy of all forms and documentations for your records.
Where do I file it?
1. If you are using this form because you became disabled while employed or you became disabled within four (4) weeks after termination of employment, your completed claim should be submitted to your employer or your last employer's insurance carrier. You may find your employer's disability insurance carrier on the Workers' Compensation Board's website, www.wcb.ny.gov, using Employer Coverage Search. 2. If you are using this form because you became disabled after having been unemployed for more than four (4) weeks after termination of employment, your completed claim MUST be mailed to: Workers' Compensation Board, Disability Benefits Bureau, PO Box 9029, Endicott, NY 13761-9029. If you answered "Yes" to question 13.B.4., please complete and attach Form DB-450.1. Note: This form has a section to be filled out by your healthcare provider, and a section to be completed by your employer. Before providing the form to your employer, fill out your section and make a copy to keep.
Sources
[1] Form DB-450 (10-23), Notice and Proof of Claim for Disability Benefits, New York State Workers' Compensation Board (the Official source link on this page).
