

Form H511.336 at a glance
What it is: Form H511.336 is the Private or School Physical Examination of School Age Student, from the Bureau of Community Health Systems, Division of School Health.
Who signs: Sign as parent / guardian / emancipated student and write the Date.
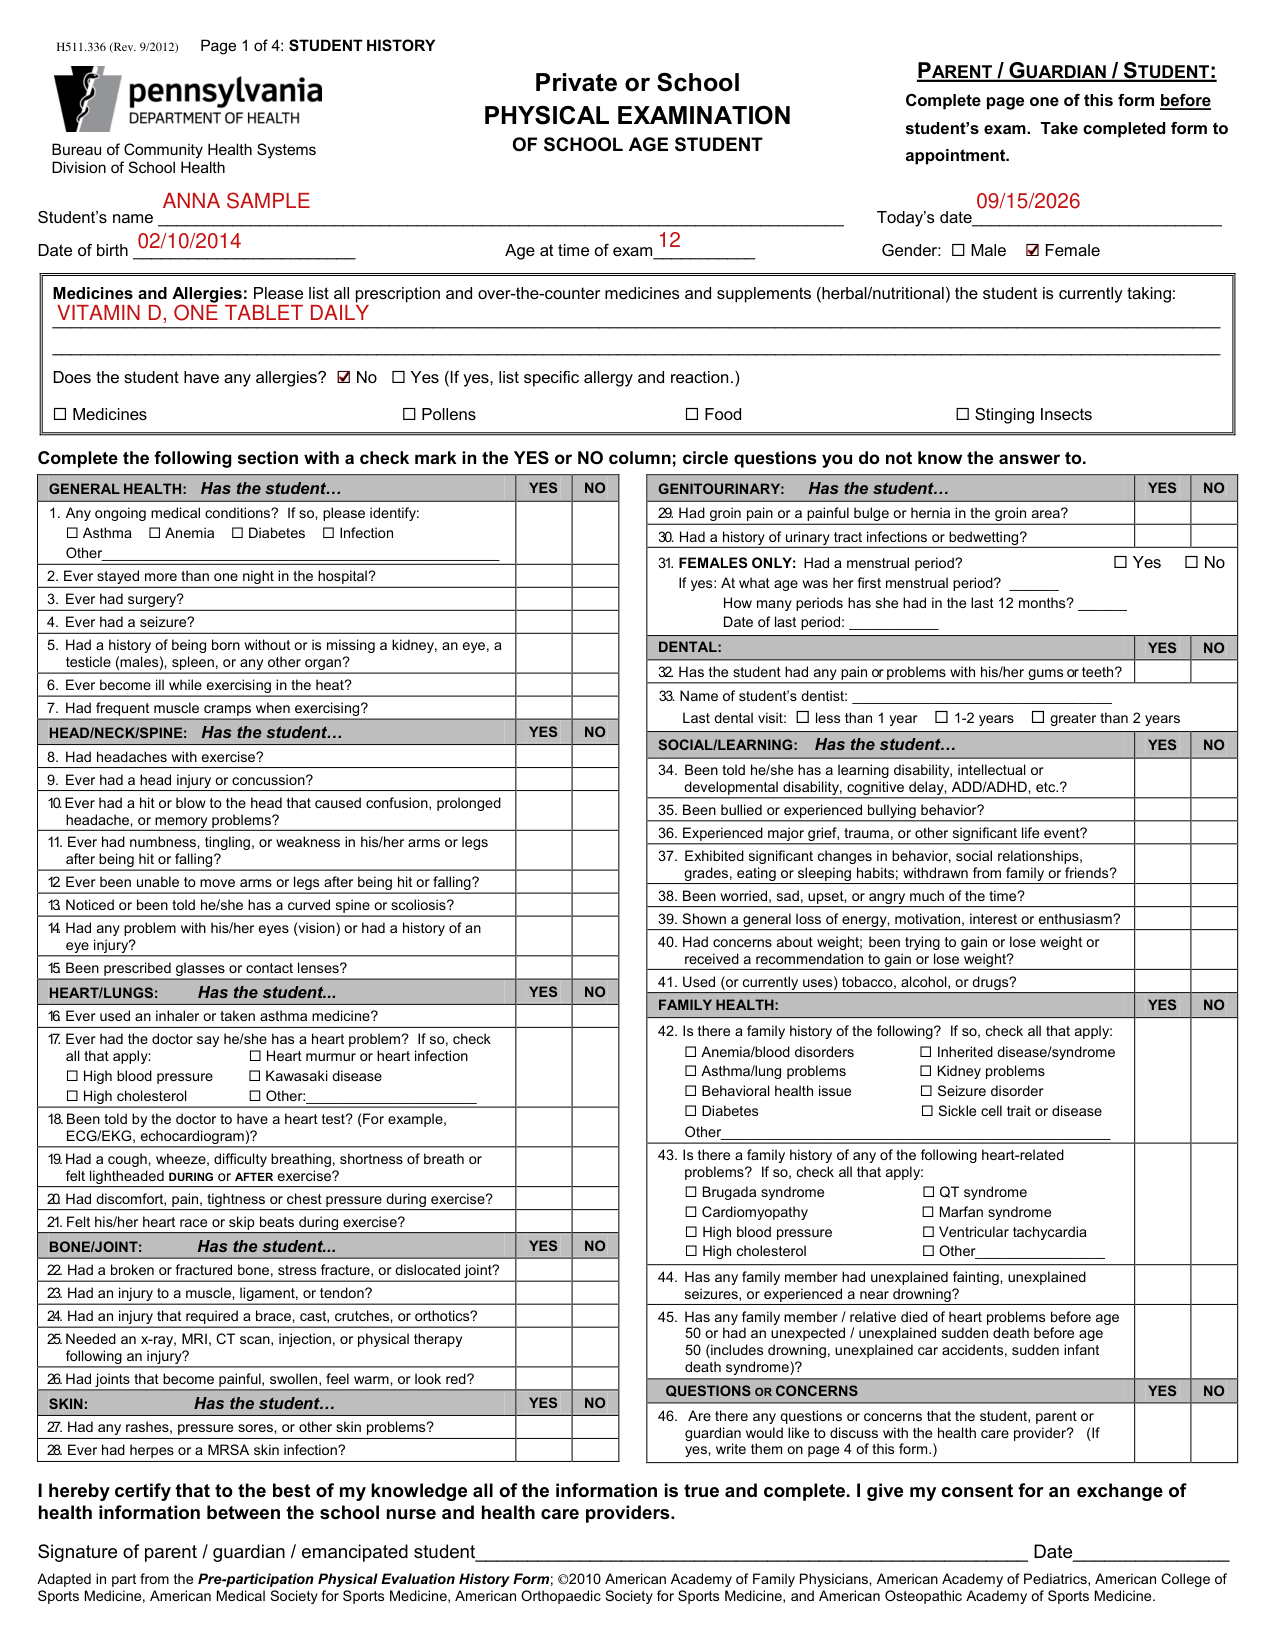
A filled-in Form H511.336 example: a parent fills out the top of page one
How to fill out Form H511.336, box by box
Student's name, Today's date, Date of birth, Age at time of exam and Gender

Write the Student's name, Today's date, Date of birth and Age at time of exam, and check Male or Female after Gender.
Medicines and Allergies

Please list all prescription and over-the-counter medicines and supplements (herbal/nutritional) the student is currently taking.
Does the student have any allergies? Check No or Yes. If yes, list specific allergy and reaction, and check Medicines, Pollens, Food or Stinging Insects.
Signature, certification and consent

By signing, you certify that to the best of your knowledge all of the information is true and complete. You give your consent for an exchange of health information between the school nurse and health care providers.
More rules for Form H511.336
PARENT / GUARDIAN / STUDENT: Complete page one of this form before student's exam. Take completed form to appointment.
Complete the following section with a check mark in the YES or NO column; circle questions you do not know the answer to.
1. Any ongoing medical conditions? If so, please identify: Asthma, Anemia, Diabetes, Infection or Other.
2. Ever stayed more than one night in the hospital?
3. Ever had surgery?
4. Ever had a seizure?
17. Ever had the doctor say he/she has a heart problem? If so, check all that apply: Heart murmur or heart infection, High blood pressure, Kawasaki disease, High cholesterol or Other.
31. FEMALES ONLY: Had a menstrual period? Check Yes or No. If yes: write At what age was her first menstrual period, How many periods has she had in the last 12 months and the Date of last period.
33. Name of student's dentist. Check the Last dental visit: less than 1 year, 1-2 years or greater than 2 years.
42. Is there a family history of the following? If so, check all that apply: Anemia/blood disorders, Inherited disease/syndrome, Asthma/lung problems, Kidney problems, Behavioral health issue, Seizure disorder, Diabetes, Sickle cell trait or disease or Other.
43. Is there a family history of any of the following heart-related problems? If so, check all that apply: Brugada syndrome, QT syndrome, Cardiomyopathy, Marfan syndrome, High blood pressure, Ventricular tachycardia, High cholesterol or Other.
46. Are there any questions or concerns that the student, parent or guardian would like to discuss with the health care provider? If yes, write them on page 4 of this form.
The examiner checks Yes or No: STUDENT'S HEALTH HISTORY (page 1 of this form) REVIEWED PRIOR TO PERFOMING EXAMINATION.
The examiner checks Physical exam for grade: K/1, 6, 11 or Other.
The examiner checks Parent/guardian present during exam: Yes or No, checks Physical exam performed at: Personal Health Care Provider's Office or School, and writes the Date of exam.
Print name of examiner, Print examiner's office address and Phone; sign as Signature of examiner and check MD, DO, PAC or CRNP.
HEALTH CARE PROVIDERS: Please photocopy immunization history from student's record - OR - insert information under VACCINE DOCUMENT.
Under IMMUNIZATION EXEMPTION(S), a Medical exemption has a Date Issued, a Reason and a Date Rescinded.
NOTE: The parent/guardian must provide a written request to the school for a religious or philosophical exemption.
VACCINE DOCUMENT: (1) Type of vaccine; (2) Date (month/day/year) for each immunization.
Page 4 of 4: ADDITIONAL COMMENTS (PARENT / GUARDIAN / STUDENT / HEALTH CARE PROVIDER).
Sources
[1] Form H511.336 (Rev. 9/2012), Private or School Physical Examination of School Age Student, Pennsylvania Department of Health (the Official source link on this page).