

Form HCA-15 at a glance
What it is: The HCA-15 (Revised 09/03/2014, page 2) is the CMS-1500, Dental, Crossover Part B Paid Claim Adjustment Request of the Oklahoma Health Care Authority.
Where and when to file: Mail completed requests to: OHCA - Adjustments, 4345 N. Lincoln Blvd., Oklahoma City, OK 73105.
A completed adjustment request form is required for each claim you are requesting to be adjusted.
A filled-in Form HCA-15 example: a dental office corrects a client ID

How to fill out Form HCA-15, box by box
Provider number, name, address and reason for adjustment
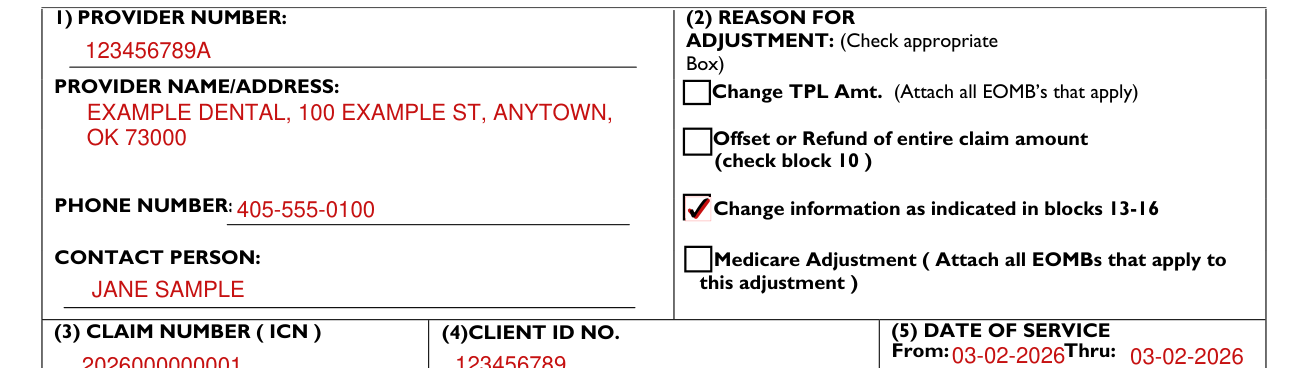
(1) Provider number: Enter your 9 digit billing provider number and 1 character service location. Enter your current billing name and address. Enter phone number of contact person. Enter a contact name. (2) Reason for adjustment: Check the appropriate box for the reason you are requesting an adjustment.
Change TPL Amt. (Attach all EOMB's that apply)
Offset or Refund of entire claim amount (check block 10)
Change information as indicated in blocks 13-16
Medicare Adjustment (Attach all EOMBs that apply to this adjustment)
Claim number, client, dates of service and explanation
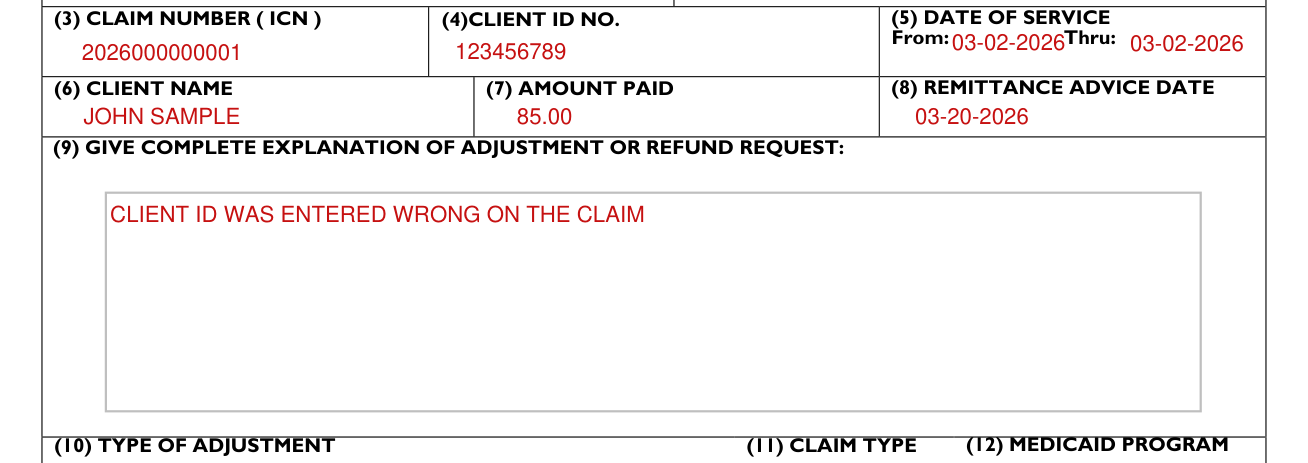
(3) Claim Number (ICN): Enter the Internal Control Number of the claim you wish to adjust. This can be found on the Remittance Advice. (Use the most current ICN for the claim to be adjusted.) The next box is (4) Client ID No.
Enter the recipient's 9 digit identification number. (5) Dates of Service: Enter the From and Thru Dates of Service as billed on the claim. (6) Client Name: Enter the First and Last Name of the Recipient. (7) Amount Paid: Enter the Paid Amount of the claim to be adjusted. (8) Remittance Advice Date: Enter the date of your Remittance Advice on which the claim last paid. (9) Explanation: Give a clear explanation for the requested adjustment or refund.
Type of adjustment, claim type and program

(10) Type of Adjustment: Check the appropriate box for the type of adjustment you are requesting. Underpayment is an adjustment to a claim in which you are requesting additional payment, or for which you are requesting a change to the claim's data which will result in no net change in payment. Overpayment is an adjustment to a claim for which you are requesting that an overpaid amount be deducted from your future payments.
An overpayment may be a recoupment of a portion of the claim or the entire amount of the claim. Refund is the same as overpayment except that you are submitting a refund check for the overpaid amount. A refund may be applied to a portion of the claim or to the entire amount of the claim.
(11) Claim Type: Check the appropriate box of the claim type to be adjusted. (12) Program: Check the appropriate box of the program to which the claim to be adjusted is associated.
Line number, description, current and corrected information
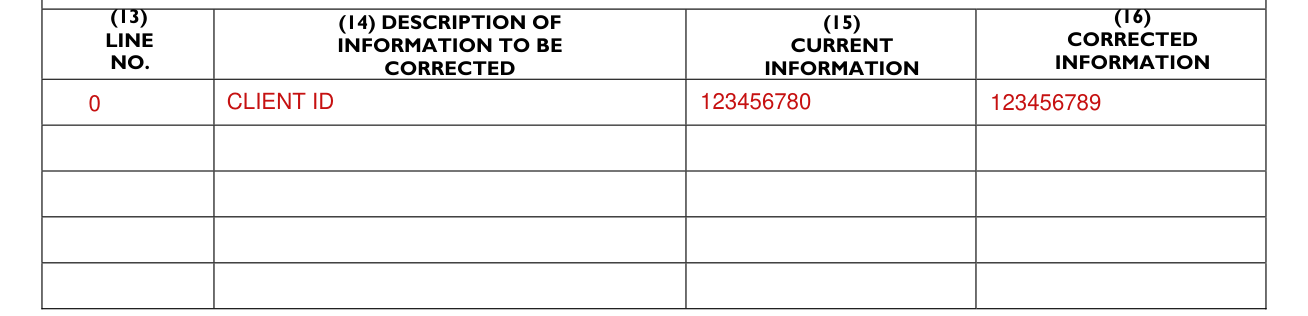
(13) Line No.: Enter the number of the line that data is to be adjusted. If the adjusted data is not associated to a specific line on the claim, enter a zero (0) in this field. (14) Description: Enter a brief description of the data that is to be corrected on the claim. (15) Current Info: Enter the information as stated on the current claim that is to be adjusted. (16) Corrected Info: Enter the corrected information for the claim.
Signature and date

(17) Signature: Sign as the appropriate person (physician, billing clerk, etc., not required). (18) Date: Enter the date you are submitting this request (Required).
More rules for Form HCA-15
In addition, a copy of the Remittance Advice and a copy of the corrected claim will also facilitate the adjustment process.
If the adjustment request is for a Crossover claim attach a copy of the Medicare EOMB or if the request is for an adjustment to the TPL amount attach a copy of the insurance EOMB.
Common questions about Form HCA-15
Where do I file it?
Mail Refunds to: OHCA-Finance, P.O. Box 18299, Oklahoma City, OK 73154-0299.
Sources
[1] Form HCA-15, CMS-1500, Dental, Crossover Part B Paid Claim Adjustment Request, Oklahoma Health Care Authority (the Official source link on this page).