


Form HC-5 at a glance
What it is: Form HC-5 is the Employee Notification to Employer for calendar year 2025 of the State of Hawaii Department of Labor and Industrial Relations, Disability Compensation Division.
Who signs: The employee fills in Print employee name, Employee signature, Address, Phone no. and Date.
Where and when to file: Keep a copy of your completed, signed form for yourself. RETURN COMPLETED FORM TO EMPLOYER.
Use this form if the employee works at least 20 hours per week and works for 2 or more employers, claims an exemption or waiver from health care coverage, terminates an exemption or changes principal and/or secondary employer designation.
A filled-in Form HC-5 example: a worker with two employers
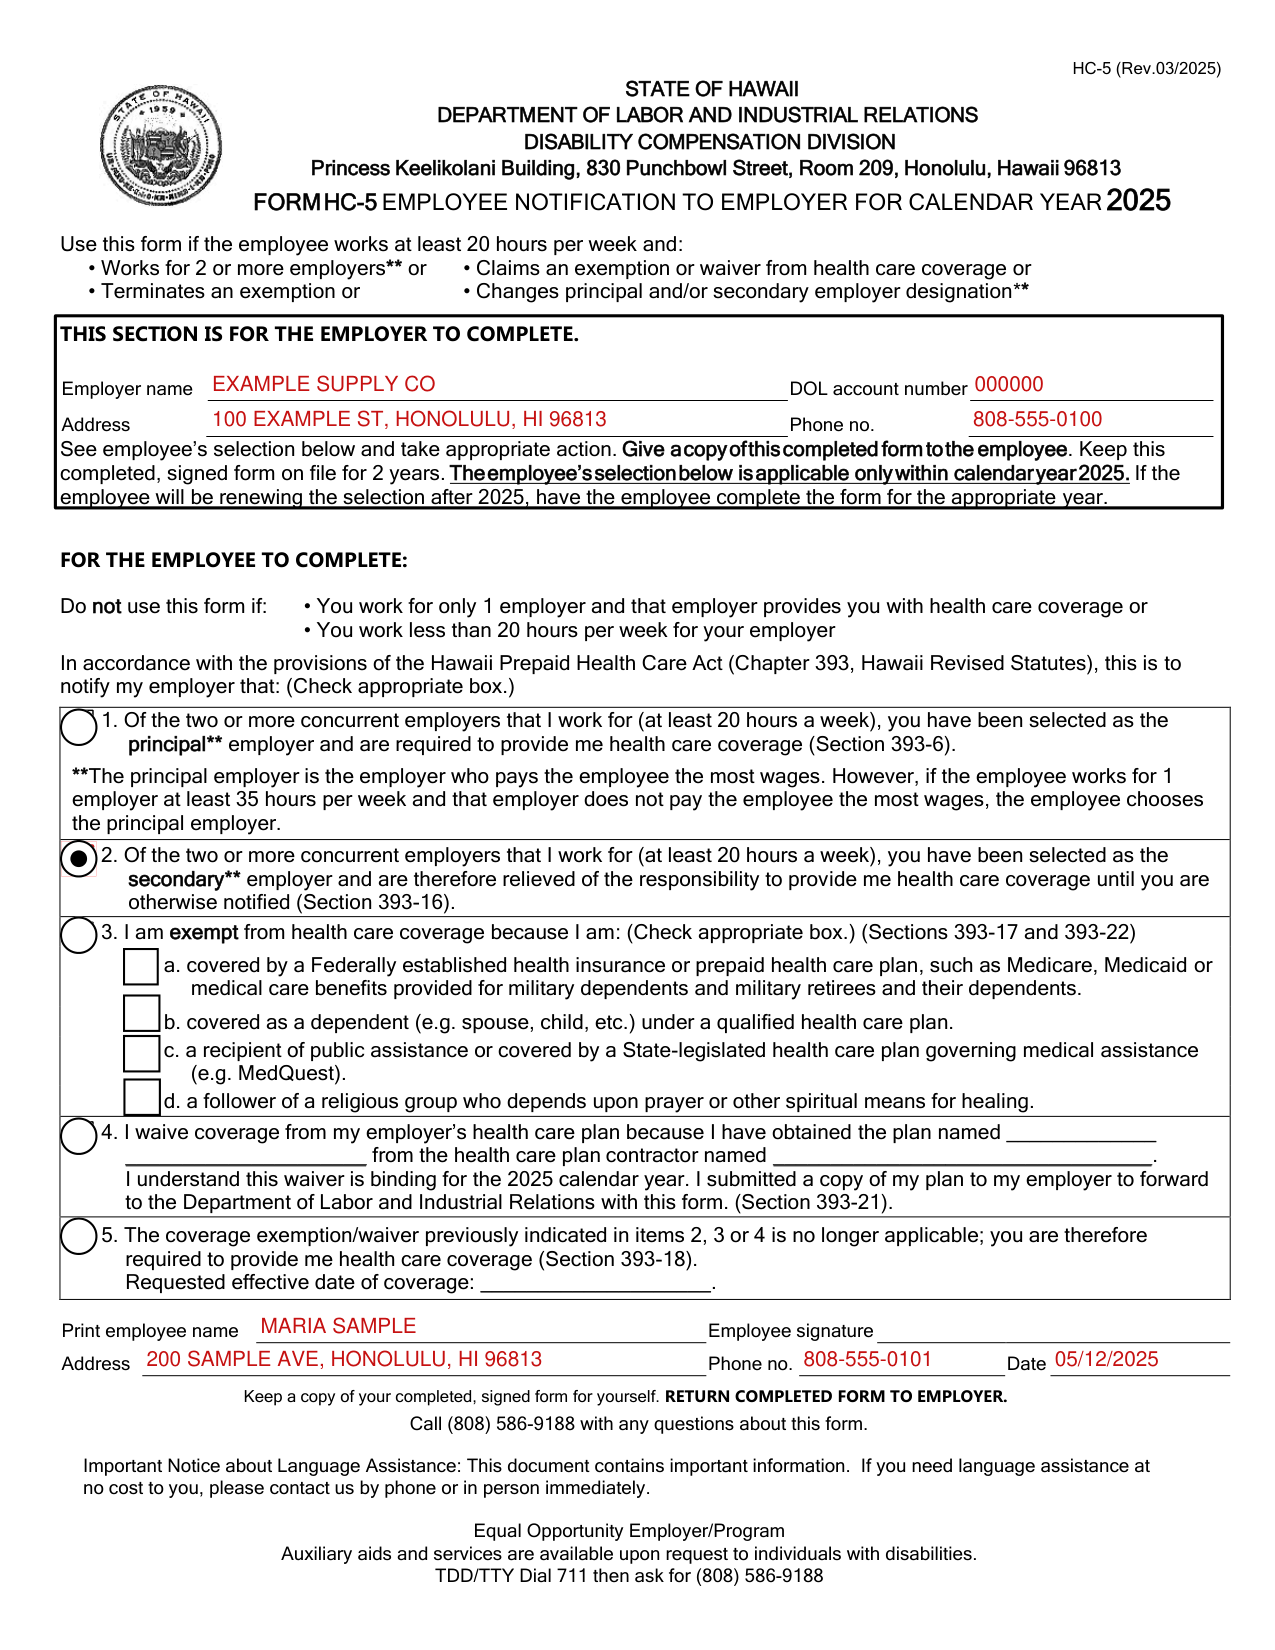
How to fill out Form HC-5, box by box
THIS SECTION IS FOR THE EMPLOYER TO COMPLETE

THIS SECTION IS FOR THE EMPLOYER TO COMPLETE: Employer name and DOL account number.
Address and Phone no. See employee's selection under FOR THE EMPLOYEE TO COMPLETE and take appropriate action. Give a copy of this completed form to the employee. Keep this completed, signed form on file for 2 years. The employee's selection under FOR THE EMPLOYEE TO COMPLETE is applicable only within calendar year 2025. If the employee will be renewing the selection after 2025, have the employee complete the form for the appropriate year.
Check appropriate box

The employee completes the section marked FOR THE EMPLOYEE TO COMPLETE and checks the appropriate box to notify the employer under the Hawaii Prepaid Health Care Act (Chapter 393, Hawaii Revised Statutes).
Box 1: of the two or more concurrent employers the employee works for (at least 20 hours a week), the employer has been selected as the principal employer and is required to provide the employee health care coverage (Section 393-6).
The principal employer is the employer who pays the employee the most wages. However, if the employee works for 1 employer at least 35 hours per week and that employer does not pay the employee the most wages, the employee chooses the principal employer.
Box 2: of the two or more concurrent employers the employee works for (at least 20 hours a week), the employer has been selected as the secondary employer and is therefore relieved of the responsibility to provide the employee health care coverage until otherwise notified (Section 393-16).
Box 3 (Sections 393-17 and 393-22): check the appropriate box if the employee is exempt from health care coverage because the employee is covered by a Federally established health insurance or prepaid health care plan, such as Medicare, Medicaid or medical care benefits provided for military dependents and military retirees and their dependents.
Box 3 (Sections 393-17 and 393-22): check the appropriate box if the employee is exempt from health care coverage because the employee is covered as a dependent (e.g. spouse, child, etc.) under a qualified health care plan.
Box 3 (Sections 393-17 and 393-22): check the appropriate box if the employee is exempt from health care coverage because the employee is a recipient of public assistance or covered by a State-legislated health care plan governing medical assistance (e.g. MedQuest).
Box 3 (Sections 393-17 and 393-22): check the appropriate box if the employee is exempt from health care coverage because the employee is a follower of a religious group who depends upon prayer or other spiritual means for healing.
Box 4: the employee waives coverage from the employer's health care plan because the employee has obtained the plan named on the form from the health care plan contractor named on the form. The employee understands this waiver is binding for the 2025 calendar year and submitted a copy of the plan to the employer to forward to the Department of Labor and Industrial Relations with this form (Section 393-21).
Box 5: "The coverage exemption/waiver previously indicated in items 2, 3 or 4, is no longer applicable; you are therefore required to provide me health care coverage (Section 393-18)." Requested effective date of coverage.
Print employee name, Employee signature and Date

The employee fills in Print employee name, Employee signature, Address, Phone no. and Date.
Common questions about Form HC-5
Where do I file it?
Keep a copy of your completed, signed form for yourself. RETURN COMPLETED FORM TO EMPLOYER.
When is this form not the right one?
Do not use this form if you work for only 1 employer and that employer provides you with health care coverage, or you work less than 20 hours per week for your employer.
Where to get help with Form HC-5
Call (808) 586-9188 with any questions about this form.
Sources
[1] Form HC-5 (Rev.03/2025), Employee Notification to Employer, State of Hawaii Department of Labor and Industrial Relations (the Official source link on this page).