
How to Fill Out Form HCFA-487

Form HCFA-487 at a glance

What it is: Form HCFA-487 is an addendum to the plan of treatment or medical update.

Who signs: Under 9. Signature of Physician, the physician signs and enters 10. Date.

A filled-in Form HCFA-487 example: an addendum to the plan of treatment
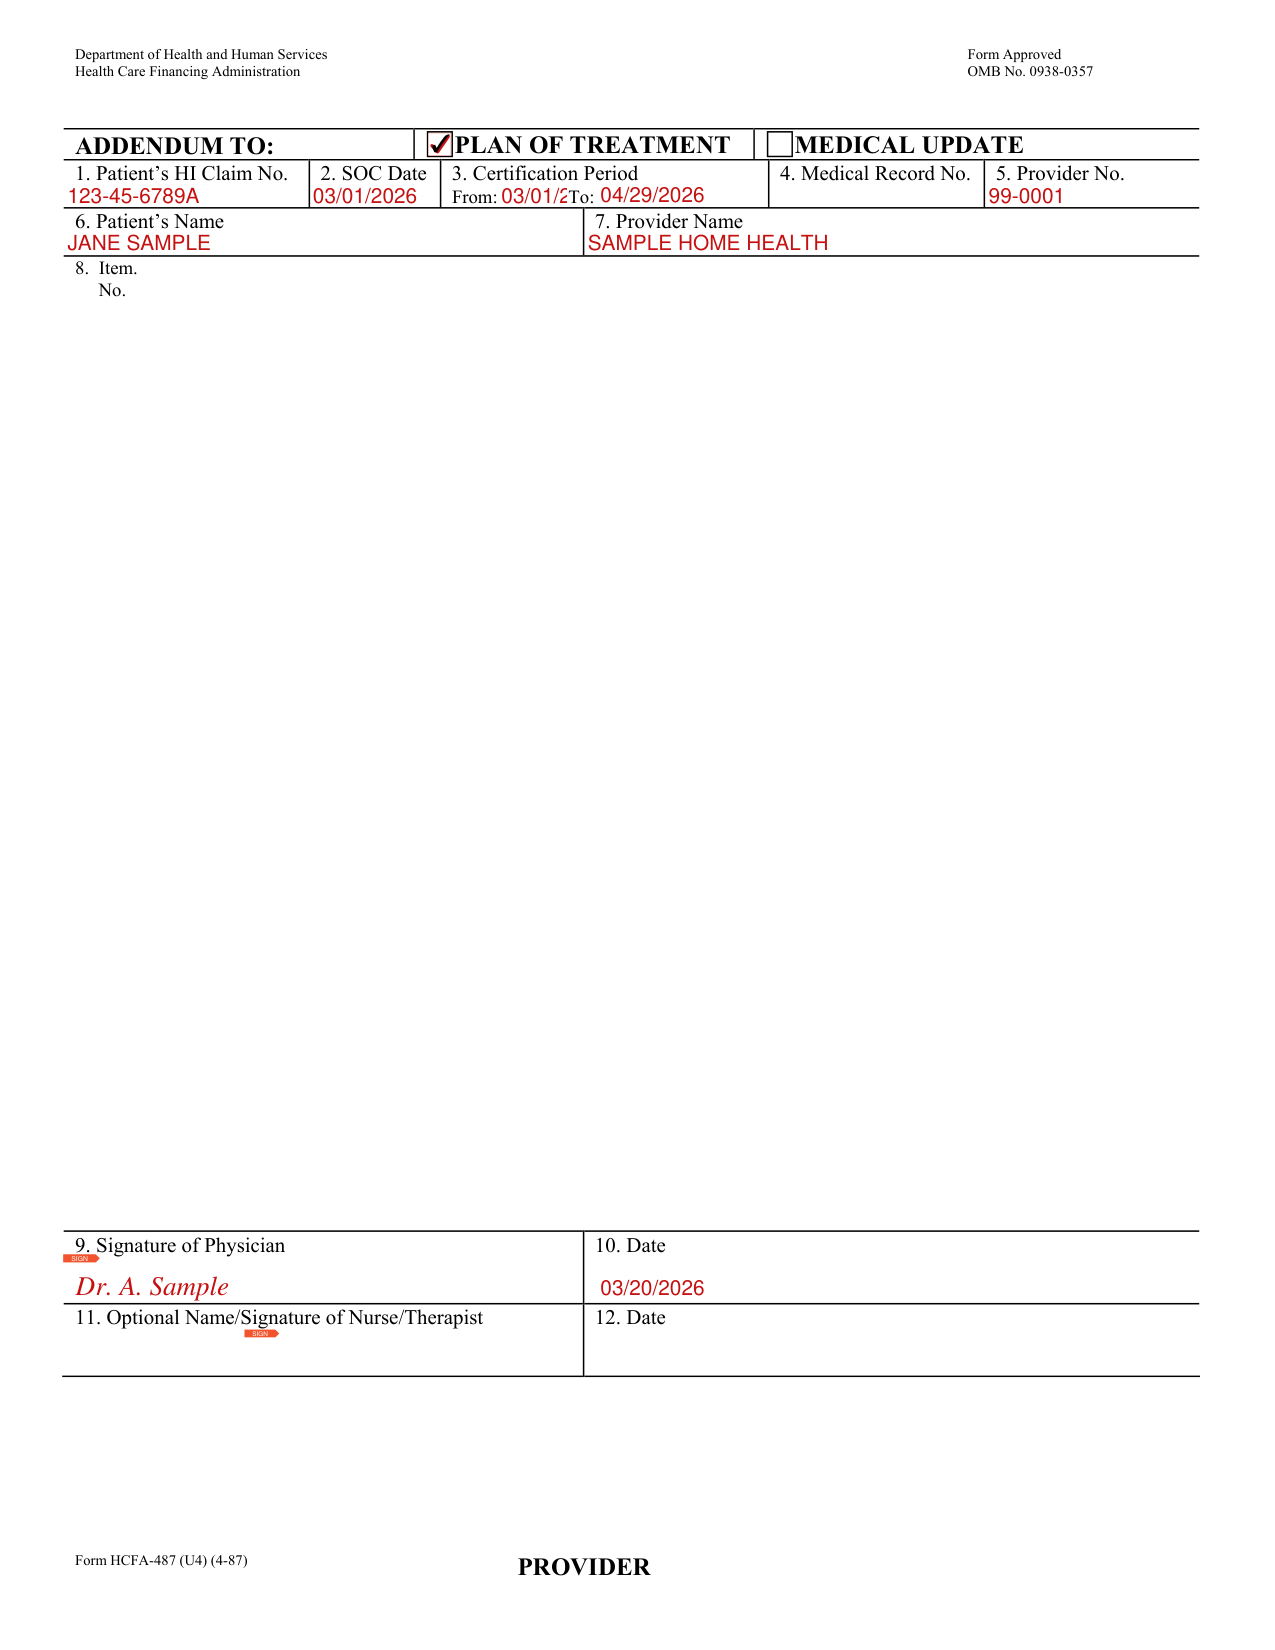
Form HCFA-487 example filled out, example: an addendum to the plan of treatment
A home health agency completes Form HCFA-487 for one patient. The addendum is to the plan of treatment, so Medical Update stays empty. The picture shows the filled form, and its names and figures are sample values.

How to fill out Form HCFA-487, box by box

Addendum to plan of treatment or medical update

Form HCFA-487 example filled out, addendum to plan of treatment or medical update

On the Health Care Financing Administration form, mark ADDENDUM TO: PLAN OF TREATMENT or MEDICAL UPDATE.

Claim No., SOC Date, Certification Period and Provider No.

Form HCFA-487 example filled out, claim No., SOC Date, Certification Period and Provider No.

Enter 1. Patient's HI Claim No., 2. SOC Date, 4. Medical Record No. and 5. Provider No.

Enter 3. Certification Period From and To.

Patient and provider names

Form HCFA-487 example filled out, patient and provider names

Enter 6. Patient's Name and 7. Provider Name, then 8. Item. No.

Signature of physician
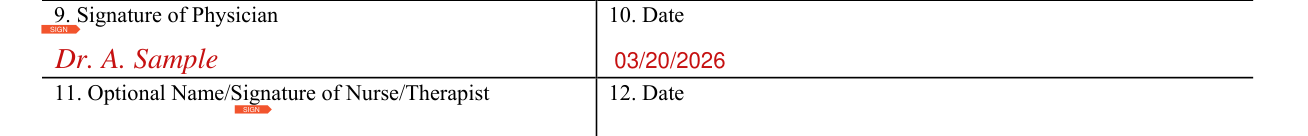
Form HCFA-487 example filled out, signature of physician

Under 9. Signature of Physician, the physician signs and enters 10. Date.

Optional name or signature of nurse or therapist

Form HCFA-487 example filled out, optional name or signature of nurse or therapist

Under 11. Optional Name/Signature of Nurse/Therapist, enter the name or signature and 12. Date.

Sources

[1] Form HCFA-487 (4-87), Addendum to Plan of Treatment / Medical Update, Health Care Financing Administration (the Official source link on this page).

Form HCFA-487 PDF Details

Form HCFA-487 (4-87), Form Approved OMB No. 0938-0357.

Patient items: Patient's HI Claim No, SOC Date, Certification Period From To, Medical Record No, Patient's Name.

Provider items: Provider No and Provider Name.

Item: Item No. 8.

Physician: Signature of Physician and Date.

Nurse or therapist: Optional Name/Signature of Nurse/Therapist and Date.

QuestionAnswer
Form NameForm HCFA-487
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out3 min
Edition(4-87)
Other namesForm HCFA-487, Form 487, HCFA 487
Official sourceForm HCFA-487 (4-87), Addendum to Plan of Treatment / Medical Update, Health Care Financing Administration