

Molina Healthcare HDO Application at a glance
What it is: The Molina Healthcare, Inc. Health Delivery Organization (HDO) Application is submitted to apply for initial credentialing or recredentialing with Molina Healthcare; approval of your credentialing does not constitute finalization/approval of your contract and network participation.
Who signs: The individual executing this Attestation is duly authorized and has the proper authority and proper authorization to execute this Attestation.
Complete a separate application for each of your locations if each location has had a separate state, CMS or accreditation survey.
Complete one application which will cover all your locations if your organization has had one state, CMS and/or accreditation survey that covered all your locations on the same date(s), or your organization is not accredited and not required to be surveyed by any state or federal organization as part of your licensure, registration and/or certification process.
What to bring and attach to Molina Healthcare HDO Application
These should accompany the completed application: current organizational or facility licenses/certifications/registrations, a copy of the letter verifying approval of CMS participation (if applicable), the current liability insurance face sheet, and W9 form(s) showing all federal Tax Identification Numbers (TINs) used by the organization/facility.
Only Page 1 of the W9 form is needed.
If your organization is not accredited by a body listed in Section 4 of this application and your organization is required to be certified by CMS or the State, a copy of the most recent CMS or State on-site survey results is also requested.
A filled-in Molina Healthcare HDO Application example: a clinic fills out Section 1 and the insurance section
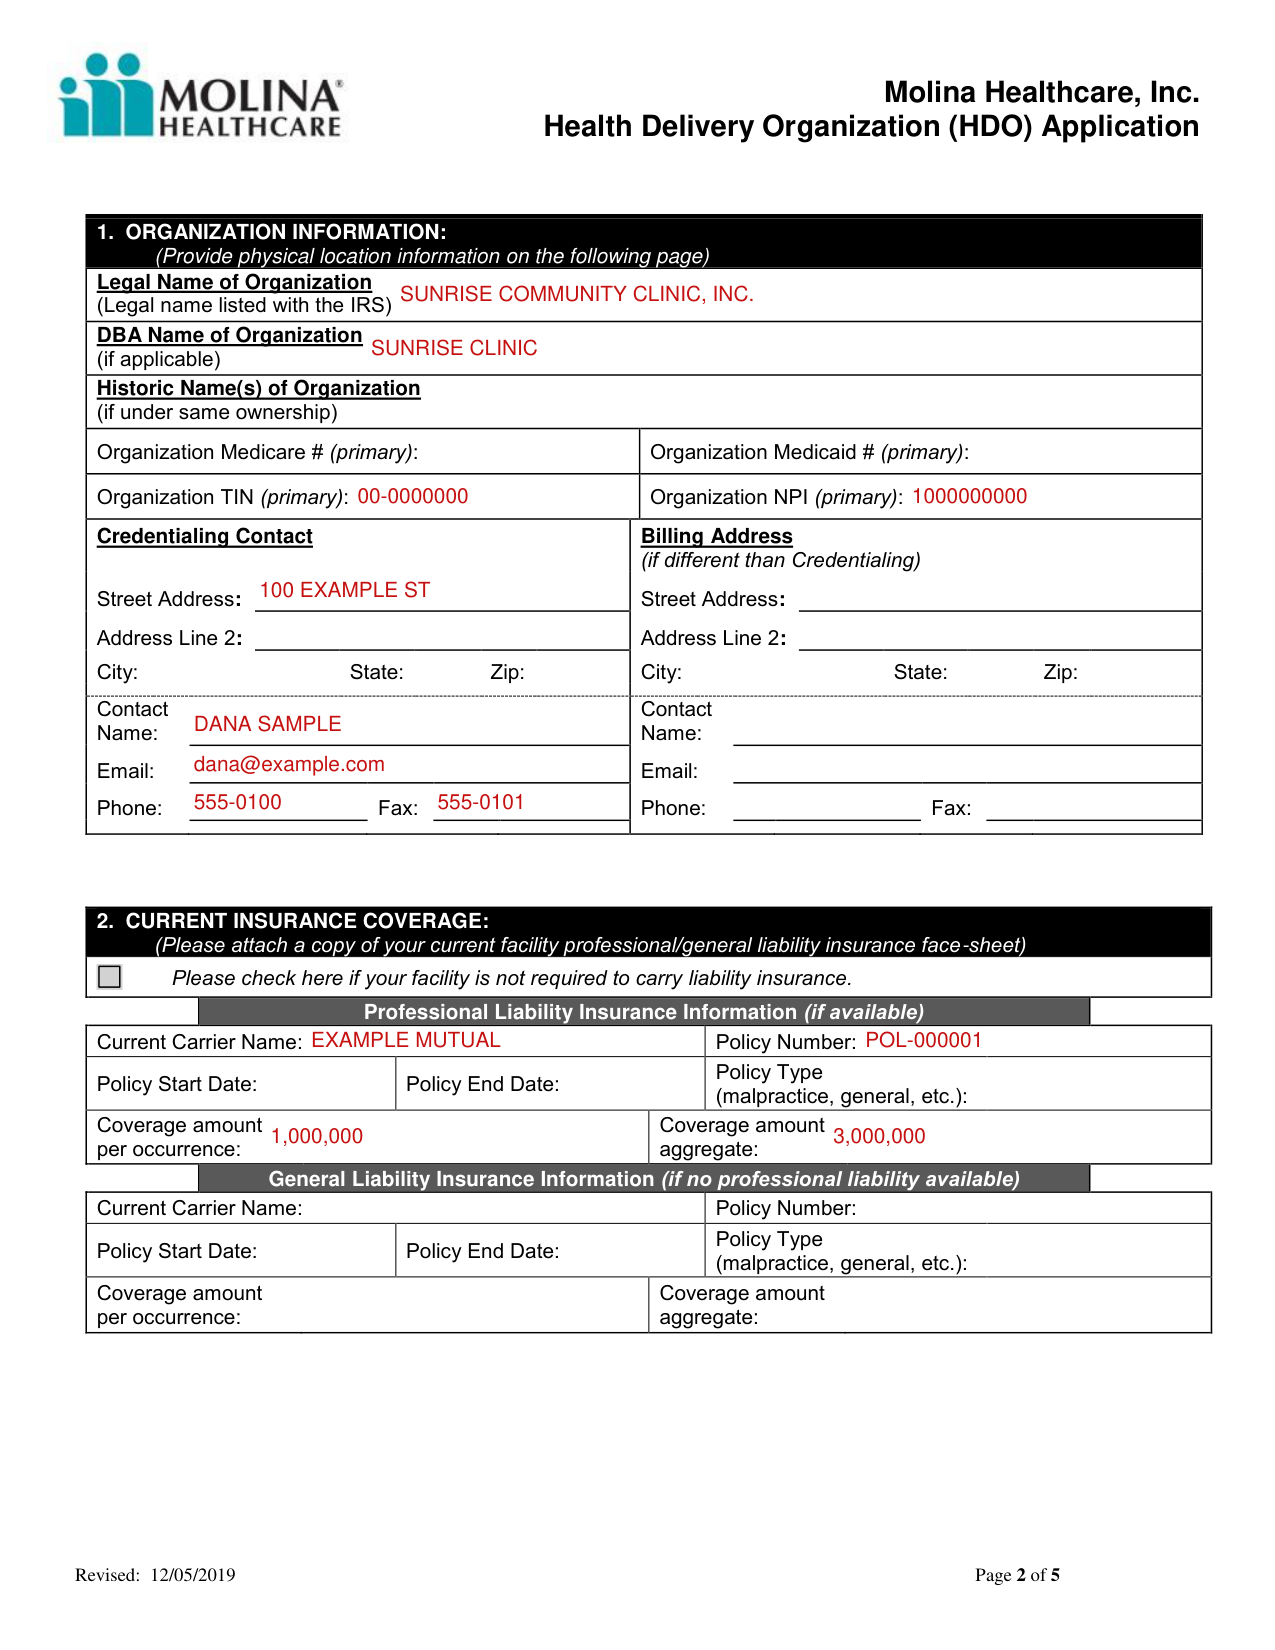
How to fill out Molina Healthcare HDO Application, box by box
Organization information

Under 1. ORGANIZATION INFORMATION, enter the Legal Name of Organization (Legal name listed with the IRS), the DBA Name of Organization (if applicable) and the Historic Name(s) of Organization (if under same ownership).
Enter the Organization TIN (primary) and the Organization NPI (primary).
Credentialing Contact

Under Credentialing Contact, enter the Street Address, Address Line 2, City, State, Zip, Contact Name, Email, Phone and Fax.
Billing Address (if different than Credentialing)

Under Billing Address (if different than Credentialing), enter the Street Address, Address Line 2, City, State, Zip, Contact Name, Email, Phone and Fax.
Professional and General Liability Insurance Information
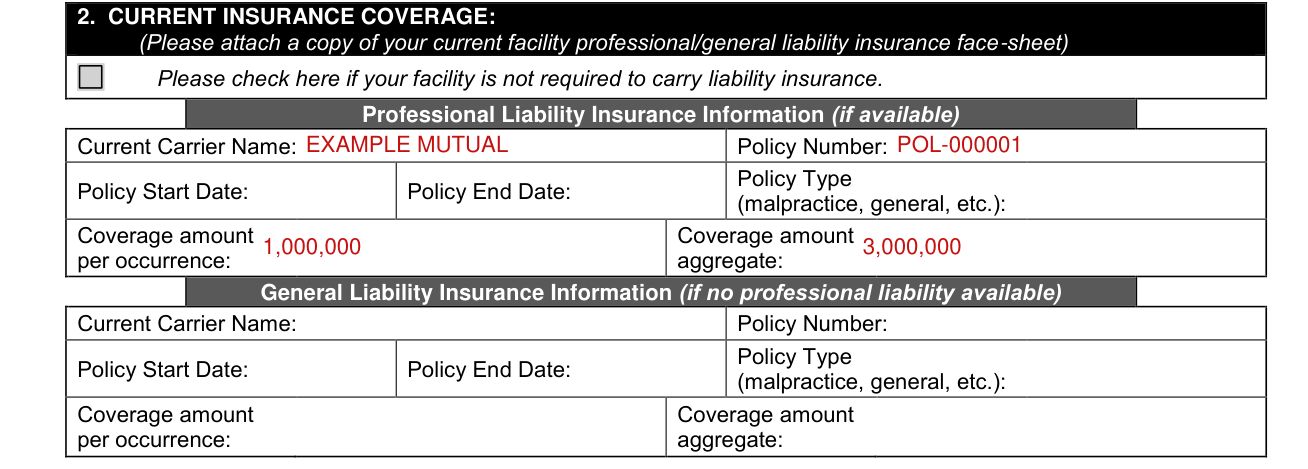
Under 2. CURRENT INSURANCE COVERAGE, attach a copy of your current facility professional/general liability insurance face sheet.
Under Professional Liability Insurance Information (if available), enter the Current Carrier Name, Policy Number, Policy Start Date, Policy End Date, Policy Type (malpractice, general, etc.), Coverage amount per occurrence and Coverage amount aggregate. Under General Liability Insurance Information (if no professional liability available), enter the Current Carrier Name, Policy Number, Policy Start Date, Policy End Date, Policy Type (malpractice, general, etc.), Coverage amount per occurrence and Coverage amount aggregate.
Facility not required to carry liability insurance

Check the box if your facility is not required to carry liability insurance.
More rules for Molina Healthcare HDO Application
Fill out this application completely with all sections answered. Do not use white-out on any part of the application. If there is NOT a checkbox in the section header to indicate why a section is not applicable, the section should be completed by all applicants.
Incomplete applications will be returned for completion prior to processing.
Complete the information for each practice location. Only include information for locations that you wish to be listed with Molina Healthcare.
Complete a copy of sections 3-4 of this application for every location where information differs between locations.
Under 3. PHYSICAL LOCATION INFORMATION, Is this location Medicare Certified? Yes No. Is this the primary address? Yes No.
Enter the Site-specific Medicare #, Site-specific Medicaid #, Site-specific TIN and Site-specific NPI.
Attach a copy of all Location State License(s) and/or State Registration(s). Check the box if this location is not required to be licensed, certified, or registered by a State agency.
Attach a copy of all Additional Location Credentials. Check the box if this location holds no additional licenses, certificates, registrations, etc.
Under 4. ACCREDITATION / CERTIFICATION, check all that apply.
Check the box if the State conducts routine surveys of your organization for license, registration, or clinical oversight.
Check the box if your organization is NOT accredited and NOT required to be surveyed by ANY organization.
Under Accreditation Organization, enter the Date of Last Survey. For (CMS) Medicare Certification, attach the most recent survey and acceptance letter.
Modifications Will Not Be Accepted on the ATTESTATION AND RELEASE OF INFORMATION FORM.
By signing, you acknowledge that any misstatements in or omissions from this application constitute denial or summary dismissal.
Common questions about Molina Healthcare HDO Application
Who signs it?
Under SIGN, enter the Signature, the Printed Name and the Date. A stamped signature is not acceptable.
Where do I file it?
Return this application and all attachments to the location specified on your cover letter.
What am I certifying when I sign?
By signing, you certify the information on this entire application is complete, accurate, and current.
Sources
[1] Molina Healthcare, Inc. Health Delivery Organization (HDO) Application (the served file, revised 12/05/2019; no issuer file found) (the Official source link on this page).
