

Application for Health Coverage & Help Paying Costs at a glance
What it is: Application for Health Coverage & Help Paying Costs: use this application to find out what coverage you qualify for.
Where and when to file: Mail your signed application to: Health Insurance Marketplace, Dept. of Health and Human Services, 465 Industrial Blvd., London, KY 40750-0001. Make a copy to keep, then send your complete, signed application to the address on page 8.
Use this application to apply for anyone in your household, even if you, your spouse, or your child already have health coverage.
If you're single, you may be able to use a short form. Visit HealthCare.gov.
What to bring and attach to Application for Health Coverage & Help Paying Costs
What you may need to apply: Social Security Numbers (SSNs) (or document numbers for any eligible immigrants who need coverage), employer and income information for everyone in your household (like from pay stubs, W-2 forms, or wage and tax statements), policy numbers for any current health insurance, and information about any job-related health insurance available to your household.
A filled-in Application for Health Coverage & Help Paying Costs example: the contact person fills out Step 1

How to fill out Application for Health Coverage & Help Paying Costs, box by box
Your name and home address
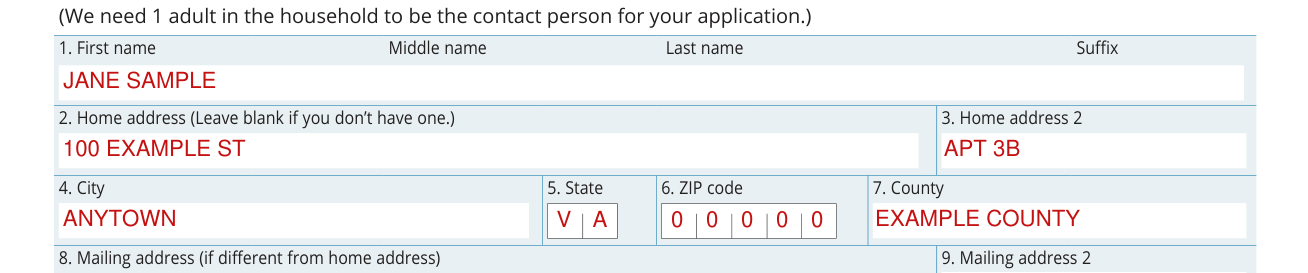
The contact person for your application is 1 adult in the household.
Print in capital letters using black or dark blue ink only.
Enter 1. First name, Middle name, Last name and Suffix; 2. Home address (Leave blank if you don't have one.); 3. Home address 2; 4. City; 5. State; 6. ZIP code; 7. County.
Mailing address
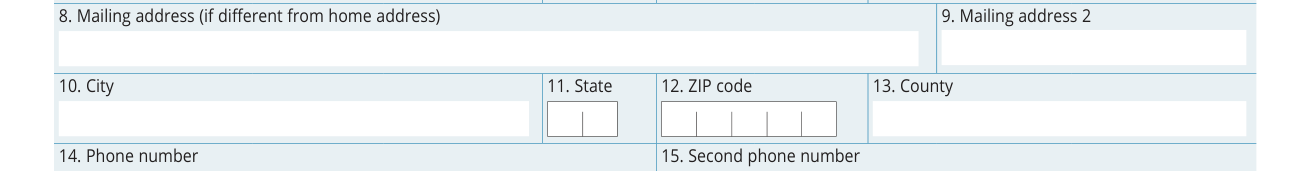
Enter 8. Mailing address (if different from home address); 9. Mailing address 2; 10. City; 11. State; 12. ZIP code; 13. County.
Phone number, email and language
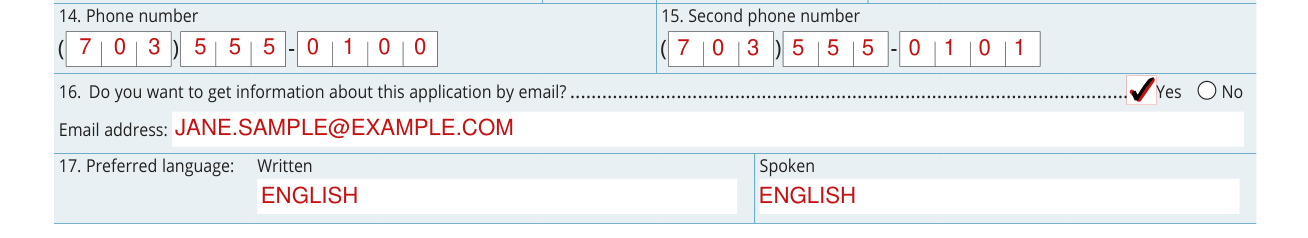
Enter 14. Phone number and 15. Second phone number.
16. Do you want to get information about this application by email? Yes or No. Enter your Email address.
17. Preferred language: Written and Spoken.
If your situation is different
Complete the Step 2 pages for each person in your household
Complete the Step 2 pages for each person in your household, even if the person has health coverage already. Start with yourself, then add other adults and children.
If you have more than 2 people in your household, you'll need to make a copy of the pages and attach them.
You don't need to provide immigration status or SSNs for household members who don't need health coverage.
You don't need to file taxes to get health coverage.
For adults who need coverage
Include these people even if they aren't applying for health coverage for themselves: any spouse; any child under age 21 they live with, including stepchildren; any other person on the same federal income tax return (including any children over age 21 who are claimed on a parent's tax return).
For children under age 21 who need coverage
Include these people even if they aren't applying for health coverage themselves: any parent (or stepparent) they live with; any sibling they live with; any child they live with, including stepchildren; any spouse they live with; any other person on the same federal income tax return.
Do you plan to file a federal income tax return NEXT YEAR?
You can still apply for coverage even if you don't file a federal income tax return. If yes, answer items a through c. If no, skip to item c.
a. Will you file jointly with a spouse? If yes, write name of spouse. b. Will you claim any dependents on your tax return? If yes, list name(s) of dependents. c. Will you be claimed as a dependent on someone's tax return? If yes, list the name of the tax filer: How are you related to the tax filer?
Current job & income information
If you're currently employed, start with item 20. Not employed: Skip to item 30. Self-employed: Skip to item 29.
Complete this question if your income changes during the year, like if you only work at a job for part of the year or get a benefit for certain months. If you don't expect changes to your monthly income, skip to the next person.
You or a household member are American Indian or Alaska Native
Complete this appendix if you or a household member are American Indian or Alaska Native and are applying for coverage. Submit this with your “Application for Health Coverage & Help Paying Costs.”
Anyone listed on this application is offered health coverage from a job
Is anyone listed on this application offered health coverage from a job? Check yes even if the coverage is from someone else's job, like a parent or spouse, even if they don't accept the coverage. Check no if the only coverage offered is COBRA.
You DON'T need to answer these questions unless someone in the household is eligible for health coverage from a job, even if they don't accept the coverage. You also don't need to answer these questions if the only coverage someone is offered is COBRA.
PERSON 1 should sign this application
If you're an authorized representative, you may sign here as long as PERSON 1 signed Appendix C.
Penalties under federal law for false information
I know that I may be subject to penalties under federal law if I intentionally provide false or untrue information.
Tell the Health Insurance Marketplace within 30 days if anything changes
I know that I must tell the Health Insurance Marketplace® within 30 days if anything changes (and is different than) what I wrote on this application.
Outside of Open Enrollment
If you're signing this application outside of Open Enrollment (November 1-January 15), make sure you review Appendix D (“Questions about life changes”).
Help with Completing this Application
For certified application counselors, navigators, agents, and brokers only: complete this section if you're a certified application counselor, navigator, agent, or broker filling out this application for somebody else.
If you're a legally appointed representative for someone on this application, submit proof with the application.
Common questions about Application for Health Coverage & Help Paying Costs
Where do I file it?
Mail your signed application to: Health Insurance Marketplace, Dept. of Health and Human Services, 465 Industrial Blvd., London, KY 40750-0001.
Sources
[1] Application for Health Coverage & Help Paying Costs (OMB No. 0938-1191, expires 09/30/2027), Centers for Medicare & Medicaid Services (the Official source link on this page).
