

Health Risk Assessment Form at a glance
What it is: This is the Health Risk Assessment Form.
Where and when to file: Mail this back in the white postage-paid envelope.
Now that you are a member of Passport Health Plan, please fill out this form. It will help Passport Health Plan see how Passport Health Plan can best serve you with benefits and special programs. Your answers on this form will be kept private. They will not affect your benefits in any way. If you need help filling out this form, please call 1-877-903-0082. TDD/TTY users may call 1-800-691-5566.
A filled-in Health Risk Assessment Form example: a member fills in her details

How to fill out Health Risk Assessment Form, box by box
Your name, address and plan ID number
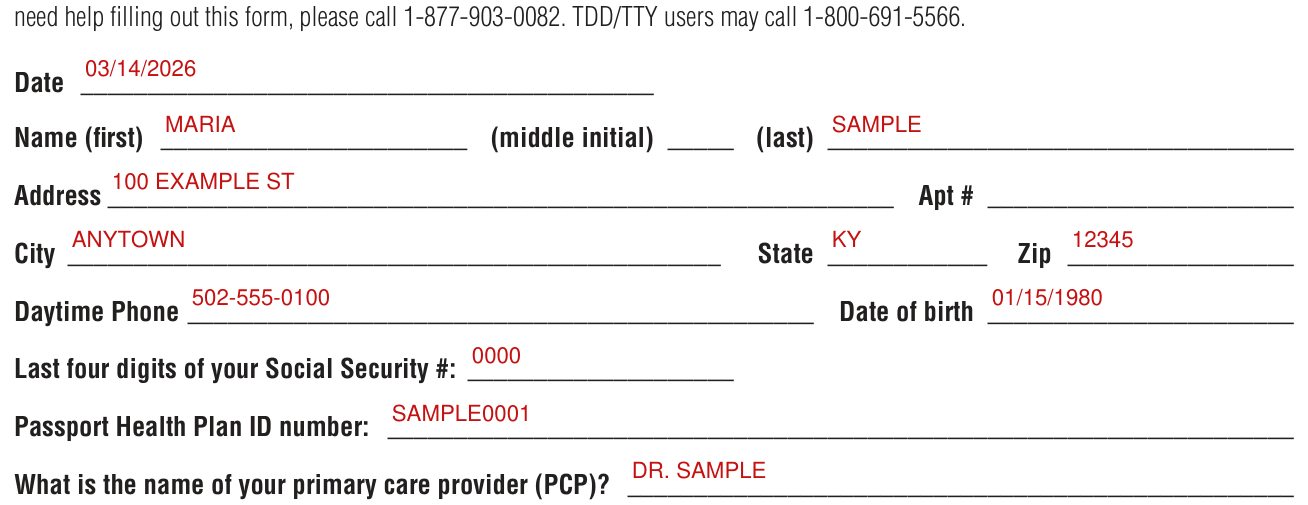
Enter the Date, Name (first), (middle initial), (last), Address, Apt #, City, State, Zip, Daytime Phone and Date of birth. Enter the last four digits of your Social Security # and your Passport Health Plan ID number.
Your primary care provider

What is the name of your primary care provider (PCP)? What is your PCP's phone number? Do you need help choosing a PCP or making an appointment with your PCP? Mark Yes or No.
If your situation is different
Language, gender, race and ethnicity
Under your preferred language, mark one of English, Somali, Spanish, Arabic, Vietnamese, Bosnian, Russian, Swahili, French, Mandarin, Sign or Other.
Mark Male or Female for your gender.
Race and ethnicity are optional. For race, mark Asian, Black or African American, Native Hawaiian/ Pacific Islander, White, American Indian/ Alaskian Native, Other or Declined to Answer. For ethnicity, mark Hispanic, Non-Hispanic, Other or Declined to Answer.
Pregnancy and your OB provider
Are you pregnant? Mark Yes or No. If yes, enter the name of your OB provider (doctor who cares for you during pregnancy) and your OB's phone number. If you are pregnant and do not have an OB provider, do you need help choosing one? Mark Yes or No.
Your last physical exam, weight and height
Enter when your last physical exam was, and your current weight and your current height.
Section One: your health in general and your activities
In Section One: Physical and Behavioral Health, circle one number for your health in general: 1 - Excellent, 2 - Very Good, 3 - Good, 4 - Fair or 5 - Poor.
The following are activities you might do during a normal day. Circle one of the numbers to describe how much your health limits you in any of these activities: 1 - Yes, limited a lot, 2 - Yes, limited a little or 3 - No, not limited. Circle one number on each line: 2. Moderate activities, such as moving a table, pushing a vacuum cleaner, bowling, or playing golf. 3. Climbing several flights of stairs.
8. During the past 4 weeks, how much did pain get in the way of your normal work (including both work outside the home and housework)? Circle one number: 1 - Not at all, 2 - Slightly, 3 - Moderately, 4 - Quite a bit or 5 - Extremely.
Section One: problems in the past 4 weeks
During the past 4 weeks, have you had any of the following problems with your work or daily activities as a result of your physical health? Mark Yes or No: 4. Could not get done as much as I would like. 5. Was limited in the kind of work or other activities.
During the past 4 weeks, have you had any of the following problems with your work or daily activities as a result of any emotional problems (such as feeling depressed or anxious)? Mark Yes or No: 7. Did not do work or other activities as carefully as usual.
These questions are about how you feel and how things have been with you during the past 4 weeks. For each question, please give the one answer that comes closest to the way you have been feeling. Circle one number on each line: 1 - All of the time, 2 - Most of the time, 3 - A good bit of the time, 4 - Some, 5 - A little of the time or 6 - None of the time. 9. Have you felt calm and peaceful? 10. Did you have a lot of energy? 11. Have you felt sad or down? 12. How often has your physical health or emotional problems gotten in the way of your social activities (such as visiting with friends, relatives, etc.)?
Section One: behavioral health and conditions
Mark Yes or No for each. 13. Have you seen a psychiatrist or any other mental/emotional health provider previously? 14. Have you ever been in a psychiatric facility? 15. Are you on any behavioral health medicines? If yes, what are they? 16. Have you ever been treated for substance abuse (alcohol, drugs)? 17. Do you need help getting a counselor, therapist, or psychiatrist? 18. Do you need help getting food, clothing or housing?
19. Has the doctor EVER told you that you had any of the following conditions? Check YES or NO for each line: a. Congestive heart failure; b. Chronic lung disease (including bronchitis, emphysema or COPD); c. Diabetes Mellitus (sugar diabetes); d. Asthma; e. Sickle Cell; f. HIV/AIDS; g. Hypertension (high blood pressure); h. Heart attack; i. Stroke; j. End stage kidney disease requiring dialysis; k. Cancer; l. Autoimmune disorders (rheumatoid arthritis, lupus, multiple sclerosis); m. Dementia; n. End stage liver disease; o. Blood disorders, clotting disorders; p. Neurologic disorders; q. Cardiovascular disorders; r. Chronic mental health conditions; s. Smoker's cough; t. Chronic kidney disease. 20. Mark Yes or No: Compared to one year ago, my health in general is much worse.
Section Two: Preventive Health
In Section Two: Preventive Health: 1. How would you describe your smoking habits? 1 - Still smoke, 2 - Used to smoke or 3 - Never smoked. 2. How long has it been since your last tetanus shot? 1 - Within the last year, 2 - Within the last 10 years, 3 - More than 10 years ago or 4 - Do not know. 3. How long has it been since your last flu shot? 1 - Within the last 6 months, 2 - Within the last year, 3 - Do not know or 4 - Never.
If your age is 50 or over, 4. How long has it been since your last colorectal exam (including colonoscopy, stool blood test)? If your age is 18 or over, 5. How long has it been since your last dilated retinal exam (eye exam by an eye specialist)? Men Only: 8. How long has it been since you had a rectal or prostate exam? 1 - less than 1 year ago, 2 - 1 year ago, 3 - 2 years ago, 4 - 3 or more years ago or 5 - Never.
Women Only: If your age is 40 or over, 6. How long has it been since your last mammogram (a test for breast cancer)? 1 - Less than 1 year ago, 2 - 1 year ago, 3 - 2 years ago, 4 - 3 or more years ago, 5 - Never or 6 - I have had both breasts removed. If your age is 21 and over, 7. How long has it been since you had a Pap smear (test for cervical cancer)? 1 - less than 1 year ago, 2 - 1 year ago, 3 - 2 years ago, 4 - 3 or more years ago, 5 - Never or 6 - I have had a hysterectomy.
Mailing the form back
Mail this back to Passport Health Plan Attn: Health Risk Assessment 5100 Commerce Crossings Drive Louisville, KY 40229.
Sources
[1] Health Risk Assessment Form, Passport Health Plan (the Official source link on this page).
