

Form LIC 503 at a glance
What it is: LIC 503 is the Health Screening Report - Facility Personnel of the California Department of Social Services.
Who signs: Signature of Applicant/Licensee or Employee, and Health Screening by: (Original Signature)
All personnel, including applicant, licensee or employed staff of Residential Care Facilities for the Elderly, Community Care Facilities, Residential Care Facilities for the Chronically Ill, or Child Care Facilities must demonstrate that their health condition allows them to perform the type of work required.
This health appraisal is to be completed by or under the direction of a physician.
A filled-in Form LIC 503 example: a child care employee's health screening

How to fill out Form LIC 503, box by box
Facility Name and Facility Address
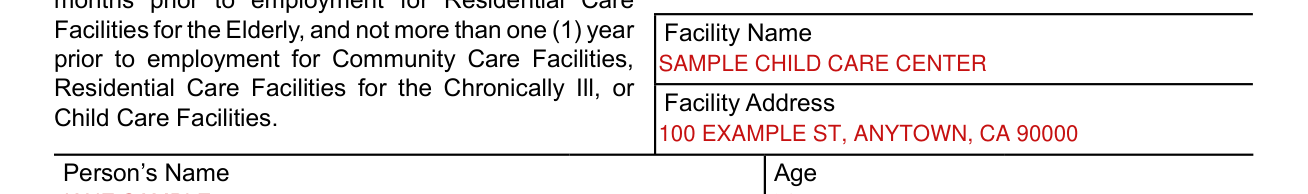
Enter the Facility Name and the Facility Address.
Person's Name, Age and position

Enter the Person's Name, Age, Position Title, Type of Facility, Workdays per Week and Work Hours per Day.
Duty Statement

Enter the Duty Statement.
Types of persons served

Under TYPES OF PERSONS SERVED, check the appropriate items: Infants, Adults, Persons with Developmental Disabilities, Persons with Physical Disabilities, Children, Elderly, Persons with Mental Health Conditions, Persons with Substance Use Disorder, or Other (specify):
Authorization for release of medical information

Sign on Signature of Applicant/Licensee or Employee, then enter the Address and the Date, under AUTHORIZATION FOR RELEASE OF MEDICAL INFORMATION: I HEREBY AUTHORIZE THE RELEASE OF MEDICAL INFORMATION CONTAINED IN THIS REPORT.
Evaluation of general health and of ability to perform work

Complete the Evaluation of general health, the Evaluation of ability to perform work described in the duty statement, and the note of any health condition that would create a hazard to persons in care or other personnel.
Date of T.B. Test

Enter the Date of T.B. Test, check Positive or Negative, and enter the Action Taken (If Positive).
Health Screening by
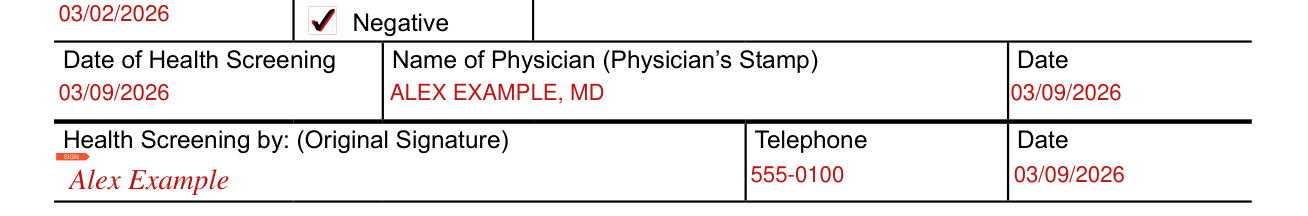
Enter the Date of Health Screening and the Name of Physician (Physician's Stamp), then enter the Telephone and the Date.
Signature of Applicant/Licensee or Employee, and Health Screening by: (Original Signature)
More rules for Form LIC 503
Personnel in Residential Care Facilities for the Elderly, Community Care Facilities, Residential Care Facilities for the Chronically Ill, or Child Care Facilities shall be free from communicable disease, and capable of performing assigned tasks.
Common questions about Form LIC 503
Is there a deadline?
A health screening, by or under the direction of a physician must have been performed within seven (7) days after employment or not more than six (6) months prior to employment for Residential Care Facilities for the Elderly, and not more than one (1) year prior to employment for Community Care Facilities, Residential Care Facilities for the Chronically Ill, or Child Care Facilities.
Sources
[1] Form LIC 503 (6/24), Health Screening Report - Facility Personnel, California Department of Social Services (the Official source link on this page).
