

Authorization to Release Copies of Medical Records at a glance
What it is: The Authorization to Release Copies of Medical Records of Hoag Memorial Hospital Presbyterian authorizes the disclosure and/or use of individually identifiable health information.
Who signs: If signed by other than patient, indicate legal relationship to patient.
A filled-in Authorization to Release Copies of Medical Records example: a patient asks for two records on paper

How to fill out Authorization to Release Copies of Medical Records, box by box
Patient Name and Date of Birth
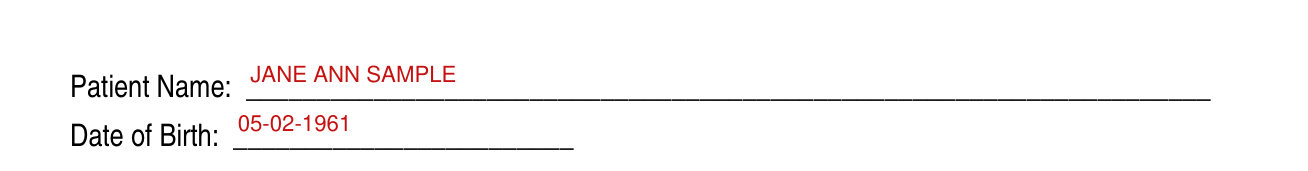
Write the Patient Name and the Date of Birth.
Who receives the information

List the person/organization authorized to receive this information: Name/Organization, Address, City, State, Zip and Phone.
Requested Media

Under Requested Media, mark Mail, Patient will pick up or Family member will pick up; for a family member, write the Name and the Phone. Mark Paper, Secured Email (with Secured Email), CD or MyChart (services on or after 4/28/18).
This authorization applies to the following

Mark All health information pertaining to any medical history, mental or physical condition and treatment received, OR the box for Only the following.
Write the Date of Service and mark ED Records, History & Physical, Consults, Operative Report, Discharge Summary, MD Progress Notes, MD Orders, Nurse's Notes, EKG, EMG, EEG, Radiology Reports, Anesthesia Records, Lab/Pathology Reports, Radiology Film/CD (with its Type) or Other.
I specifically authorize release of the following information

Mark Alcohol/drug treatment information, HIV Test Results or Mental Health Treatment Information (check as appropriate). A separate authorization is required to authorize disclosure or use of psychotherapy notes.
Purpose for use/disclosure

Under Purpose for use/disclosure, mark Patient Request, Further Medical Care, Insurance OR Other and write the Other purpose.
Expiration

Write the date in This authorization expires (insert date).
Signature

After This authorization expires (insert date), sign on the Signature line [Patient/Legal Representative] and write the Date and the Time (AM/PM).
If signed by other than patient, write the Print Name (Legal Representative).
More rules for Authorization to Release Copies of Medical Records
Failure to provide all information requested may invalidate this authorization. You may refuse to sign this authorization.
Your refusal will not affect your ability to obtain treatment or payment or eligibility for benefits. You may revoke this authorization at any time.
A revocation must be in writing, signed by you or on your behalf, and delivered to Hoag Hospital, Health Information Department, One Hoag Drive, Newport Beach, CA 92658.
A revocation will be effective upon receipt, but will not be effective to the extent that the requestor or others have acted in reliance on this authorization. You have a right to receive a copy of this authorization. Information disclosed pursuant to this authorization could be re-disclosed by the recipient and might no longer be protected by federal confidentiality law (HIPAA). However, California law prohibits the person receiving the health information from making further disclosure of it unless another authorization for such disclosure is obtained or unless such disclosure is specifically required or permitted by law. You may inspect or obtain a copy of the health information you are being asked to use or disclose.
Sources
[1] Hoag Memorial Hospital Presbyterian, Authorization to Release Copies of Medical Records, Rev 01/29 (the served file; no issuer file found) (the Official source link on this page).