Hospital Discharge Forms Download PDF Details

The Hospital Discharge Summary Form serves as a critical component in the transition of care from a hospital setting to the next stage of recovery for a patient. This comprehensive document captures essential details ranging from the patient's personal information, such as their name, identification number, and primary care provider, to more intricate aspects of their hospital stay, including the dates of service, attending physician, and specific medical group or facility handling their treatment. Before discharge, the form meticulously outlines the elements that must be addressed, including a physician’s note indicating readiness for discharge, a detailed discharge plan that has been discussed with both the attending provider and the patient or family, and any therapy notes or other pertinent information. Significantly, it delves into applicable Medicare coverage policies, driving attention towards the necessity of distinguishing services that are medically necessary and those that could be administered in a different setting, as per the regulations. The form encourages the use of plain language to articulate the patient's medical condition, treatments received, and reasons for the cessation of hospital services, ensuring clarity and comprehensibility. It concludes with sections for the detailed capture of the current medical condition, proposed follow-up care, and the formal completion of the form by the relevant healthcare professional. Through its structured format, the Hospital Discharge Summary Form plays a pivotal role in ensuring a seamless and informed transition for patients from inpatient care to their next phase of recovery or care setting.

QuestionAnswer
Form NameHospital Discharge Forms Download
Form Length2 pages
Fillable?No
Fillable fields0
Avg. time to fill out30 sec
Other names Fillable Online www5 esc13 Speaker Proposal Form - www5 ...

How to Fill Out Hospital Discharge Summary Form

Hospital Discharge Summary Form at a glance

What it is: Hospital Discharge Summary Form: complete this form for all hospital discharges.

Where and when to file: Securely email completed form to TMP_Appeals_Requests@tufts-health.com.

A filled-in Hospital Discharge Summary Form example: a case manager reports a discharge

Hospital Discharge Summary Form example filled out, example: a case manager reports a discharge
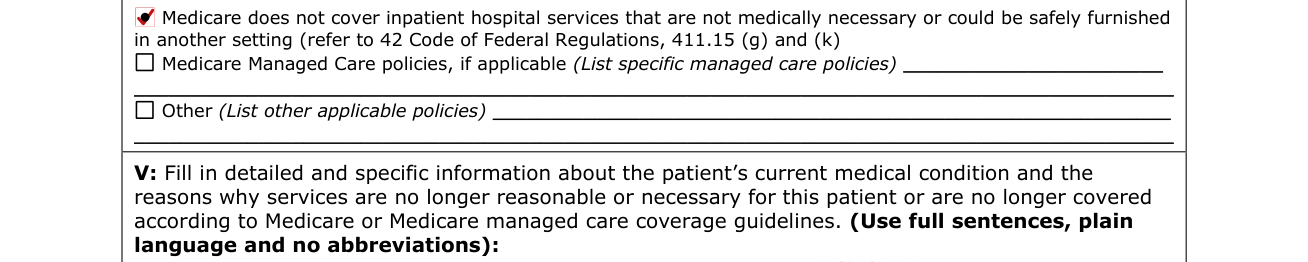
Dana Sample, a case manager, fills out the Hospital Discharge Summary Form. The member Jamie Sample leaves the facility, so Date Services should end holds one date. The picture shows page 1, and none of its entries is real. Dana selects the first Medicare coverage policy, so Medicare Managed Care policies and Other (List other applicable policies) stay empty. Nothing goes in Other under III because every element listed there fits the printed choices, and the later lines under V are left blank because each entry fits on its first line.

How to fill out Hospital Discharge Summary Form, box by box

I: Member name and facility

Hospital Discharge Summary Form example filled out, i: Member name and facility

Under I, enter the Member name, I.D.#, CM/DCM name, Phone #, Fax #, PCP name, Medical group/IPA #, Facility name and Attending physician.

II: Date Services should end

Hospital Discharge Summary Form example filled out, iI: Date Services should end

Under II, enter the Date Services should end.

III: Elements that need to be put in place prior to discharge

Hospital Discharge Summary Form example filled out, iII: Elements that need to be put in place prior to discharge

Under III, verify that the following information is documented in the record, if applicable: Physician note reflecting readiness for discharge, Discharge plan discussed with attending provider, Discharge plan discussed with member/family, Description of discharge plan in place, Therapy notes (if applicable) and Other (please be specific).

IV: Applicable Medicare coverage policies
Hospital Discharge Summary Form example filled out, iV: Applicable Medicare coverage policies

Under IV, please select one: Medicare does not cover inpatient hospital services that are not medically necessary or could be safely furnished in another setting; Medicare Managed Care policies, if applicable (List specific managed care policies); or Other (List other applicable policies).

V: The patient's current medical condition
Hospital Discharge Summary Form example filled out, v: The patient's current medical condition

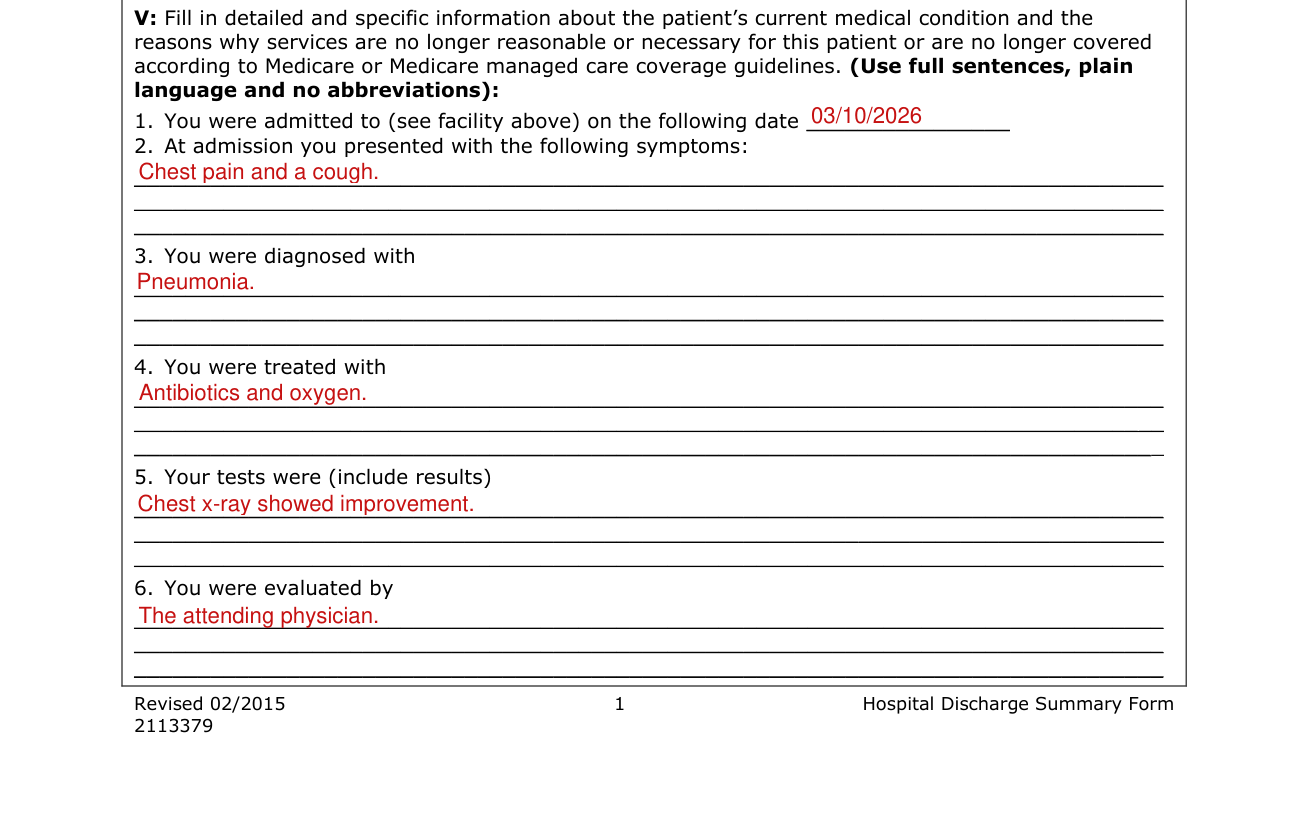
Under V, fill in detailed and specific information about the patient's current medical condition and the reasons why services are no longer reasonable or necessary for this patient or are no longer covered according to Medicare or Medicare managed care coverage guidelines. Use full sentences, plain language and no abbreviations.

In V, 1 and 2, enter the date admitted to the facility and the symptoms presented with at admission.

In V, 3 to 6, enter what the diagnosis was, what was treated with, the tests (include results) and who the evaluation was by.

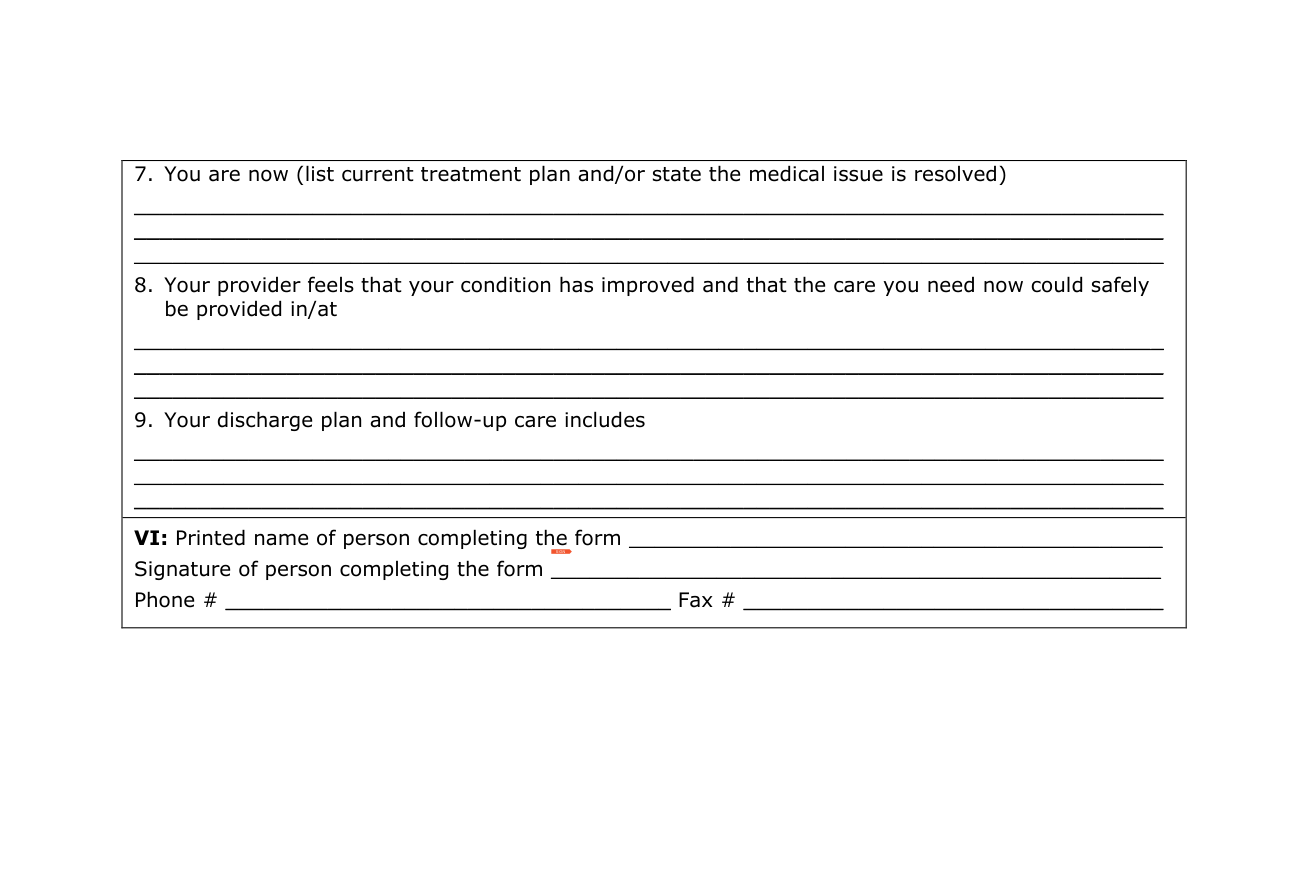
In V, 7, list the current treatment plan and/or state the medical issue is resolved.

In V, 8, enter where the care needed now could safely be provided, when the provider feels that the condition has improved.

In V, 9, enter what the discharge plan and follow-up care includes.

VI: Person completing the form
Hospital Discharge Summary Form example filled out, vI: Person completing the form

Under VI, enter the Printed name of person completing the form, sign on the Signature of person completing the form line, and enter the Phone # and Fax #.

Sources

[1] Hospital Discharge Summary Form, Revised 02/2015, Tufts Health Plan (the Official source link on this page).

Please rate Hospital Discharge Forms Download

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .