

Form NS-9934 at a glance
What it is: Form NS-9934 (08-21) is the Authorization for Use or Disclosure of Patient Health Information to a Third-Party Recipient.
Who signs: Enter the Date and sign in Signature. If personal representative, print name/relationship.
A filled-in Form NS-9934 example: a patient authorizes records for a lawyer
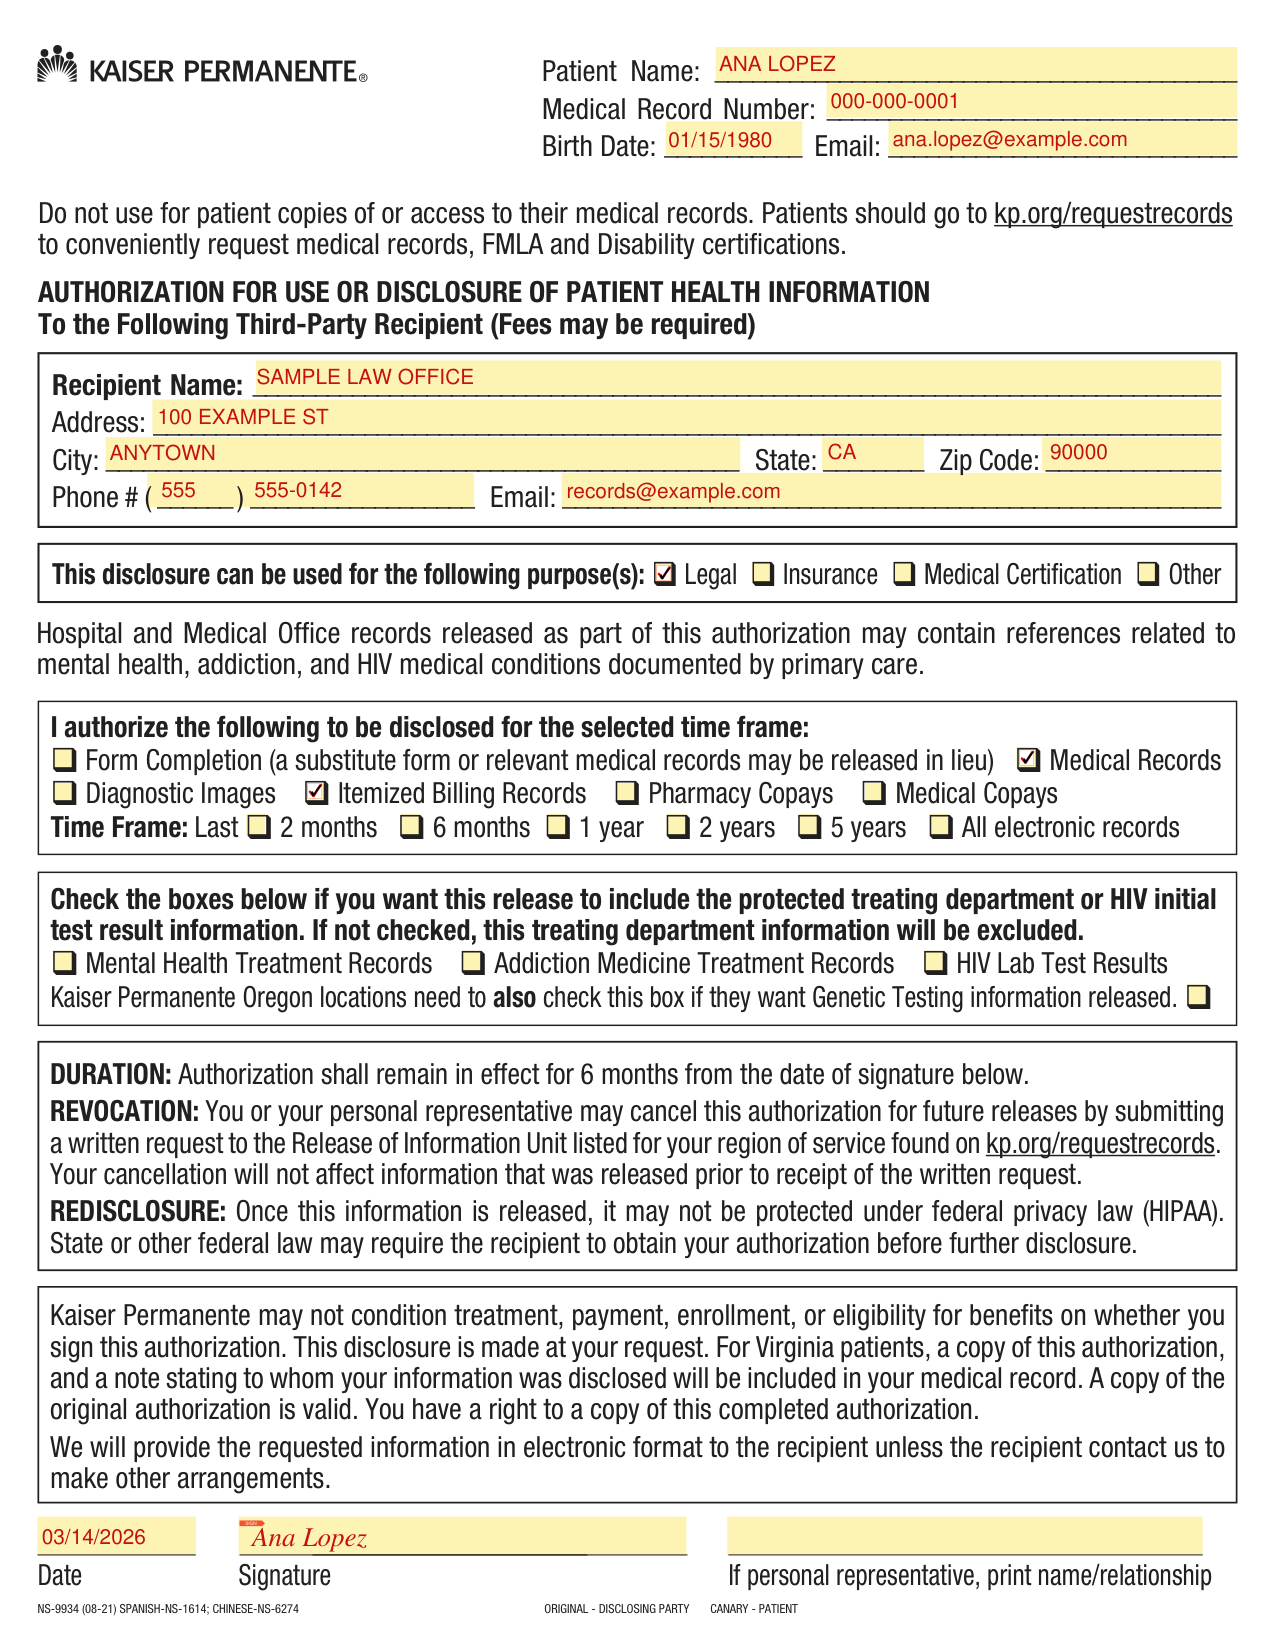
How to fill out Form NS-9934, box by box
Patient Name, Medical Record Number, Birth Date and Email

Fill in Patient Name, Medical Record Number, Birth Date and Email.
To the Following Third-Party Recipient
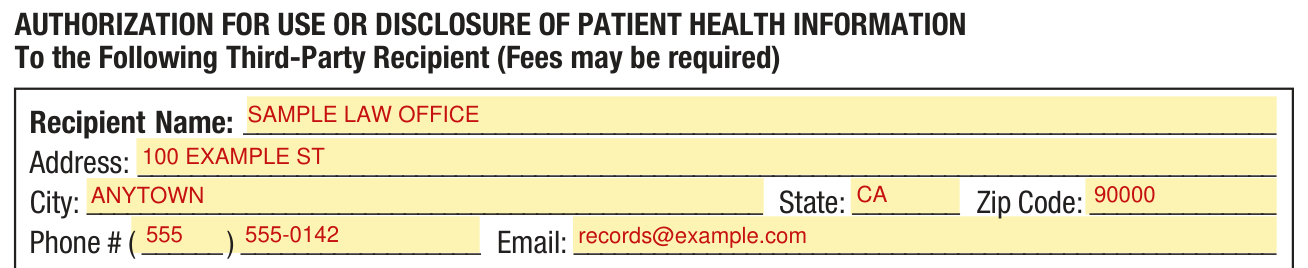
For the Third-Party Recipient (Fees may be required), fill in Recipient Name, Address, City, State, Zip Code, Phone # and Email.
This disclosure can be used for the following purpose(s)

For the purpose(s) of this disclosure, check Legal, Insurance, Medical Certification or Other.
I authorize the following to be disclosed for the selected time frame
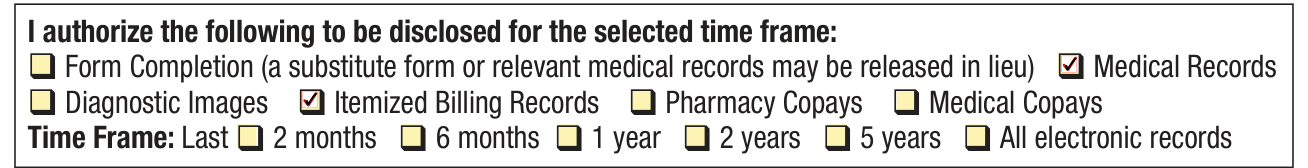
To authorize disclosure for the selected time frame, check Form Completion (a substitute form or relevant medical records may be released in lieu), Medical Records, Diagnostic Images, Itemized Billing Records, Pharmacy Copays or Medical Copays. Time Frame: Last 2 months, 6 months, 1 year, 2 years, 5 years or All electronic records.
Check the boxes if you want this release to include the protected treating department or HIV initial test result information

Check the boxes if you want this release to include the protected treating department or HIV initial test result information: Mental Health Treatment Records, Addiction Medicine Treatment Records or HIV Lab Test Results. If not checked, this treating department information will be excluded. Kaiser Permanente Oregon locations need to also check the Oregon box if they want Genetic Testing information released.
Hospital and Medical Office records released as part of this authorization may contain references related to mental health, addiction, and HIV medical conditions documented by primary care.
Sign: Date, Signature and personal representative

Enter the Date and sign in Signature. If personal representative, print name/relationship.
More rules for Form NS-9934
Instructions: 1) Complete the patient identification information on the top right-hand corner 2) Complete all required information for the recipient including a valid email address 3) Check the box for purpose of disclosure 4) Check the box(es) for the type of information to be disclosed and also check the box for a timeframe 5) If you want specially protected information to be included, check the appropriate box(es) 6) Enter the date you are signing the authorization 7) Sign the form 8) If you are a personal representative, print your name and relationship.
DURATION: Authorization shall remain in effect for 6 months from the date of signature. REVOCATION: You or your personal representative may cancel this authorization for future releases by submitting a written request to the Release of Information Unit listed for your region of service found on kp.org/requestrecords. Your cancellation will not affect information that was released prior to receipt of the written request. REDISCLOSURE: Once this information is released, it may not be protected under federal privacy law (HIPAA). State or other federal law may require the recipient to obtain your authorization before further disclosure.
Kaiser Permanente may not condition treatment, payment, enrollment, or eligibility for benefits on whether you sign this authorization. This disclosure is made at your request. For Virginia patients, a copy of this authorization, and a note stating to whom your information was disclosed will be included in your medical record. A copy of the original authorization is valid. You have a right to a copy of this completed authorization. Kaiser Permanente will provide the requested information in electronic format to the recipient unless the recipient contact Kaiser Permanente to make other arrangements.
Common questions about Form NS-9934
Where do I file it?
9) Submit this form to the third party you are authorizing to obtain records 10) Keep a copy for your records “Kaiser Permanente” means both your insurance company (a Kaiser Permanente health plan) and your doctors (a Permanente medical or dental group).
When is this form not the right one?
Do not use for patient copies of or access to their medical records. Patients should go to kp.org/requestrecords to conveniently request medical records, FMLA and Disability certifications.
Sources
[1] Form NS-9934 (08-21), Authorization for Use or Disclosure of Patient Health Information, Kaiser Permanente (the Official source link on this page).
