
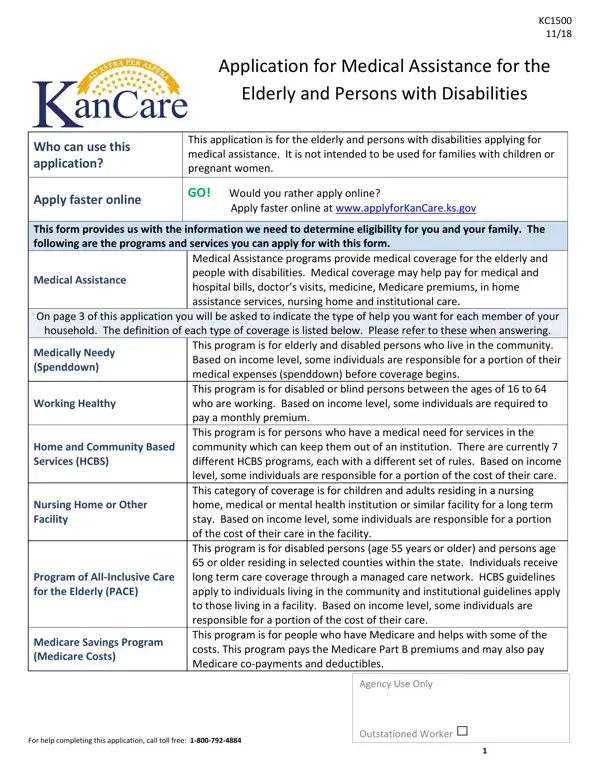

Elderly and Persons with Disabilities Medical Assistance Application (KC-1500) at a glance
What it is: This is the Elderly and Persons with Disabilities Medical Assistance Application.
Who signs: The primary applicant must sign here.
Where and when to file: Mail your completed and signed application to KanCare Clearinghouse, P.O. Box 3599, Topeka, KS 66601-9738, or fax it to 1-844-264-6285.
A filled-in Elderly and Persons with Disabilities Medical Assistance Application (KC-1500) example: a retired woman fills out Part A
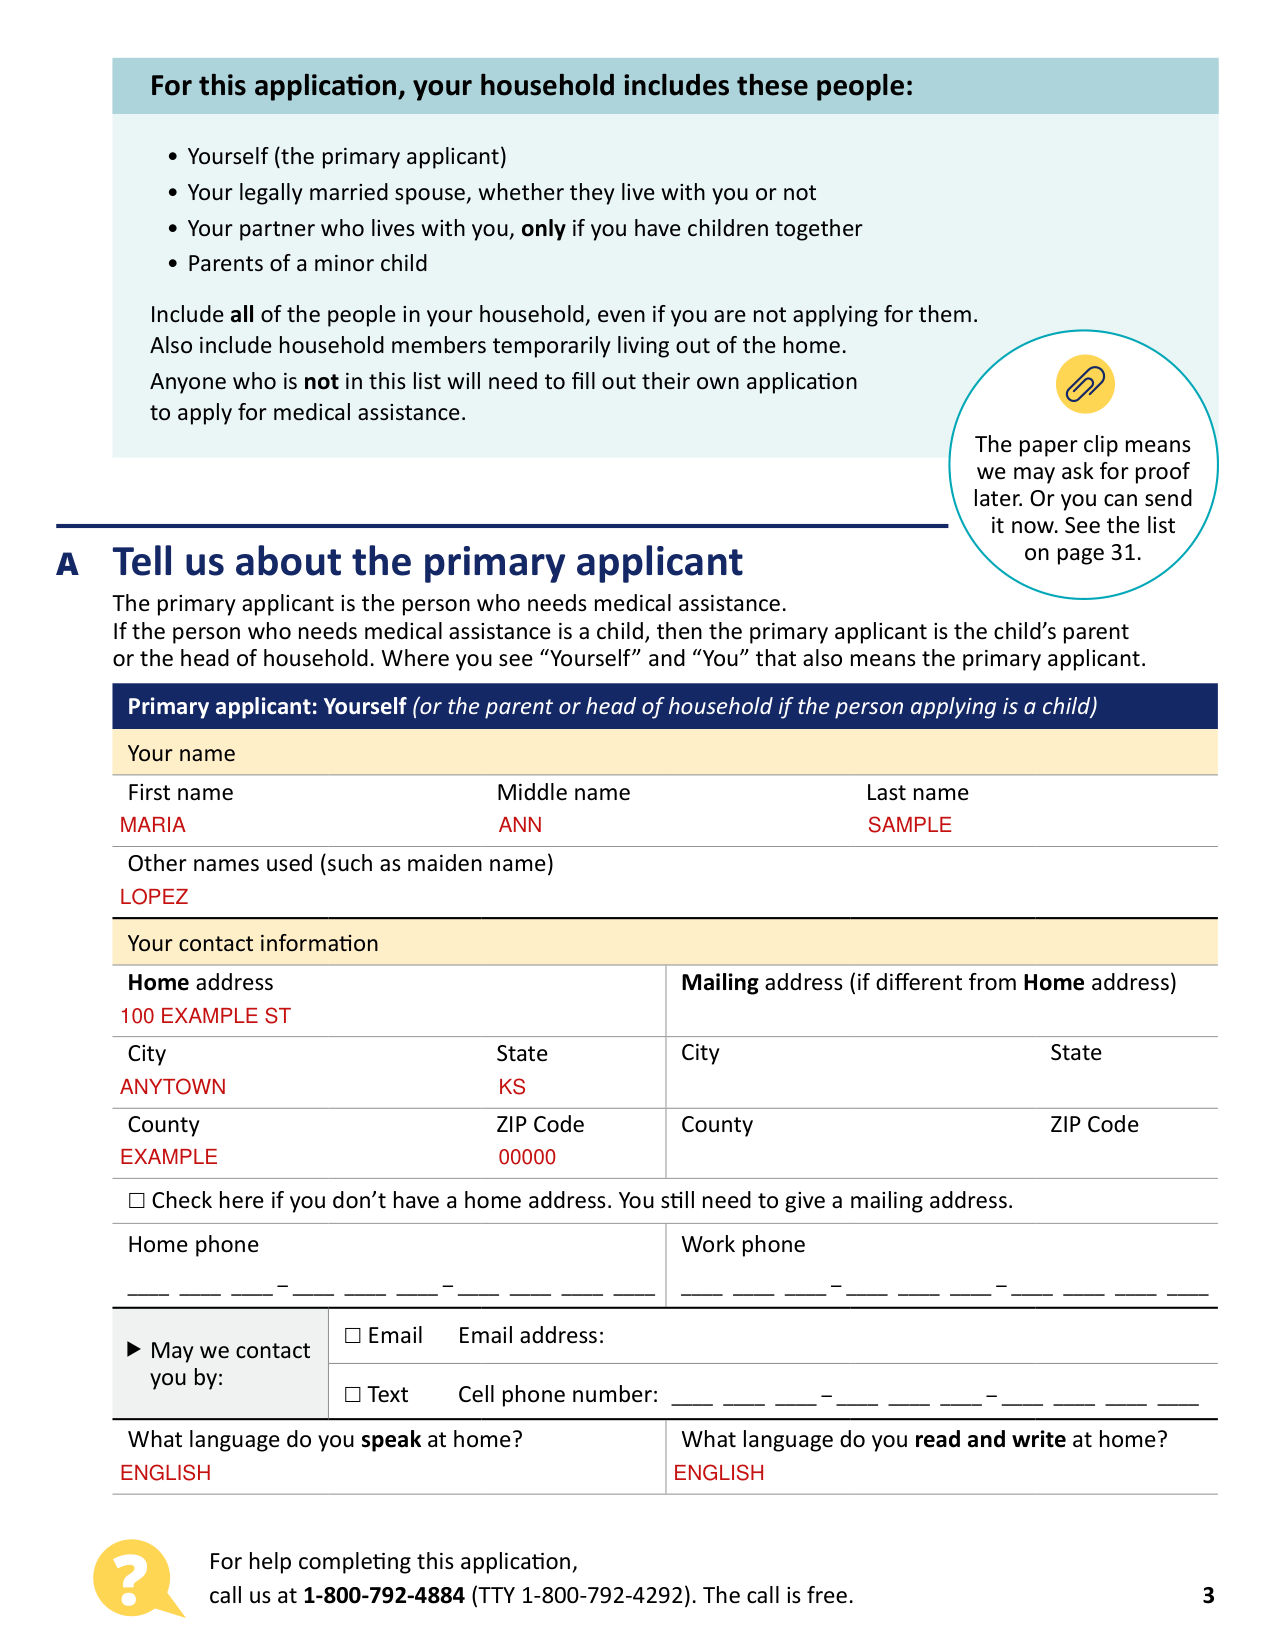
How to fill out Elderly and Persons with Disabilities Medical Assistance Application (KC-1500), box by box
Your name and your home and mailing address
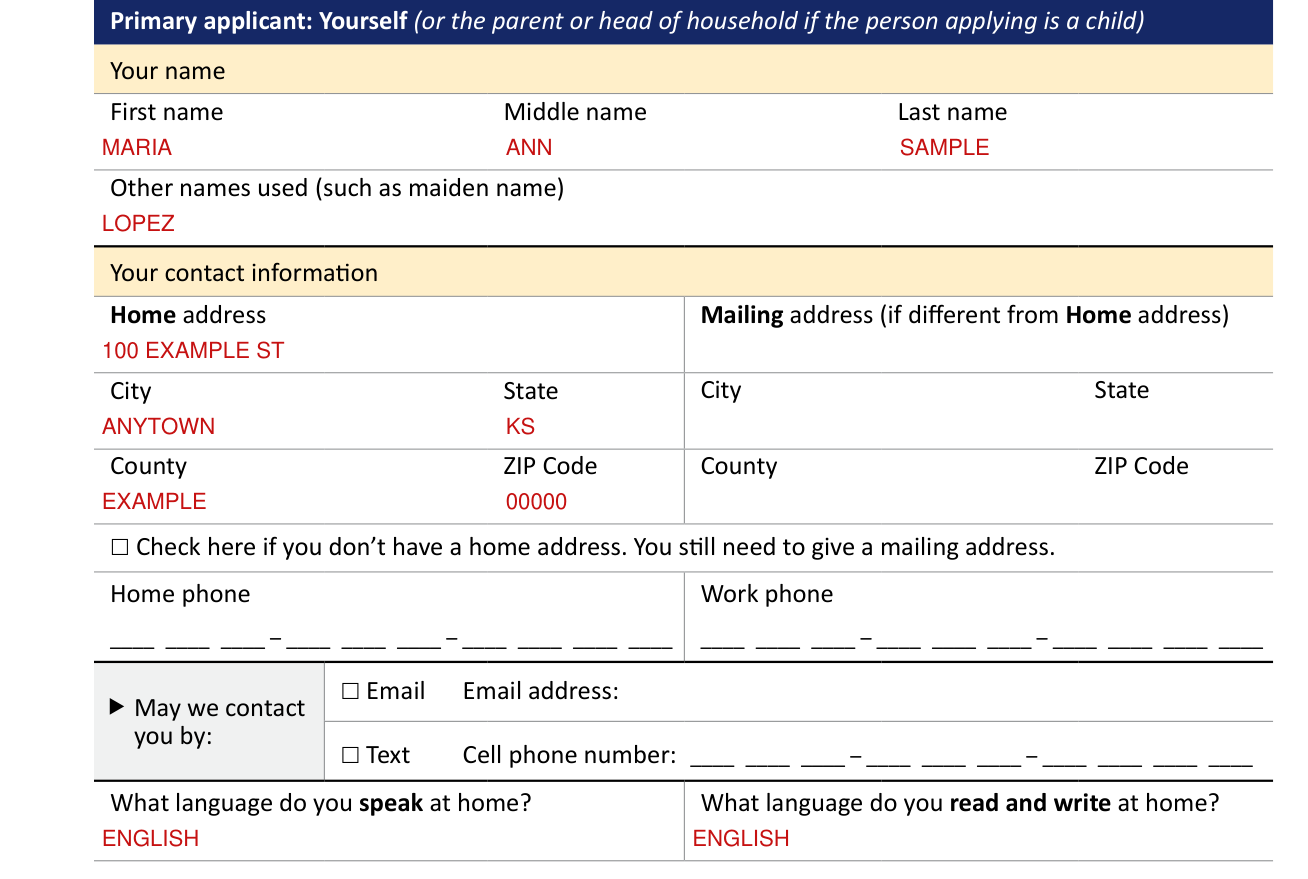
The primary applicant is the person who needs medical assistance.
If the person who needs medical assistance is a child, then the primary applicant is the child's parent or the head of household.
Enter your name: First name, Middle name and Last name.
Enter other names used (such as maiden name).
Enter the Home address, City, State, County and ZIP Code; the Mailing address (if different from Home address) has its own City, State, County and ZIP Code.
Check here if you don't have a home address. You still need to give a mailing address.
What language do you speak at home? What language do you read and write at home?
Signing the application
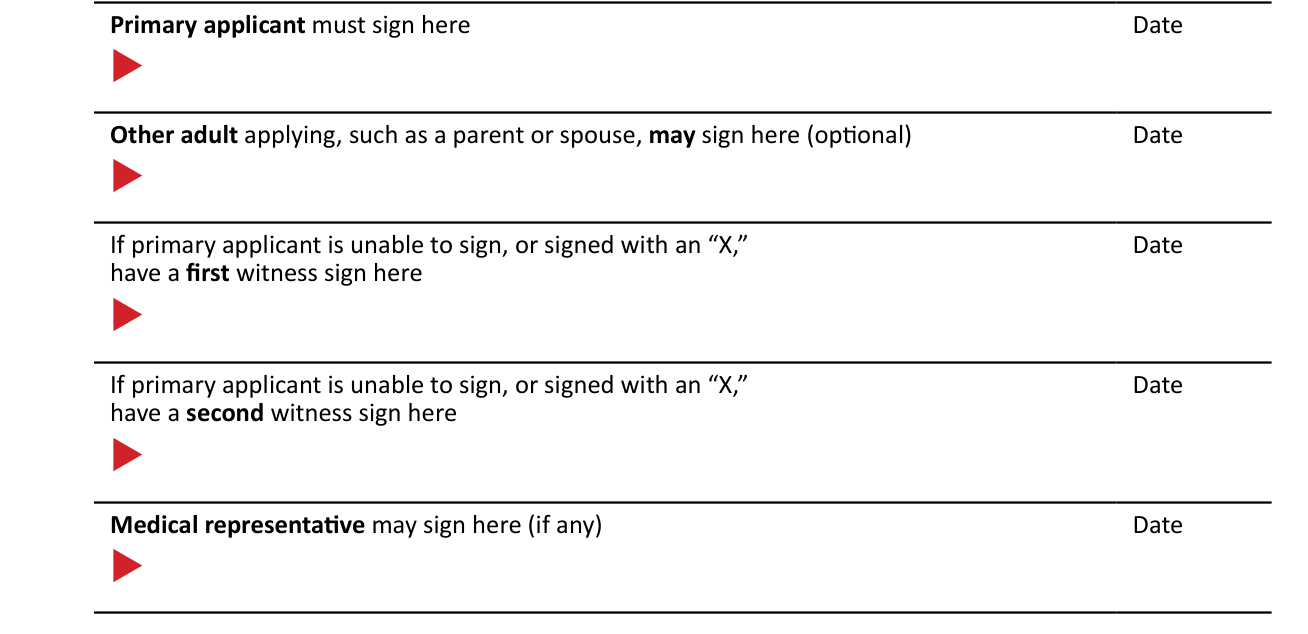
The primary applicant must sign here.
Another adult applying, such as a parent or spouse, may sign here (optional).
If the primary applicant is unable to sign, or signed with an “X,” have a first witness sign here and a second witness sign here.
A medical representative may sign here (if any).
More rules for Elderly and Persons with Disabilities Medical Assistance Application (KC-1500)
Answer all questions on the application.
Include all of the people in your household, even if you are not applying for them.
Start with yourself (the primary applicant, or the parent or head of household if the person applying is a child).
If your situation is different
More than 3 people are in your household
There is room on this application for 3 people.
If more than 3 people are in your household, make copies of pages 4-12 before you fill them out.
Use the copies to complete persons 4, 5, 6 and so on. Attach the copies to your application.
You are pregnant
This application is for elderly persons, persons with a disability, and families that include a child with a disability. If you are pregnant or your family does not include a child with a disability, use the Families with Children Medical Assistance Application.
You disagree with an agency decision
You have the right to ask for a fair hearing if you disagree with an agency decision or you think they did not follow all federal and state rules. The office must get your hearing request within 33 days of the date on the decision notice. You can ask for the hearing by phone or mail: Phone: 1-800-792-4884 (TTY 1-800-792-4292), or Mail: The Office of Administrative Hearings 1020 S. Kansas Ave Topeka, KS 66612.
The hearing decision usually comes within 90 days of the request date.
You send proof with the application
You can send your proof with the application so it can be processed faster, but you do not have to send any proof now.
Common questions about Elderly and Persons with Disabilities Medical Assistance Application (KC-1500)
Where do I file it?
Mail your completed and signed application to KanCare Clearinghouse, P.O. Box 3599, Topeka, KS 66601-9738, or fax it to 1-844-264-6285.
Is there a penalty?
If you give false or purposefully misleading information on this application or hide information requested by the application, you will be subject to penalties for your actions.
Sources
[1] Elderly and Persons with Disabilities Medical Assistance Application (KC-1500 1/25), KanCare, Kansas Department of Health and Environment (the Official source link on this page).