
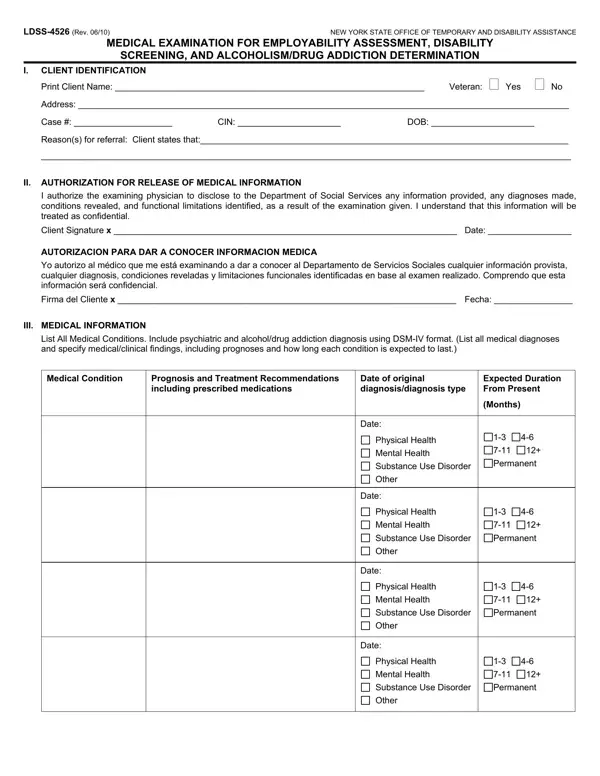

Form LDSS-4526 at a glance
What it is: Form LDSS-4526 is the New York State Office of Temporary and Disability Assistance Medical Examination for Employability Assessment, Disability Screening, and Alcoholism/Drug Addiction Determination.
Who signs: The client signs after Client Signature x, and the physician or psychologist signs after Signature of physician or psychologist: x.
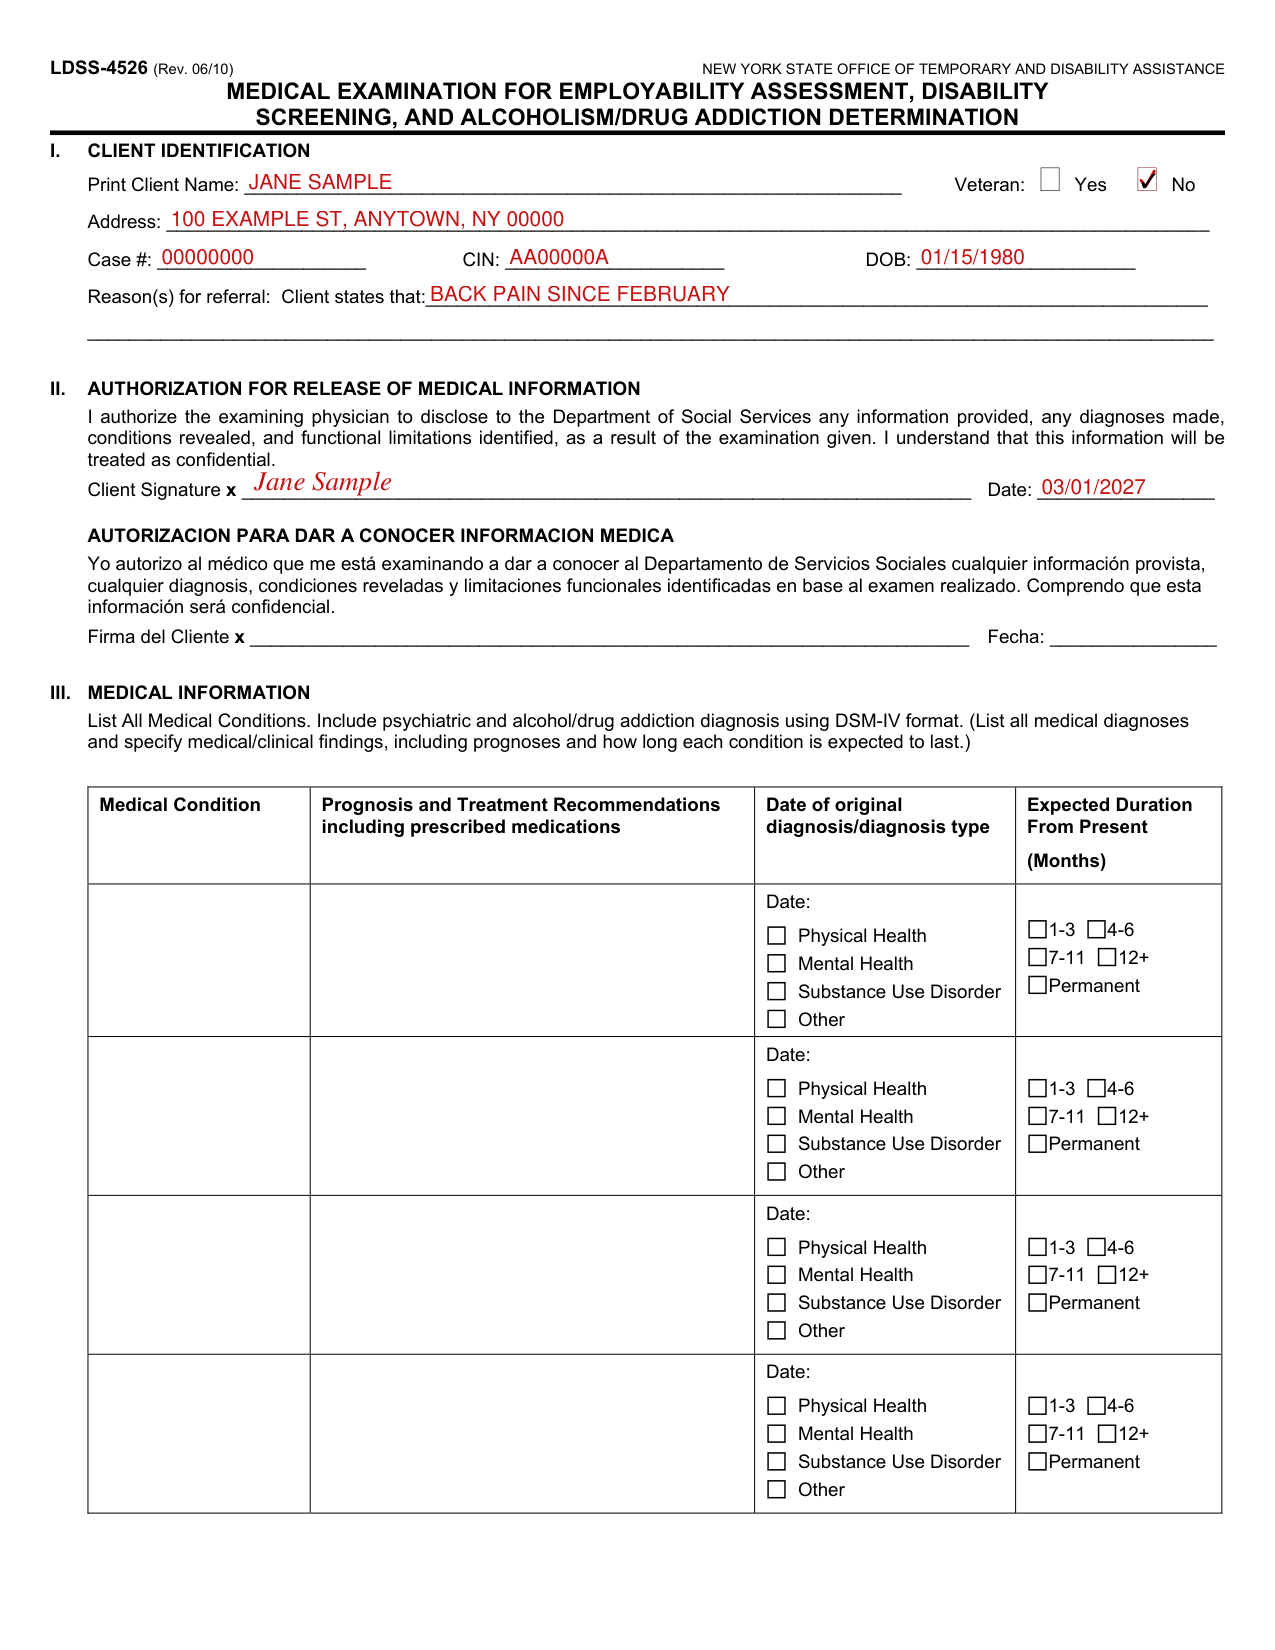
A filled-in Form LDSS-4526 example: a client fills out the identification and release
How to fill out Form LDSS-4526, box by box
I. CLIENT IDENTIFICATION

Under I. CLIENT IDENTIFICATION, enter Print Client Name and Address, and mark Yes or No after Veteran.
Enter the Case #, CIN and DOB.
Write the Reason(s) for referral after Client states that.
II. AUTHORIZATION FOR RELEASE OF MEDICAL INFORMATION

Under II. AUTHORIZATION FOR RELEASE OF MEDICAL INFORMATION, you authorize the examining physician to disclose to the Department of Social Services any information provided, any diagnoses made, conditions revealed, and functional limitations identified, as a result of the examination given. You understand that this information will be treated as confidential.
Sign after Client Signature x and enter the Date. AUTORIZACION PARA DAR A CONOCER INFORMACION MEDICA has its own lines, Firma del Cliente x and Fecha.
III. MEDICAL INFORMATION
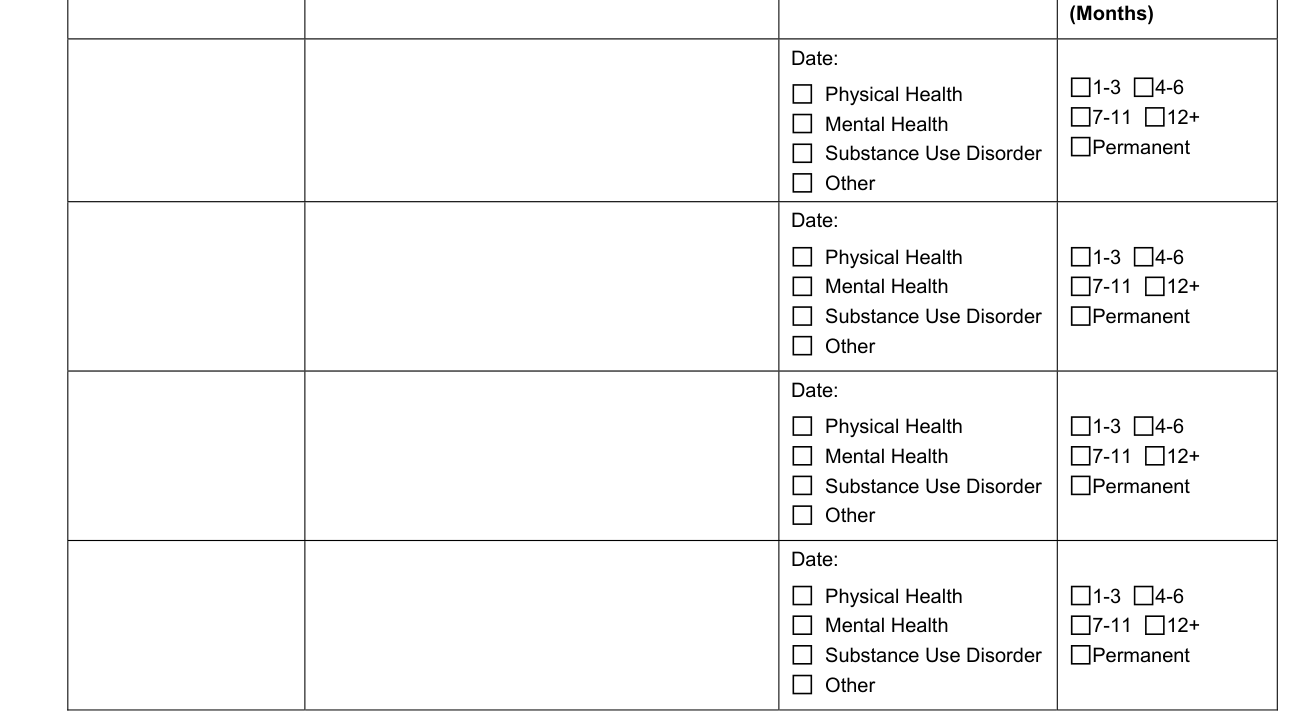
Under III. MEDICAL INFORMATION, List All Medical Conditions. Include psychiatric and alcohol/drug addiction diagnosis using DSM-IV format. List all medical diagnoses and specify medical/clinical findings, including prognoses and how long each condition is expected to last.
For each condition, enter the Medical Condition, the Prognosis and Treatment Recommendations including prescribed medications, and the Date of original diagnosis/diagnosis type. Mark Physical Health, Mental Health, Substance Use Disorder or Other. Mark the Expected Duration From Present (Months): 1-3, 4-6, 7-11, 12+ or Permanent.
IV. FUNCTIONAL LIMITATIONS
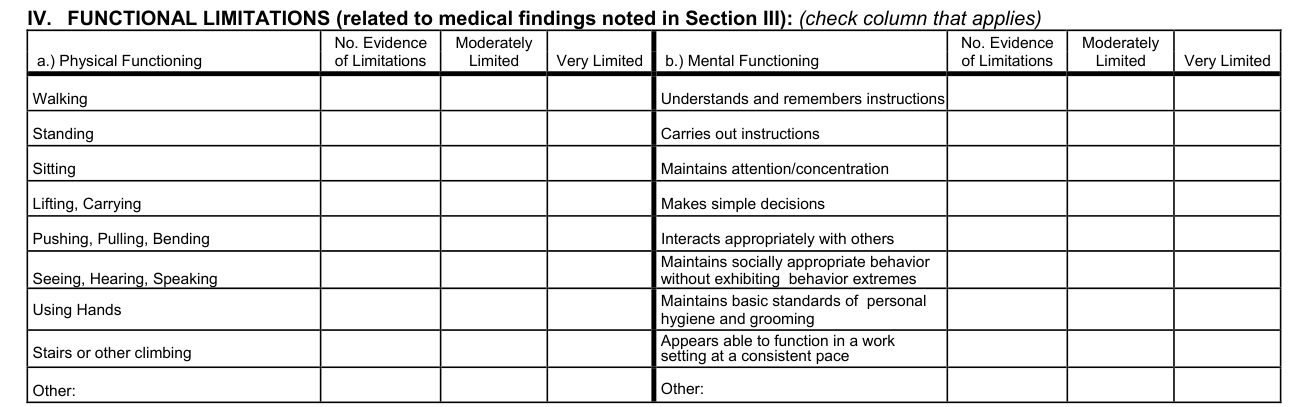
Under IV. FUNCTIONAL LIMITATIONS (related to medical findings noted in Section III), check the column that applies: No Evidence of Limitations, Moderately Limited or Very Limited.
For a.) Physical Functioning, check a column for Walking, Standing, Sitting, Lifting, Carrying, Pushing, Pulling, Bending, Seeing, Hearing, Speaking, Using Hands, Stairs or other climbing, and Other. For b.) Mental Functioning, check a column for Understands and remembers instructions, Carries out instructions, Maintains attention/concentration, Makes simple decisions, Interacts appropriately with others, Maintains socially appropriate behavior without exhibiting behavior extremes, Maintains basic standards of personal hygiene and grooming, Appears able to function in a work setting at a consistent pace, and Other.
V. TREATMENT HISTORY

Under V. TREATMENT HISTORY, list medical, psychiatric, alcoholism and drug treatment for the past Two Years. Enter the Name of Program/Provider, the Type of Program/Provider i.e. Outpatient, Residential, Methadone (for addiction specify modality) and the Length of Treatment (# of Months).
VI. CURRENT TREATMENT PROGRAM IDENTIFICATION

Under VI. CURRENT TREATMENT PROGRAM IDENTIFICATION, include medical, psychiatric, alcoholism and drug treatment as applicable. Enter the Program Name, the Address of Client's Treatment Site, the Mailing Address (If different from the Address of Client's Treatment Site), the Treatment Program Contact, Title, Telephone # and Fax #.
VII. LIMITATIONS ON WORK ACTIVITIES

Under VII. LIMITATIONS ON WORK ACTIVITIES, a.) taking into consideration physical, mental and addiction limitation(s), describe any working conditions, environments, or work activities which are contraindicated.
For b.) say if these restrictions are expected to last 1-3 months, 4-6 months, 7-11 months, 12+ months or permanent.
For c.) mark Yes or No after Do you recommend referral to rehabilitation, including but not limited to, a mental health or alcohol/substance abuse, or a physical rehabilitation program. If yes, please specify.
VIII. SCREENING FOR POSSIBLE SSI REFERRAL

Under VIII. SCREENING FOR POSSIBLE SSI REFERRAL: Based on the evidence available to you, does this individual have severe impairment(s) which has lasted, or is expected to last at least 12 months? IF YES, please check and Explain briefly.
If substance abuse is also found, mark Yes or No to say if such impairment would be expected to continue if use of drugs and/or alcohol were to cease.
IX. PHYSICIAN INFORMATION
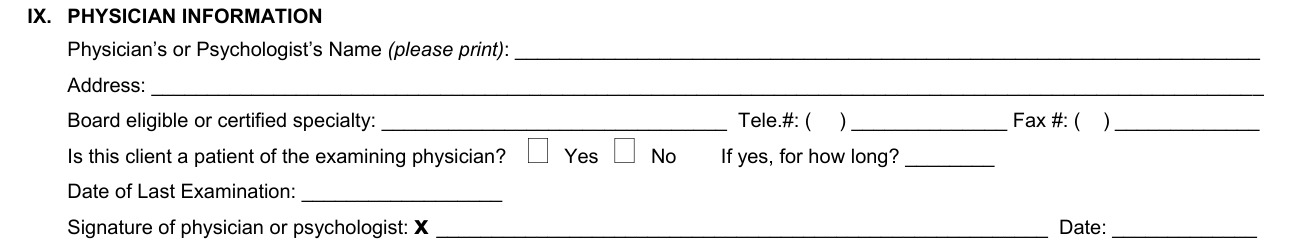
Under IX. PHYSICIAN INFORMATION, enter the Physician's or Psychologist's Name (please print), Address, Board eligible or certified specialty, Tele.# and Fax #.
Mark Yes or No to say if this client is a patient of the examining physician. If yes, enter for how long. Enter the Date of Last Examination.
The physician or psychologist signs after Signature of physician or psychologist: x and enters the Date.
Social Services Contact

Please forward this completed form to the Social Services Contact, and enter the Telephone # and Address.
Sources
[1] Form LDSS-4526 (Rev. 06/10), Medical Examination for Employability Assessment, Disability Screening, and Alcoholism/Drug Addiction Determination, New York State Office of Temporary and Disability Assistance (the Official source link on this page).