
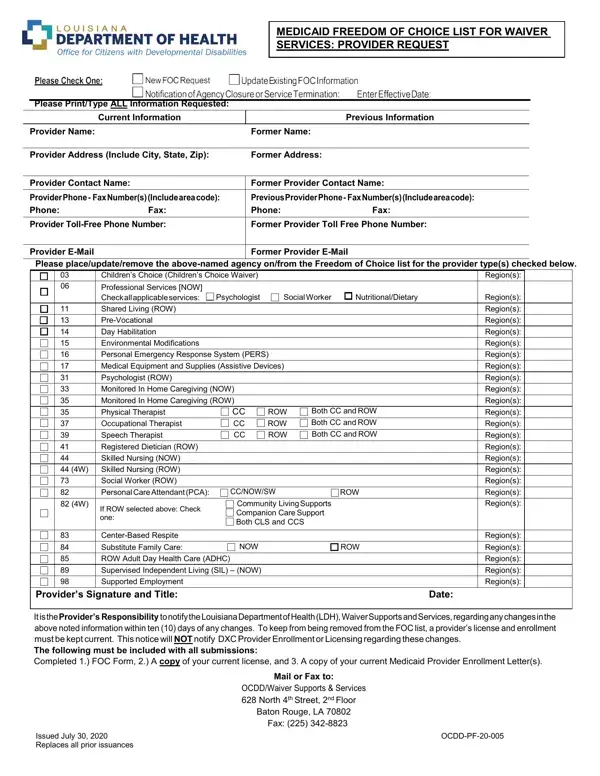

Form OCDD-PF-20-005 at a glance
What it is: Medicaid Freedom of Choice List for Waiver Services: Provider Request.
Who signs: Sign in Provider's Signature and Title, and enter the Date.
What to bring and attach to Form OCDD-PF-20-005
The following must be included with all submissions:
Completed FOC Form
A copy of your current license
Include a copy of your current Medicaid Provider Enrollment Letter(s) with all submissions.
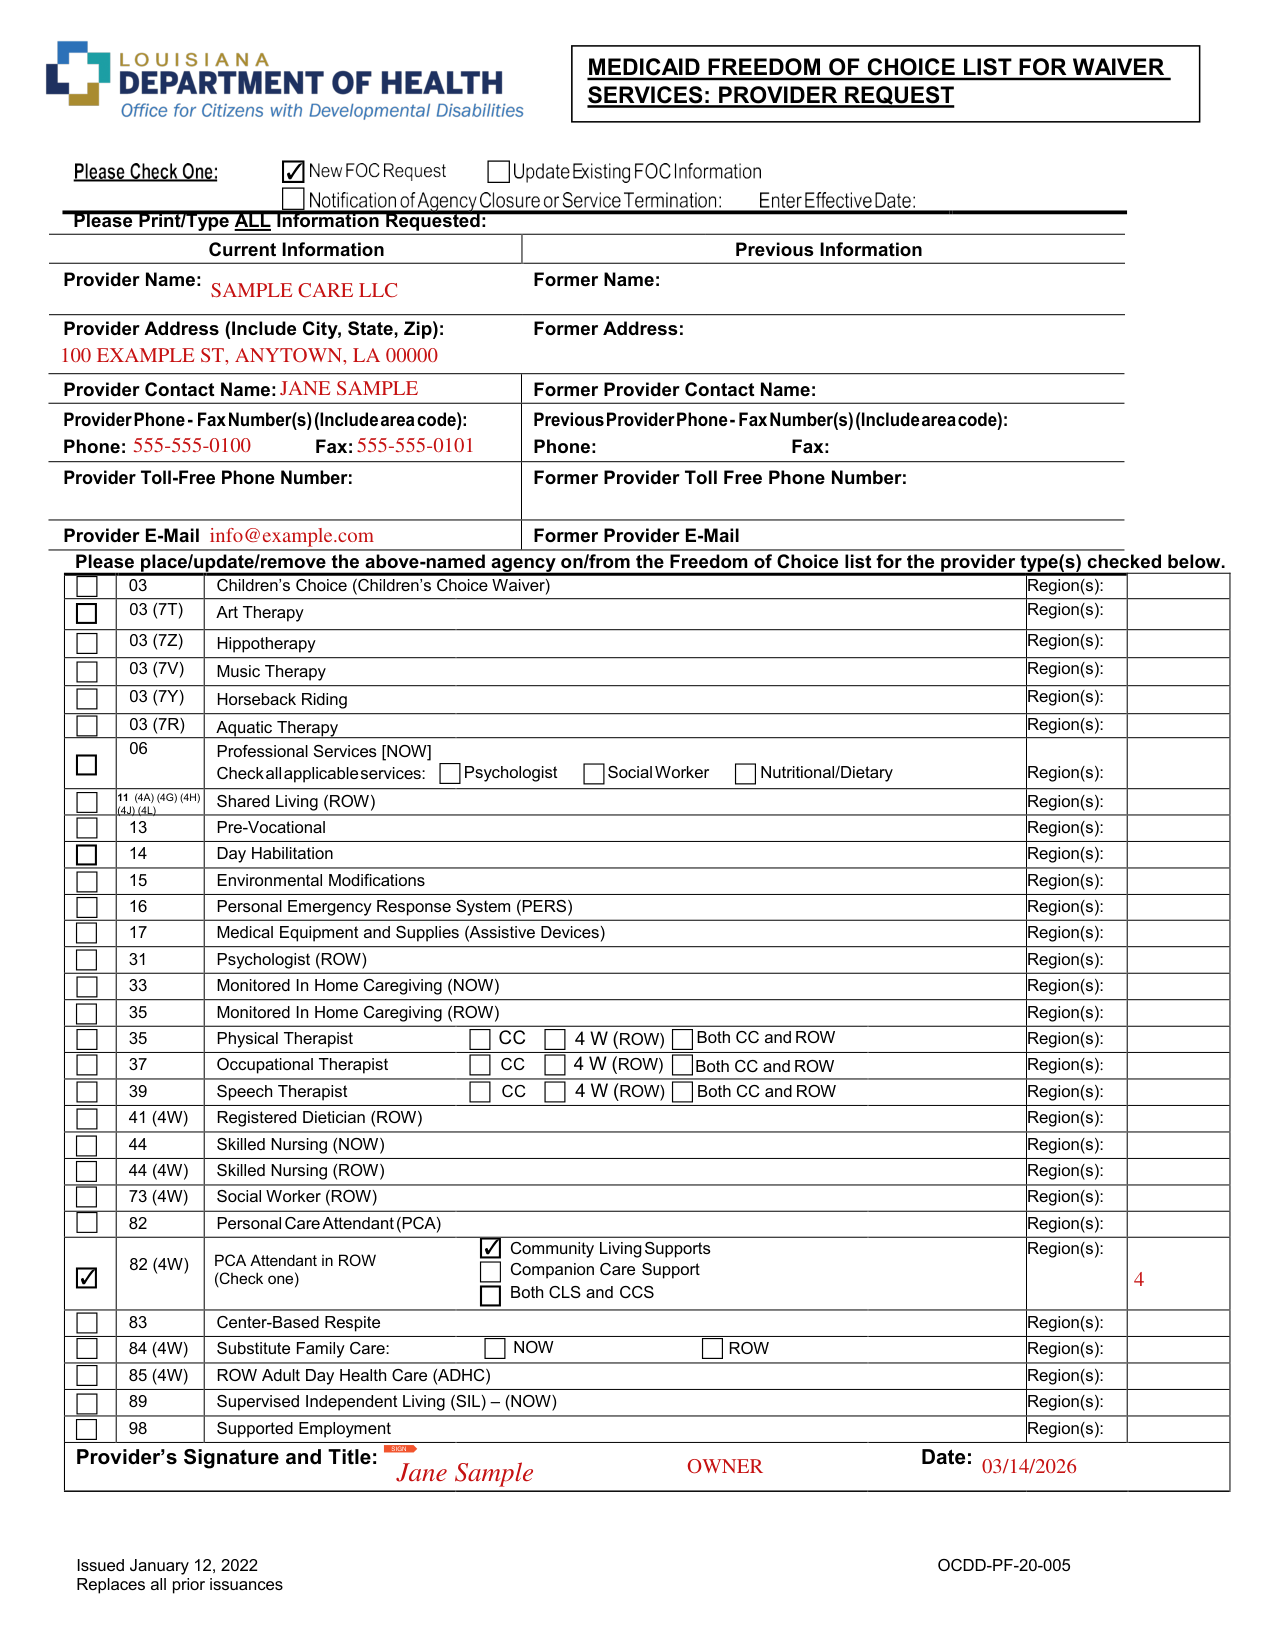
A filled-in Form OCDD-PF-20-005 example: a new provider requests PCA Attendant in ROW
How to fill out Form OCDD-PF-20-005, box by box
Place, update or remove the agency
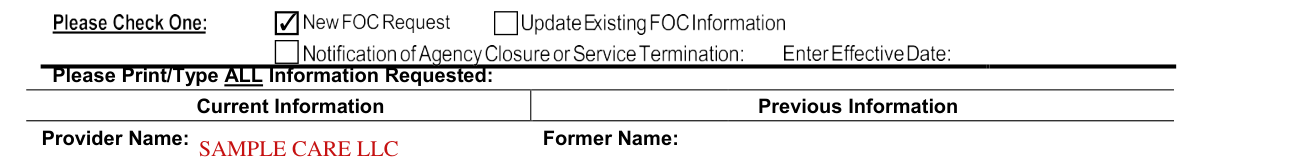
Place, update or remove the agency on or from the Freedom of Choice list for the provider type(s) checked.
Current Information and Previous Information
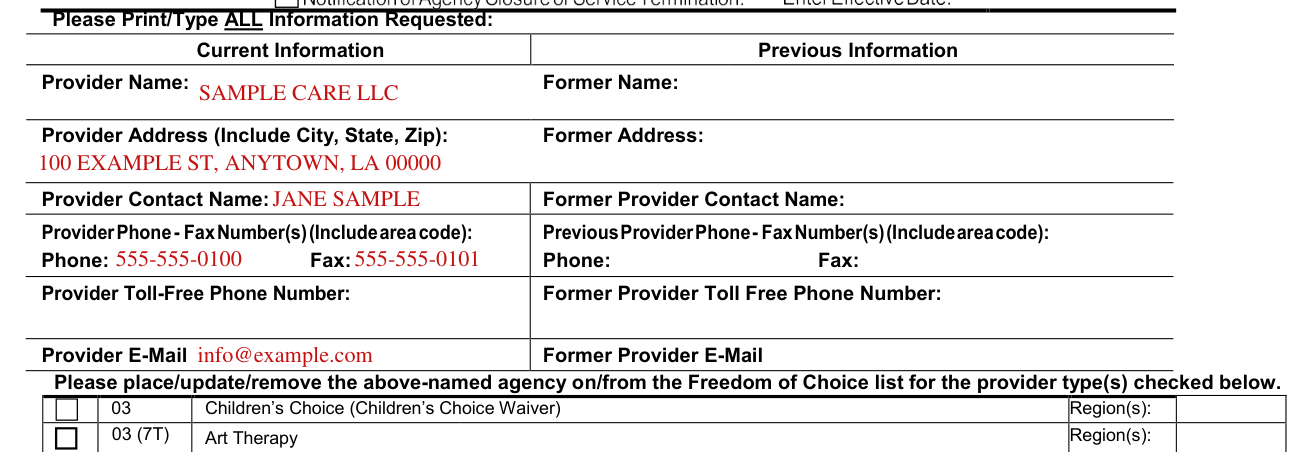
Print or type ALL Information Requested.
Under Current Information, enter the Provider Name, the Provider Address (Include City, State, Zip) and the Provider Contact Name; under Previous Information, enter the Former Name, Former Address and Former Provider Contact Name.
Include the area code in the Phone and Fax Number(s) for Current Information and for Previous Information; also enter the Provider Toll-Free Phone Number and Provider E-Mail, or the Former Provider Toll Free Phone Number and Former Provider E-Mail.
Children's Choice and its therapies
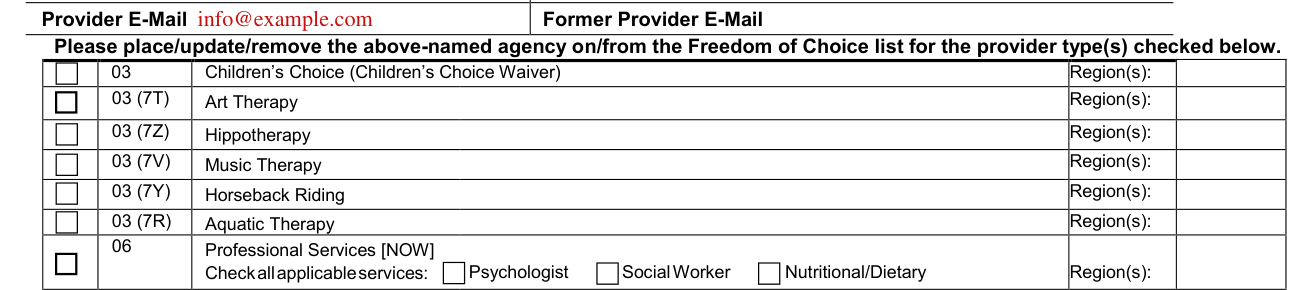
Check 03 Children's Choice (Children's Choice Waiver), 03 (7T) Art Therapy, 03 (7Z) Hippotherapy, 03 (7V) Music Therapy, 03 (7Y) Horseback Riding or 03 (7R) Aquatic Therapy, and enter the Region(s).
06 Professional Services [NOW]

Under 06 Professional Services [NOW], check all applicable services: Psychologist, Social Worker, Nutritional/Dietary, and enter the Region(s).
Shared Living, Pre-Vocational, Day Habilitation and Monitored In Home Caregiving
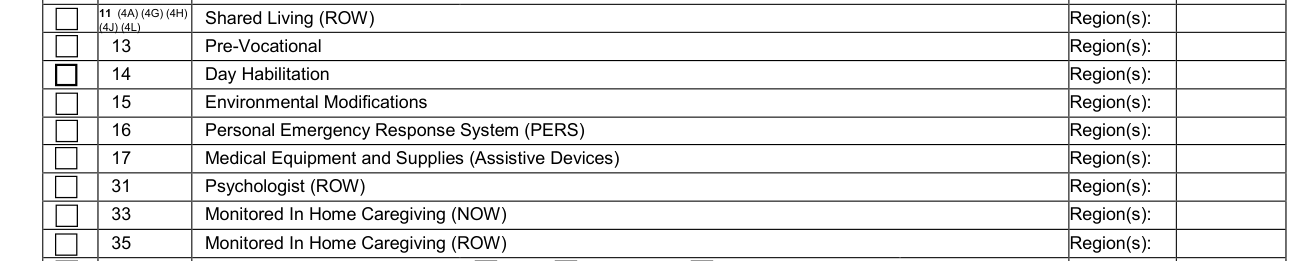
Each of these has Region(s): 11 (4A) (4G) (4H) (4J) (4L) Shared Living (ROW), 13 Pre-Vocational, 14 Day Habilitation, 15 Environmental Modifications, 16 Personal Emergency Response System (PERS), 17 Medical Equipment and Supplies (Assistive Devices), 31 Psychologist (ROW), 33 Monitored In Home Caregiving (NOW) and 35 Monitored In Home Caregiving (ROW).
Therapists: Physical, Occupational and Speech

35 Physical Therapist, 37 Occupational Therapist and 39 Speech Therapist each print CC 4 W (ROW) and Both CC and ROW, with Region(s).
Dietician, Skilled Nursing and Social Worker

41 (4W) Registered Dietician (ROW), 44 Skilled Nursing (NOW), 44 (4W) Skilled Nursing (ROW) and 73 (4W) Social Worker (ROW) each have Region(s).
Personal Care Attendant (PCA)

For 82 (4W) PCA Attendant in ROW (Check one), check Community Living Supports, Companion Care Support or Both CLS and CCS, and enter the Region(s); 82 Personal Care Attendant (PCA) has Region(s).
Respite, Substitute Family Care, Adult Day Health Care, Supervised Independent Living and Supported Employment
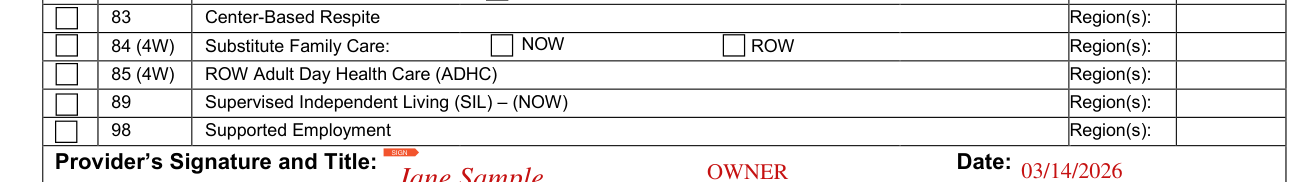
83 Center-Based Respite, 84 (4W) Substitute Family Care: NOW or ROW, 85 (4W) ROW Adult Day Health Care (ADHC), 89 Supervised Independent Living (SIL) - (NOW) and 98 Supported Employment each have Region(s).
Provider's Signature and Title

Sign in Provider's Signature and Title, and enter the Date.
If your situation is different
A change in the above noted information
It is the Provider's Responsibility to notify the Louisiana Department of Health (LDH), Waiver Supports and Services, regarding any changes in the above noted information on page 1 within ten (10) days of any changes.
To keep from being removed from the FOC list, a provider's license and enrollment must be kept current.
This notice will NOT notify DXC Provider Enrollment or Licensing regarding these changes.
Common questions about Form OCDD-PF-20-005
Where do I file it?
Mail or Fax to: OCDD/Waiver Supports & Services 628 North 4th Street, 2nd Floor Baton Rouge, LA 70802 Fax: (225) 342-8823
Sources
[1] Form OCDD-PF-20-005 (Issued 01/12/2022), Medicaid Freedom of Choice List for Waiver Services: Provider Request, Louisiana Department of Health (the Official source link on this page).