


Form LS-202 at a glance
What it is: Form LS-202 is the U.S. Department of Labor, Office of Workers' Compensation Programs, Employer's First Report of Injury or Occupational Illness.
Who signs: Box 37: Signature of person authorized to sign for employer.
REPORTABLE INJURY - Any accidental injury which causes loss of one or more shifts of work or death allegedly arising out of and in the course of employment, including any occupational disease or infection believed or alleged to have arisen naturally out of such employment, or as a natural or unavoidable result from an accidental injury.
Completion of this form is mandatory.
A filled-in Form LS-202 example: a safety manager reports a fall from a ladder
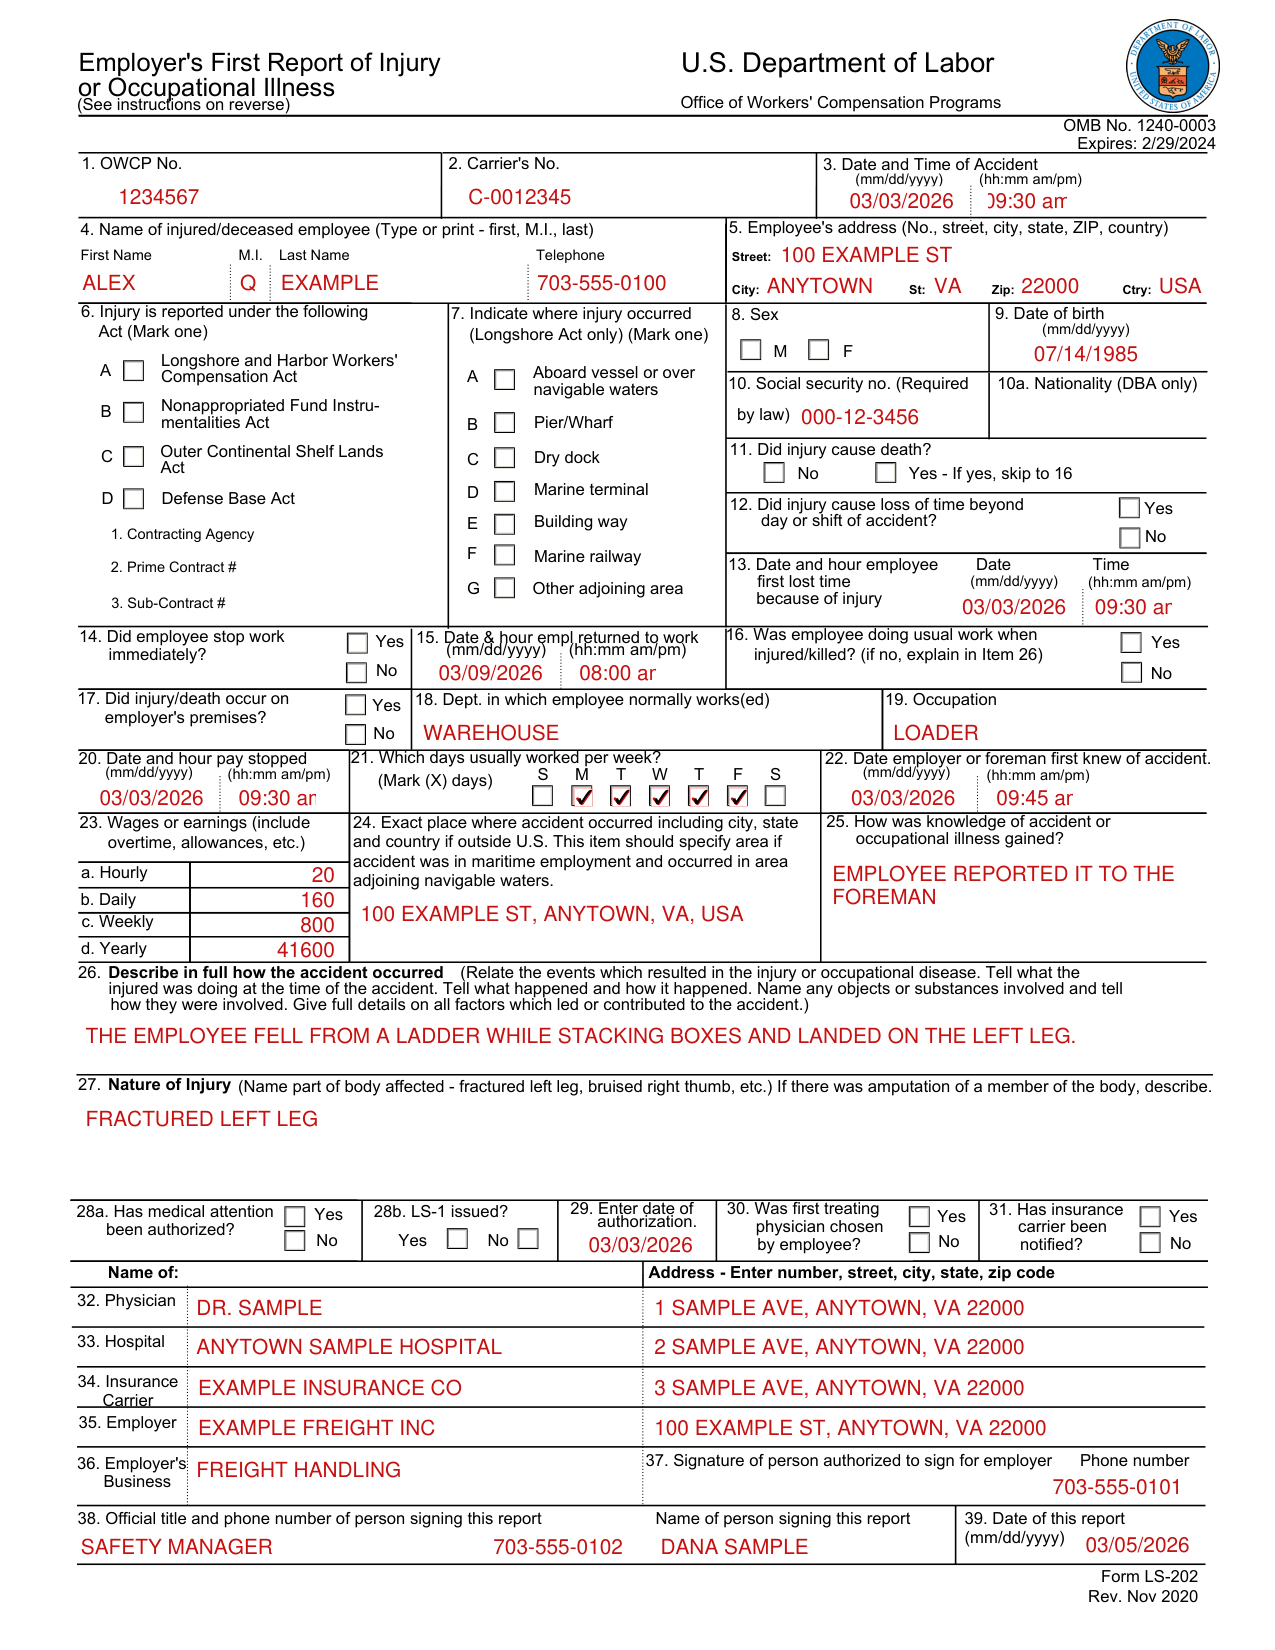
How to fill out Form LS-202, box by box
Boxes 1, 2 and 3: OWCP No., Carrier's No. and Date and Time of Accident

Enter the OWCP No. in Box 1, the Carrier's No. in Box 2 and the Date and Time of Accident in Box 3, as (mm/dd/yyyy) and (hh:mm am/pm).
Boxes 4 and 5: the injured/deceased employee and the Employee's address

Enter in Box 4 the name of the injured/deceased employee (Type or print - first, M.I., last) with Telephone, and in Box 5 the Employee's address (No., street, city, state, ZIP, country): Street, City, St, Zip and Ctry.
Boxes 6 and 7: the Act and where the injury occurred
In Box 6, Mark one Act under which the injury is reported: Longshore and Harbor Workers' Compensation Act, Nonappropriated Fund Instrumentalities Act, Outer Continental Shelf Lands Act or Defense Base Act.
Longshore and Harbor Workers' Compensation Act covers employees injured while engaged in maritime employment upon the navigable waters of the United States (including any adjoining pier, wharf, dry dock, terminal, building way, marine railway, or other adjoining area customarily used by an employer in loading, unloading, repairing, or building a vessel); - employees injured upon the navigable waters of the United States and other described areas who at the time of injury were engaged in maritime employment and are not otherwise specifically excluded under the Act (33 U.S.C. 902).
In Box 7, indicate where injury occurred: Aboard vessel or over navigable waters, Pier/Wharf, Dry dock, Marine terminal, Building way, Marine railway or Other adjoining area.
Boxes 8 to 10a: Sex, Date of birth, Social security no. and Nationality

In Box 8, Mark one, M or F, for Sex (Longshore Act only).
Enter the Date of birth in Box 9 as (mm/dd/yyyy).
In Box 10, enter the Social security no. (Required by law).
Enter the Nationality in Box 10a (DBA only).
Defense Base Act: Contracting Agency, Prime Contract # and Sub-Contract #

For the Defense Base Act, enter the Contracting Agency, the Prime Contract # and the Sub-Contract #.
Boxes 11 to 16: death, lost time and work
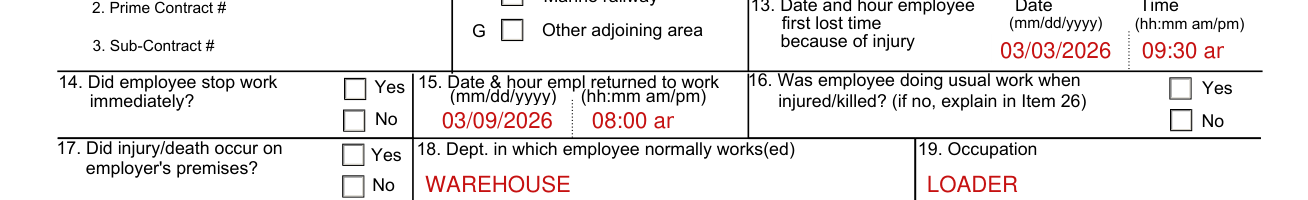
Box 11: Did injury cause death? Yes or No. If yes, skip to 16.
Box 12: Did injury cause loss of time beyond day or shift of accident? Yes or No.
In Box 13, enter the Date and hour employee first lost time because of injury (mm/dd/yyyy) (hh:mm am/pm).
Box 14: Did employee stop work immediately? Yes or No. In Box 15, enter the Date & hour employee returned to work (mm/dd/yyyy) (hh:mm am/pm). Box 16: Was employee doing usual work when injured/killed? Yes or No (if no, explain in Item 26).
Boxes 17 to 22: employer's premises, Dept., Occupation, pay stopped, days worked and when the employer knew

In Box 18, enter the Dept. in which employee normally works(ed).
In Box 19, enter the Occupation.
In Box 20, enter the Date and hour pay stopped (mm/dd/yyyy) (hh:mm am/pm).
Box 17: Did injury/death occur on employer's premises? Yes or No. In Box 21, Mark (X) the days usually worked per week. In Box 22, enter the Date employer or foreman first knew of accident (mm/dd/yyyy) (hh:mm am/pm).
Boxes 23 to 26: Wages or earnings, place of accident, knowledge and how the accident occurred

In Box 23, enter Wages or earnings (include overtime, allowances, etc.): a. Hourly, b. Daily, c. Weekly and d. Yearly. In Box 24, enter the Exact place where accident occurred including city, state and country if outside U.S. This item should specify area if accident was in maritime employment and occurred in area adjoining navigable waters. In Box 25, enter How was knowledge of accident or occupational illness gained?
Item 24 - Exact place where accident occurred requires the nearest street address, city and town.
26. Describe in full how the accident occurred (Relate the events which resulted in the injury or occupational disease. Tell what the injured was doing at the time of the accident. Tell what happened and how it happened. Name any objects or substances involved and tell how they were involved. Give full details on all factors which led or contributed to the accident.)
Boxes 27 to 35: Nature of Injury and authorization
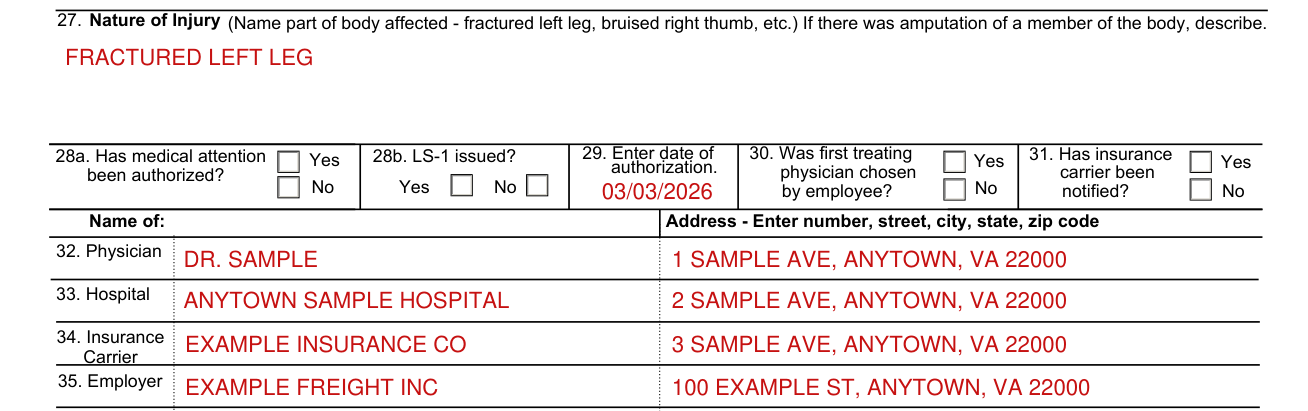
In Box 27, enter the Nature of Injury (Name part of body affected - fractured left leg, bruised right thumb, etc.) If there was amputation of a member of the body, describe.
Box 28a: Has medical attention been authorized? Yes or No. Box 28b: LS-1 issued? Yes or No. In Box 29, enter the date of authorization. Box 30: Was first treating physician chosen by employee? Yes or No. Box 31: Has insurance carrier been notified? Yes or No.
Box 32 Physician, Box 33 Hospital, Box 34 Insurance Carrier and Box 35 Employer each ask for a Name of: and an Address - Enter number, street, city, state, zip code.
Boxes 36 to 39: Employer's Business, Signature and Date of this report

In Box 36, enter the Employer's Business.
In Box 38, enter the Official title and phone number of person signing this report, and the Name of person signing this report.
In Box 39, enter the Date of this report (mm/dd/yyyy).
More rules for Form LS-202
Under the law all medical treatment and compensation must be furnished by the employer or its insurance company.
Treatment must be by a physician chosen by the employee, unless the physician is on a list of physicians currently not authorized by the Department of Labor to render medical care under the Act.
Compensation payments become due and are payable on the 14th day after the employer first has knowledge of the injury or death.
NOTE: Filing this form does not constitute an admission of liability under the Compensation Act.
This report shall not be evidence of any fact stated herein in any proceeding in respect to any such injury or death on account of which the report is made. [33 U.S.C. 930(c)]
Common questions about Form LS-202
Is there a deadline?
File form within 10 days from the date of injury or death or from the date the employer first has knowledge of an injury or death. If the employer controverts the right to compensation it must also file a notice of controversion with the District Director within 14 days after it has knowledge of the allged injury or death.
Where do I file it?
This report is required by 33 U.S.C. 930(a) and must be filed with the U.S. Department of Labor, Office of Workers' Compensation Programs, Division of Longshore and Harbor Workers' Compensation by electronic submission via OWCP web portal, facsimile or Central Mail Receipt Site.
Is there a penalty?
Penalties may be charged for failure to comply with provisions of the law. Any employer, insurance carrier, or self-insured employer who knowingly and willfully fails to submit this report when required or knowingly or willfully makes a false statement or misrepresentation in this report shall be subject to a civil penalty based on amounts outlined in the Federal Civil Penalties Inflation Adjustment Act Improvements Act of 2015, for each such failure, refusal, false statement, or misrepresentation. [33 U.S.C.930(e)]
Sources
[1] Form LS-202 (Rev. Nov 2020), Employer's First Report of Injury or Occupational Illness, U.S. Department of Labor (the Official source link on this page).