


Merck Patient Assistance Program application at a glance
What it is: MERCK PATIENT ASSISTANCE PROGRAM: Merck PAP provides certain Merck medicines free of charge to people who do not have prescription drug or health insurance coverage and who, without assistance, cannot afford their Merck medicines.
Who signs: Both the Patient and the Prescribing Healthcare Professional must check, sign, AND date this form in all designated places.
What to bring and attach to Merck Patient Assistance Program application
The Patient must authorize Merck PAP to verify their current gross annual household income (household income before taxes are withdrawn) by either Option 1: Sending with this application, a COPY of any ONE of the following documents showing proof of the household income the Patient provided on the application form:
Most recent 1040 Federal Tax Form, Social Security Benefits Letter, Disability Statement, One month of pay stubs, prior to the application date, Veteran Benefits Statement, Pension Letter, Unemployment Benefits Statement, Income Verification Letter from an employer.
A filled-in Merck Patient Assistance Program application example: a first-time applicant fills in Section 1
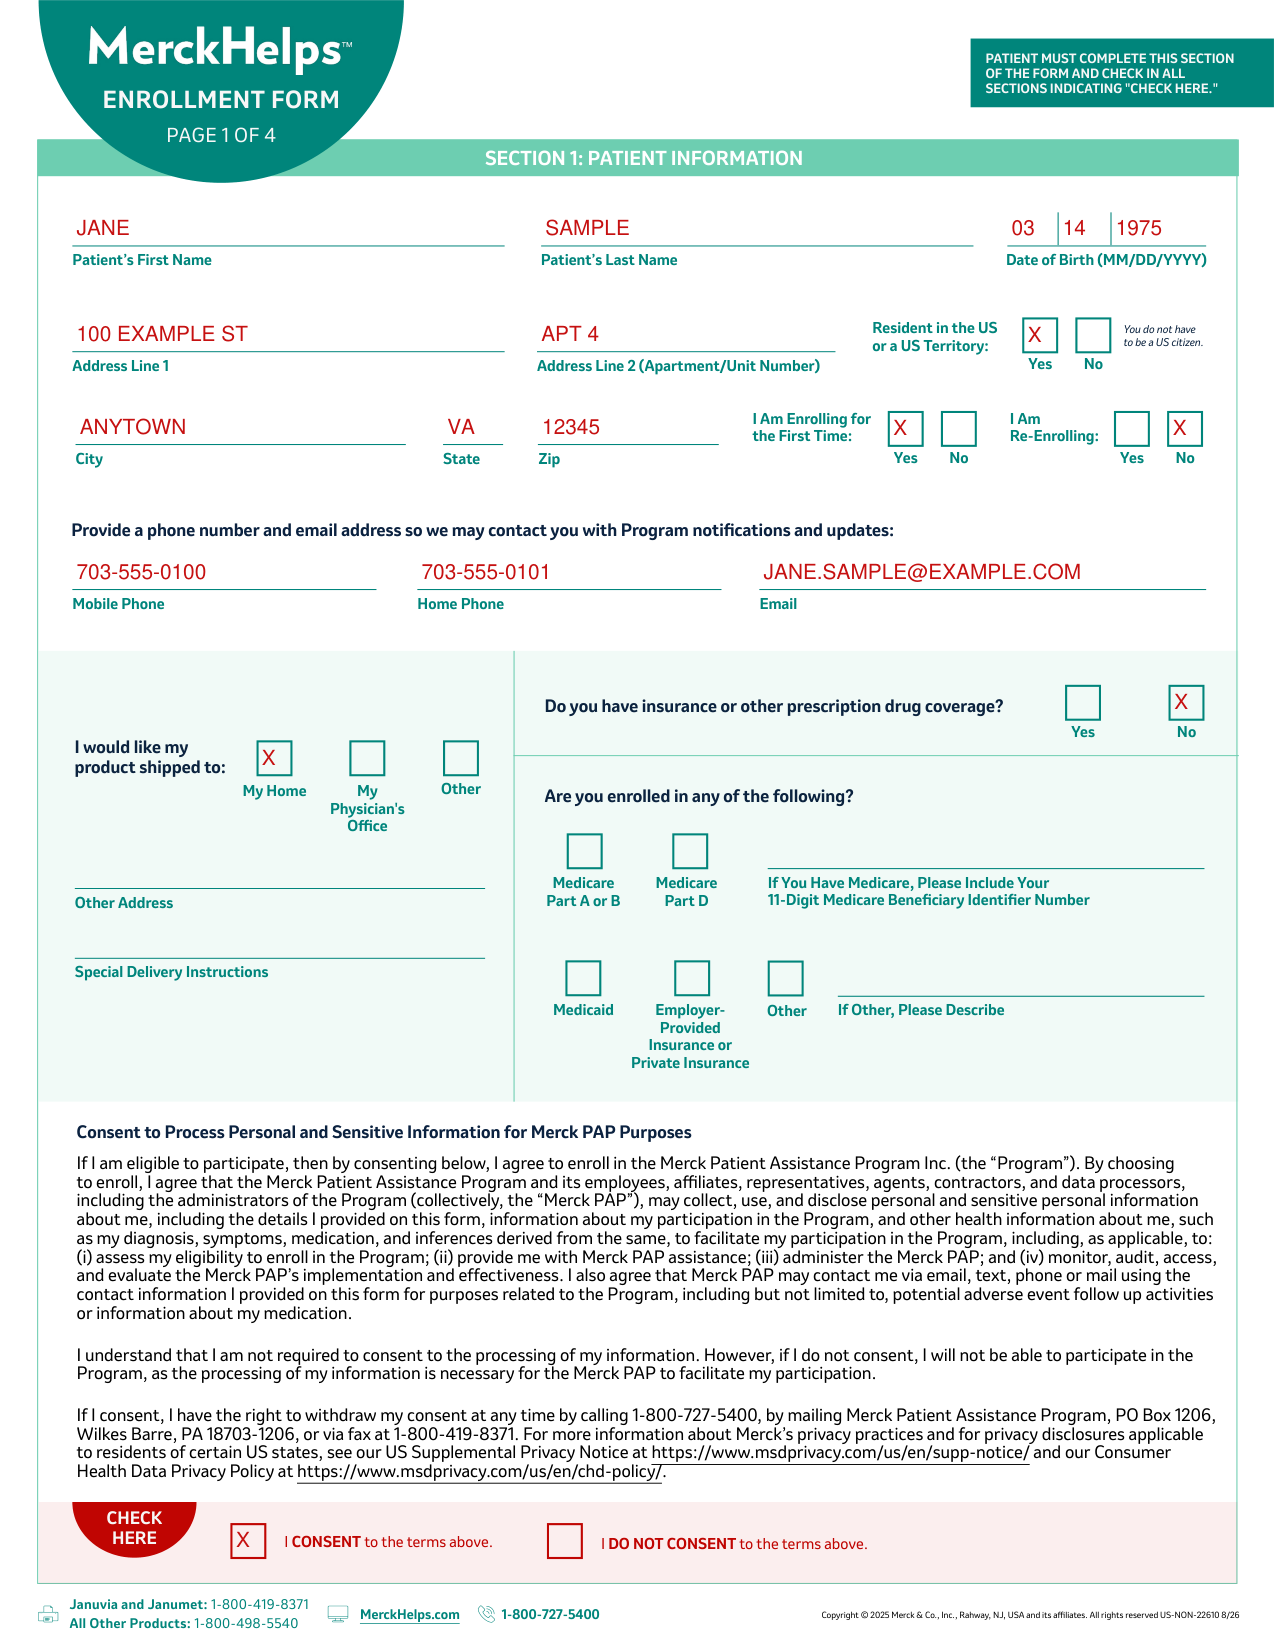
How to fill out Merck Patient Assistance Program application, box by box
Who can apply
To be eligible for Merck PAP, both the Patient AND the Prescribing Healthcare Professional must complete, sign, and date this Program application form and certify that a Healthcare Provider has prescribed the Patient a Merck medicine covered in the Merck Patient Assistance Program (Merck PAP).
The Patient currently resides in the United States or a United States Territory (the Patient does not need to be a United States citizen).
The Patient does not have an insurance plan or employer that participates in or is involved in any way with an alternative funding program that requires or encourages you to apply to the Merck Patient Assistance Program as a condition, requirement, or prerequisite for coverage of specific Merck medications.
The Patient cannot afford to pay for the Merck medicine and Merck PAP can verify the Patient meets the Program's financial eligibility criteria. Information about specific financial criteria levels is available by visiting MerckHelps.com or calling 1-800-727-5400.
Patient information
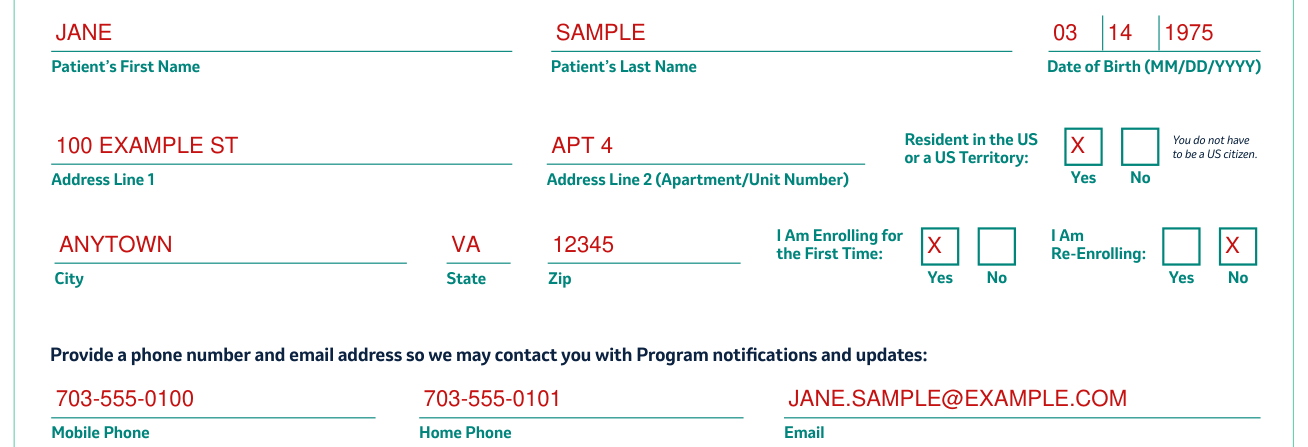
The Patient must complete Section 1: Patient Information and check in all sections indicating "CHECK HERE."
Enter the Patient's First Name, Patient's Last Name and Date of Birth (MM/DD/YYYY).
Mark Yes or No under Resident in the United States or a United States Territory: you do not have to be a United States citizen.
Enter Address Line 1, Address Line 2 (Apartment/Unit Number), City, State and Zip.
Mark Yes or No under I Am Enrolling for the First Time and under I Am Re-Enrolling.
Provide a phone number and email address for Program notifications and updates: Mobile Phone, Home Phone, Email.
Insurance or other coverage

Mark Yes or No for Do you have insurance or other prescription drug coverage?
Are you enrolled in any of the following
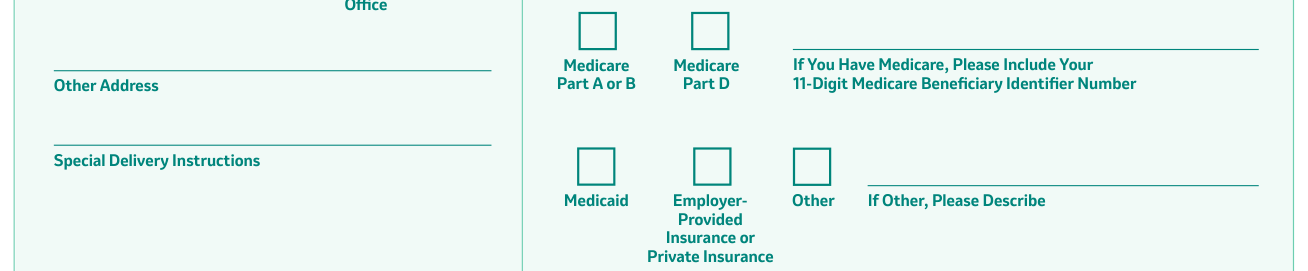
Under Are you enrolled in any of the following?, mark Medicare Part A or B, Medicare Part D, Medicaid, Employer-Provided Insurance or Private Insurance, and Other. If Other, Please Describe.
If You Have Medicare, Please Include Your 11-Digit Medicare Beneficiary Identifier Number.
Where the product is shipped
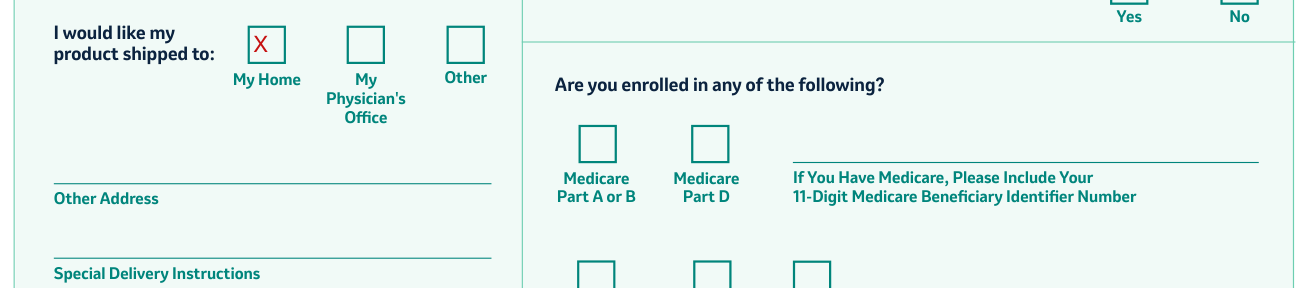
Under I would like my product shipped to, mark My Home, My Physician's Office or Other.
Consent to process personal information

Under Consent to Process Personal and Sensitive Information for Merck PAP Purposes, CHECK HERE for I CONSENT or I DO NOT CONSENT.
You are not required to consent to the processing of your information. However, if you do not consent, you will not be able to participate in the Program, as the processing of your information is necessary for the Merck PAP to facilitate your participation.
Section 2 signatures
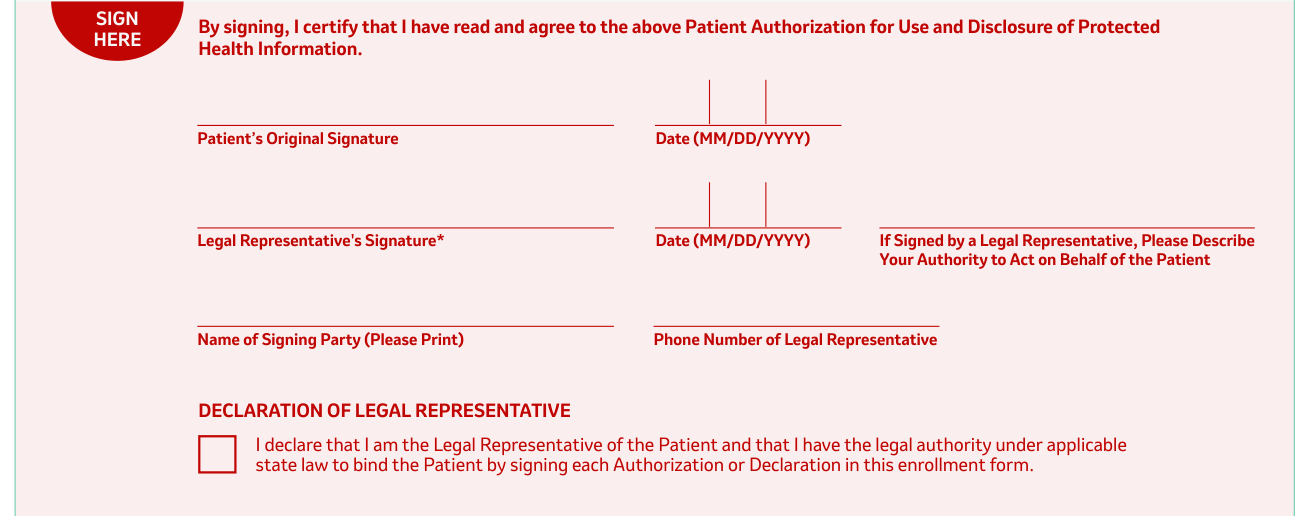
The Patient must complete Section 2: Patient Authorization and sign in all sections indicating "SIGN HERE."
By signing, certify that you have read and agree to the Patient Authorization for Use and Disclosure of Protected Health Information: sign Patient's Original Signature and enter the Date (MM/DD/YYYY).
If Signed by a Legal Representative, Please Describe Your Authority to Act on Behalf of the Patient, and fill in Legal Representative's Signature, Date (MM/DD/YYYY), Name of Signing Party (Please Print) and Phone Number of Legal Representative.
In Legal Representative's Signature*, a Legal Representative is a person who has legal authority under applicable law to bind you (the Patient) by signing each Authorization or Declaration in this enrollment form.
Household income
The Patient must complete Section 3: Income Verification and follow all signature instructions.
Provide current gross annual household income (your income before taxes), including Social Security and pension benefits: enter Total Gross Annual Household Income and Number of Household Members (Including Patient) Who Depend on This Income.
Option 1 or Option 2
Option 2: Authorizing Merck PAP and other individuals involved in administering the Merck PAP to obtain his/her consumer report and/or other information related to his/her credit report to determine the Patient's eligibility to participate in the Program. This verification will not affect the Patient's credit rating.
Patients should only sign this section if they are selecting Option 2: sign Patient's Original Signature and Date (MM/DD/YYYY).
Applicant declarations and signatures
Under Applicant Declarations and Authorization, certify that all of the information provided in this application, including household income, is complete and accurate; that you cannot afford this medication; and that you will not seek reimbursement or credit for this prescription from any insurer, health plan, or government program.
Under SIGN HERE, sign Patient's Original Signature and Date (MM/DD/YYYY).
Prescription information
The Prescriber must complete Section 4: Prescription Information and sign in all sections indicating "SIGN HERE."
Complete the prescription and product information (enter only one Merck product per line). This is the prescription. Please do not submit a prescription separate from this application. All controlled substance prescriptions must be submitted electronically (NPI: 1285159152) and separately from this enrollment form and must include your DEA number.
Enter Patient's First Name, Patient's Last Name and Date of Birth (MM/DD/YYYY); for Product/Strength 1 and Product/Strength 2, enter Directions for Use, Quantity and Refill (1, 2, or 3 Times).
Current medications
Enter the Patient's Current Medication(s) Including OTC.
Prescriber signature
Under SIGN HERE, sign Prescriber's Signature. Signature stamps cannot be accepted.
Prescriber information
Under Section 5: Prescriber Information, enter Prescriber's First Name, M.I., Prescriber's Last Name, Prescriber's NPI Number, Name of Facility/Site, Address Line 1 (PO Boxes Not Permitted), Address Line 2 (Suite/Building/Floor), City, State, Zip, Office Phone Number, Ext., Fax, Office Contact Name and Email.
Prescriber attestation and signature
Prescriber Attestation: certify that this prescription is medically appropriate for this Patient and that you will be supervising the Patient's treatments, and that you will not seek reimbursement or credit for this prescription from any insurer, health plan, or government program.
Sign Prescriber's Signature and enter the Date (MM/DD/YYYY).
More rules for Merck Patient Assistance Program application
You do not need to sign this Authorization in order to receive healthcare treatment or insurance benefits, but if you do not sign the Authorization, you will not be able to obtain assistance from the Merck PAP.
If you do not cancel this Authorization, the Authorization will expire 15 months from the date of signature (or the maximum period allowed by applicable state law, if less than 15 months).
Program assistance will terminate if the Program becomes aware of any fraud or if this medication is no longer prescribed for you.
Completing this application does not ensure that you will qualify for this Program.
Once the Patient and Prescriber have completed all sections of the enrollment form, submit the enrollment form to the Merck Patient Assistance Program. Failure to include all information may result in delayed processing times.
Do not include this cover page when faxing the completed and signed enrollment form.
Before you go
Check your eligibility at MerckHelps.com.
Both the Patient and the Prescribing Healthcare Professional must complete all sections of this form.
Common questions about Merck Patient Assistance Program application
Where do I file it?
How Can I Submit My Completed Application? FAX Januvia and Janumet: 1-800-419-8371, All Other Products: 1-800-498-5540. MAIL Merck Patient Assistance Program PO Box 1206, Wilkes Barre, PA 18703-1206. ONLINE Apply online at www.MerckHelps.com. For inquiries, call 1-800-727-5400.
Are there fees?
Applying to Merck PAP is FREE. Merck PAP is not associated with any individuals or organizations who may charge Patients a fee to assist them in completing enrollment forms.
Sources
[1] Merck Patient Assistance Program application (US-NON-22610 8/26), Merck Patient Assistance Program, Inc. (the Official source link on this page).