

MetLife Statement of Health at a glance
What it is: Statement of Health: medical information that will be used by MetLife to determine insurability.
Who signs: Sign & Date Here: Applicant Signature, Date (Mo./Day/Yr.). Sign, Date & Return: Signature of Proposed Insured or Print Name of Proposed Insured, Date (Mo./Day/Yr.).
A filled-in MetLife Statement of Health example: an employee requests Dependent Life (or Buy-Up) for a spouse
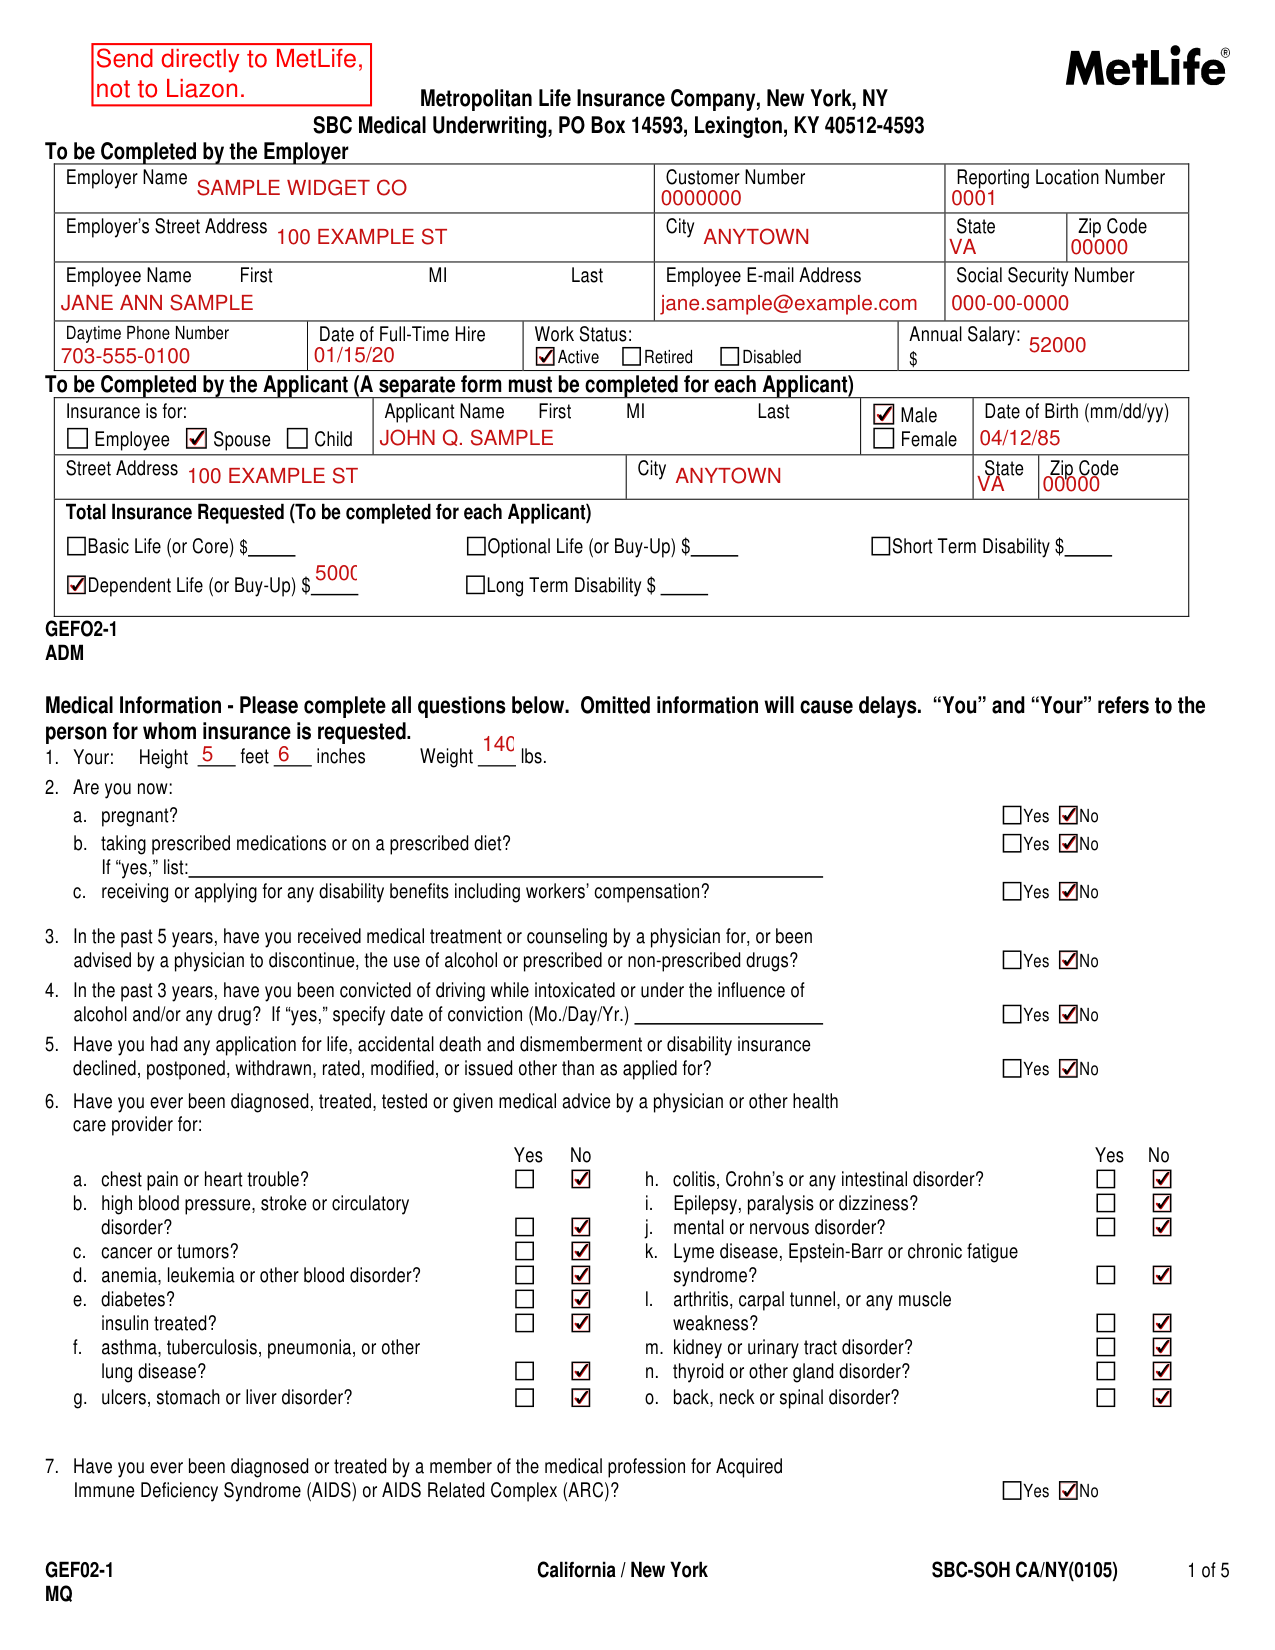
How to fill out MetLife Statement of Health, box by box
To be Completed by the Employer
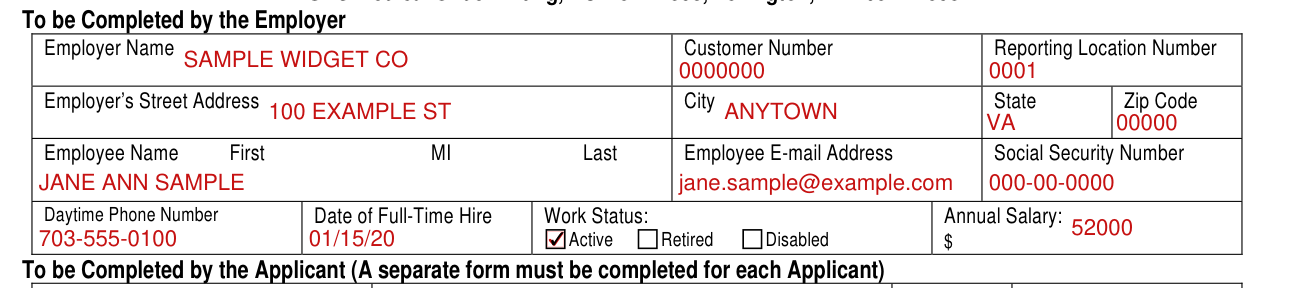
To be Completed by the Employer: Employer Name, Customer Number, Reporting Location Number, Employer's Street Address, City, State, Zip Code, Employee Name First MI Last, Employee E-mail Address and Social Security Number.
Enter the Daytime Phone Number, Date of Full-Time Hire and Annual Salary $, and mark the Work Status: Active, Retired or Disabled.
To be Completed by the Applicant
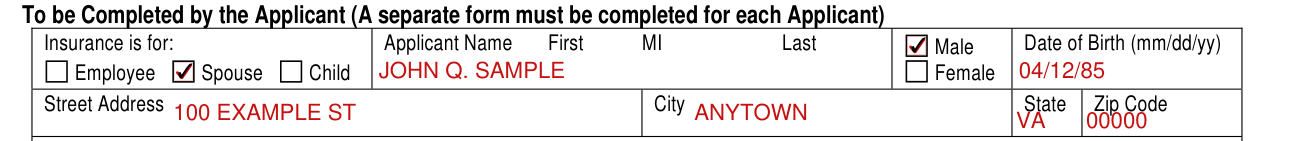
To be Completed by the Applicant: mark Insurance is for Employee, Spouse or Child, then enter the Applicant Name First MI Last, mark Male or Female and enter the Date of Birth (mm/dd/yy).
A separate form must be completed for each Applicant.
Enter the Street Address, City, State and Zip Code.
Total Insurance Requested
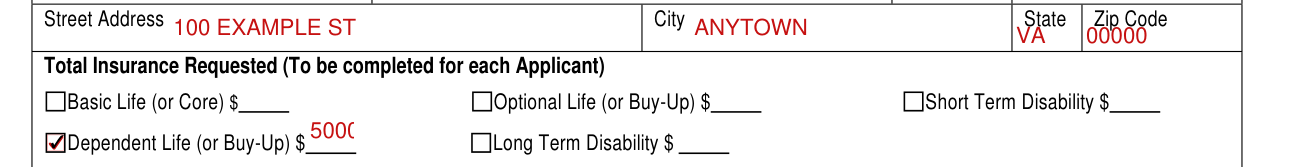
Total Insurance Requested (To be completed for each Applicant): Basic Life (or Core) $, Dependent Life (or Buy-Up) $, Optional Life (or Buy-Up) $, Short Term Disability $ and Long Term Disability $.
Medical Information
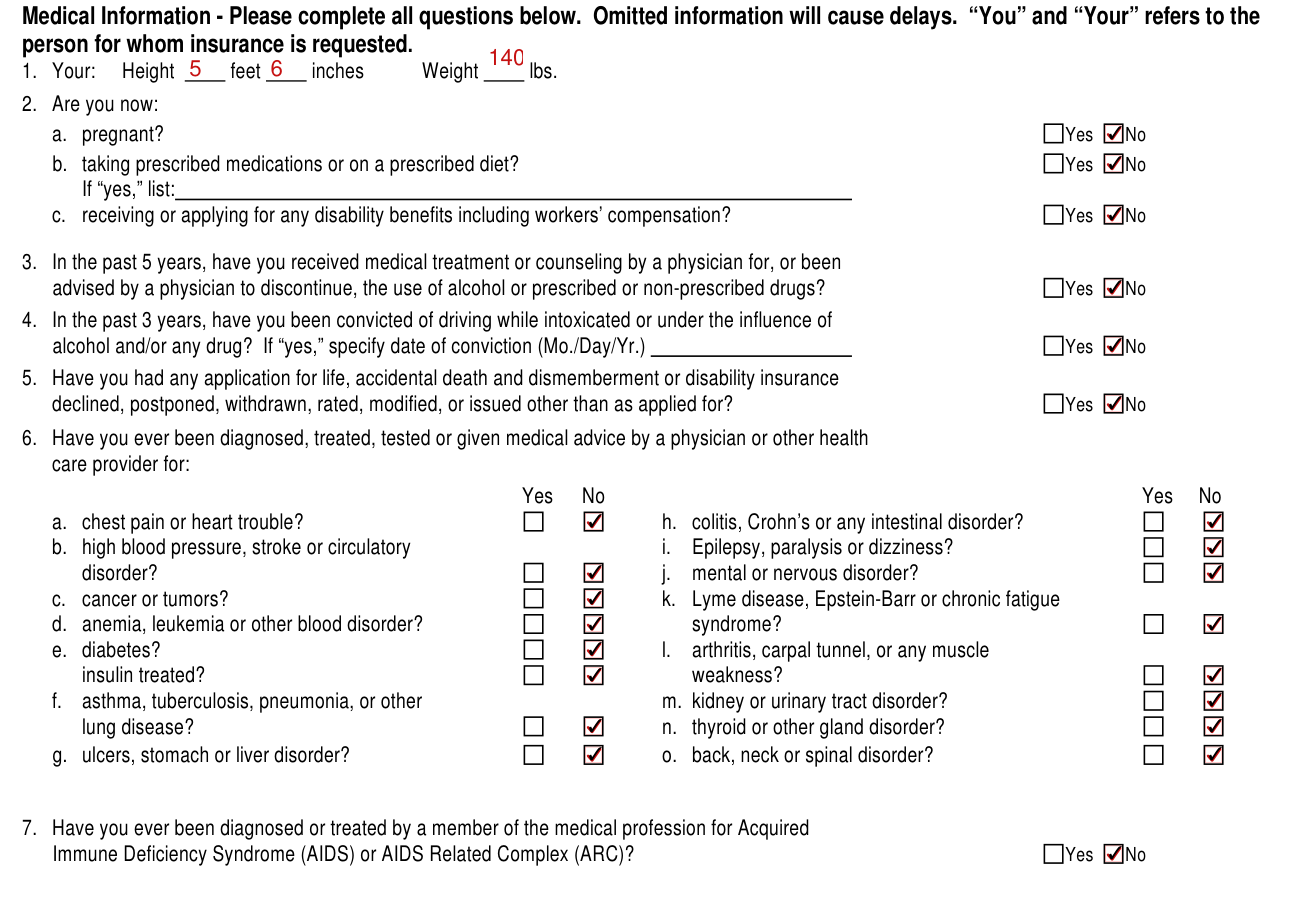
Medical Information - Please complete all questions. Omitted information will cause delays.
“You” and “Your” refers to the person for whom insurance is requested.
Enter Your Height in feet and inches and Weight in lbs.
Are you now: pregnant? taking prescribed medications or on a prescribed diet? If “yes,” list: receiving or applying for any disability benefits including workers' compensation? Mark Yes or No for each.
In the past 5 years, have you received medical treatment or counseling by a physician for, or been advised by a physician to discontinue, the use of alcohol or prescribed or non-prescribed drugs? Mark Yes or No.
In the past 3 years, have you been convicted of driving while intoxicated or under the influence of alcohol and/or any drug? If “yes,” specify date of conviction (Mo./Day/Yr.). Mark Yes or No.
Have you had any application for life, accidental death and dismemberment or disability insurance declined, postponed, withdrawn, rated, modified, or issued other than as applied for? Mark Yes or No.
Have you ever been diagnosed, treated, tested or given medical advice by a physician or other health care provider for: a. chest pain or heart trouble? b. high blood pressure, stroke or circulatory disorder? c. cancer or tumors? d. anemia, leukemia or other blood disorder? e. diabetes? insulin treated? f. asthma, tuberculosis, pneumonia, or other lung disease? g. ulcers, stomach or liver disorder? h. colitis, Crohn's or any intestinal disorder? i. Epilepsy, paralysis or dizziness? j. mental or nervous disorder? k. Lyme disease, Epstein-Barr or chronic fatigue syndrome? l. arthritis, carpal tunnel, or any muscle weakness? m. kidney or urinary tract disorder? n. thyroid or other gland disorder? o. back, neck or spinal disorder? Mark Yes or No for each.
Have you ever been diagnosed or treated by a member of the medical profession for Acquired Immune Deficiency Syndrome (AIDS) or AIDS Related Complex (ARC)? Mark Yes or No.
Have you ever had persistent cough, pneumonia, chest discomfort

Have you ever had persistent cough, pneumonia, chest discomfort, muscle weakness, unexplained weight loss of 10 pounds or more, swollen glands, patches in the mouth, visual disturbance, or recurring diarrhea, fever or infection? Mark Yes or No.
Personal Physician
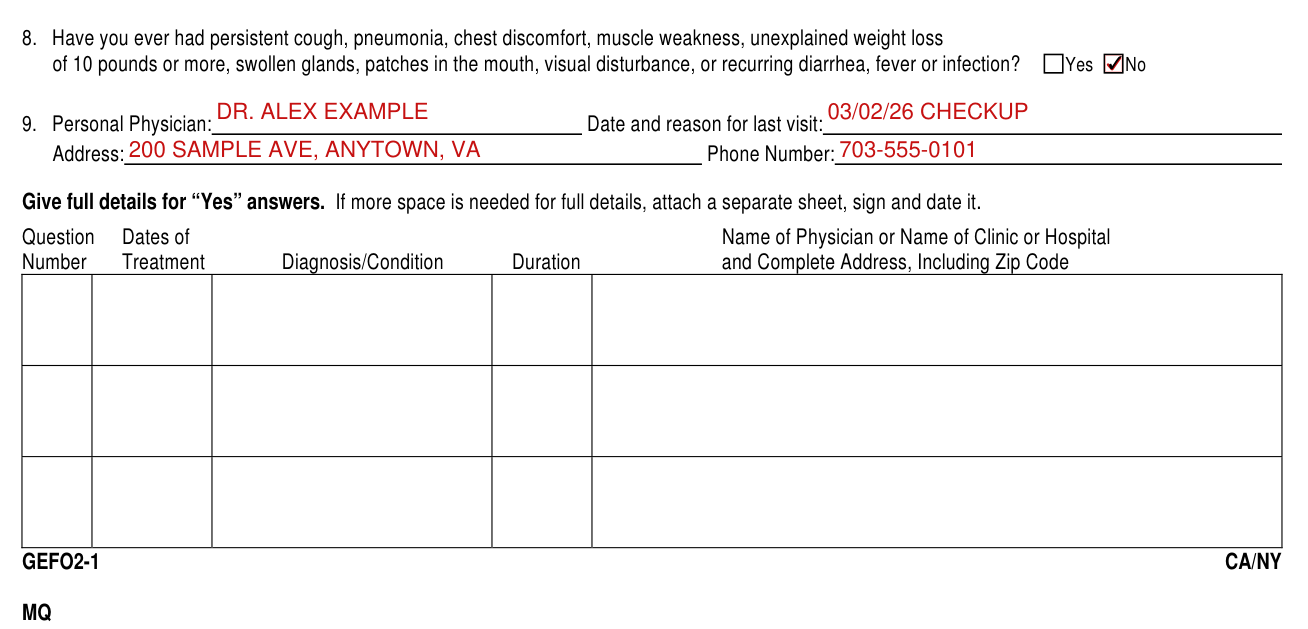
Personal Physician: enter the Personal Physician, the Date and reason for last visit, the Address and the Phone Number.
Give full details for “Yes” answers.
If more space is needed for full details, attach a separate sheet, sign and date it. Enter the Question Number, Dates of Treatment, Diagnosis/Condition, Duration, and the Name of Physician or Name of Clinic or Hospital and Complete Address, Including Zip Code.
More rules for MetLife Statement of Health
Medical Information Form Will Not Be Processed Without Accompanying Authorization Form.
If the proposed insured does not sign this Authorization, that person's enrollment for group insurance cannot be processed.
This authorization will expire 24 months from the date on this form or sooner if prescribed by law.
If you reside in or are applying for insurance under a policy issued in one of the following states, please read the applicable warning.
New York [only applies to Accident and Health Benefits (AD&D/Disability/Dental)]: Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance containing any materially false information, or conceals for the purpose of misleading, information concerning any fact material thereto, commits a fraudulent insurance act, which is a crime, and shall also be subject to a civil penalty not to exceed five thousand dollars and the stated value of the claim for each such violation.
Florida: Any person who knowingly and with intent to injure, defraud, or deceive any insurer files a statement of claim or an application containing any false, incomplete, or misleading information is guilty of a felony of the third degree.
Massachusetts: Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance containing any materially false information or conceals, for the purpose of misleading, information concerning any fact material thereto commits a fraudulent insurance act, and may subject such person to criminal and civil penalties.
New Jersey: Any person who includes any false or misleading information on an application for an insurance policy is subject to criminal and civil penalties.
Oklahoma: Any person who knowingly, and with intent to injure, defraud or deceive any insurer, makes any claim for the proceeds of an insurance policy containing any false, incomplete or misleading information is guilty of a felony.
Kansas and Oregon: Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance containing any materially false information or conceals, for the purpose of misleading, information concerning any fact material thereto may be guilty of insurance fraud, and may be subject to criminal and civil penalties.
Virginia: Any person who, with the intent to defraud or knowing that he is facilitating a fraud against an insurer, submits an application containing a false or deceptive statement may have violated state law.
Common questions about MetLife Statement of Health
Who signs it?
The applicant signs and dates the Applicant Signature line, and the proposed insured signs and dates the Signature of Proposed Insured line. On the Authorization: if a child proposed for insurance is age 18 or over, the child must sign this Authorization. If the child is under age 18, a Personal Representative for the child must sign, and indicate the legal relationship between the Personal Representative and the proposed insured.
Where do I file it?
Send directly to MetLife, not to Liazon: SBC Medical Underwriting, PO Box 14593, Lexington, KY 40512-4593.
Is there a penalty?
Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance or a statement of claim containing any materially false information or conceals, for the purpose of misleading, information concerning any fact material thereto commits a fraudulent insurance act, which is a crime and subjects such person to criminal and civil penalties.
What am I certifying when I sign?
Declaration - I have read this Statement of Health and declare that all information given is true and complete to the best of my knowledge and belief.
Sources
[1] MetLife Statement of Health (GEF02-1 California / New York SBC-SOH CA/NY(0105)), Metropolitan Life Insurance Company (the Official source link on this page).
