

Form MV-80L at a glance
What it is: The Eye Test Report for the Medical Review Unit is for the Low Vision Program: for persons with corrected vision of less than 20/40 but not less than 20/70, or telescopic lens wearers.
Who signs: The practitioner signs (Practitioner's Signature) and dates (Date). Telescopic lens wearers must complete the certification at the bottom of page 2 of the form only for a first-time evaluation, and sign on the Signature of Patient line.
Where and when to file: Return both pages of the completed form to the Medical Review Unit at the address shown at the top of page 1 of the form (Room 337, 6 Empire State Plaza, Albany, NY 12228) or fax it to (518) 402-2991. The MV-80L must be completed by a physician, ophthalmologist or optometrist, and must be based on an examination performed within 60 days.
A filled-in Form MV-80L example: a first-time telescopic lens wearer

How to fill out Form MV-80L, box by box
Tap a group of boxes to open it, and a picture to see it full size.
Instructions on page 1 of the form
If this completed form is not returned to the Medical Review Unit, you may not renew your license and you may be suspended.
Common mistake: Do not go into a DMV office until you have submitted your completed MV-80L to the Medical Review Unit at the address shown at the top of page 1 of the form and have received a response letter in the mail from them.
The MV-80L must be completed by a physician, ophthalmologist or optometrist, and must be based on an examination performed within 60 days.
Return both pages of the completed form to the Medical Review Unit at the address shown at the top of page 1 of the form (Room 337, 6 Empire State Plaza, Albany, NY 12228) or fax it to (518) 402-2991.
PATIENT: complete this section
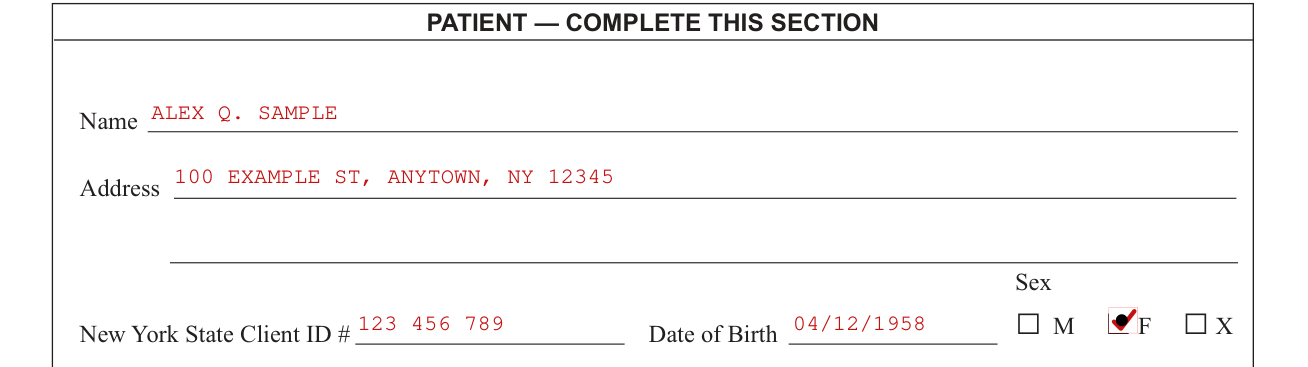
In the PATIENT section, write the Name and the Address.
Write the New York State Client ID # and the Date of Birth, and mark the Sex: M, F or X.
PRACTITIONER: the patient and the examination
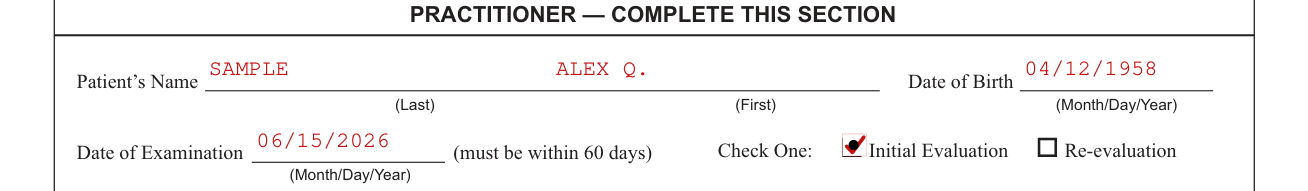
In the PRACTITIONER section, write the Patient's Name (Last, First) and the Date of Birth (Month/Day/Year).
Write the Date of Examination (Month/Day/Year); it must be within 60 days. Check One: Initial Evaluation or Re-evaluation.
PRACTITIONER: Visual Acuity (Snellen Method)

Visual Acuity (Snellen Method): check the appropriate box to identify how visual acuity was achieved, then give the visual acuity.
With corrective lenses: write Right eye 20/ and/or left eye 20/ and Both 20/.
Without corrective lenses is one of the boxes to check to identify how visual acuity was achieved.
With telescopic lenses only: write Through telescopic lenses right eye 20/ and/or left eye 20/, and Through carrier lenses right eye 20/ and/or left eye 20/.
PRACTITIONER: telescopic lenses and the field of vision

If telescopic lenses are used, write the date the patient received them.
Does the patient meet or exceed the minimum acceptable horizontal, binocular field of vision of 140 degrees? Check Yes or No.
The test object size for determining horizontal, binocular field of vision must be either a white 3 mm size test object at a one-half meter distance, or a white 6mm size test object at a one meter distance, or the equivalent angular size for any test distance.
If telescopic lenses, did the patient achieve his/her horizontal, binocular field of vision with the use of field expanders? Check Yes or No.
PRACTITIONER: medical condition and re-evaluation

Write the medical condition(s) that caused the present loss of the patient's visual acuity.
Patient should be re-evaluated every: check 6 Months or Year.
Is this condition stable at this time? Check Yes or No.
PRACTITIONER: restrictions and opinion

Check the restriction(s) recommended: Day Driving Only, Full-View Mirror, No Limited Access Roads or None.
In the opinion of the practitioner, would the patient's condition interfere with the safe operation of a motor vehicle? Check Yes or No.
If Yes, explain in the space provided, or attach an explanation on the practitioner's letterhead.
PRACTITIONER: signature, name, license number, address and telephone

Practitioner: the information is true, complete and best reflects my professional judgement.
The practitioner signs (Practitioner's Signature) and dates (Date).
Write the Practitioner's Name (please print), the Certificate or License Number, the Address and the Telephone Number.
Telescopic lens wearers: certification for a first-time evaluation

Telescopic lens wearers must complete the certification at the bottom of page 2 of the form only for a first-time evaluation, and sign on the Signature of Patient line.
Telescopic lens wearers: I certify that I have successfully completed the minimum training requirements for telescopic lens wearers as outlined in Part 5 of the Commissioner's Regulations, and that I received the training from:
Write the Name of Trainer, the Telephone Number, the Address of Trainer and the Date Training Completed.
Low Vision Program, telescopic lenses and corrected vision
You are currently in the Low Vision Program
If you are currently in the Low Vision Program, you do not need to submit form MV-80L.
The Medical Review Periodic Eye Test form MV-80L.1 will be mailed to you every six or twelve months based on your eye care provider's recommendation.
If there are no changes or your license is not due to expire within the next year, you have satisfied the requirements and will not receive anything in the mail from the Medical Review Unit.
You have corrected vision of less than 20/40 but not less than 20/70
Minimum standard for individuals with corrected vision of less than 20/40, but not less than 20/70: horizontal, binocular field of vision must be no less than 140 degrees.
You wear telescopic lenses
Minimum standard for telescopic lens wearers: must have been fitted with, trained to use, and used telescopic lenses for at least 60 days prior to filing this form.
Common mistake: Clip-on or hand-held telescopic lenses are not acceptable.
Visual acuity (Snellen Method) through telescopic portion in either or both eyes must be no less than 20/40.
Visual acuity (Snellen Method) through carrier lens in either or both eyes must be no less than 20/100.
Total horizontal, binocular field of vision (no field expanders) must be no less than 140 degrees.
A telescopic lens wearer must pass a road test if he/she has not taken a road test while wearing his/her telescopic lenses.
Eligible for a Class D or DJ driver license only.
Ineligible for a commercial driver license (CDL), a motorcycle license or a moped license.
Common questions about Form MV-80L
How do I submit my eye test to NY DMV?
Return both pages of the completed form to the Medical Review Unit at the address shown at the top of page 1 of the form (Room 337, 6 Empire State Plaza, Albany, NY 12228) or fax it to (518) 402-2991.
Is there a deadline?
The MV-80L must be completed by a physician, ophthalmologist or optometrist, and must be based on an examination performed within 60 days.
Is there a penalty for filing late?
If this completed form is not returned to the Medical Review Unit, you may not renew your license and you may be suspended.
Sources
[1] Form MV-80L (5/22), Eye Test Report for Medical Review Unit, New York State Department of Motor Vehicles (the Official source link on this page).
