
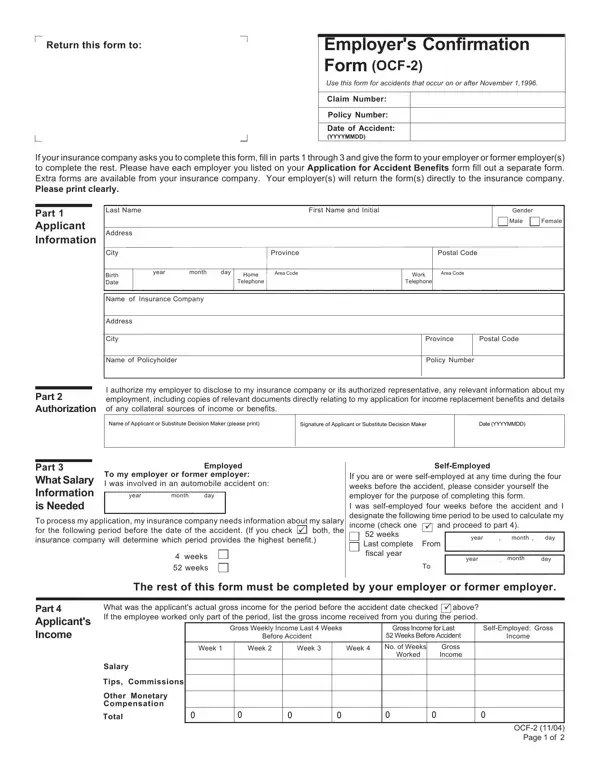
Form OCF-2 at a glance
What it is: The Employer's Confirmation Form (OCF-2) is for accidents that occur on or after November 1, 1996.
Who signs: Enter the Name of applicant or substitute decision maker, sign as Signature of applicant or substitute decision maker and enter the Date of signature (yyyy/mm/dd). The employer signs as Signature of employer, then enters the Date (yyyy/mm/dd), Employer name and Title.
A filled-in Form OCF-2 example: an applicant fills out parts 1 and 2

How to fill out Form OCF-2, box by box
Return this form to, Claim Number, Policy Number and Date of Accident

Fill in Return this form to:, Claim Number, Policy Number and Date of Accident (yyyy/mm/dd).
Part 1 - Applicant information
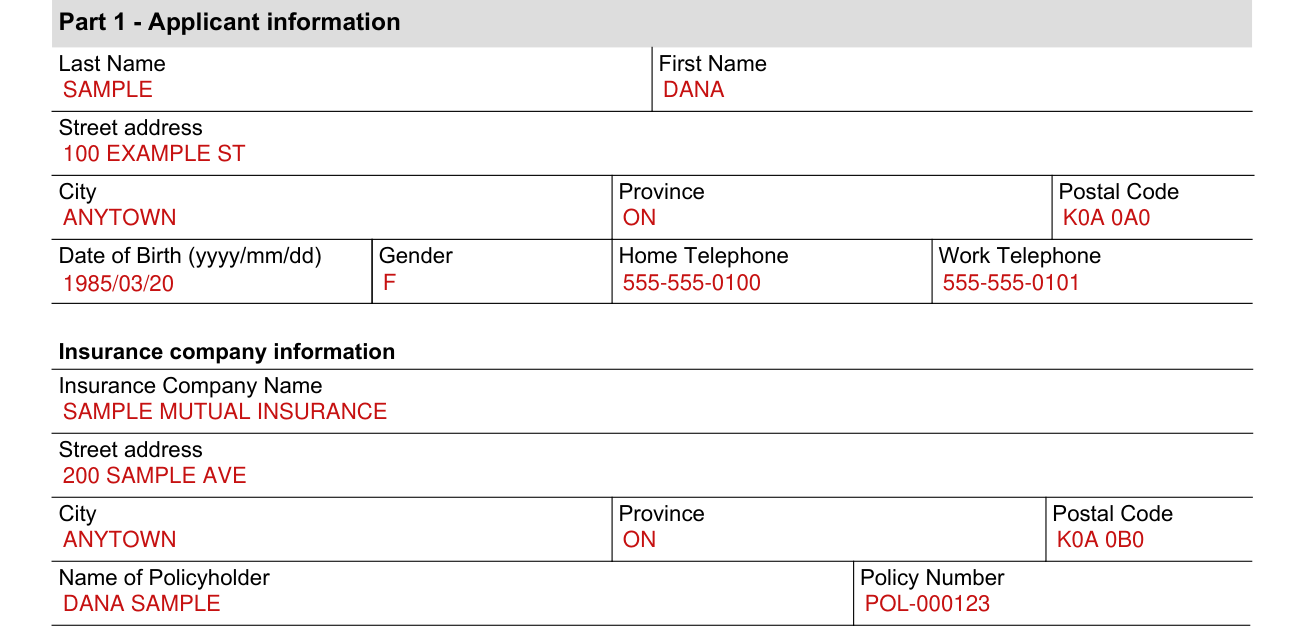
In Part 1 - Applicant information, enter Last Name, First Name, Street address, City, Province, Postal Code, Date of Birth (yyyy/mm/dd), Gender, Home Telephone and Work Telephone.
Under Insurance company information, enter Insurance Company Name, Street address, City, Province, Postal Code, Name of Policyholder and Policy Number.
Part 2 - Authorization

Part 2 - Authorization: I authorize my employer to disclose to my insurance company or its authorized representative, any relevant information about my employment, including copies of relevant documents directly relating to my application for income replacement benefits and details of any collateral sources of income or benefits.
Part 3 - What salary information is needed
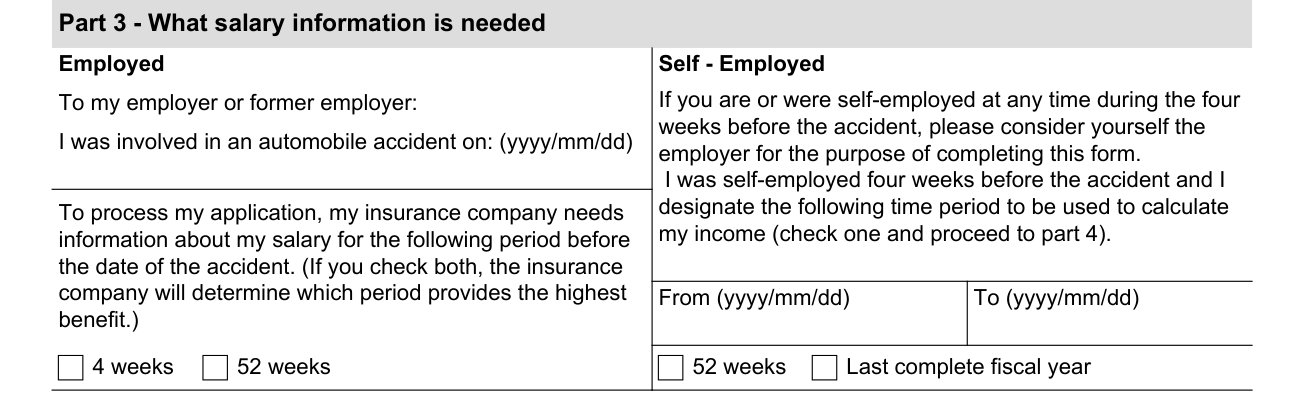
Enter yyyy/mm/dd after: I was involved in an automobile accident on:
To process my application, my insurance company needs information about my salary for the following period before the date of the accident: check 4 weeks or 52 weeks.
If you check both, the insurance company will determine which period provides the highest benefit.
If you are or were self-employed at any time during the four weeks before the accident, please consider yourself the employer for the purpose of completing this form.
I was self-employed four weeks before the accident and I designate the following time period to be used to calculate my income (check one and proceed to part 4).
Enter From (yyyy/mm/dd) To (yyyy/mm/dd), or check 52 weeks or Last complete fiscal year.
Part 4 - Applicant's income
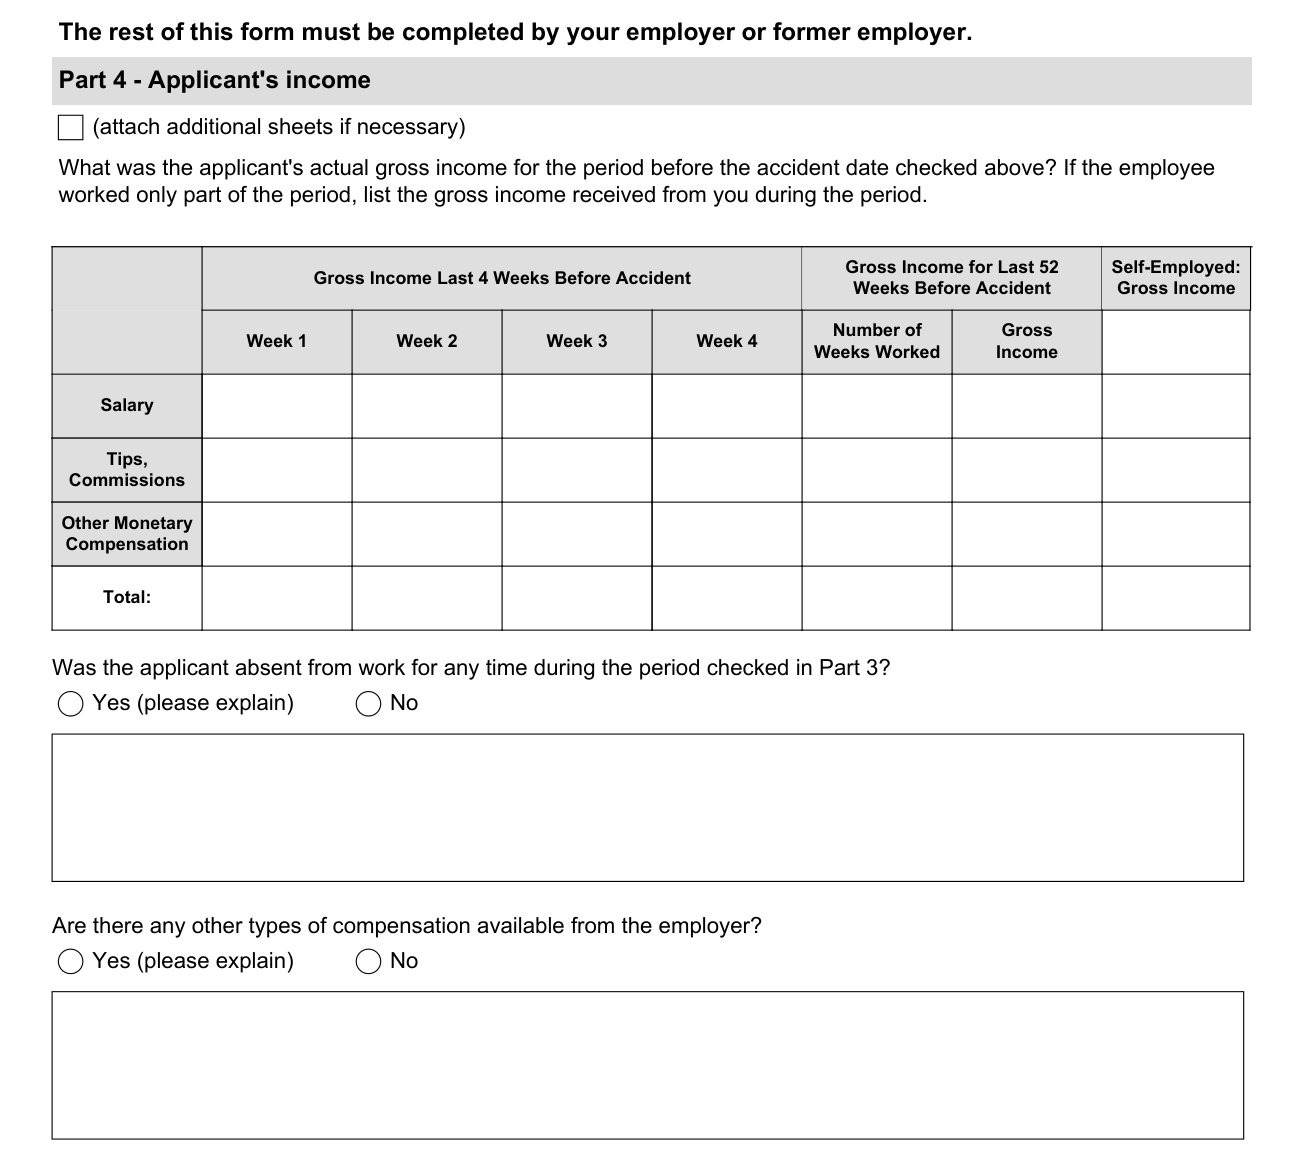
Part 4 - Applicant's income (attach additional sheets if necessary): What was the applicant's actual gross income for the period before the accident date checked?
If the employee worked only part of the period, list the gross income received from you during the period.
Under Gross Income Last 4 Weeks Before Accident, enter Salary, Tips, Commissions and Other Monetary Compensation for Week 1, Week 2, Week 3 and Week 4, and the Total.
Under Gross Income for Last 52 Weeks Before Accident and Self-Employed: Gross Income, enter the Number of Weeks Worked and the Gross Income.
Was the applicant absent from work for any time during the period checked in Part 3? Yes (please explain) No
Are there any other types of compensation available from the employer? Yes (please explain) No
Part 5 - Other benefits

Part 5 - Other benefits: To your knowledge, is the applicant eligible to receive the following benefits?
Income Continuation Benefit (short-term or long-term disability plan) Yes No, with the Insurance company and Policy number.
Supplementary Medical, Rehabilitation or Attendant Care Benefits Yes No, with the Insurance company and Policy number.
Sick leave Yes No Did applicant use sick credits following the auto accident? Yes No
Mark Yes or No for each: Is the applicant a member of a union? Does or did the applicant contribute to the Canada Pension Plan or a similar plan? Was a claim filed with the Workplace Safety and Insurance Board as a result of this accident?
Part 6 - Employment details
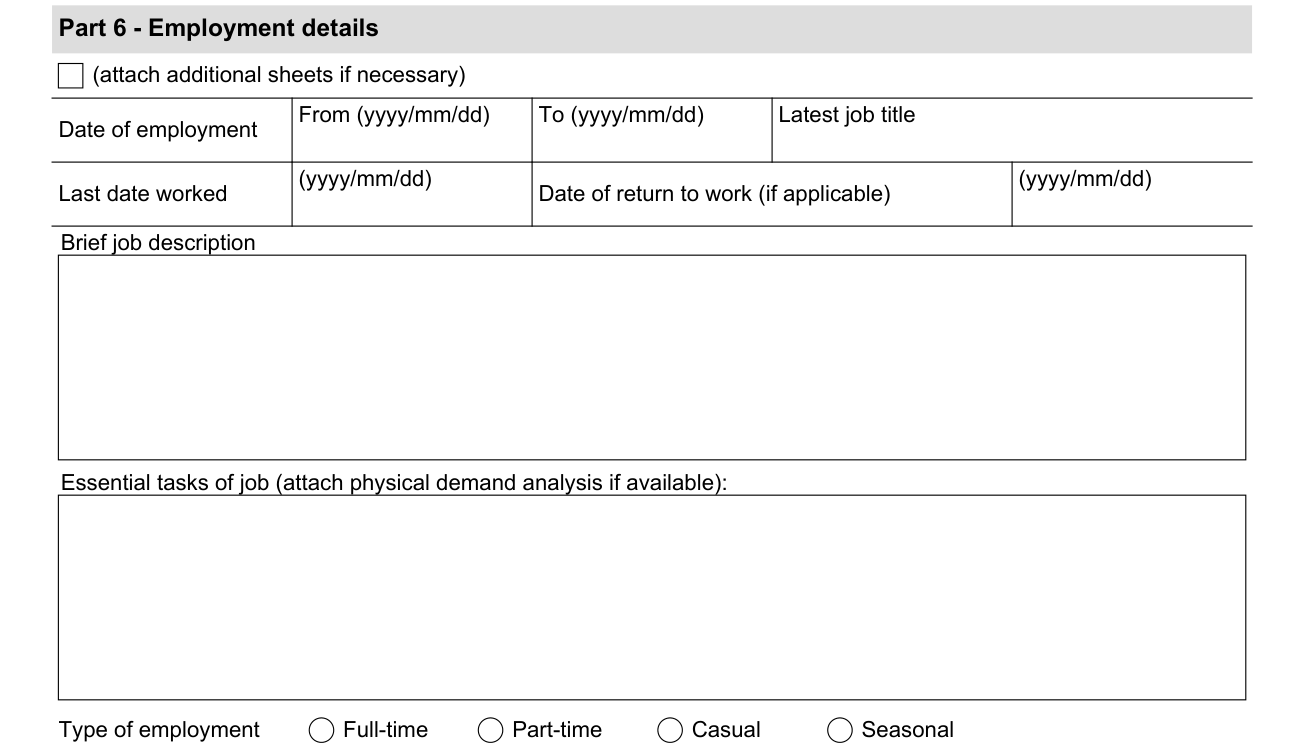
Part 6 - Employment details (attach additional sheets if necessary).
Enter the Date of employment From (yyyy/mm/dd) To (yyyy/mm/dd), the Latest job title, the Last date worked (yyyy/mm/dd) and the Date of return to work (if applicable) (yyyy/mm/dd).
Enter the Brief job description and the Essential tasks of job (attach physical demand analysis if available): and mark the Type of employment Full-time, Part-time, Casual or Seasonal.
Part 7 - Employer information
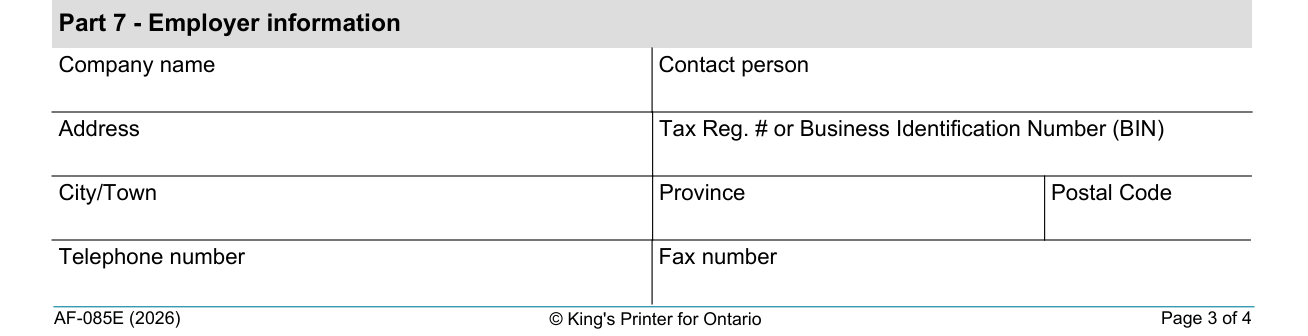
In Part 7 - Employer information, enter Company name, Contact person, Address, Tax Reg. # or Business Identification Number (BIN), City/Town, Province, Postal Code, Telephone number and Fax number.
Part 8 - Signature
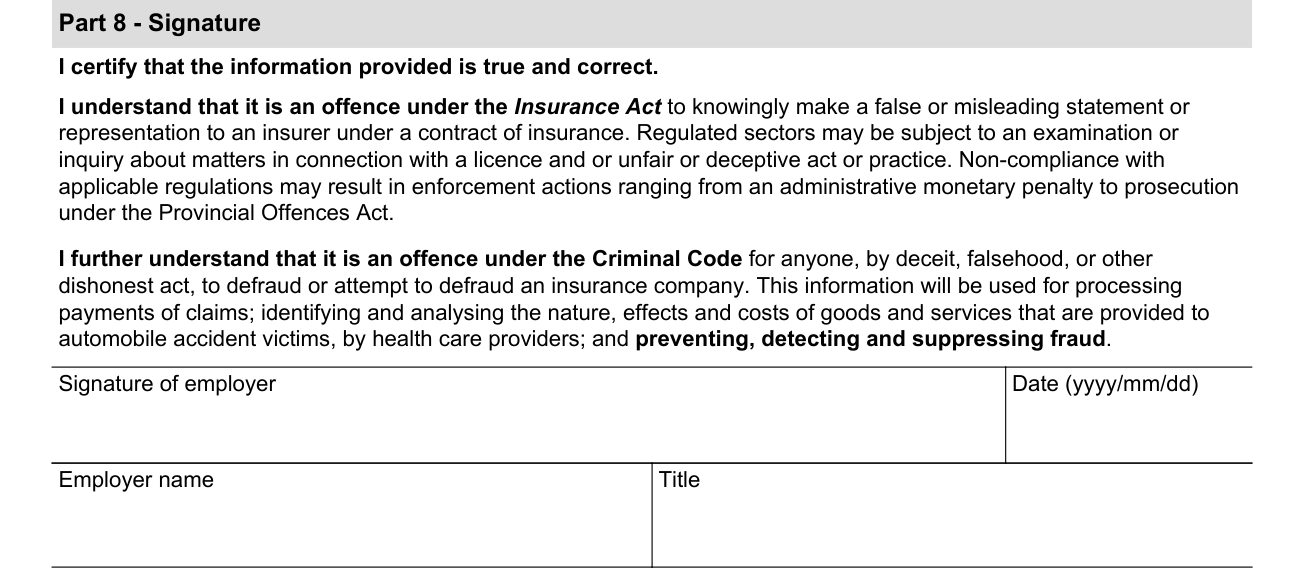
By signing Part 8 - Signature, you certify that the information provided is true and correct.
I understand that it is an offence under the Insurance Act to knowingly make a false or misleading statement or representation to an insurer under a contract of insurance.
Non-compliance with applicable regulations may result in enforcement actions ranging from an administrative monetary penalty to prosecution under the Provincial Offences Act.
I further understand that it is an offence under the Criminal Code for anyone, by deceit, falsehood, or other dishonest act, to defraud or attempt to defraud an insurance company.
The employer signs as Signature of employer, then enters the Date (yyyy/mm/dd), Employer name and Title.
Common questions about Form OCF-2
What is the OCF2 form?
The Employer's Confirmation Form (OCF-2) is for accidents that occur on or after November 1, 1996. If your insurance company asks you to complete this form, fill in parts 1 through 3 and give the form to your employer or former employer(s) to complete the rest. Please have each employer you listed on your Application for Accident Benefits form fill out a separate form. Extra forms are available from your insurance company. Your employer(s) will return the form(s) directly to the insurance company. Please print clearly
Sources
[1] Employer's Confirmation Form (OCF-2), AF-085E (2026), Financial Services Regulatory Authority of Ontario (the Official source link on this page).