

Form 801 at a glance
What it is: Form 801 is the Report of Job Injury or Illness.
Who signs: Worker signature: By my signature, I am making a claim for workers' compensation benefits. If you do not intend to file a workers' compensation claim with the insurance company, do not sign the signature line. Employer signature: By my signature, I acknowledge I am responsible for notifying my workers' compensation insurance company within five days of knowledge of the claim.
A filled-in Form 801 example: a worker reports a sprained foot
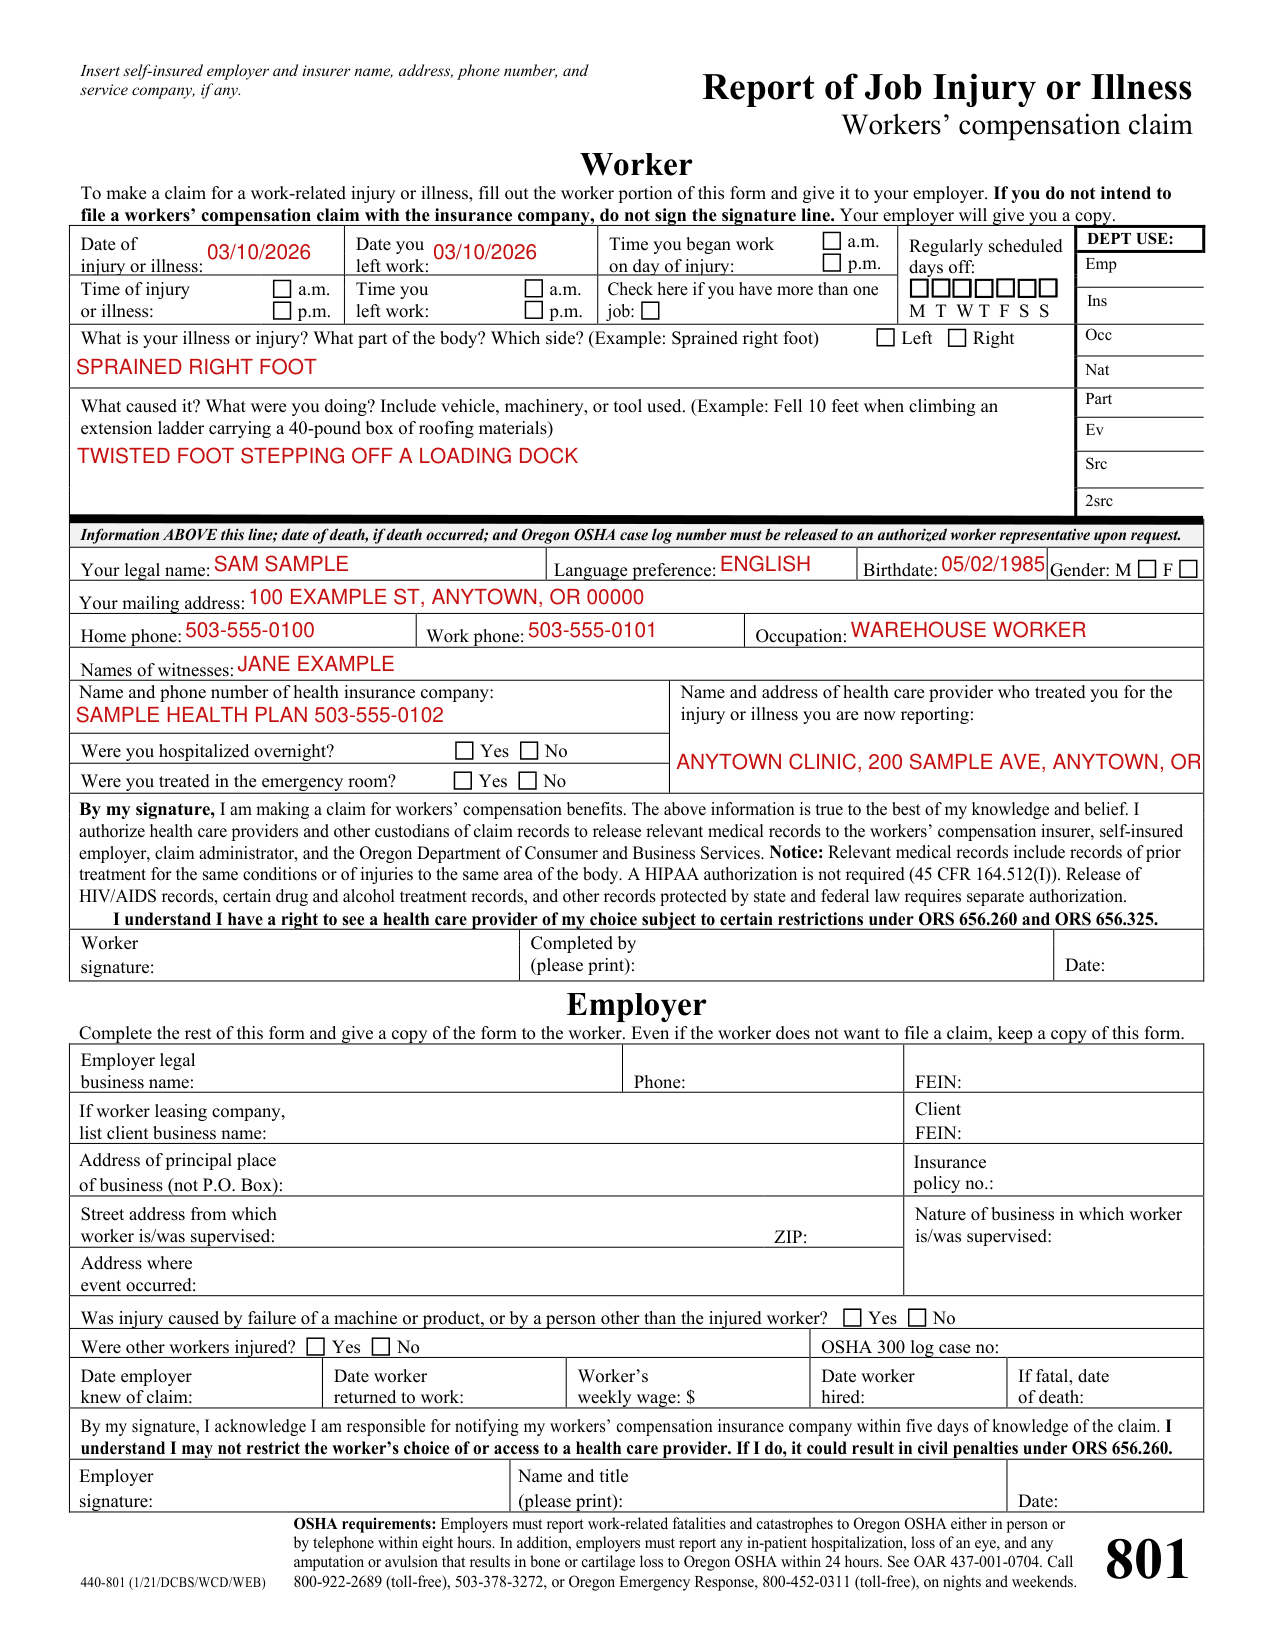
How to fill out Form 801, box by box
Date of injury or illness, days off and what caused it
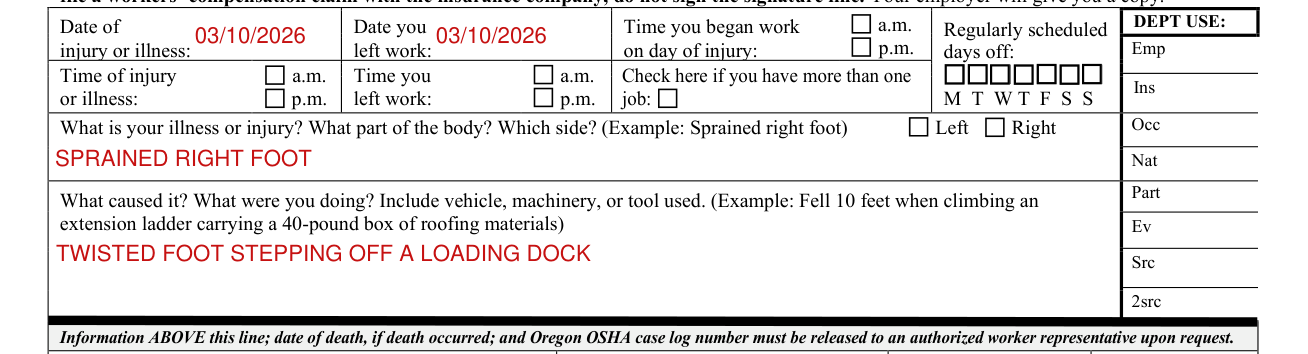
Enter the Date of injury or illness and the Date you left work.
Check the boxes for the Regularly scheduled days off.
What is your illness or injury? What part of the body? Which side? (Example: Sprained right foot)
In the box for What caused it? What were you doing?, include vehicle, machinery, or tool used. (Example: Fell 10 feet when climbing an extension ladder carrying a 40-pound box of roofing materials)
About you and your care

Enter Your legal name, Language preference, Birthdate and Gender.
Enter Your mailing address, Home phone, Work phone and Occupation.
Enter Names of witnesses and Name and phone number of health insurance company.
Enter the Name and address of health care provider who treated you for the injury or illness you are now reporting, and mark Yes or No for Were you hospitalized overnight?
Employer legal business name and the rest
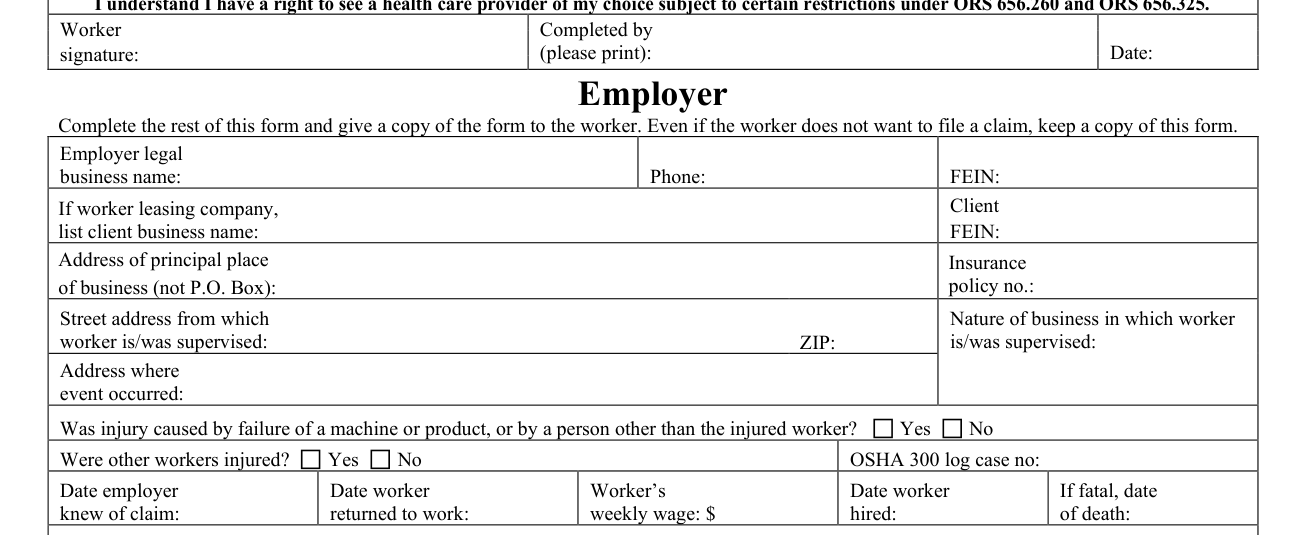
Complete the rest of this form and give a copy of the form to the worker.
Even if the worker does not want to file a claim, keep a copy of this form.
Enter Completed by (please print), Employer legal business name, Phone and FEIN.
If worker leasing company, list client business name and the Client FEIN; enter the Address of principal place of business (not P.O. Box) and the Insurance policy no.
Enter the Street address from which worker is/was supervised, ZIP, the Nature of business in which worker is/was supervised and the Address where event occurred.
Mark Yes or No for Was injury caused by failure of a machine or product, or by a person other than the injured worker? and for Were other workers injured?, and enter the OSHA 300 log case no.
Enter the Date employer knew of claim, Date worker returned to work, Worker's weekly wage, Date worker hired and, if fatal, the date of death.
Employer name, title and date

I understand I may not restrict the worker's choice of or access to a health care provider.
If I do, it could result in civil penalties under ORS 656.260.
Enter Name and title (please print) and the Date.
More rules for Form 801
OSHA requirements: Employers must report work-related fatalities and catastrophes to Oregon OSHA either in person or by telephone within eight hours.
In addition, employers must report any in-patient hospitalization, loss of an eye, and any amputation or avulsion that results in bone or cartilage loss to Oregon OSHA within 24 hours.
See OAR 437-001-0704. Call 800-922-2689 (toll-free), 503-378-3272, or Oregon Emergency Response, 800-452-0311 (toll-free), on nights and weekends.
If your situation is different
Worker signature
Worker signature: By my signature, I am making a claim for workers' compensation benefits.
Your employer will give you a copy.
I understand I have a right to see a health care provider of my choice subject to certain restrictions under ORS 656.260 and ORS 656.325.
Common questions about Form 801
What is Orea Form 801?
Form 801 is the Report of Job Injury or Illness. To make a claim for a work-related injury or illness, fill out the worker portion of this form and give it to your employer.
Sources
[1] Form 801 (440-801 1/21/DCBS/WCD/WEB), Report of Job Injury or Illness, Oregon Workers' Compensation Division (the Official source link on this page).
