
PA 162-RM at a glance
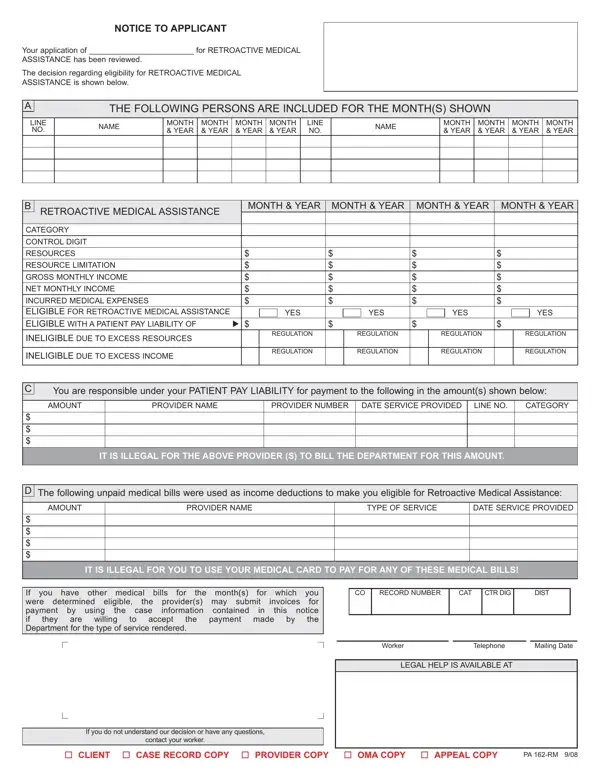
What it is: The PA 162-RM is a NOTICE TO APPLICANT: your application for RETROACTIVE MEDICAL ASSISTANCE has been reviewed, and the decision regarding eligibility is shown on it.
Who signs: The client signs on the CLIENT SIGNATURE line; anyone who represents the client signs on the CLIENT REPRESENTATIVE SIGNATURE line.
You have the right to appeal any Departmental action or failure to act and to have a hearing if you are dissatisfied with the decision regarding your eligibility for RETROACTIVE MEDICAL ASSISTANCE.
A filled-in PA 162-RM example: a client asks for a Face-to-Face Hearing

How to fill out PA 162-RM, box by box
A to D: PERSONS INCLUDED, RETROACTIVE MEDICAL ASSISTANCE, PATIENT PAY LIABILITY, unpaid medical bills
Section A lists the following persons included for the month(s) shown, by line no., name and month & year.
Section B, Retroactive Medical Assistance, lists for each month & year the resources, resource limitation, gross monthly income, net monthly income and incurred medical expenses, and marks eligible for retroactive medical assistance, eligible with a patient pay liability, ineligible due to excess resources or ineligible due to excess income, with the regulation.
In Section C, you are responsible under your PATIENT PAY LIABILITY for payment to the providers listed, in the AMOUNT shown; it is illegal for those provider(s) to bill the Department for this amount.
Section D lists the unpaid medical bills used as income deductions to make you eligible for Retroactive Medical Assistance; it is illegal for you to use your medical card to pay for any of these medical bills.
HOW TO REQUEST A FAIR HEARING
You must request a hearing within 30 days of the mailing date of this notice; if your request is not postmarked or received within the 30-day time limit, your appeal will be dismissed without a hearing.
To appeal and request a hearing for ASSISTANCE CHECKS, MEDICAL ASSISTANCE or SOCIAL SERVICES, you may call your worker, but you must also put the appeal in writing: (1) fill out and sign one copy of the form.
Give the reason for your appeal, your telephone number and your exact address, and (2) mail or take this form to your CAO; the blank form prints no address, and the CAO address is on the front side of this form.
PLEASE CHECK THE BOX NEXT TO THE TYPE OF HEARING YOU WANT

Check the box next to the type of hearing you want; for I want a Telephone Hearing at a phone number, enter the phone number where you and your witnesses and anyone helping you will be.
Check the second I want a Telephone Hearing box if you and your witnesses and anyone helping you will be at the County Assistance Office (CAO).
Check the first I want a Face-to-Face Hearing box if you and your witnesses and anyone helping you will be in the hearing room with the Judge and the caseworker and CAO staff.
Check the second I want a Face-to-Face Hearing box if you and your witnesses and anyone helping you will be in the hearing room with the Judge; the caseworker and other staff will be on the phone from the CAO.
HELP BECAUSE OF A HEARING PROBLEM OR A DISABILITY OR AN INTERPRETER

If you need help because of a hearing problem or a disability or you need an interpreter, check I have a hearing impairment or a disability and describe the accommodations needed, or check I need an interpreter.
For I need an interpreter, write what language; there will be no cost to you.
You must make the request for an interpreter or other accommodation in advance of the hearing.
I WANT TO REQUEST A HEARING BECAUSE

Under I WANT TO REQUEST A HEARING BECAUSE, present the reasons why you think the decision of the County Assistance Office is incorrect.
CLIENT SIGNATURE, DATE, TELEPHONE # AND CLIENT ADDRESS

With your signature, enter the DATE, your TELEPHONE # and your CLIENT ADDRESS.
You have the right to represent yourself or to have anyone represent you; only a representative enters the DATE and TELEPHONE # with the CLIENT REPRESENTATIVE SIGNATURE.
More rules for PA 162-RM
If you do not understand the decision or have any questions, contact your worker at the Worker Telephone.
A staff member of the County Assistance Office will refer you for free legal help upon request.
If you need an interpreter at the hearing because you do not speak English or you have limited understanding of English, or you have a hearing impairment, the Department will arrange for an official interpreter.
You may bring a friend or relative to assist you at the hearing, but the interpreter provided by the Department will be the official interpreter.
The Department will provide reasonable or special accommodations for you if you have a hearing impairment or other disability.
HEARING LOCATIONS: PHILADELPHIA for Bucks, Chester, Delaware, Montgomery, Philadelphia.
HEARING LOCATIONS: PITTSBURGH for Allegheny, Armstrong, Beaver, Bedford, Blair, Butler, Cambria, Cameron, Clarion, Clearfield, Crawford, Elk, Erie, Fayette, Forest, Greene, Indiana, Jefferson, Lawrence, McKean, Mercer, Potter, Somerset, Venango, Warren, Washington, Westmoreland.
HEARING LOCATIONS: HARRISBURG for Adams, Berks, Centre, Cumberland, Dauphin, Franklin, Fulton, Huntingdon, Juniata, Lancaster, Lebanon, Lycoming, Mifflin, Montour, Northampton, Northumberland, Perry, Schuylkill, Snyder, Union, York, Lehigh.
HEARING LOCATIONS: PLYMOUTH for Bradford, Clinton, Lackawanna, Monroe, Sullivan, Tioga, Wyoming, Carbon, Columbia, Luzerne, Pike, Susquehanna, Wayne.
If your situation is different
If your appeal is about FOOD STAMPS
To appeal and request a hearing for FOOD STAMPS, you may call your worker, or put the appeal in writing, or do both; if you put the appeal in writing, follow the instructions for putting the appeal in writing.
If you would like to meet the County Assistance Office staff informally
If you and your representative would like to meet with the County Assistance Office staff to discuss the matter informally or to present information which might change the decision regarding your eligibility for retroactive medical assistance, please call your worker; this will not delay or replace your hearing.
If you have other medical bills for the month(s) you were determined eligible
If you have other medical bills for the month(s) for which you were determined eligible, the provider(s) may submit invoices for payment by using the case information contained in the notice if they are willing to accept the payment made by the Department for the type of service rendered.
Sources
[1] PA 162-RM (9/08), Notice to Applicant, Retroactive Medical Assistance, Pennsylvania Department of Human Services (the Official source link on this page).