

Physician Statement Form at a glance
What it is: The Physician Statement Form has a part to be completed by Primary Insured and a part to be completed by Examining Physician.
Who signs: Sign on Physician Signature, enter the Date and add the Physician Stamp to certify that it is true and correct.
A filled-in Physician Statement Form example: a physician completes the statement

How to fill out Physician Statement Form, box by box
The primary insured's part

Enter the Primary Insured's Name, Policy Number and Insurance Purchase Date.
Patient information

Under Patient Information, enter the Patient's Name, Date of Birth, Street Address, City, State and Zip Code.
Physician information

Under Physician Information, enter the Examining Physician's Name, Specialty, Street Address, City, State, Zip Code, Phone and Fax.
Primary care physician and referral

Enter Yes or No under "Are you the patient's primary care physician?", enter the Name and Phone under "Who is this patient's primary care physician?" and enter Yes or No under "Was the patient referred to you by the primary care physician?"
Patient's diagnosis
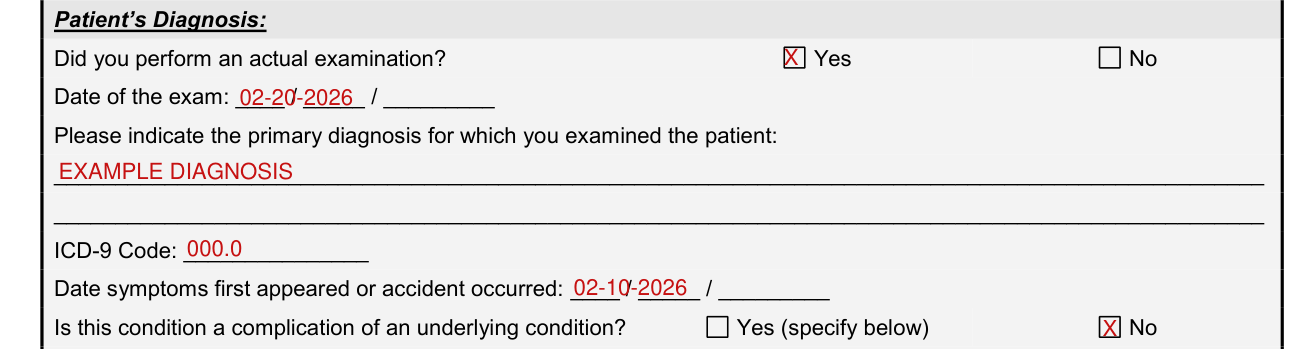
Under Patient's Diagnosis, enter Yes or No under "Did you perform an actual examination?", and enter the Date of the exam, the primary diagnosis for which you examined the patient and the ICD-9 Code.
Enter the Date symptoms first appeared or accident occurred, and enter Yes or No under "Is this condition a complication of an underlying condition?"
Office visits

List the dates of the patient's office visits in the 120 days before the Insurance Purchase Date and circle the dates where you treated the patient for the stated condition.
Trip cancelled or interrupted
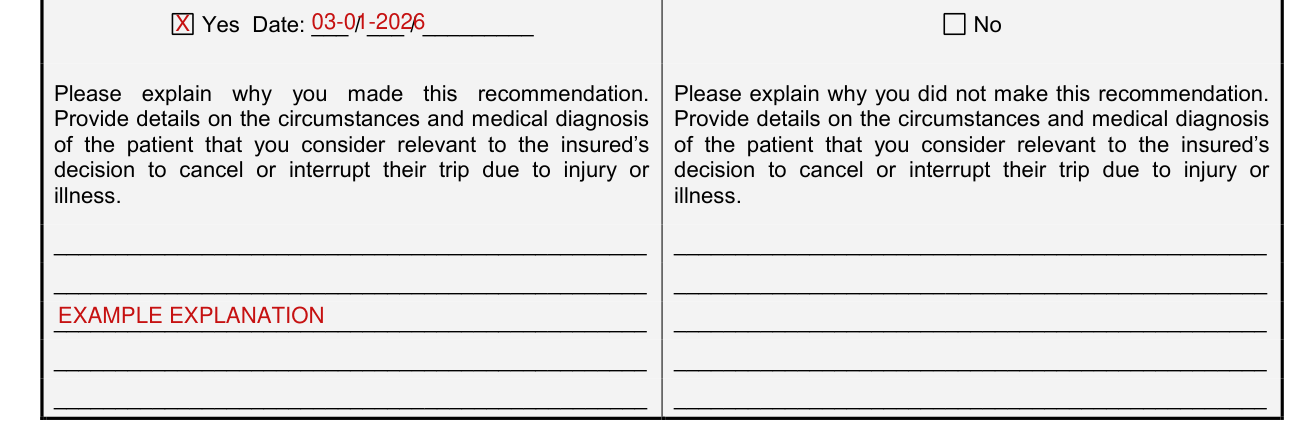
Under "Did you advise the trip be cancelled or interrupted due to the patient's medical condition?", enter Yes and a Date. Then explain why you made this recommendation, with details on the circumstances and medical diagnosis of the patient that you consider relevant to the insured's decision to cancel or interrupt their trip due to injury or illness.
Under "Did you advise the trip be cancelled or interrupted due to the patient's medical condition?", enter No. Then explain why you did not make this recommendation, with details on the circumstances and medical diagnosis of the patient that you consider relevant to the insured's decision to cancel or interrupt their trip due to injury or illness.
Medically unable to travel

If the patient is the insured, enter the date for "on what date did he/she become medically unable to travel?"
Physician signature and stamp

Sign on Physician Signature, enter the Date and add the Physician Stamp to certify that it is true and correct.
If your situation is different
E-mail to, Mail to or Fax to
E-mail to claimsinquiry@allianzassistance.com, mail to Allianz Global Assistance, P.O. Box 72031, RICHMOND, VA 23255-2031, or fax to 804-673-1469.
Sources
[1] Physician Statement Form (the served file; no issuer file found) (the Official source link on this page).
