

NYU Pre Employment Physical at a glance
What it is: The New York University Pre Employment Physical form has a part for the Human Resource Department only and a part for the Prospective Employee to complete PRIOR TO APPT.
Who signs: Under I hereby declare the answers I have given are to the best of my knowledge, PRINT NAME, then SIGNATURE and DATE.
A filled-in NYU Pre Employment Physical example: an employee completes the first part
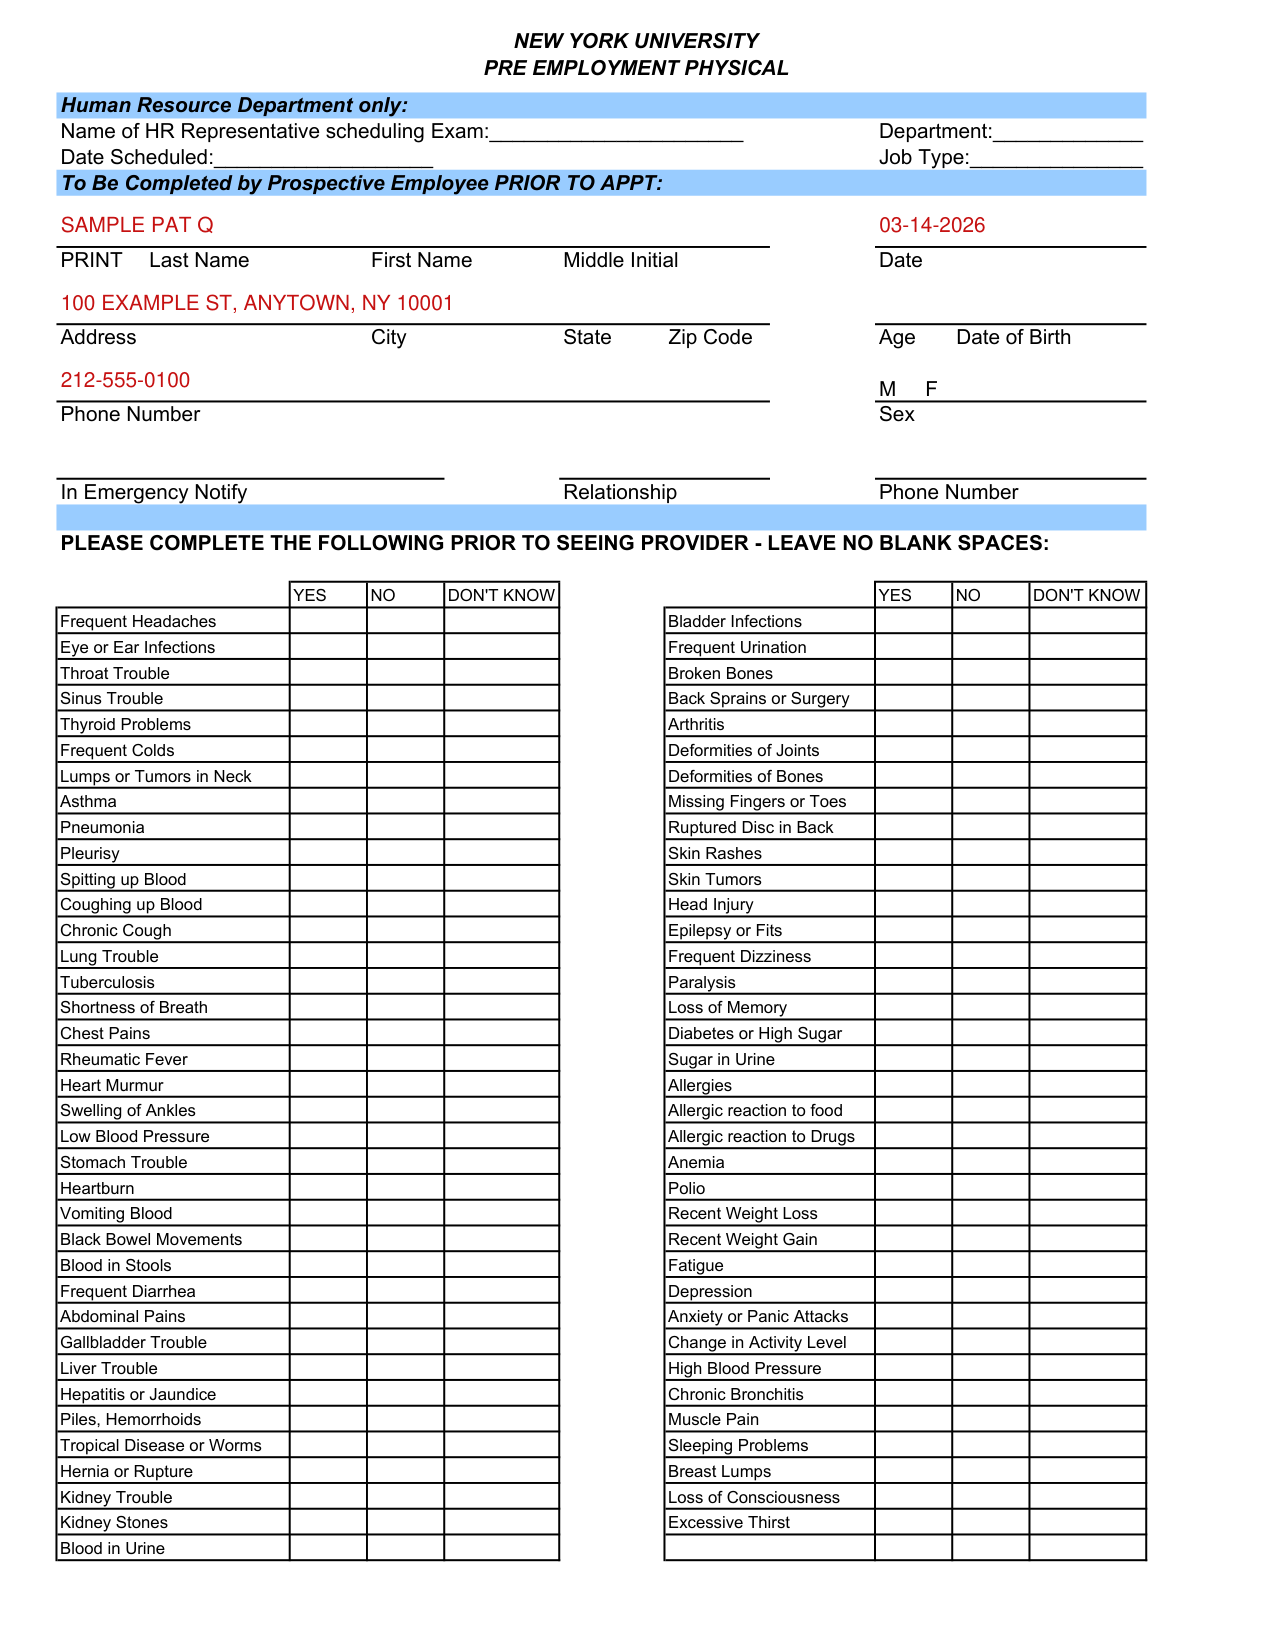
How to fill out NYU Pre Employment Physical, box by box
Human Resource Department only

Leave the Human Resource Department only part to that department: Name of HR Representative scheduling Exam, Department, Date Scheduled and Job Type.
Your name, address and phone number
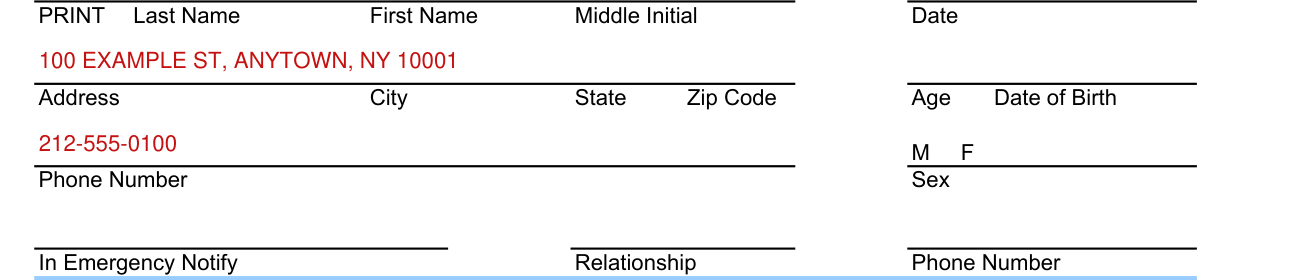
PRINT your Last Name, First Name and Middle Initial, and enter the Date.
Enter your Address, City, State, Zip Code, Age, Date of Birth and Phone Number, and mark Sex as M or F.
Fill in In Emergency Notify, Relationship and Phone Number.
Signature

By signing, you give permission to the screening healthcare provider at New York University Health Center to forward any abnormal findings to your healthcare provider, you understand that you are responsible for following up with your own healthcare provider on any abnormal findings, and you understand that NYU will not provide follow-up treatment for such findings. Then PRINT NAME, SIGNATURE and DATE.
More rules for NYU Pre Employment Physical
Complete the following prior to seeing the provider and leave no blank spaces: mark YES, NO or DON'T KNOW for each, from Frequent Headaches to Blood in Urine.
Under Have you ever, mark YES or NO for Suffered from hearing problems or hearing loss, Suffered from visual problems or eye diseases, Had back problems, back pain or back injuries and Had foot problems.
Mark YES or NO to: Have you ever been a patient in a hospital for any reason? If YES, please complete the following section with NAME OF HOSPITAL, CONDITION TREATED FOR and DATES, on lines 1 to 8.
Mark YES or NO to: Have you ever lost time from work in the past year for ANY REASON? If YES, please explain.
Mark YES or NO to: Are you currently under the treatment or care of a physician, Nurse Practitioner or other health care provider in the past year? If YES, please explain.
Mark YES or NO to Do you SMOKE? If YES, write what you smoke, how many per day and how many years.
Mark YES or NO to Do you drink ALCOHOL? If YES, write how many drinks you drink at each sitting and how many days per week, and mark what you drink: BEER, WINE, HARD LIQUOR or OTHER.
Fill in the lines for: Are you taking prescribed or over the counter medications, herbal products, vitamins or supplements?
MALES ONLY: mark YES or NO to Have you now or have you ever had a HERNIA or RUPTURE OF A HERNIA? and to Have you ever had problems with your testicles (surgery, infection, injury)? Also fill in Have you ever had a Sexually Transmitted Disease? (Gonorrhea, Syphilis, Chlamydia).
FEMALES ONLY: mark YES or NO to any problems with your breasts (lumps, tumors, surgery) and to Are you now or have you ever been pregnant? If YES, write how many pregnancies and Miscarriages. Also mark YES or NO to Are your periods regular? and Do you have pain with your periods?, fill in the line for Date of Last Period, and fill in Have you ever had a Sexually Transmitted Disease? (Gonorrhea, Syphilis).
Under VACCINATION HISTORY, write the Last known Tuberculin Skin Test and mark Results as Negative or Positive. If positive, mark YES or NO to Chest X ray done, and if YES write the Results of Chest x ray.
Write the Last Tetanus Shot, and mark YES or NO to Hepatitis B Vaccination. If YES, write when.
Write your private healthcare providers name, Address and Phone number.
The information contained in this form is of a strictly confidential nature. The form will remain in the New York University Health Center confidential files and may be seen only by the examining healthcare provider, nurses in attendance and administrative personnel reviewing the chart for quality assurance reasons.
Sources
[1] NYU Pre Employment Physical form (no issuer file published) (the Official source link on this page).
