Provider Information Update Form PDF Details

Maintaining an accurate provider directory is a cornerstone of Johns Hopkins Healthcare's commitment to quality service delivery. The Provider Information Update Form plays a pivotal role in this process, ensuring all provider data remains current and thereby, aiding in the seamless operation of healthcare services. Providers are required to notify Johns Hopkins Healthcare of any changes to their information at least thirty (30) days before such changes take effect. This notification can be done in writing or by submitting the specified form, complete with all the current details. Additionally, it's crucial for the providers to include their W-9 when submitting the completed form to the Provider Relations through the designated email address. It is important to highlight that if a Social Security Number is used instead of a Tax ID, the form has to be faxed for enhanced identity protection. The form accommodates various updates, including changes in provider name, specialty, panel status, or practice information such as name, Tax ID, NPI, and contact details. This systematic approach not only facilitates an up-to-date provider directory but also supports Johns Hopkins Healthcare's dedication to operational excellence and patient satisfaction.

QuestionAnswer
Form NameProvider Information Update Form
Form Length2 pages
Fillable?Yes
Fillable fields85
Avg. time to fill out15 sec
Other namesprovider information update form, provider update form, florida bluecross provider form, provider information update

How to Fill Out Provider Information Update Form

Provider Information Update Form at a glance

What it is: The Provider Information Update Form is how Johns Hopkins Health Plans maintains an accurate and up-to-date provider directory.

Where and when to file: Send completed form along with your W-9 to Provider Relations at ProviderChanges@jhhp.org.

A filled-in Provider Information Update Form example: a clinic changes a physician's specialty

Provider Information Update Form example filled out, example: a clinic changes a physician's specialty
Dr. Jane Sample's clinic sends the Provider Information Update Form. Her Specialty changes in 45 days, so Change and Specialty are checked. The picture shows page 1 only, and its names and figures are sample values. Today's Date is 12-01-2026 and the Effective Date of Change is 01-15-2027, 45 days later. The Provider Information group lists her old and new Specialty. Is Provider a Primary Care Physician? and Board Certified in Specialty are left blank because the story gives no answer for them. Name stays empty because her name does not change. The Product group stays empty because the picture's file cannot check those boxes. Authorized Signature stays empty because page 1 is the only page shown.

How to fill out Provider Information Update Form, box by box

Product and dates

Provider Information Update Form example filled out, product and dates

Under Product, check Advantage MD, Employer Health Programs (EHP), Family Health Plan (USFHP), Priority Partners or ElderPlus.

Enter Today's Date and the Effective Date of Change.

Provider Information
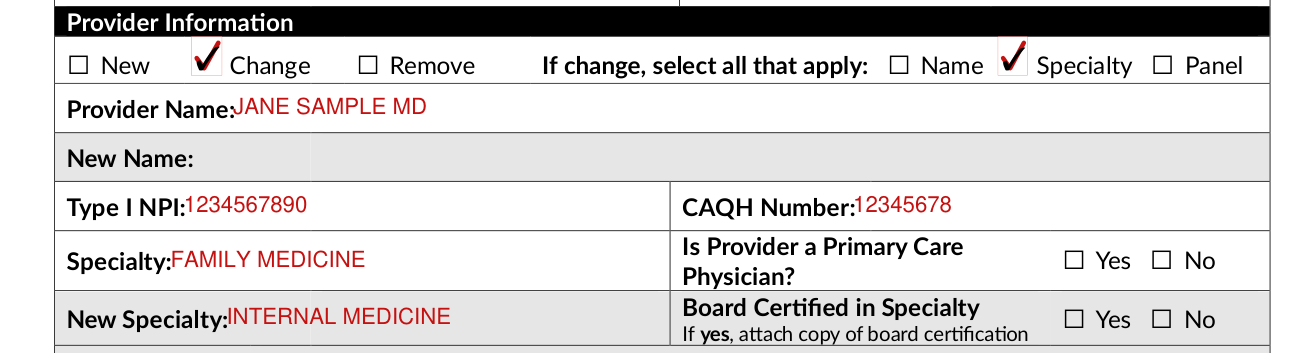
Provider Information Update Form example filled out, provider Information

Under Provider Information, check New, Change or Remove. If change, select all that apply: Name, Specialty or Panel.

Enter the Provider Name. Enter the New Name if you select Name.

Enter the Type I NPI and the CAQH Number.

Enter the Specialty. Enter the New Specialty if you select Specialty. Mark Is Provider a Primary Care Physician? with Yes or No. Mark Board Certified in Specialty with Yes or No. If yes, attach copy of board certification.

Panel Status and Provider Leaving Practice
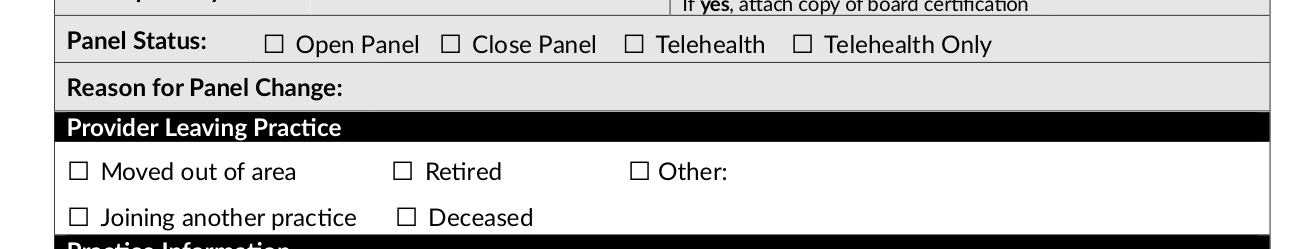
Provider Information Update Form example filled out, panel Status and Provider Leaving Practice

For Panel Status, check Open Panel, Close Panel, Telehealth or Telehealth Only.

Enter the Reason for Panel Change. Under Provider Leaving Practice, check Moved out of area, Retired, Other, Joining another practice or Deceased.

Practice Information
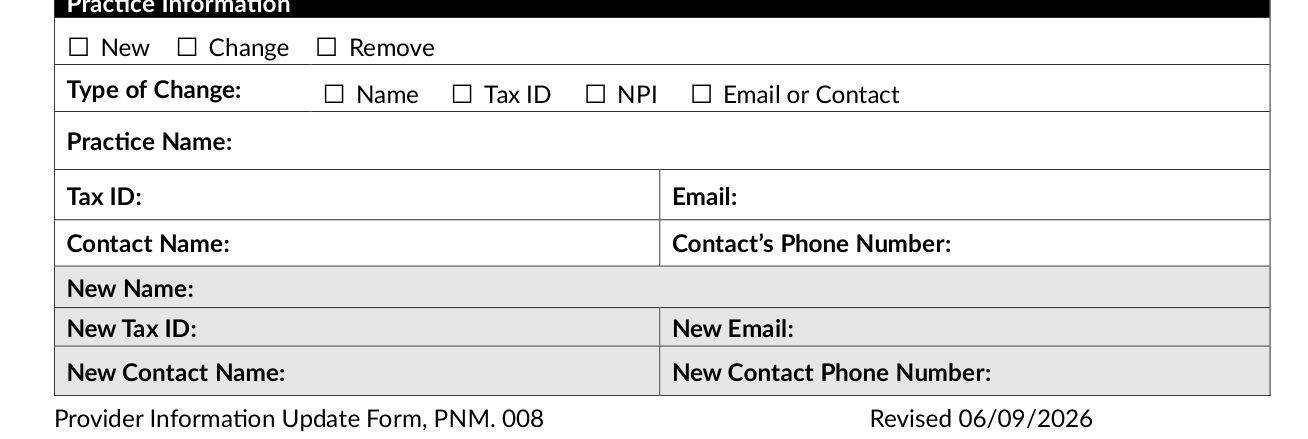
Provider Information Update Form example filled out, practice Information

Under Practice Information, check New, Change or Remove.

For Type of Change, check Name, Tax ID, NPI or Email or Contact.

Enter the Practice Name, Tax ID, Email, Contact Name and Contact's Phone Number.

Enter the New Name, New Tax ID, New Email, New Contact Name and New Contact Phone Number.

Address Information
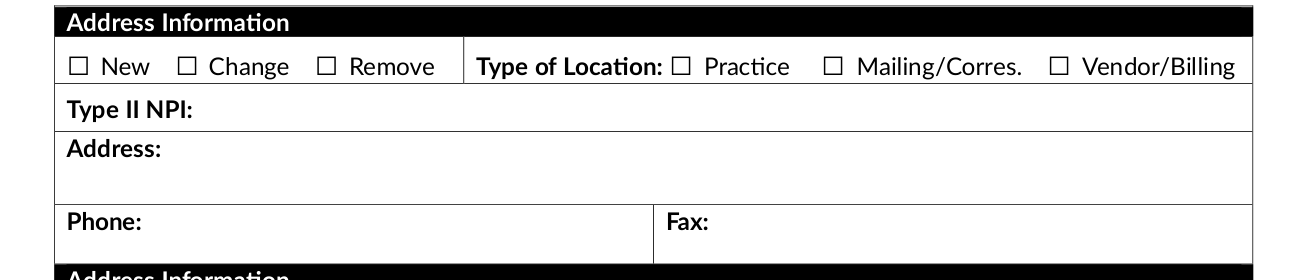
Provider Information Update Form example filled out, address Information

Under Address Information, check New, Change or Remove, and the Type of Location: Practice, Mailing/Corres. or Vendor/Billing.

Enter the Type II NPI, Address, Phone and Fax.

Authorized Signature

Provider Information Update Form example filled out, authorized Signature

Print the Person authorized to make change, then add the Signature, Date, Title and Email.

More rules for Provider Information Update Form

Complete this form with all current information.

This form may also be completed electronically.

Questions? Call Provider Relations at 888-895-4998.

Check the box to indicate there are no changes at this time.

Common questions about Provider Information Update Form

Is there a deadline?

Provider Information Change Notification must be made at least thirty (30) days in advance of the change in writing or using this form.

Where do I file it?

Send completed form along with your W-9 to Provider Relations at ProviderChanges@jhhp.org.

Sources

[1] Provider Information Update Form, PNM. 008 (revised 06/09/2026), Johns Hopkins Health Plans (the Official source link on this page).

Please rate Provider Information Update Form Fillable

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .