
The Referral To Emergency Department form is a crucial document designed to ensure a smooth transition for patients requiring emergency or partial hospitalization services from various healthcare settings. It contains vital information regarding the patient, such as personal details, medical history, insurance coverage, and the reason for referral. To provide the best possible care for individuals in urgent need, completing this form with accuracy and thoroughness is essential. For assistance in filling out the form, please click the button below.
Get Form Now
Download PDF
How to Fill Out DayBridge Referral Form
DayBridge Referral Form at a glance
What it is: The DayBridge Referral Form, 640 Jackson Street, St. Paul, MN 55101, Phone: 651-254-2402, Fax: 651-254-6655.
A filled-in DayBridge Referral Form example: a nurse refers a patient to DayBridge
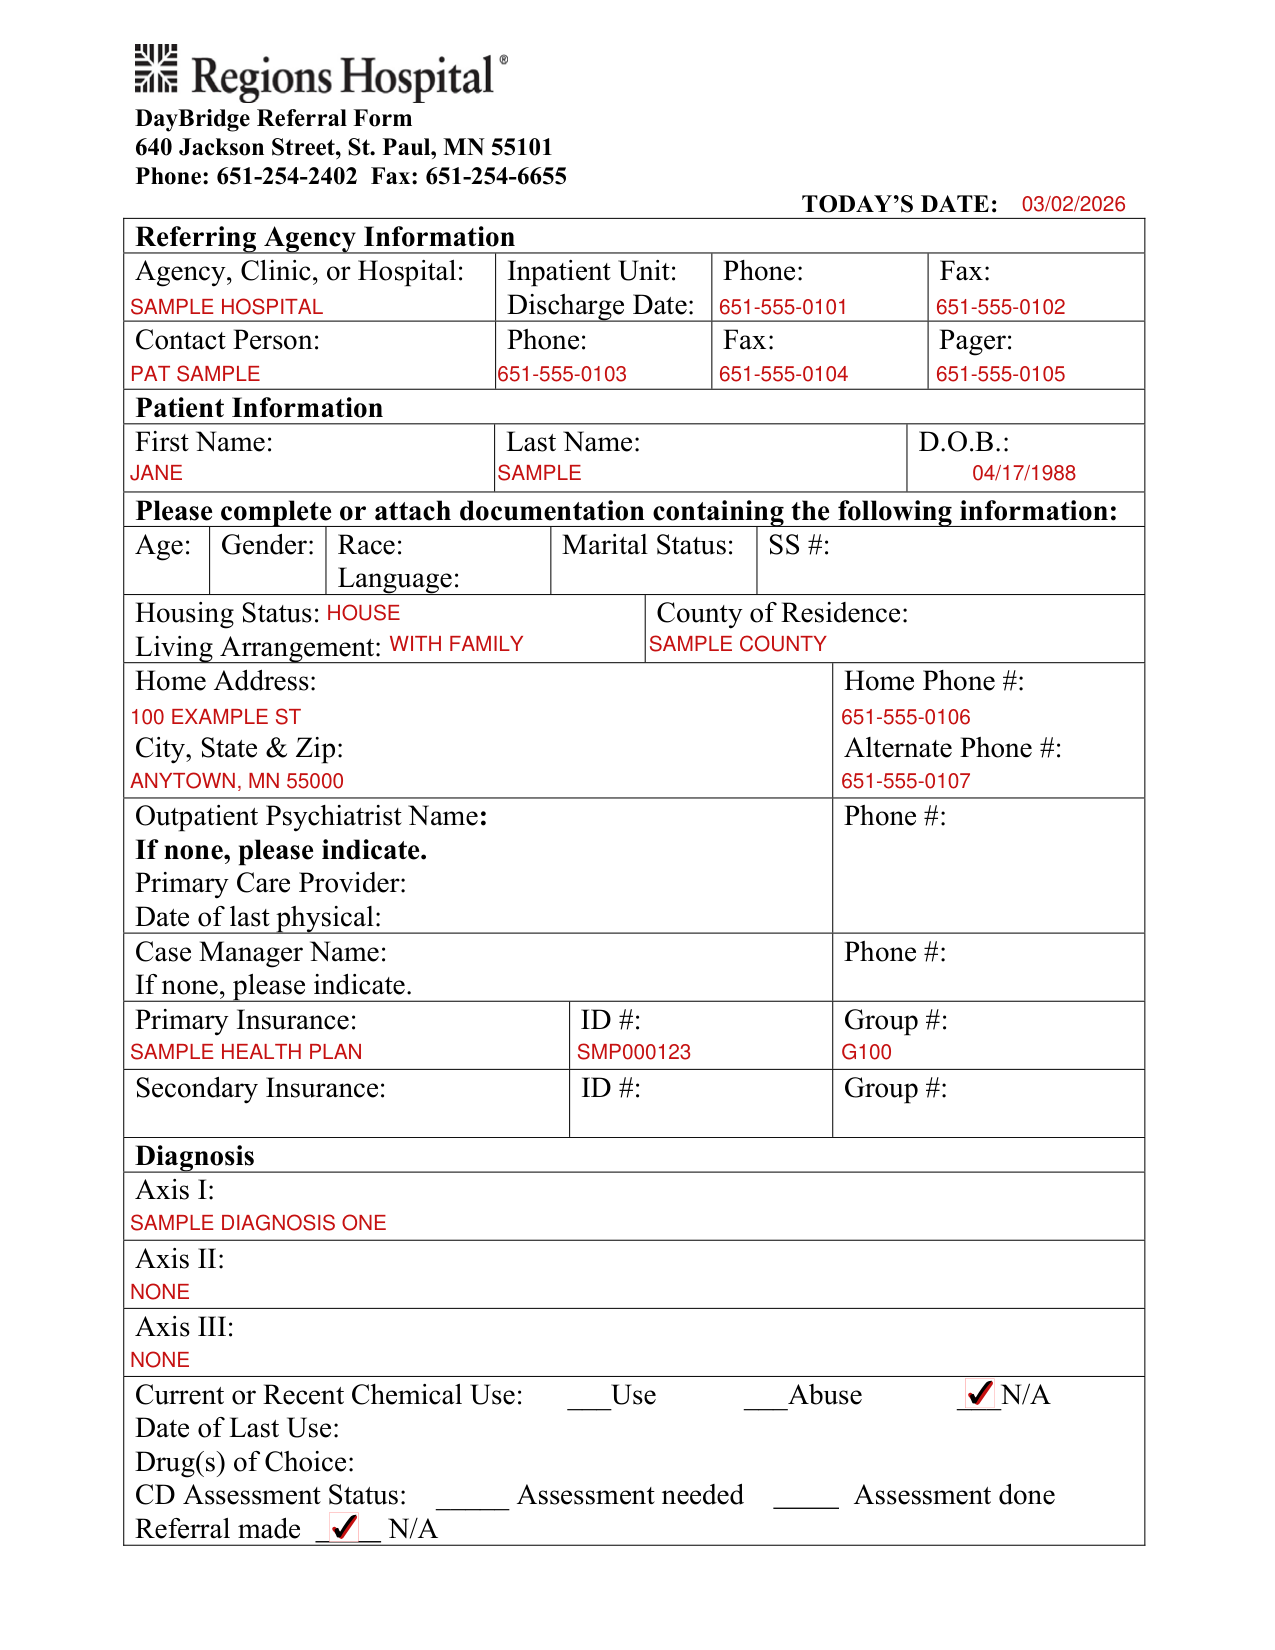
Nurse Pat Sample refers patient Jane Sample on the DayBridge Referral Form. The form is dated March 2, 2026. The picture shows page 1; its names and figures are sample values. Pat Sample works at Sample Hospital and is the contact person. Jane reports no chemical use, so the nurse marks N/A under Current or Recent Chemical Use and under CD Assessment Status; Date of Last Use and Drug(s) of Choice stay empty. The nurse marks No under Is Client Dangerous to Self or Others. The age, gender, race, language, marital status and SS # come on attached documentation, so those boxes stay empty. Jane's primary insurance is not on the list of insurance not accepted, and she has no secondary insurance, so Secondary Insurance stays empty.
How to fill out DayBridge Referral Form, box by box
Today's date and Referring Agency Information

Enter TODAY'S DATE, then under Referring Agency Information the Agency, Clinic, or Hospital, the Inpatient Unit, the Discharge Date, the Phone and the Fax, and the Contact Person with Phone, Fax and Pager.
Patient Information

Under Patient Information, enter the First Name and Last Name, then the D.O.B. date.
Complete or attach documentation for the Age, Gender, Race, Language, Marital Status and SS #.
Housing Status, Living Arrangement, County of Residence, Home Address and City, State & Zip
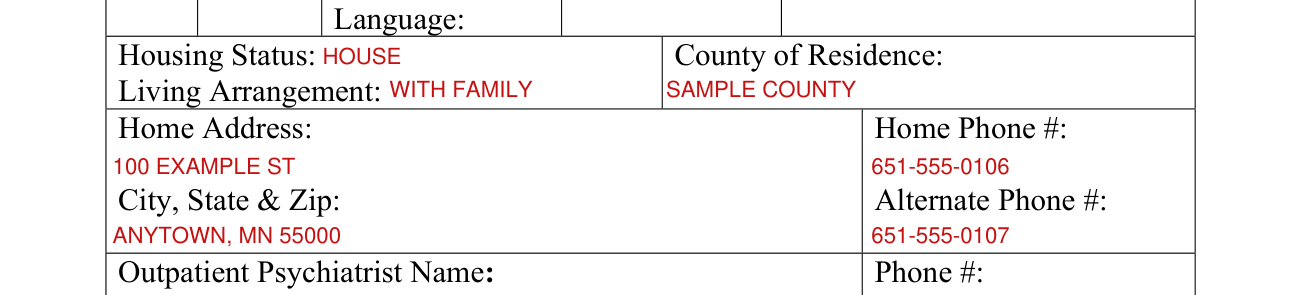
Enter the Housing Status, Living Arrangement, County of Residence, Home Address and City, State & Zip.
Home Phone #, Alternate Phone #, Outpatient Psychiatrist, Primary Care Provider and Case Manager

Enter the Home Phone # and Alternate Phone #, then the Outpatient Psychiatrist Name and Phone #. If none, please indicate. Enter the Primary Care Provider and the Date of last physical.
Enter the Case Manager Name and the Phone #. If none, please indicate.
Primary Insurance and Secondary Insurance
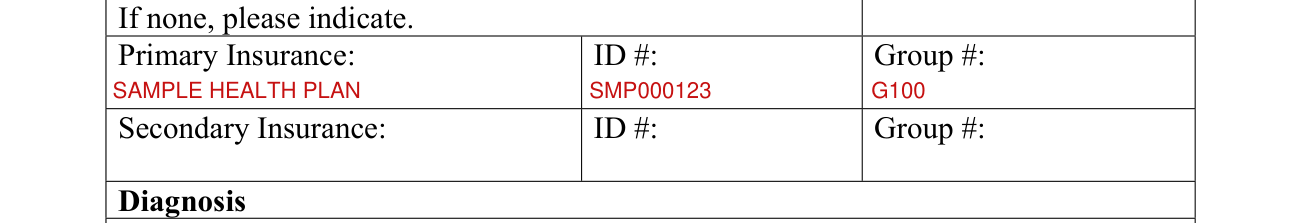
Enter the Primary Insurance and the Secondary Insurance, each with its ID # and Group #.
Diagnosis
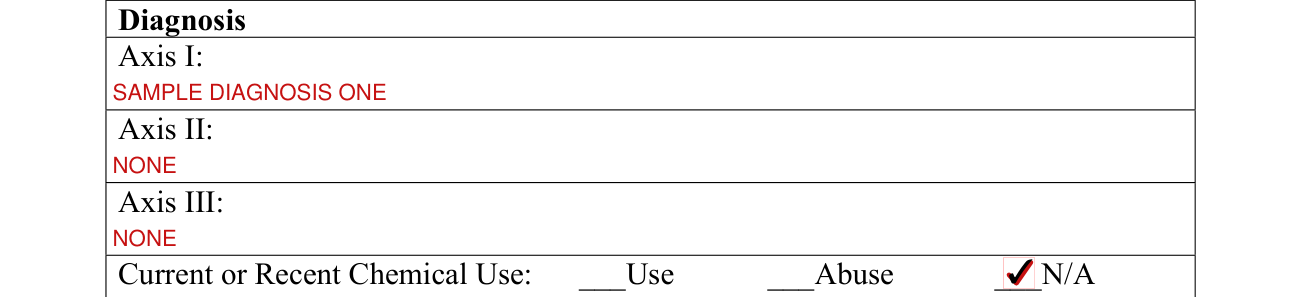
Enter the Diagnosis under Axis I, Axis II and Axis III.
Current or Recent Chemical Use

For Current or Recent Chemical Use, mark Use, Abuse or N/A, then enter the Date of Last Use and the Drug(s) of Choice.
CD Assessment Status

For CD Assessment Status, mark Assessment needed, Assessment done, Referral made or N/A.
Is Client Dangerous to Self or Others

Mark Yes or No to Is Client Dangerous to Self or Others (currently or by history)?
Reason for Referral to Partial Hospitalization

Under Reason for Referral to Partial Hospitalization, enter the Client need, the Client group Readiness, the Commitment Status and Follow-up Appointments. Does patient have safe discharge plan with support without inpatient hospitalization?
More rules for DayBridge Referral Form
Please attach History and Physical or initial assessment, ROI, medications list, and current progress notes or MD discharge summary. *Attach commitment papers if applicable.
Insurance that DayBridge currently does NOT accept : Aetna, Ammerica's PPO, Champ VA, MA pending, GAMC, Hennepin Health or Metropolotin Health, Humana, Select Care, UCARE, Value Options, WEA/WEIT, Wisconsin MA.
Sources
[1] DayBridge Referral Form, served form (no issuer file) (the Official source link on this page).
Referral Form To Emergency Department PDF Details
In the intricate network of healthcare, the Referral To Emergency Department form stands as a crucial document, navigating the transition of care for patients from one medical setting to another. Located at 640 Jackson Street in St. Paul, Minnesota, the form is an essential tool for DayBridge, facilitating seamless communication between referring agencies, such as clinics or hospitals, and the emergency department. It captures a comprehensive snapshot of the patient's current medical and psychosocial status, including details such as the referring agency's information, patient demographics, medical and psychiatric diagnoses, current and past substance use, insurance details, and the specific reason for referral. Particularly noteworthy is the inclusion of details regarding the patient's safety risks to themselves or others and their readiness for partial hospitalization, underscoring the form's role in not just relaying medical facts but also ensuring the continuity and safety of patient care. Additionally, the exclusion of certain insurances by DayBridge underscores the complexities of healthcare coverage, making the referral process not just a medical decision but also a navigational challenge through the healthcare system's financial labyrinth. This form epitomizes the intersection of clinical need, care coordination, and administrative necessities in providing healthcare, highlighting the layered reality healthcare professionals navigate to ensure patients receive the appropriate level of care at the right time.
Question
Answer
Form Name
Regions Hospital DayBridge Referral Form
Form Length
2 pages
Fillable?
No
Fillable fields
0
Avg. time to fill out
30 sec
Other names
regions daybridge referral, TODAYS, applicable, Outpatient
12
Referral Form To Emergency Department isn’t the one you’re looking for?