

Request for Tax Household Information (RFTHI) at a glance
What it is: The RFTHI Redetermination Packet collects the necessary income and tax household information that is missing from their current Medi-Cal case in order to conduct a MAGI eligibility determination.
Who signs: Only the head of household (the person who files taxes) must complete Section 9 of the Request for Tax Household Information (RFTHI) form and sign the forms.
Complete the forms for yourself and the family members either living with you or claimed on your tax return.
Information is needed about each person living in your household or listed on your tax return, including those who get Medi-Cal now, those who do not have Medi-Cal now but would like to apply, and those who live in the household and do not have Medi-Cal but do not want to apply.
You must fill out one of these forms for each person in your household.
The Supplemental Form must be completed, or information otherwise provided, once for the entire household. Only one Supplemental Form per household is required.
What to bring and attach to Request for Tax Household Information (RFTHI)
When you call, you should have your most recent federal tax return available, if you file taxes.
A filled-in Request for Tax Household Information (RFTHI) example: an employee fills out her own form
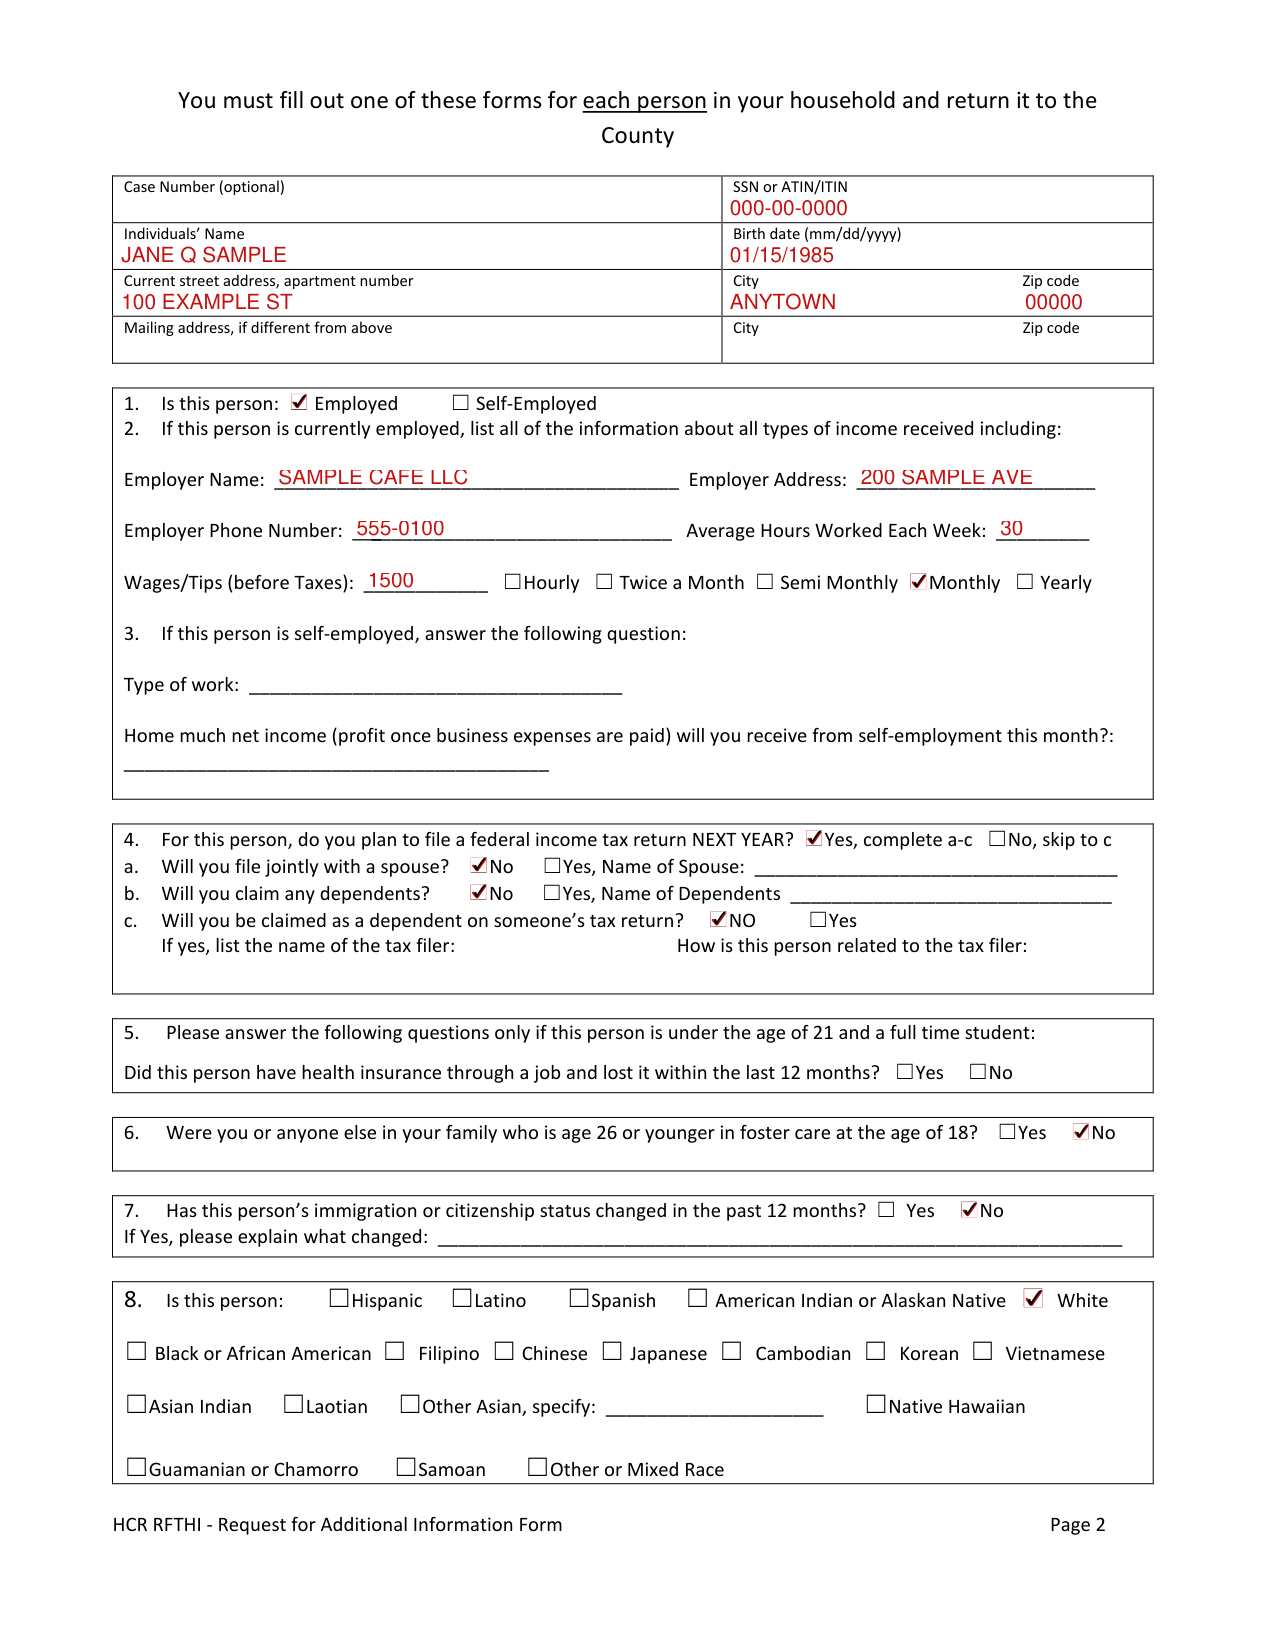
How to fill out Request for Tax Household Information (RFTHI), box by box
Case Number, SSN or ATIN/ITIN, Individuals' Name, Birth date and addresses
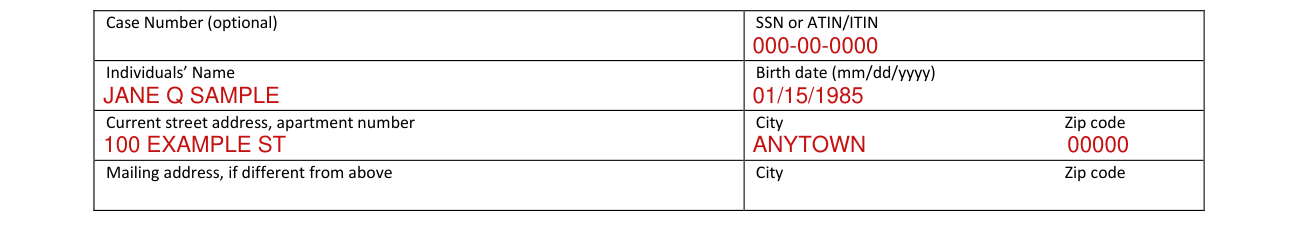
Enter the Case Number (optional), SSN or ATIN/ITIN, Individuals' Name, Birth date (mm/dd/yyyy), Current street address, apartment number, City and Zip code, and a Mailing address, if different from the current street address, with its City and Zip code.
1. Is this person: Employed or Self-Employed

1. Is this person: Employed or Self-Employed?
2. If this person is currently employed, list all of the information about all types of income received including Employer Name, Employer Address, Employer Phone Number, Average Hours Worked Each Week and Wages/Tips (before Taxes), and check Hourly, Twice a Month, Semi Monthly, Monthly or Yearly.
3. If this person is self-employed, answer the following question: Type of work, and how much net income (profit once business expenses are paid) will you receive from self-employment this month?
If additional family members are employed or self-employed, questions 1-4 should be answered for these individuals as well.
4. File a federal income tax return NEXT YEAR

4. For this person, do you plan to file a federal income tax return NEXT YEAR? Yes, complete a-c, or No, skip to c.
a. Will you file jointly with a spouse? No, or Yes, with the Name of Spouse.
b. Will you claim any dependents? No, or Yes, with the Name of Dependents.
c. Will you be claimed as a dependent on someone's tax return? No, or Yes; if yes, list the name of the tax filer and how this person is related to the tax filer.
5. Under the age of 21 and a full time student

5. Answer the following questions only if this person is under the age of 21 and a full time student: Did this person have health insurance through a job and lost it within the last 12 months? Yes or No.
6. Foster care at the age of 18

6. Were you or anyone else in your family who is age 26 or younger in foster care at the age of 18? Yes or No.
7. Immigration or citizenship status changed in the past 12 months

7. Has this person's immigration or citizenship status changed in the past 12 months? Yes or No. If Yes, please explain what changed.
8. Is this person

8. Is this person: Hispanic, Latino, Spanish, American Indian or Alaskan Native, White, Black or African American, Filipino, Chinese, Japanese, Cambodian, Korean, Vietnamese, Asian Indian, Laotian, Other Asian (specify), Native Hawaiian, Guamanian or Chamorro, Samoan or Other or Mixed Race?
9. Renewal of coverage for future years

9. Renewal of coverage for future years: To make it easier to determine my eligibility for help applying for health coverage in future years, I agree to allow the Marketplace to use income data, including information from tax returns. The Marketplace will send me a notice, let me make any changes, and I may opt out at any time.
Check 5 years (the maximum number of years allowed), or for a shorter number of years: 4 years, 3 years, 2 years, 1 year. Or check Don't use information from tax returns to renew my coverage. The income/tax filing information is required for all household members.
Signature and Date
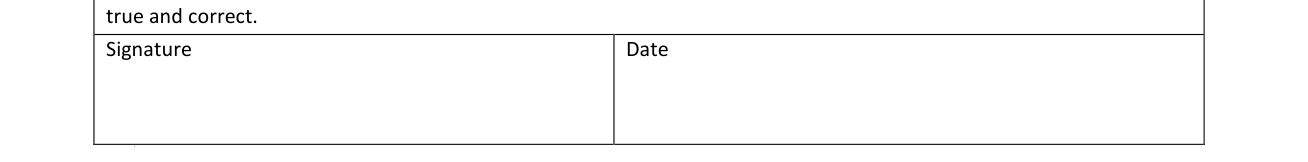
By signing, you declare, under penalty of perjury, under the laws of the State of California that all information provided on this form is true and correct. Signature, Date.
More rules for Request for Tax Household Information (RFTHI)
Answer all of the questions on the form.
Use ink and print your answers. If you need more space, attach a separate sheet to this form.
Read the information about you and each member of your household, including tax dependents. Add any missing information. If any information has changed, write in the correct information.
In order to see if you are still eligible for Medi-Cal, you must give the information on the Request for Tax Household Information (RFTHI) form and the RFTHI Supplemental Form.
The beneficiary is not required to physically return the RFTHI Redetermination Packet.
Common questions about Request for Tax Household Information (RFTHI)
Is there a deadline?
Return this form by MM/DD/YYYY. IF you do not return the form by this deadline, you will lose your Medi-Cal coverage.
Where do I file it?
Use the postage paid envelope to return the form. The beneficiary can provide the information requested in the packet by mail, by fax, in person, or over the phone.
Where to get help with Request for Tax Household Information (RFTHI)
Need Help?: Call your Medi-Cal Agency at (866) 613-3777 TTY: (800) 660-4026 You can call Monday to Friday 8:00 A.M. - 5:00 P.M.
Sources
[1] All County Welfare Directors Letter No. 14-03, Attachment A, Request for Tax Household Information (RFTHI), California Department of Health Care Services (the Official source link on this page).