
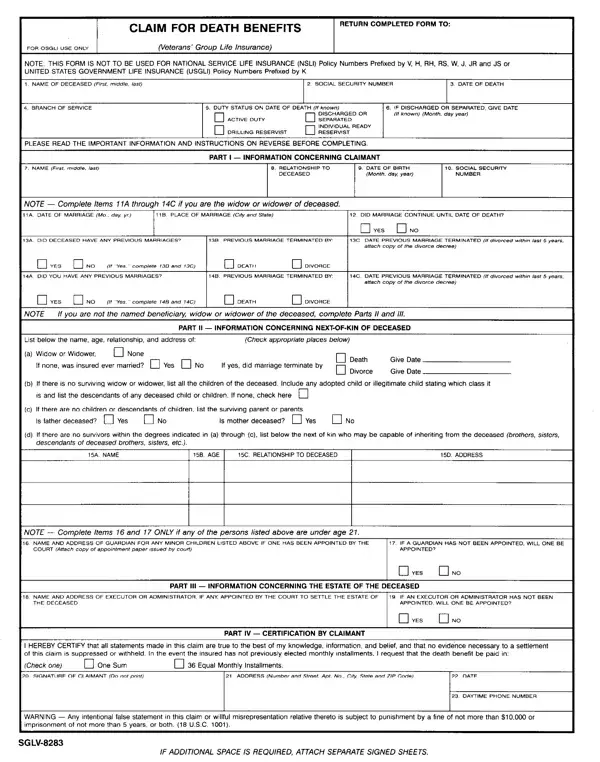
SGLV 8283 at a glance
What it is: SGLV 8283, the Claim for Death Benefits, should be used when the deceased had insurance in force under Servicemembers' Group Life Insurance (SGLI) or Veterans' Group Life Insurance (VGLI).
Where and when to file: For SGLI claims, return the completed form to the Branch of Service Casualty Office, and do NOT send it directly to the Office of Servicemembers' Group Life Insurance.
What to bring and attach to SGLV 8283
For VGLI claims only (veterans who applied for VGLI coverage and had it in effect at the time of death), the claimant must submit certified copy of the death certificate.
A filled-in SGLV 8283 example: a widow files a claim for death benefits
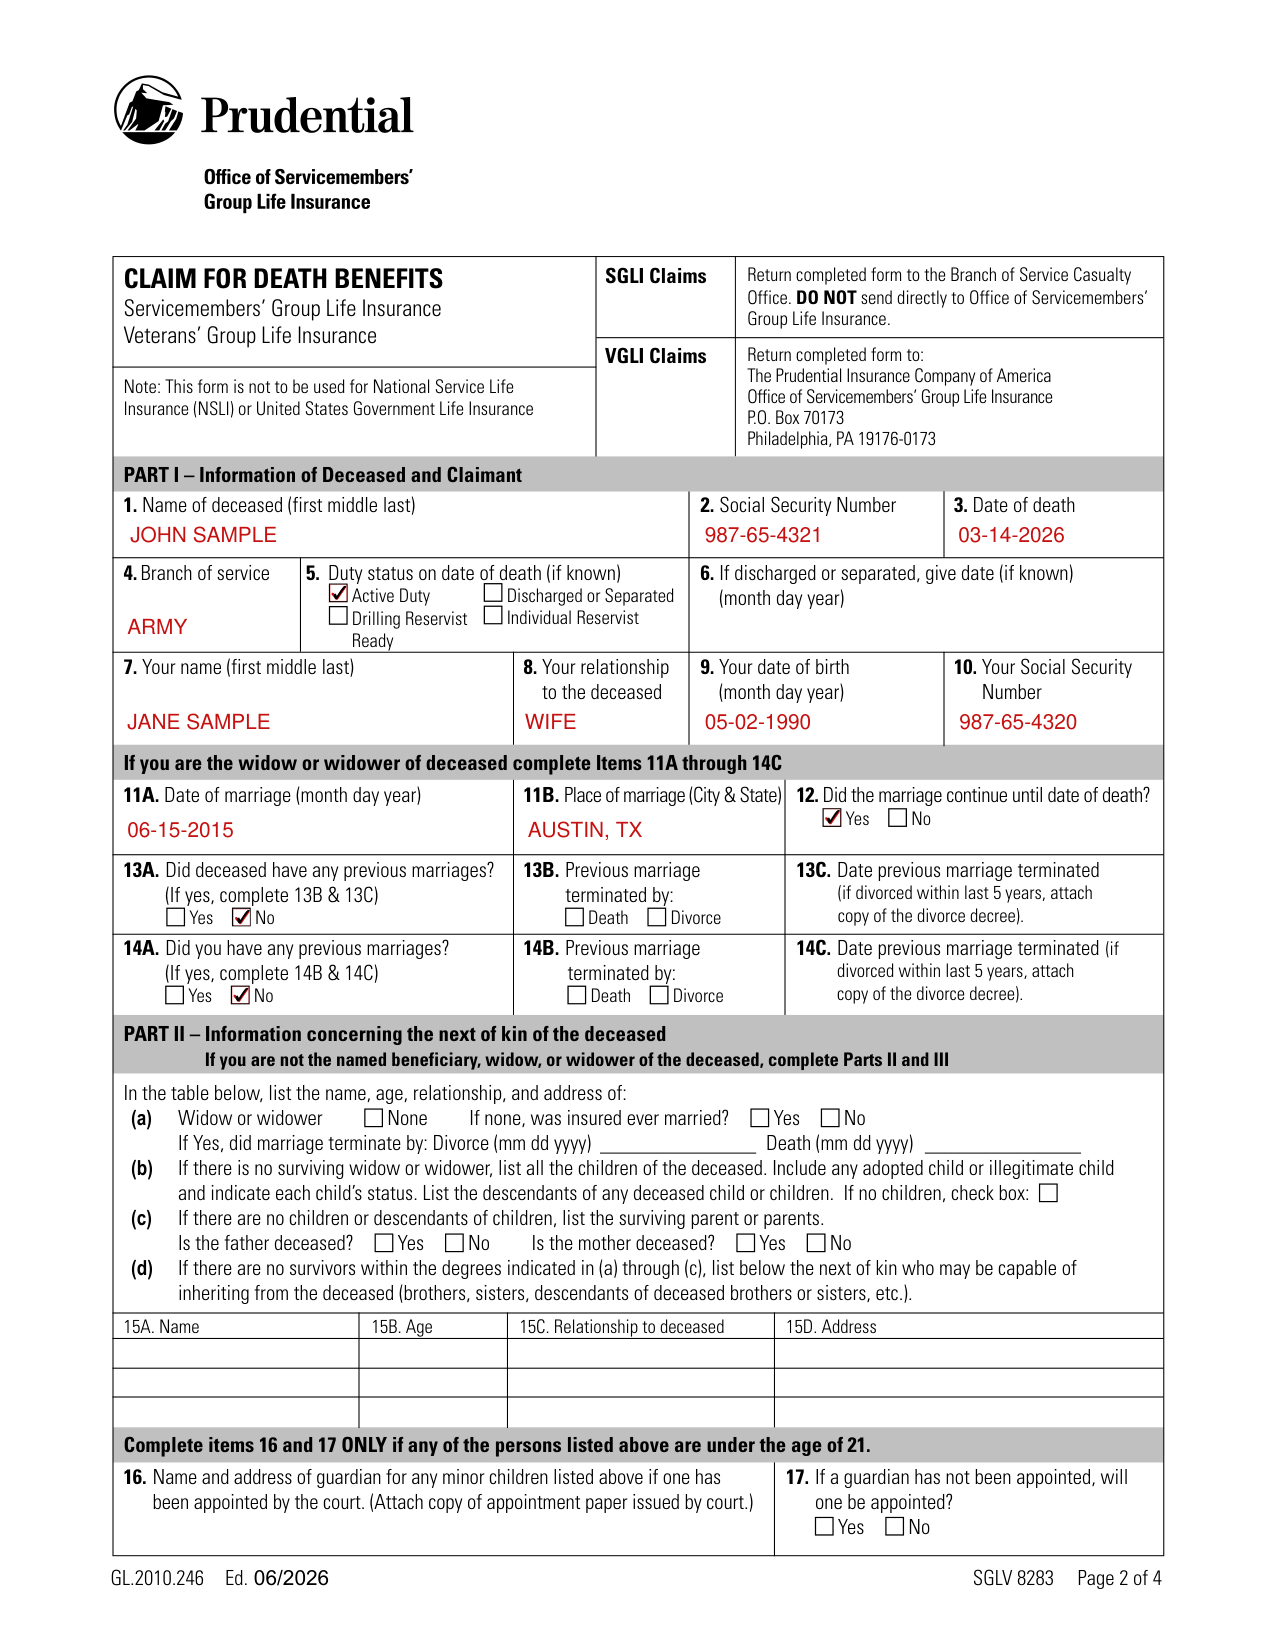
How to fill out SGLV 8283, box by box
Return the completed form to
For VGLI claims, return the completed form to: The Prudential Insurance Company of America, Office of Servicemembers' Group Life Insurance, P.O. Box 70173, Philadelphia, PA 19176-0173.
Part I, items 1 to 10, the deceased and you
Provide the full name of the deceased Service Member or Veteran in Item 1, the Social Security Number of deceased in Item 2, and the date of death of deceased in Item 3.
At 1, write the name of the deceased (first middle last).
Items 4, 5 and 6: provide branch of service, duty status on date of death (if known), and date of discharge or separation (if known) of deceased.
At 5, duty status on date of death (if known): mark Active Duty, Drilling Reservist Ready, Discharged or Separated, or Individual Reservist.
At 6, if discharged or separated, give date (if known) (month day year).
Items 7, 8, 9 and 10: provide your full name, relationship to deceased, your date of birth, and Social Security Number.
Write your name (first middle last) at 7 and your date of birth (month day year) at 9.
Items 11A to 14C, if you are the widow or widower
If you were married to the deceased when he/she died, but were NOT named as his/her insurance beneficiary, complete items 11A through 14C as applicable.
If you are the widow or widower of deceased complete Items 11A through 14C.
Enter the date of marriage (month day year) in 11A and the place of marriage (City & State) in 11B; for 12, Did the marriage continue until date of death? mark Yes or No.
13A. Did deceased have any previous marriages? Yes or No. If yes, complete 13B & 13C.
14A. Did you have any previous marriages? Yes or No. If yes, complete 14B & 14C.
13B and 14B. Previous marriage terminated by: Death or Divorce. 13C and 14C. Date previous marriage terminated (if divorced within last 5 years, attach copy of the divorce decree).
Part II, items 15A to 17, the next of kin
If you were NOT married to the deceased when he/she died and were not specifically named as his/her insurance beneficiary, complete Part II through 15D.
Be sure to provide the required information as to the deceased's marital status and any children.
In the table, list the name, age, relationship, and address of (a) widow or widower: None. If none, was insured ever married?
If Yes, did marriage terminate by: Divorce (mm dd yyyy) or Death (mm dd yyyy)? (b) If there is no surviving widow or widower, list all the children of the deceased.
Include any adopted child or illegitimate child and indicate each child's status. List the descendants of any deceased child or children. If no children, check box: (c) If there are no children or descendants of children, list the surviving parent or parents.
Is the father deceased? Yes or No. Is the mother deceased? Yes or No.
If there are no survivors within the degrees indicated in (a) through (c), then under (d) list the next of kin who may be capable of inheriting from the deceased (brothers, sisters, descendants of deceased brothers or sisters, etc.).
In items 15A through 15D, provide the information about persons indicated in the answers to the preceding questions.
Enter 15A. Name, 15B. Age, 15C. Relationship to deceased and 15D. Address.
Use a separate signed sheet if necessary.
Complete items 16 and 17 ONLY if any of the persons listed in the table are under the age of 21.
16. Name and address of guardian for any minor children listed in the table if one has been appointed by the court. (Attach copy of appointment paper issued by court.)
17. If a guardian has not been appointed, will one be appointed? Yes or No.
Part III, the estate (18 and 19)
Complete Part III if you were not named as the insurance beneficiary, were NOT married to the deceased at his/her death, and are not a parent of the deceased.
18. Name and address of the executor or administrator, if any, appointed by the court to settle the estate of the deceased.
19. If an executor has not been appointed, will one be appointed? Yes or No.
Part IV, the method of payment
In the event the insured has not previously elected 36 monthly installments, my preferred method of payment is:
Mark one: Lump Sum - Alliance Account, Lump Sum - Check, or Lump Sum - Electronic Funds Transfer (EFT) - Please provide your banking information in Part IV.
Or mark 36 equal monthly payments - Check, or 36 equal monthly payments - Electronic Funds Transfer (EFT) - Please provide your banking information in Part IV.
Failure to designate a Method of Payment will delay the claim payment.
Common mistake: Electronic Funds Transfer. The full amount due will be transferred to the bank account you provide on the Claim for Death Benefits. The account MUST be in your name as the designated beneficiary.
For EFT only - Please provide your banking information in Part IV to have the benefit paid by Electronic Funds Transfer. Bank Routing Number, Bank Account Number, Checking or Savings.
The bank routing number is always 9 digits.
The bank account number varies in length and may contain dashes or spaces.
Enter the Bank Name, Bank Phone Number, and your First Name, MI and Last Name.
Part V, certification by claimant (20 to 24)
Parts IV and V must be completed by all claimants.
By signing, you certify that all statements made in this claim are true to the best of your knowledge, information, and belief and that no evidence necessary to a settlement of this claim is suppressed or withheld.
Sign on line 20, Signature of claimant, and enter your 21. Address (Number and Street, Apt. No., City, State, ZIP Code).
Enter 22. Date, 23. Phone and 24. Claimant Email Address.
More rules for SGLV 8283
SGLI and VGLI death benefits will be paid to the beneficiary designated by the insured.
If no beneficiary has been named, the proceeds are payable to: the widow or widower of the insured; if none, the child or children in equal shares with the share of any deceased child distributed among the descendants of the child; if none, parent(s) in equal shares; if none, a duly appointed executor or administrator of the insured's estate, and if none, other next of kin.
Common questions about SGLV 8283
Is there a penalty?
Any intentionally false statement in this claim or willful misrepresentation relative thereto is subject to punishment by a fine of not more than $10,000 or imprisonment of not more than 5 years, or both (18 U.S.C. 1001) (checked November 8, 2026).
When is this form not the right one?
This form is not to be used for National Service Life Insurance (NSLI) or United States Government Life Insurance.
Where to get help with SGLV 8283
If you have questions, please call the Office of Servicemembers' Group Life Insurance at 1-800-419-1473.
Sources
[1] SGLV 8283 (Ed. 06/2026), Claim for Death Benefits, Department of Veterans Affairs (the Official source link on this page).