
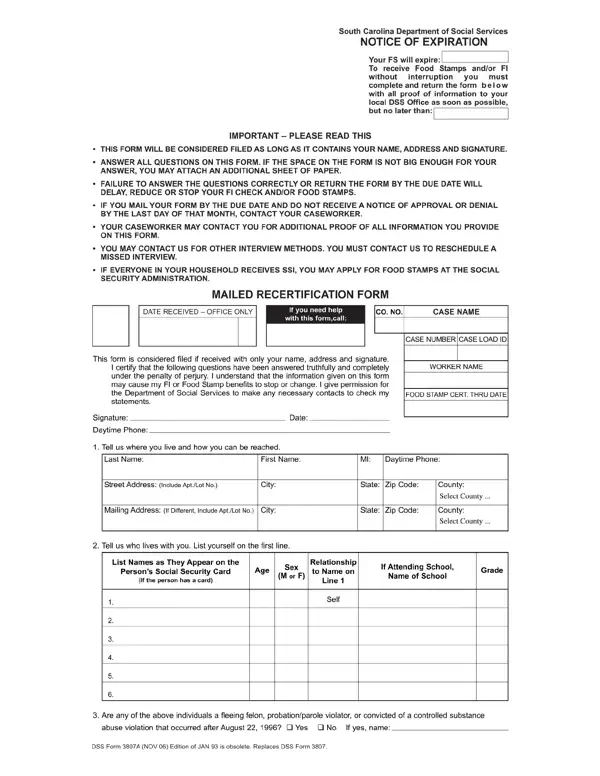

DSS Form 3807A at a glance
What it is: South Carolina Department of Social Services NOTICE OF EXPIRATION: your Supplemental Nutrition Assistance Program (SNAP) and/or Temporary Assistance for Needy Families (TANF) benefits will expire on the day entered in the box.
Who signs: Enter your SIGNATURE and the DATE.
A filled-in DSS Form 3807A example: a SNAP renewal for two people
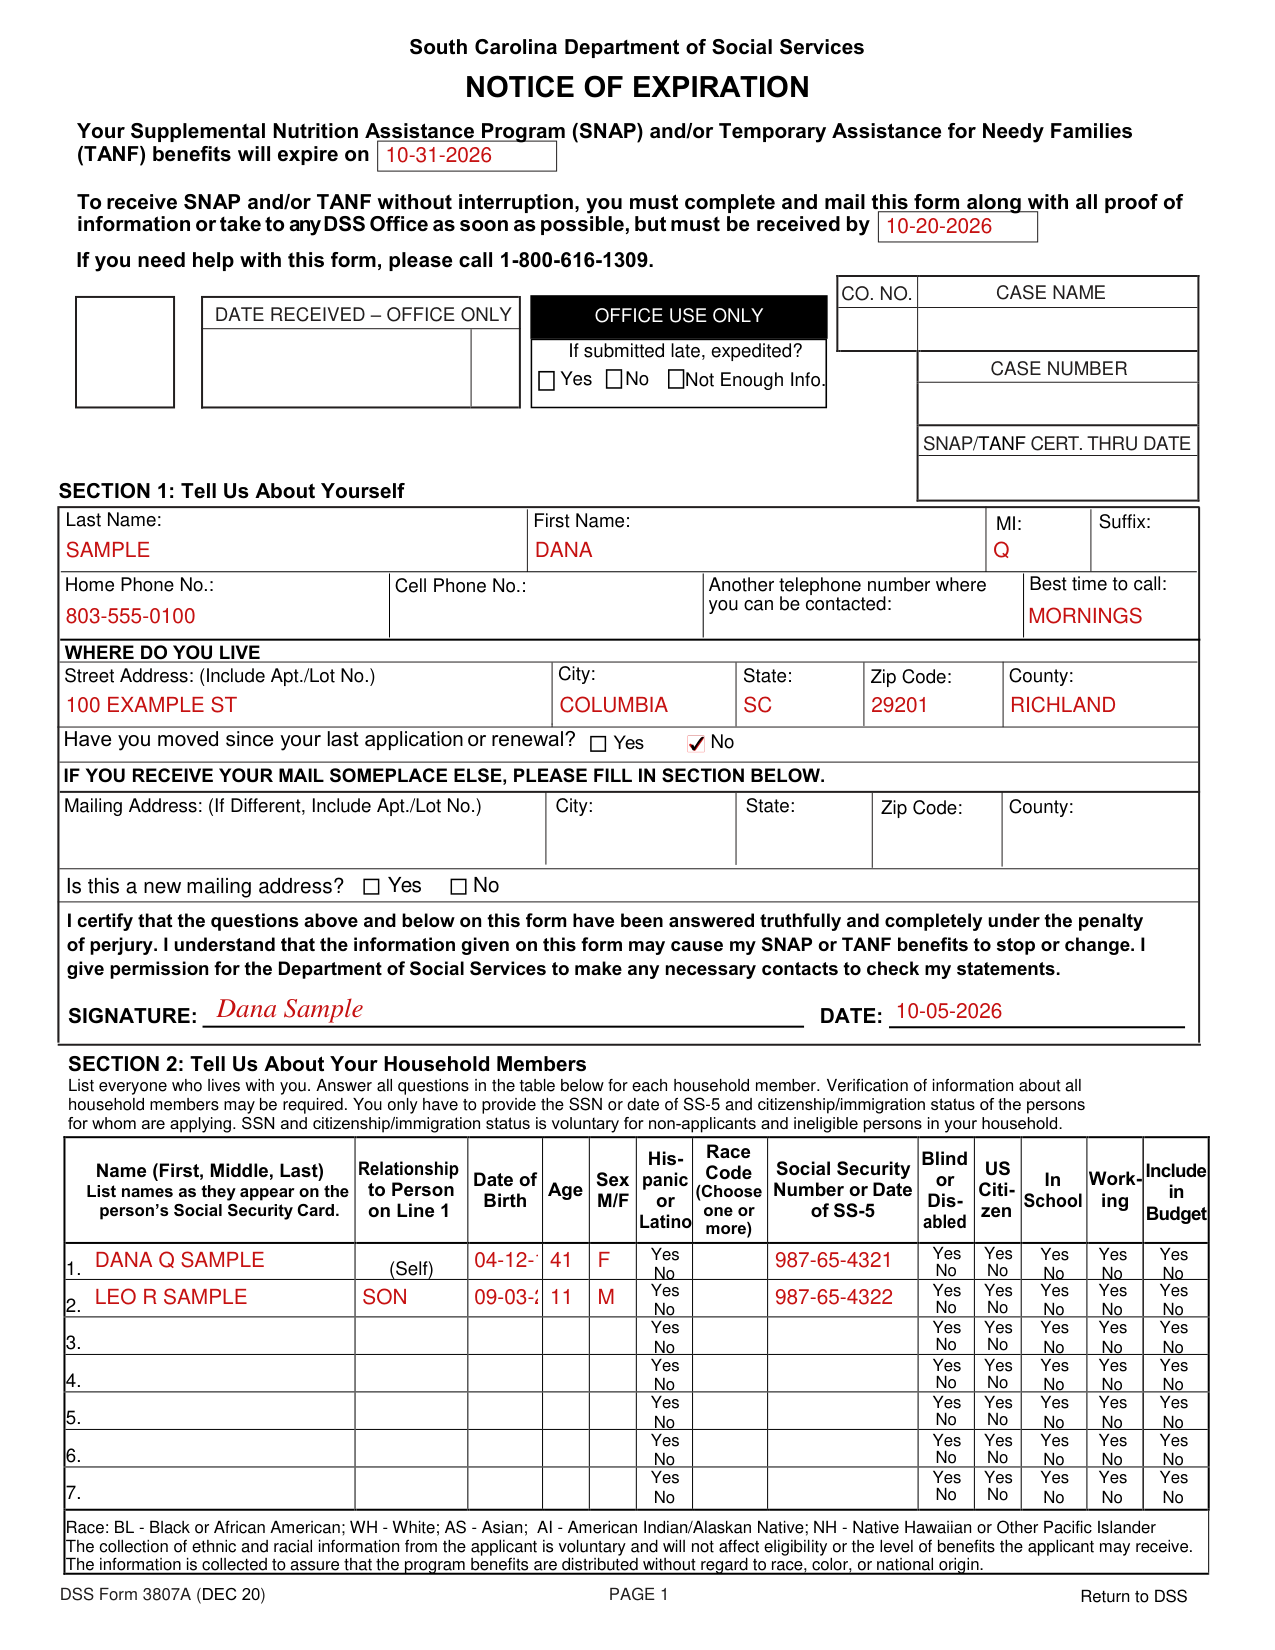
How to fill out DSS Form 3807A, box by box
Received after the due date

Forms received after the due date, or without the requested proof, will be considered late/incomplete and may delay your SNAP/TANF benefits for the next month.
Last Name, First Name, MI and Suffix
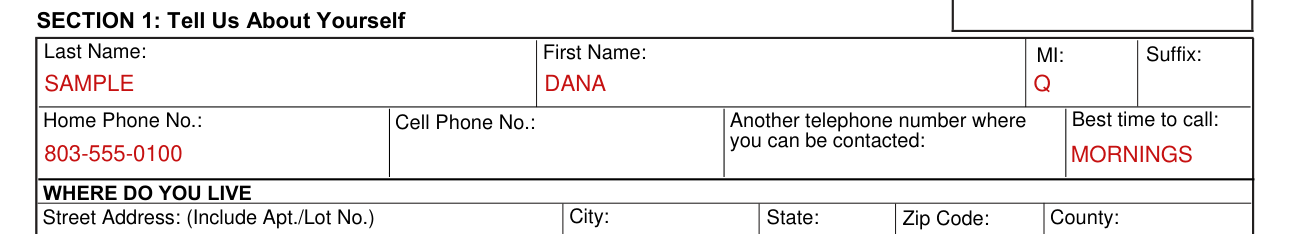
Under SECTION 1, enter your Last Name, First Name, MI and Suffix.
Enter your Home Phone No., Cell Phone No., another telephone number where you can be contacted, and the Best time to call.
Where do you live
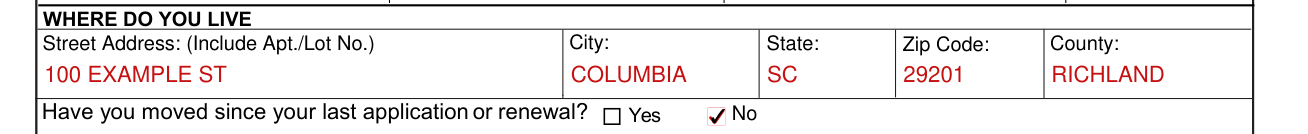
Under WHERE DO YOU LIVE, enter the Street Address (Include Apt./Lot No.), City, State, Zip Code and County.
Mark Yes or No for: Have you moved since your last application or renewal?
Mailing address

If you receive your mail someplace else, fill in the Mailing Address (If Different, Include Apt./Lot No.), City, State, Zip Code and County.
Mark Yes or No for: Is this a new mailing address?
I certify

You certify that the questions on this form have been answered truthfully and completely under the penalty of perjury. You understand that the information given on this form may cause your SNAP or TANF benefits to stop or change, and you give permission for the Department of Social Services to make any necessary contacts to check your statements.
Household members
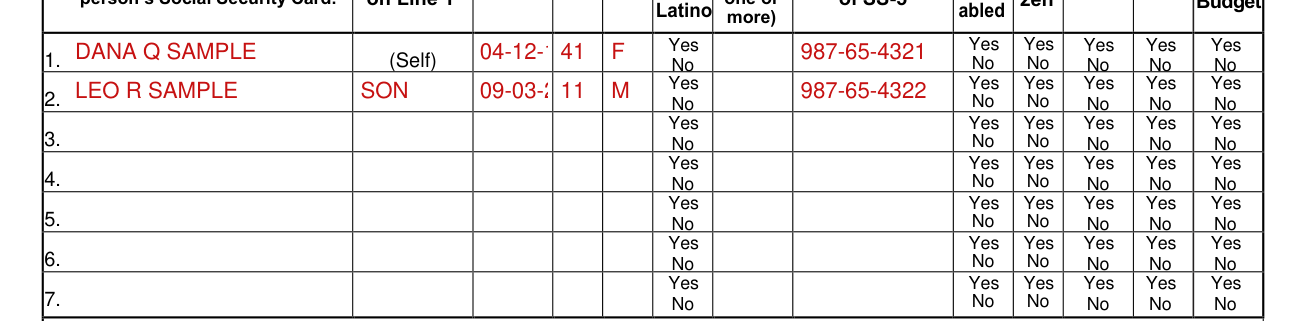
Under SECTION 2, list everyone who lives with you and answer all questions in the table for each household member. You only have to provide the SSN or date of SS-5 and citizenship/immigration status of the persons for whom are applying. SSN and citizenship/immigration status is voluntary for non-applicants and ineligible persons in your household.
List names as they appear on the person's Social Security Card.
Providing the requested information, including the SSN of each household member, is voluntary. However, failure to provide an SSN will result in the denial of SNAP benefits to each individual failing to provide an SSN.
Race Code (Choose one or more): BL - Black or African American; WH - White; AS - Asian; AI - American Indian/Alaskan Native; NH - Native Hawaiian or Other Pacific Islander. The collection of ethnic and racial information from the applicant is voluntary and will not affect eligibility or the level of benefits the applicant may receive. The information is collected to assure that the program benefits are distributed without regard to race, color, or national origin.
Pregnant, special setting, household assets and offenses
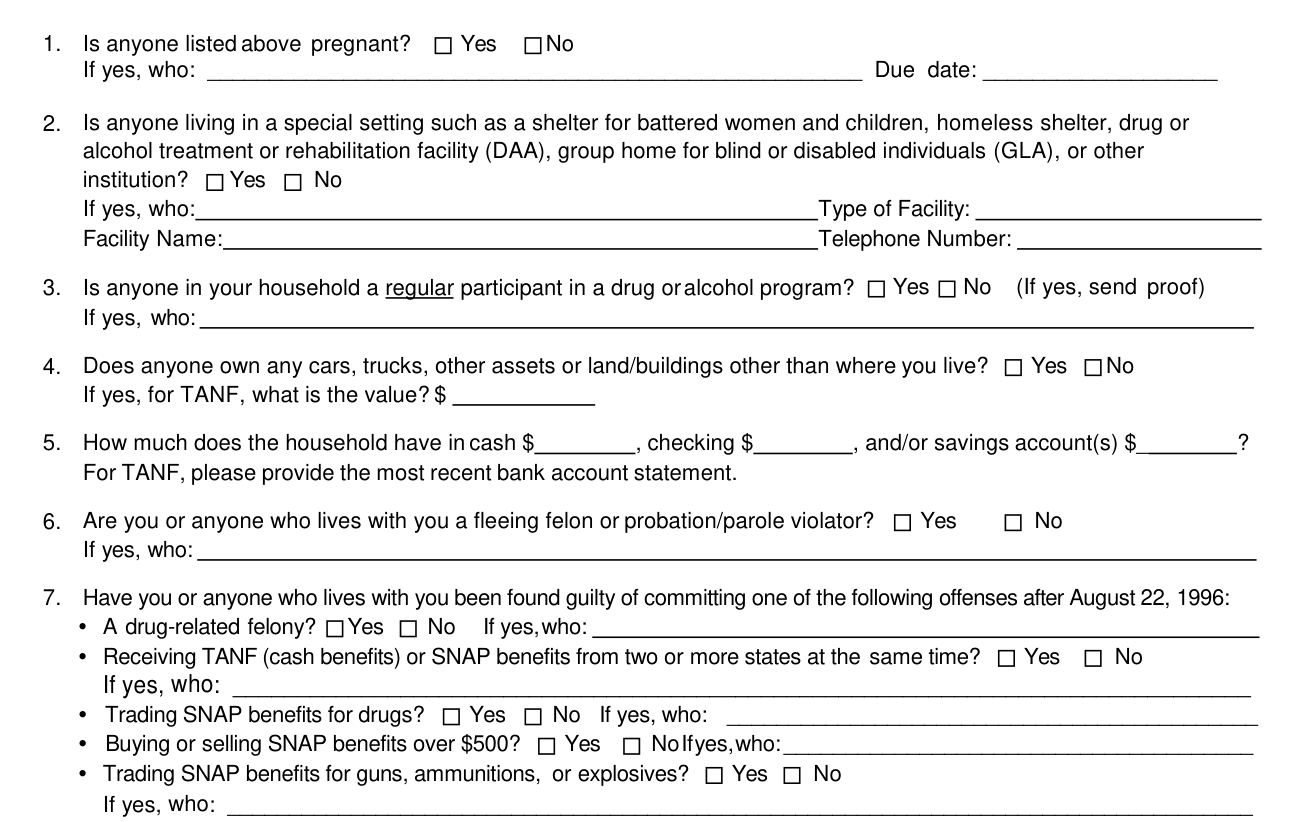
1. Is anyone listed on this form pregnant? Mark Yes or No; if yes, enter who and the Due date.
2. Is anyone living in a special setting such as a shelter for battered women and children, homeless shelter, drug or alcohol treatment or rehabilitation facility, group home for blind or disabled individuals, or other institution? Mark Yes or No; if yes, enter who, Type of Facility, Facility Name and Telephone Number.
3. Is anyone in your household a regular participant in a drug or alcohol program? Mark Yes or No; if yes, send proof and enter who.
4. Does anyone own any cars, trucks, other assets or land/buildings other than where you live? Mark Yes or No; if yes, for TANF, enter the value.
5. How much does the household have in cash, checking, and/or savings account(s)? For TANF, please provide the most recent bank account statement.
6. Are you or anyone who lives with you a fleeing felon or probation/parole violator? Mark Yes or No; if yes, enter who.
7. Mark Yes or No, and if yes enter who, for each offense of which you or anyone who lives with you has been found guilty of committing after August 22, 1996. A drug-related felony. Receiving TANF (cash benefits) or SNAP benefits from two or more states at the same time. Trading SNAP benefits for drugs. Buying or selling SNAP benefits over $500 (checked October 22, 2026). Trading SNAP benefits for guns, ammunitions, or explosives.
For Temporary Assistance for Needy Families ONLY
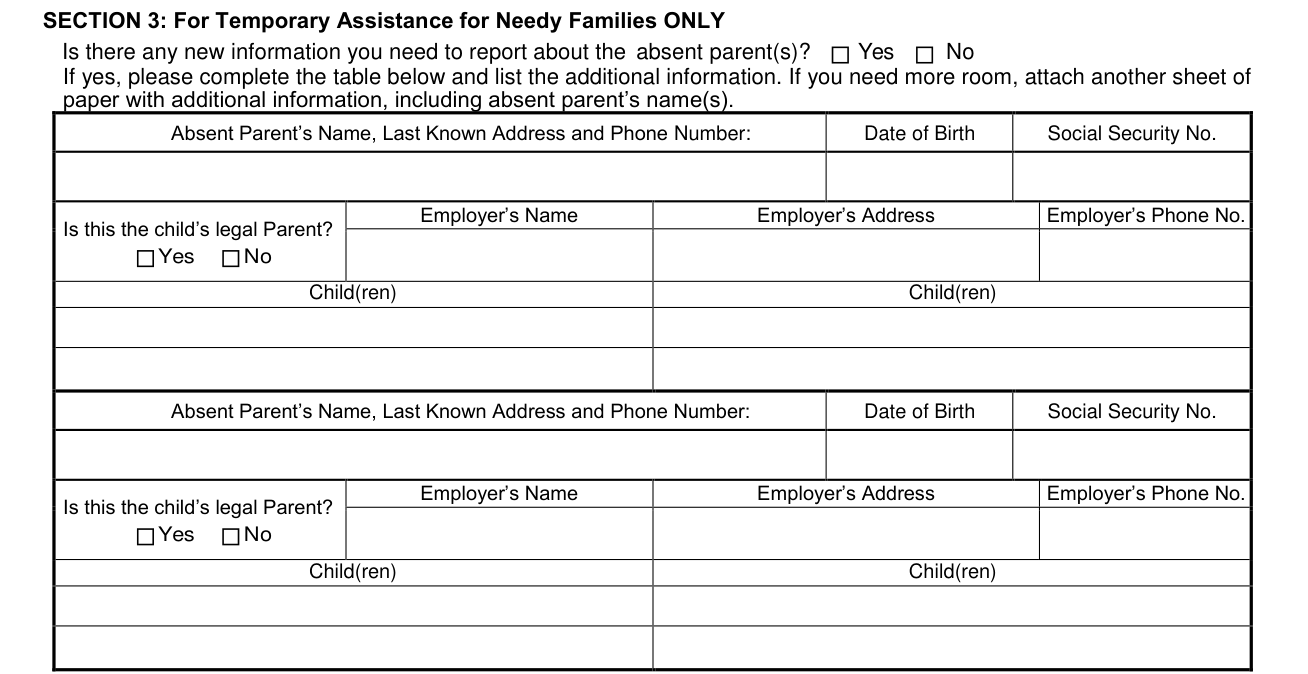
SECTION 3 is For Temporary Assistance for Needy Families ONLY. Is there any new information you need to report about the absent parent(s)? Mark Yes or No; if yes, please complete the table and list the additional information.
For each absent parent enter the Absent Parent's Name, Last Known Address and Phone Number, Date of Birth, Social Security No., Employer's Name, Employer's Address, Employer's Phone No., Child(ren), and Yes or No for: Is this the child's legal Parent?
Your Household Income
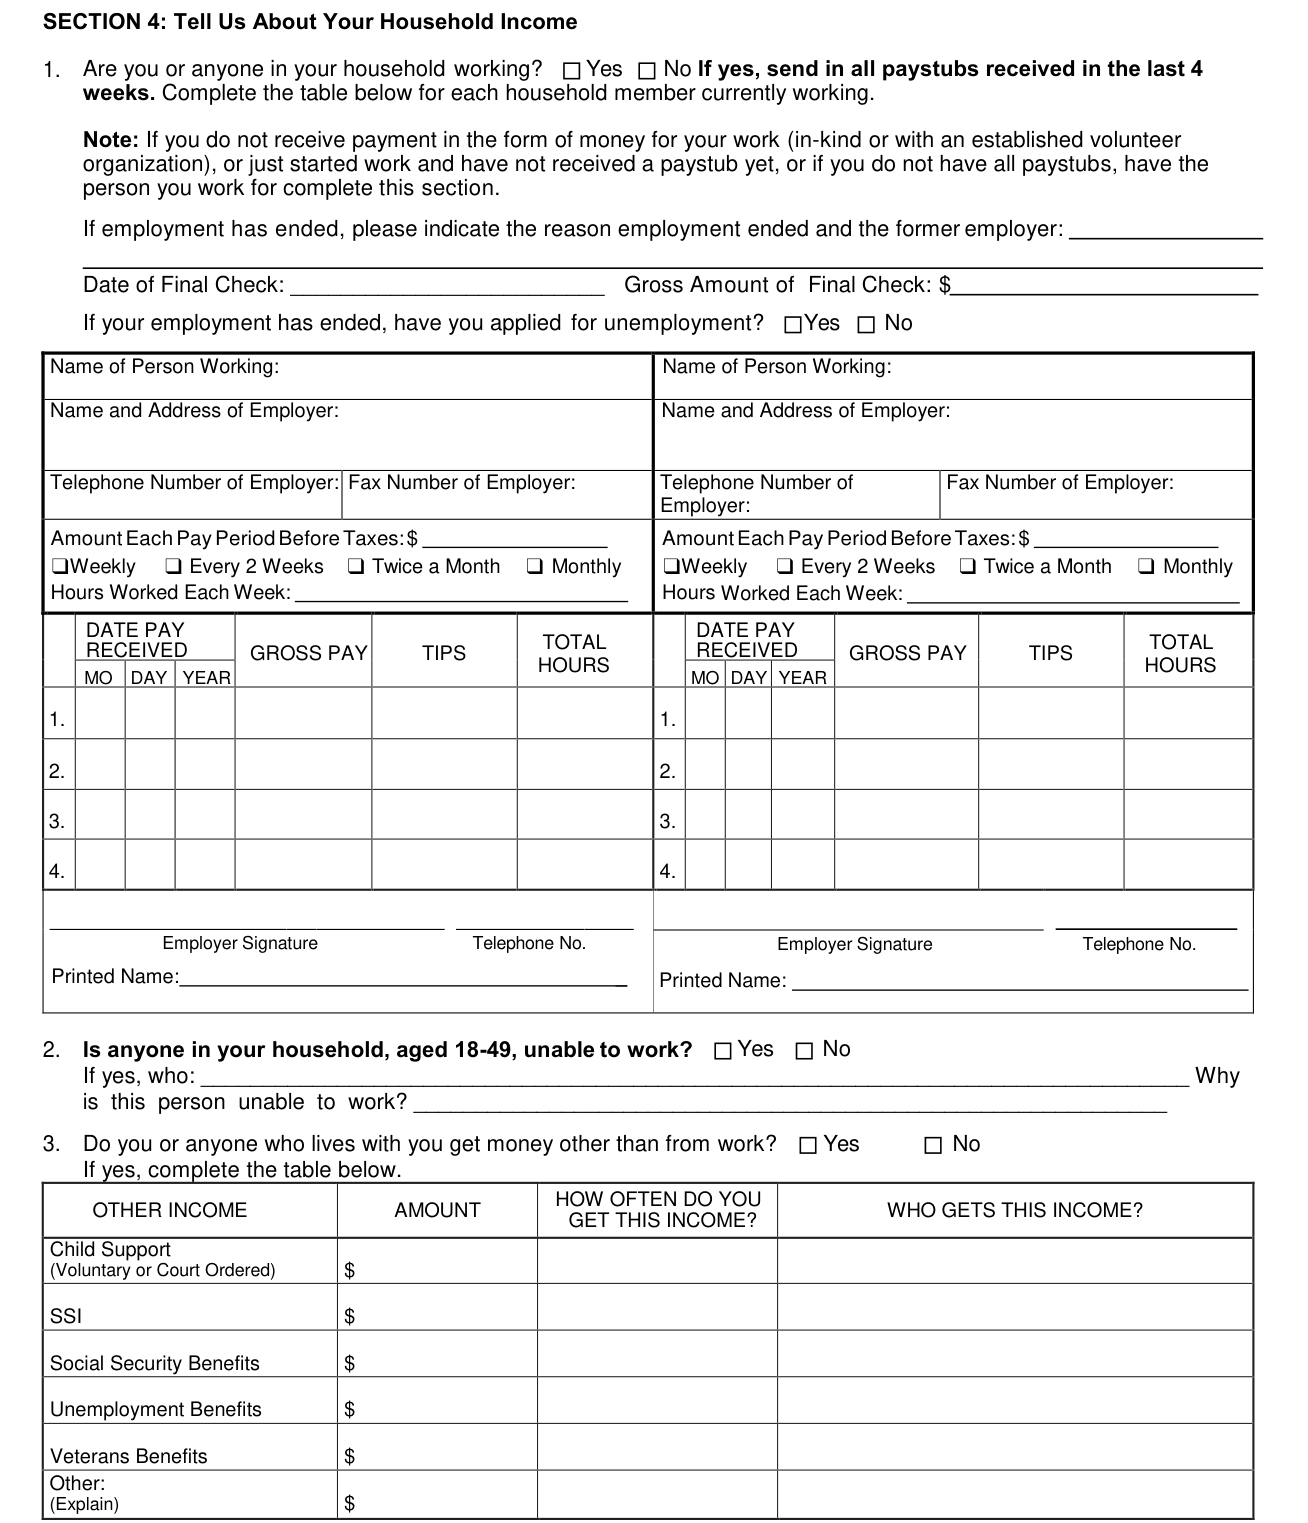
Under SECTION 4, mark Yes or No for: Are you or anyone in your household working? If yes, send in all paystubs received in the last 4 weeks and complete the table for each household member currently working.
If you do not receive payment in the form of money for your work (in-kind or with an established volunteer organization), or just started work and have not received a paystub yet, or if you do not have all paystubs, have the person you work for complete this section.
If employment has ended, please indicate the reason employment ended and the former employer, the Date of Final Check, the Gross Amount of Final Check, and mark Yes or No for: have you applied for unemployment?
2. Is anyone in your household, aged 18-49, unable to work? Mark Yes or No; if yes, enter who and why this person is unable to work.
3. Do you or anyone who lives with you get money other than from work? Mark Yes or No; if yes, complete the table.
For Child Support (Voluntary or Court Ordered), SSI, Social Security Benefits, Unemployment Benefits, Veterans Benefits and Other (Explain), enter the OTHER INCOME AMOUNT, how often you get this income, and who gets this income.
Your Household Expenses
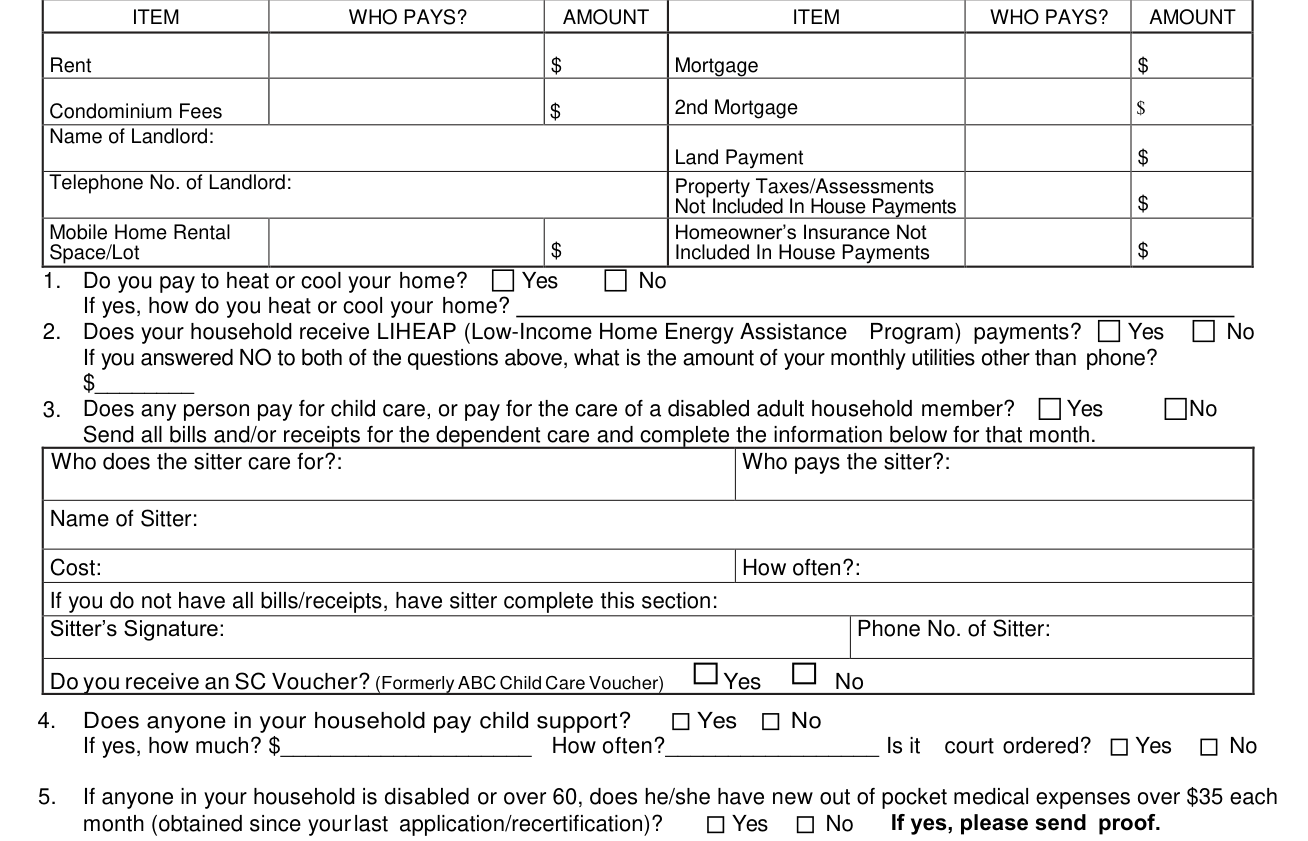
Under SECTION 5, list any expenses that you or anyone who lives with you pays for and send proof of the expenses.
Do you pay to heat or cool your home? Mark Yes or No; if yes, enter how you heat or cool your home.
Does your household receive LIHEAP (Low-Income Home Energy Assistance Program) payments? Mark Yes or No. If you answered NO to both of the questions, enter the amount of your monthly utilities other than phone. 3. Does any person pay for child care, or pay for the care of a disabled adult household member? Mark Yes or No; if yes, send all bills and/or receipts for the dependent care and complete the information for that month: who the sitter cares for, who pays the sitter, Name of Sitter, Cost and how often. If you do not have all bills/receipts, have sitter complete this section with the Sitter's Signature and Phone No. of Sitter.
If anyone in your household is disabled or over 60, does he/she have new out of pocket medical expenses over $35 each month (obtained since your last application/recertification)? Mark Yes or No; if yes, please send proof (checked October 22, 2026)
More rules for DSS Form 3807A
This form will be considered filed as long as it contains a legible name, address, and signature.
Common questions about DSS Form 3807A
Where do I file it?
To receive SNAP and/or TANF without interruption, you must complete and mail this form along with all proof of information or take it to any DSS Office as soon as possible, but it must be received by the day entered in the box after "must be received by".
Is there a penalty?
Violators of the SNAP Warnings and Penalties rules may not be able to get SNAP benefits for a period of 1 year to permanently and may be fined up to $250,000 or imprisoned up to 20 years or both (checked October 22, 2026)
Where to get help with DSS Form 3807A
If you need help with this form, please call 1-800-616-1309.
Sources
[1] DSS Form 3807A (DEC 20), Notice of Expiration, South Carolina Department of Social Services (the Official source link on this page).