

Form SSA-8010-BK at a glance
What it is: Form SSA-8010-BK is the STATEMENT OF INCOME AND RESOURCES, to determine eligibility for Supplemental Security Income and benefits under the other programs administered by the Social Security Administration.
Who signs: Sign in ink as Your Signature (First name, middle initial, last name) with the DATE (MM/DD/YYYY), and add the Spouse's Signature (First name, middle initial, last name) (Write in ink).
A filled-in Form SSA-8010-BK example: both answer No to public income maintenance payments
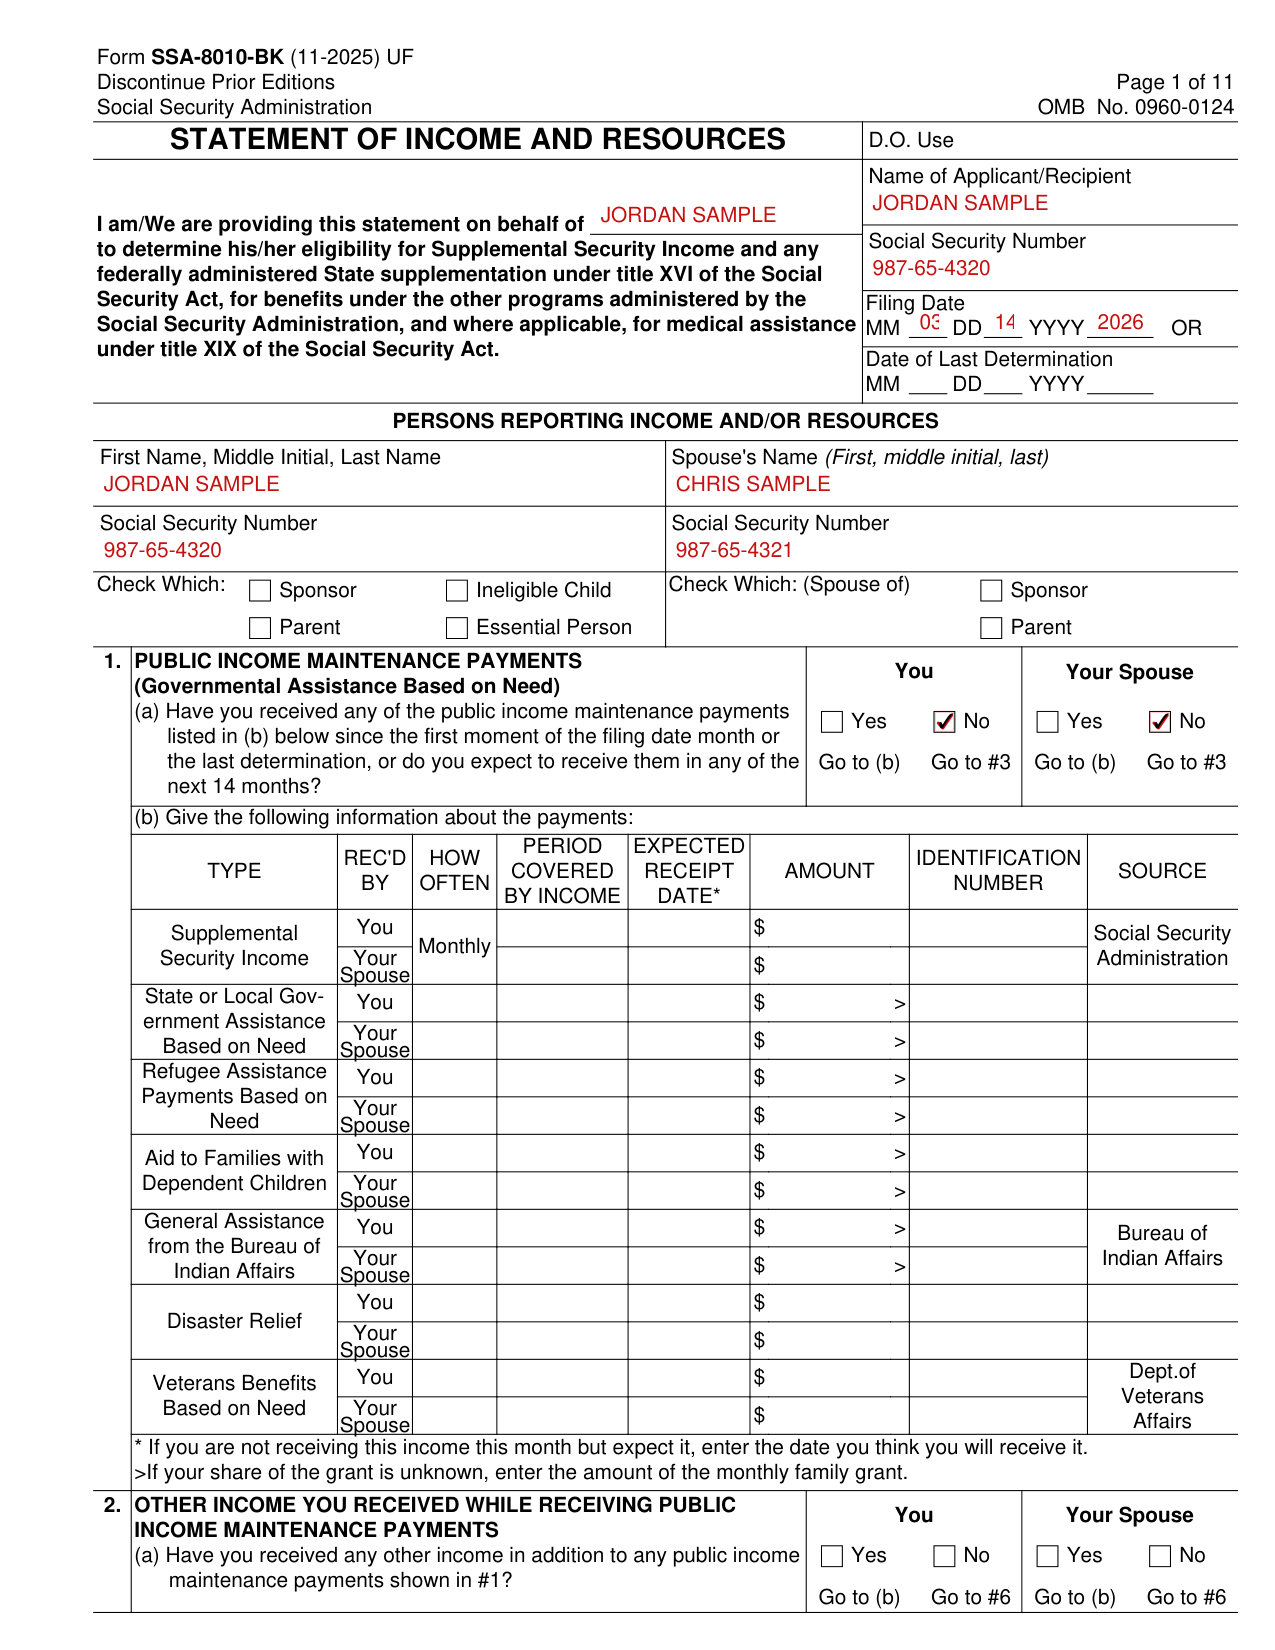
How to fill out Form SSA-8010-BK, box by box
Persons reporting income and resources
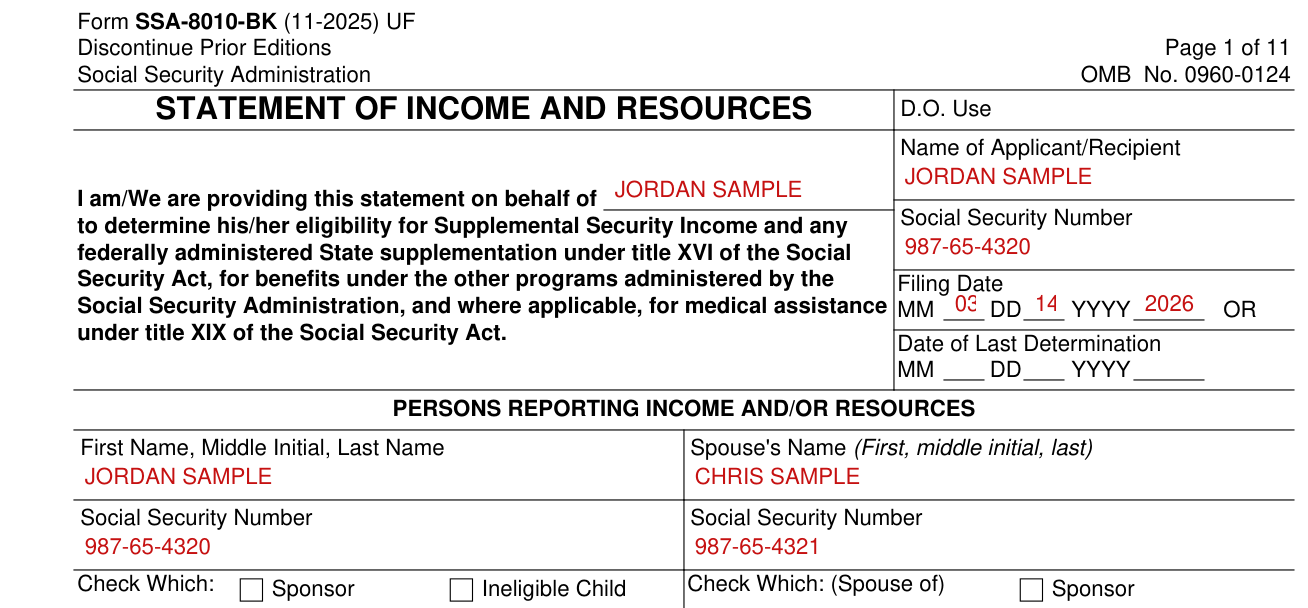
State on behalf of whom you are providing this statement, to determine his/her eligibility for Supplemental Security Income and any federally administered State supplementation under title XVI of the Social Security Act.
Enter the Name of Applicant/Recipient and the Social Security Number.
Enter the Filing Date MM DD YYYY OR the Date of Last Determination MM DD YYYY.
Under PERSONS REPORTING INCOME AND/OR RESOURCES, enter First Name, Middle Initial, Last Name and the Social Security Number.
Enter the Spouse's Name (First, middle initial, last) and the Social Security Number.
Check Which
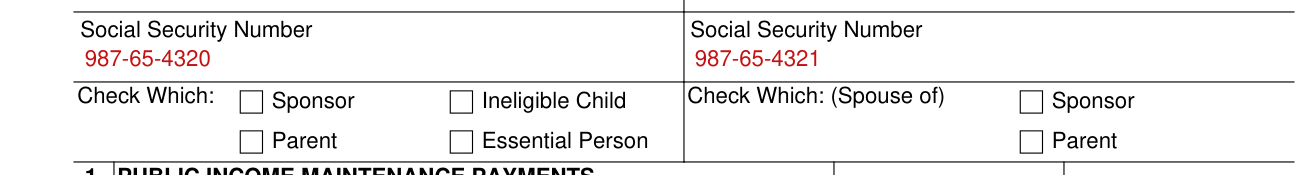
Check Which: Sponsor, (Spouse of) Sponsor, Ineligible Child, Parent, Essential Person.
1. Public income maintenance payments
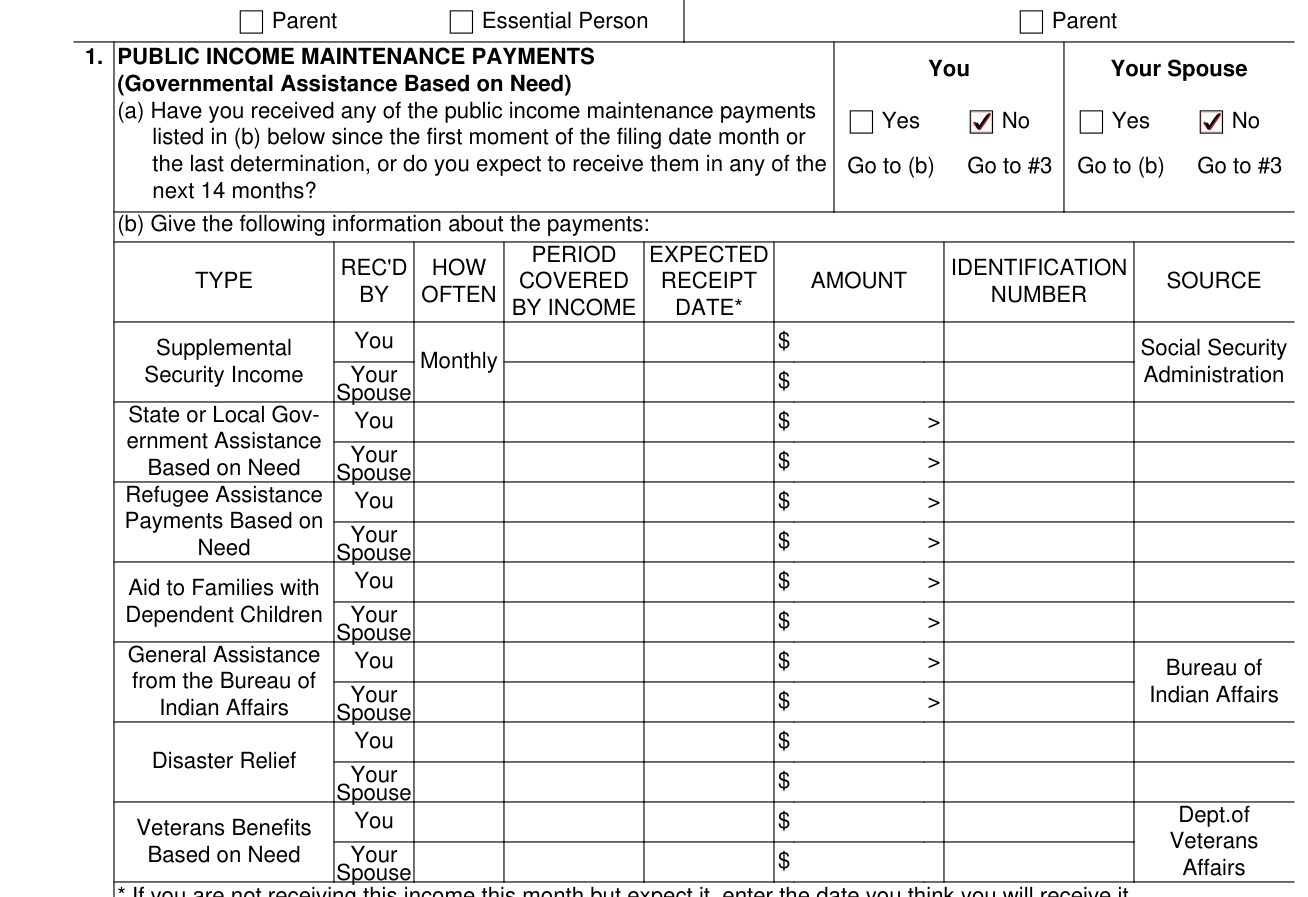
Check the box for You and Your Spouse: Have you received any of the public income maintenance payments listed in (b) since the first moment of the filing date month or the last determination, or do you expect to receive them in any of the next 14 months?
Yes: Go to (b). No: Go to #3.
In (b), give the following information about the payments.
Expected Receipt Date*: if you are not receiving this income this month but expect it, enter the date you think you will receive it. If your share of the grant is unknown, enter the amount of the monthly family grant.
2. Other income while receiving public income maintenance payments

Check the box: Have you received any other income in addition to any public income maintenance payments shown in #1?
Yes: Go to (b). No: Go to #6.
3. Wages
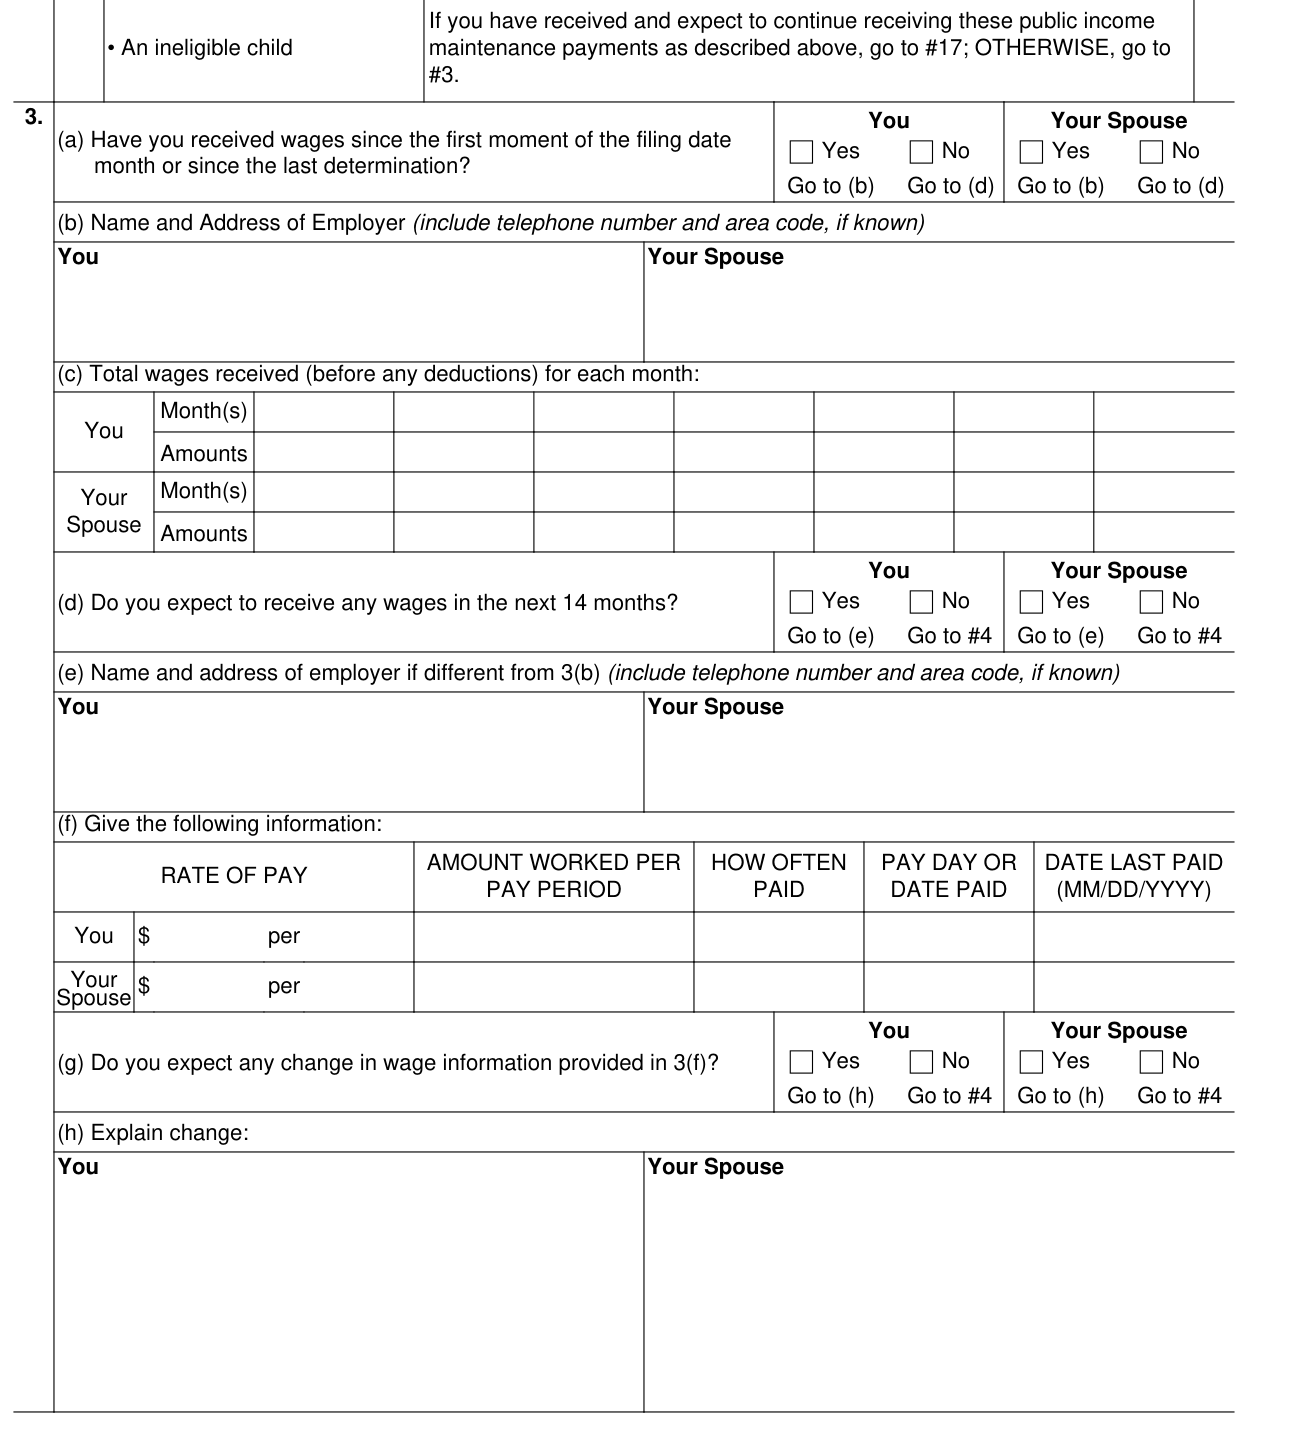
Check the box: Have you received wages since the first moment of the filing date month or since the last determination?
Under (b), enter the Name and Address of Employer (include telephone number and area code, if known).
Under (c), enter the total wages received (before any deductions) for each month.
Under (d), check the box: Do you expect to receive any wages in the next 14 months?
Under (f), enter the rate of pay amount worked per pay period, how often paid, pay day or date paid and date last paid (MM/DD/YYYY).
Check the box: Do you expect any change in wage information provided in 3(f)?
Under (h), explain the change.
4. Self-employment
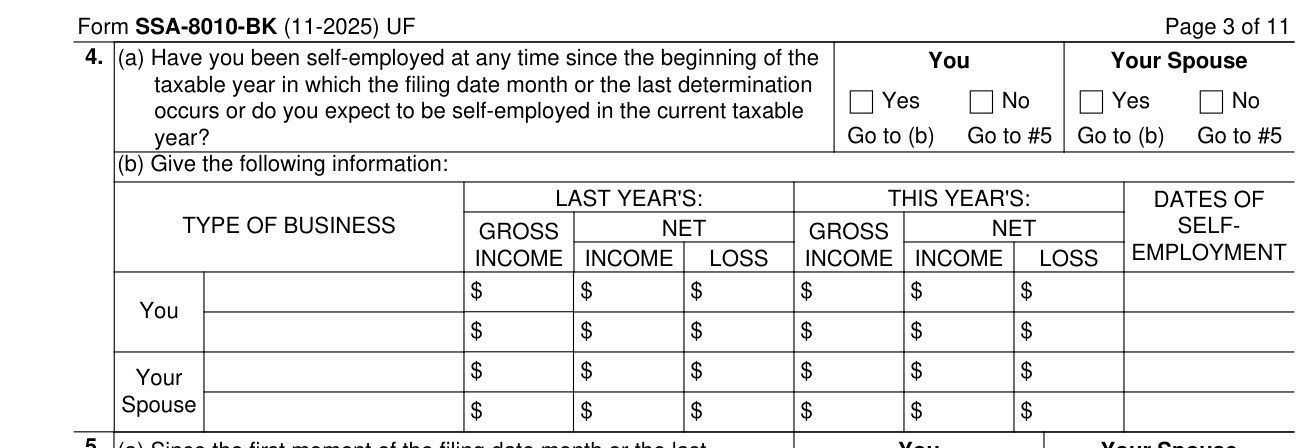
Check the box: Have you been self-employed at any time since the beginning of the taxable year in which the filing date month or the last determination occurs or do you expect to be self-employed in the current taxable year?
Under (b), enter last year's and this year's gross income, net income loss, dates of self-employment and type of business.
5. Other income sources

Check the box for You and Your Spouse: Since the first moment of the filing date month or the last determination, have you received or do you expect to receive income in the next 14 months from any of the following sources?
Check the box for each: federal benefits, state/local benefits, private benefits, miscellaneous and other income not previously mentioned.
5 (b). Information on each Yes answer
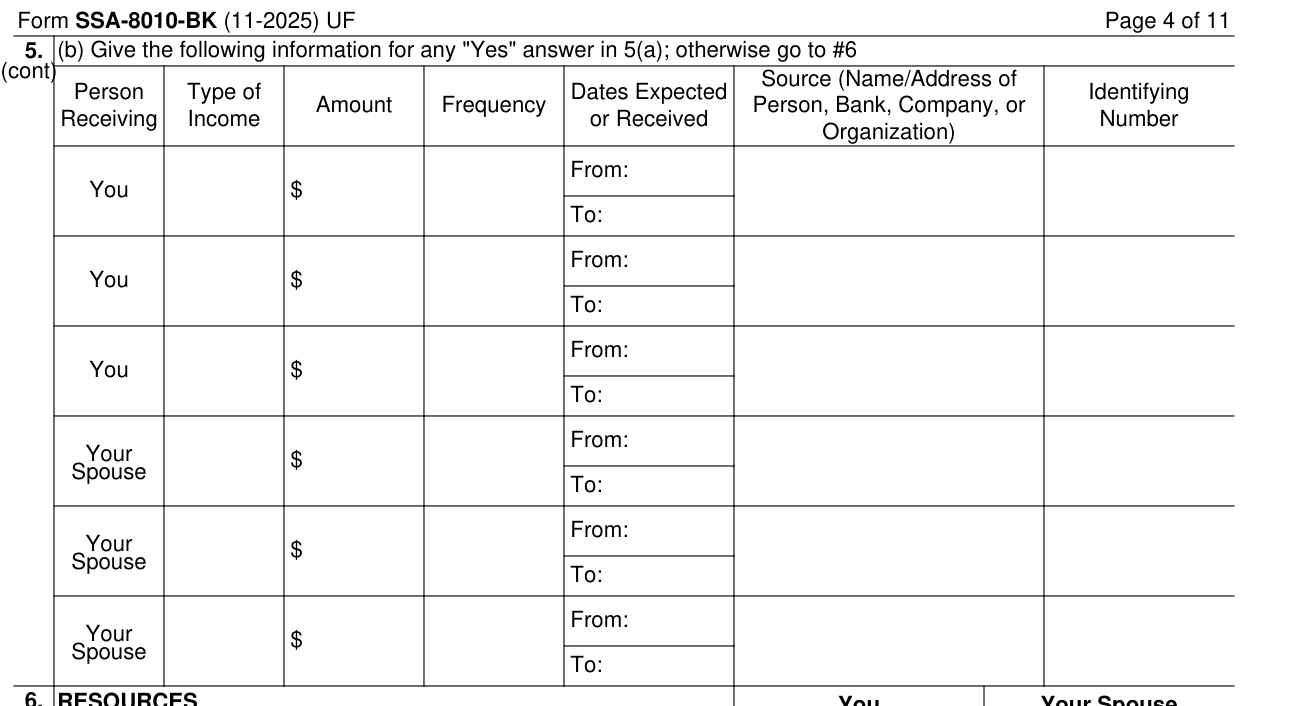
Give the following information for any "Yes" answer in 5(a); otherwise go to #6.
Under Source, enter the Name/Address of Person, Bank, Company, or Organization.
6. Real estate
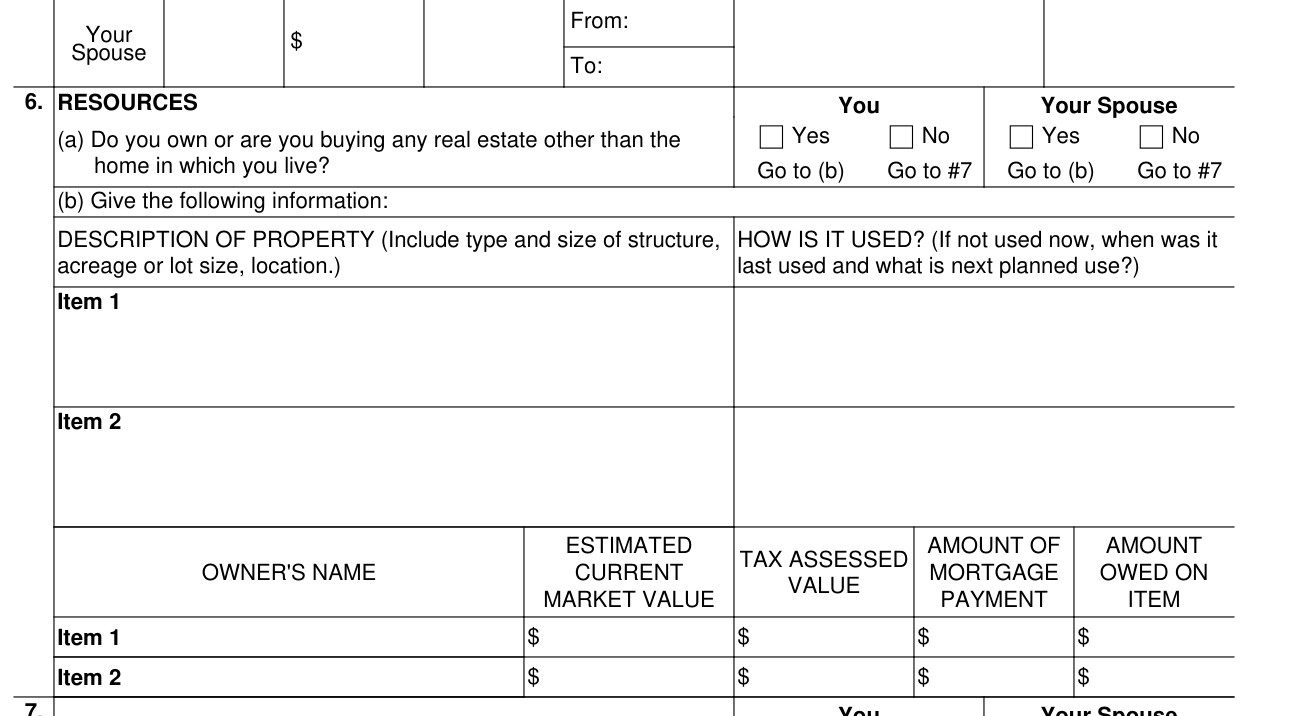
Do you own or are you buying any real estate other than the home in which you live?
Under DESCRIPTION OF PROPERTY, include type and size of structure, acreage or lot size, location.
Under HOW IS IT USED?, if not used now, say when it was last used and what is next planned use.
7. Vehicles
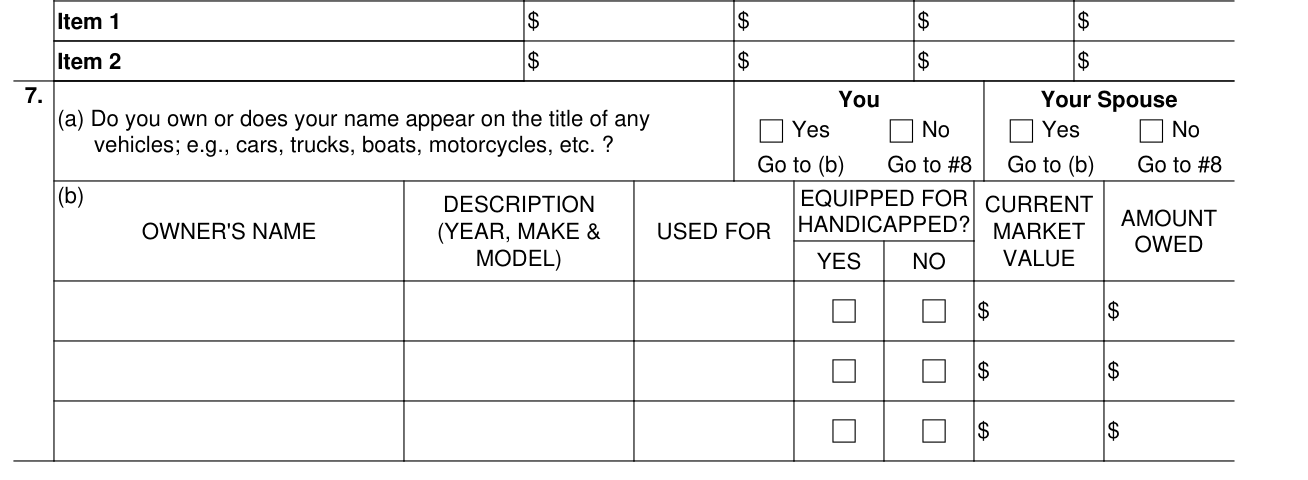
Do you own or does your name appear on the title of any vehicles; e.g., cars, trucks, boats, motorcycles, etc.?
Under (b), enter the description (year, make & model), current market value, amount owed, owner's name, used for and equipped for handicapped? yes no.
8. Life insurance
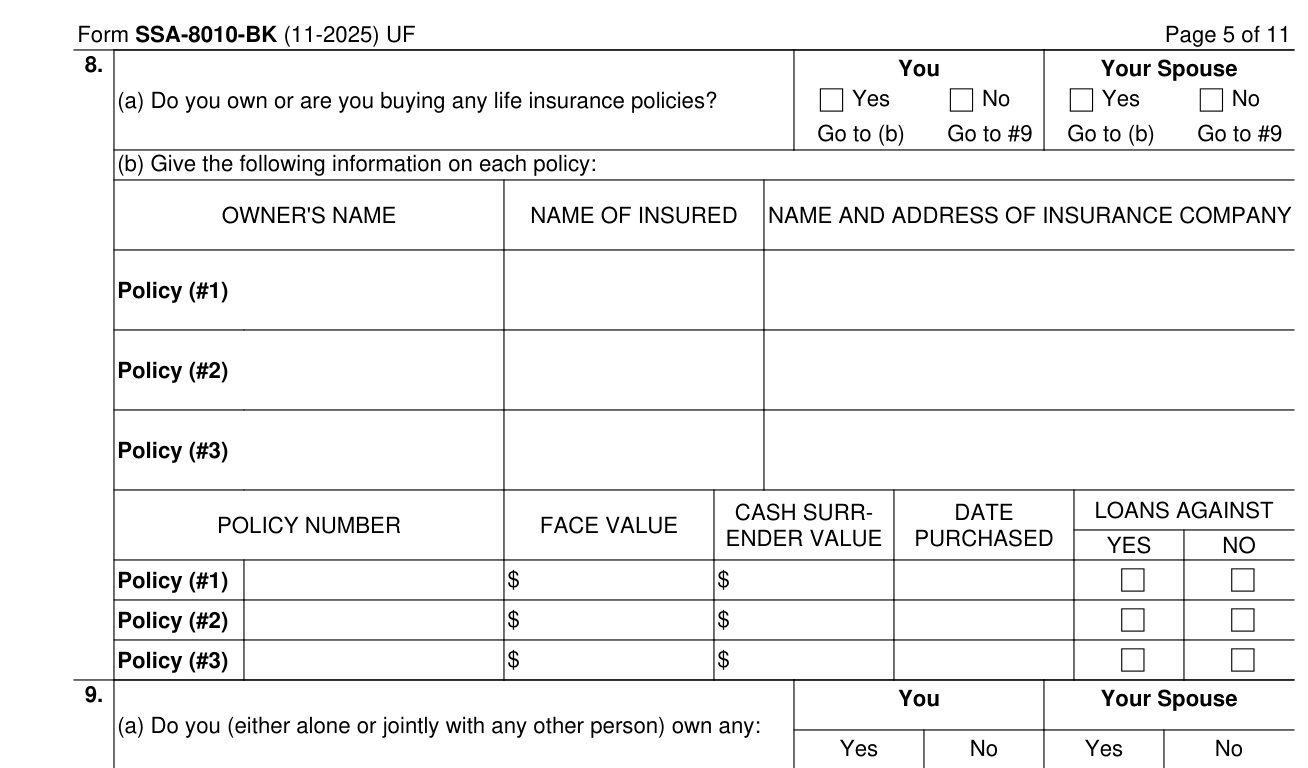
Do you own or are you buying any life insurance policies?
Under (b), enter on each policy the owner's name, name of insured, name and address of insurance company, policy number, face value, cash surrender value, date purchased and loans against.
10. Cash and accounts

Do you own or does your name appear (either alone or with any other person's name) on any of the following items?
The items are cash at home, with you, or anywhere else; checking accounts; savings accounts; credit union accounts; Christmas Club accounts; certificates of deposit; notes; stocks or mutual funds; bonds; and other items that can be turned into cash.
10 (b). Information on each Yes answer
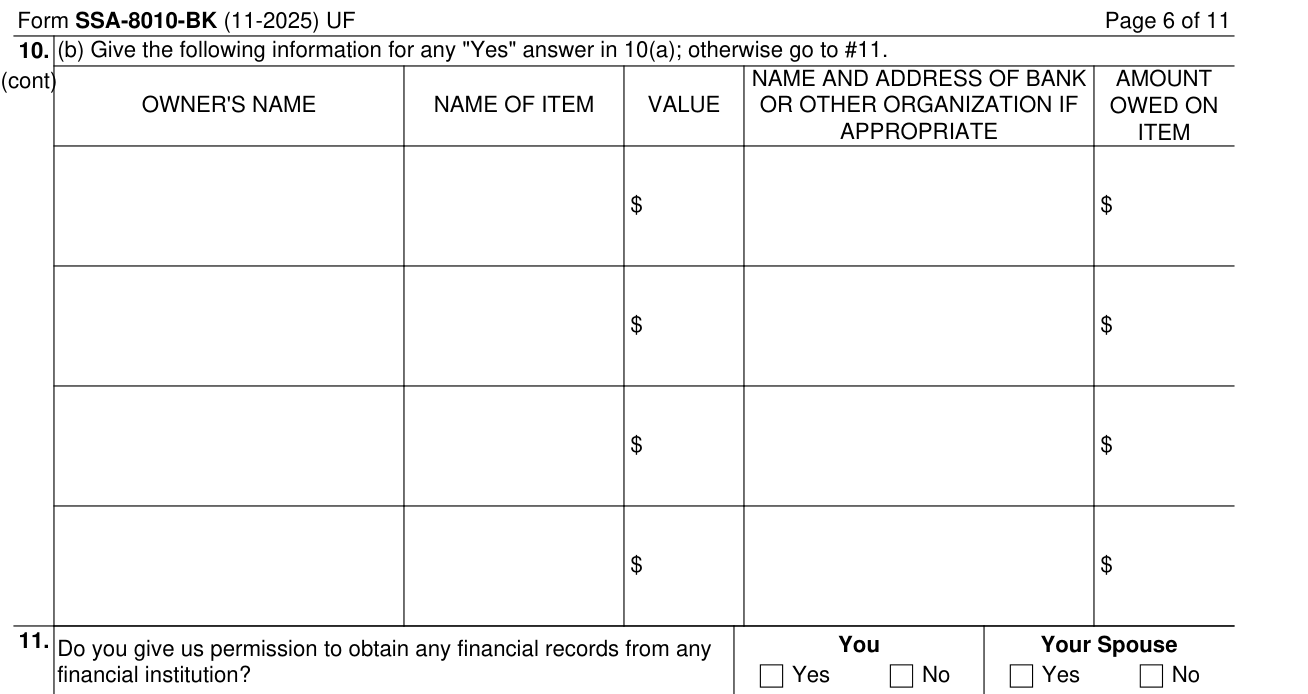
Give the following information for any "Yes" answer in 10(a); otherwise go to #11.
Enter the name and address of the bank or other organization if appropriate, the OWNER'S NAME, NAME OF ITEM, VALUE and AMOUNT OWED ON ITEM.
12. Burial assets
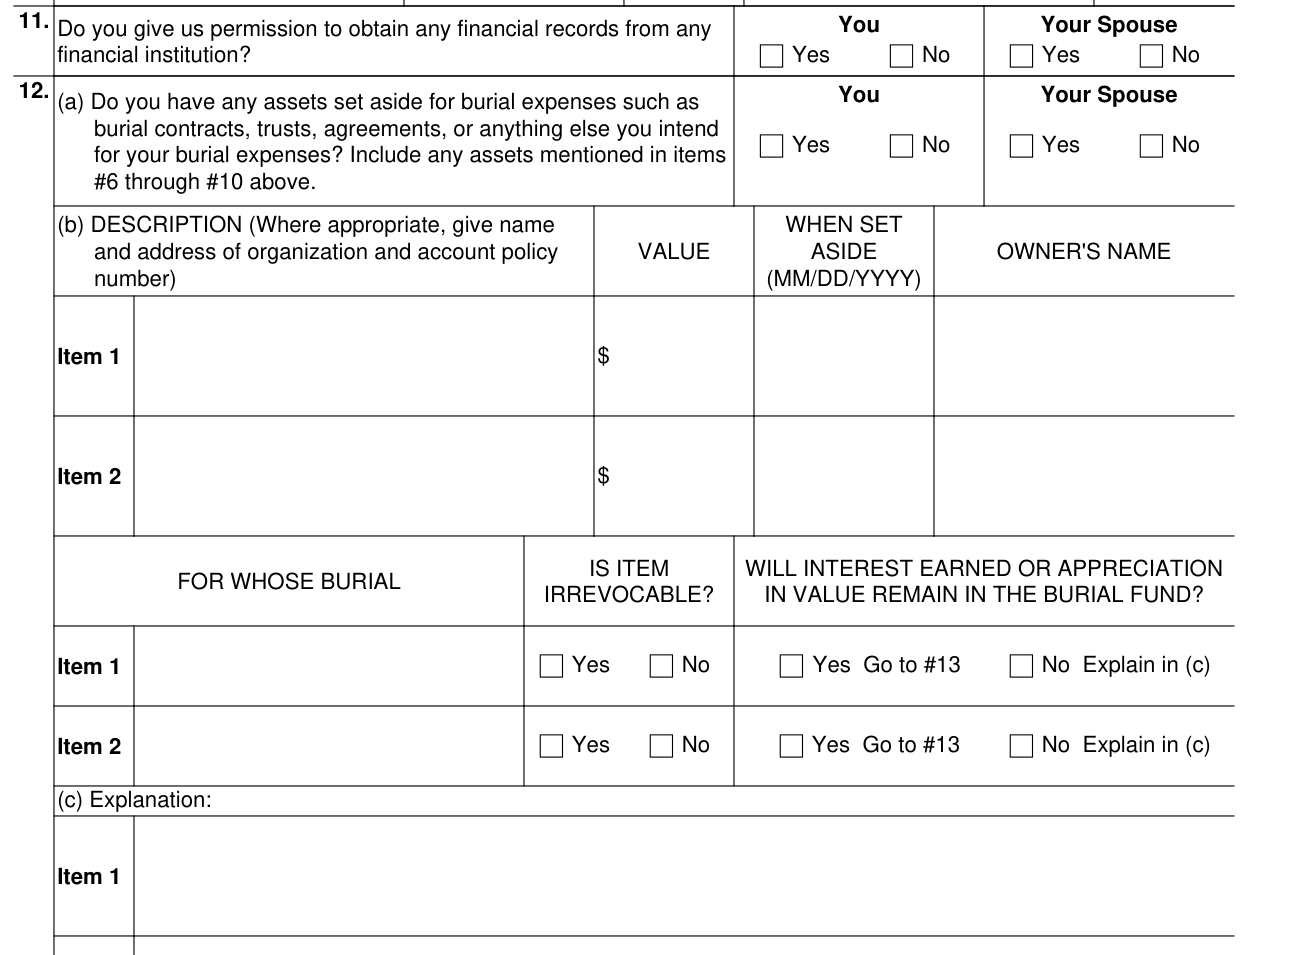
Check the box: Do you have any assets set aside for burial expenses such as burial contracts, trusts, agreements, or anything else you intend for your burial expenses? Include any assets mentioned in items #6 through #10.
Under (b), enter the DESCRIPTION (where appropriate, give name and address of organization and account policy number), WHEN SET ASIDE (MM/DD/YYYY), VALUE and OWNER'S NAME.
15. Dependents
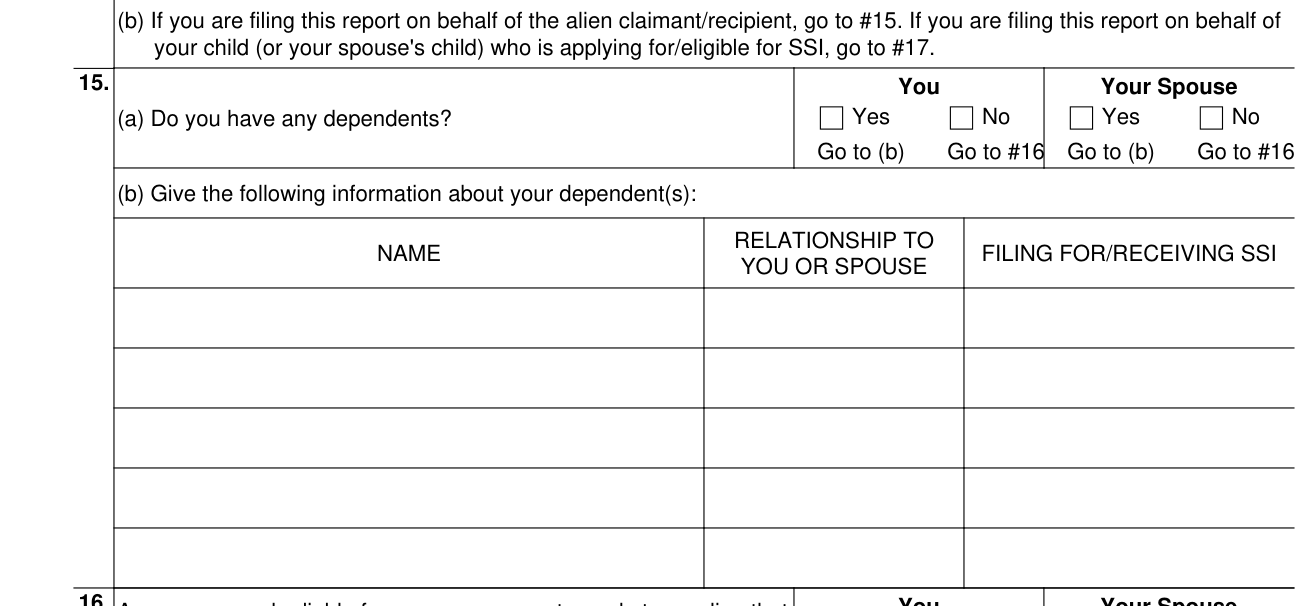
Check the box: Do you have any dependents?
Under (b), give the NAME, RELATIONSHIP TO YOU OR SPOUSE and FILING FOR/RECEIVING SSI of your dependent(s).
Remarks

Use this Remarks box for any explanations. Enter the item number before each explanation. If you need more space, use a signed form SSA-795.
18. Signatures

Sign under "I declare under penalty of perjury that I have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of my knowledge."
Sign under "I understand that anyone who knowingly gives a false statement about a material fact in this information, or causes someone else to do so, commits a crime and may be subject to a fine or imprisonment."
Under 18, write Your Signature (First name, middle initial, last name) in ink, then the DATE (MM/DD/YYYY) and the telephone number(s) at which you may be contacted during the day.
Representative payee, addresses and witnesses
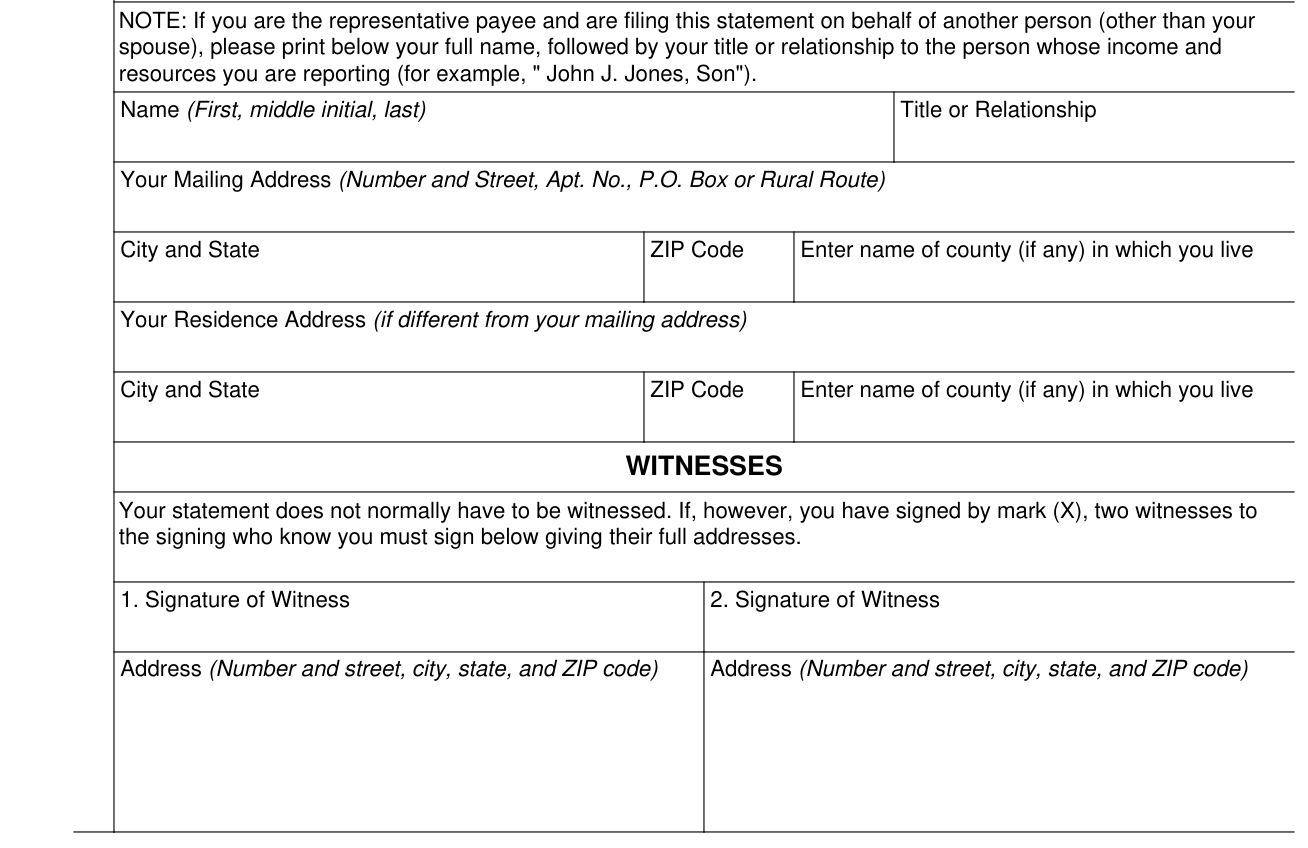
If you are the representative payee and are filing this statement on behalf of another person (other than your spouse), print your full name, followed by your title or relationship to the person whose income and resources you are reporting.
Enter Your Mailing Address (Number and Street, Apt. No., P.O. Box or Rural Route), City and State, ZIP Code and the name of county (if any) in which you live.
Enter Your Residence Address (if different from your mailing address), City and State, ZIP Code and the name of county (if any) in which you live.
Your statement does not normally have to be witnessed. If, however, you have signed by mark (X), two witnesses to the signing who know you must sign giving their full addresses.
If your situation is different
Report any change
Failure to report any change within 10 days after the end of the month in which the change occurs could result in a penalty deduction.
Sources
[1] Form SSA-8010-BK (11-2025), Statement of Income and Resources, Social Security Administration (the Official source link on this page).