

Form SSA-632-BK at a glance
What it is: Form SSA-632-BK is the Request for Waiver of Overpayment Recovery of the Social Security Administration.
Who signs: If the overpaid individual is a minor child, a parent or legal guardian must complete and sign the form on the child's behalf. If a court has assigned a legal guardian to an adult individual, the legal guardian must complete and sign the form. Adults who do not have a court appointed legal guardian must complete and sign the form, even if they have a representative payee.
Complete this form if any of the following applies: You think that you are not at fault for the overpayment and you cannot afford to pay the money back. You think that you are not at fault and you think the overpayment is unfair for some other reason. The answers decide if you have to pay the money back. If it is decided you do not have to pay the money back, it is called a waiver.
What to bring and attach to Form SSA-632-BK
Please answer all the questions and submit any supporting documents for you, your spouse, and your dependents. Your supporting documents should be dated no more than 3 months from the date that you are requesting a waiver.
A filled-in Form SSA-632-BK example: a retiree asks to waive an overpayment

How to fill out Form SSA-632-BK, box by box
Identifying questions

Enter the name, Social Security Number, and claim number (if any) of the overpaid person.
If you are filling out the waiver request for the overpaid person, provide your name and relationship to the person.
Waiver request

Check Yes or No: the total amount of the overpayment stated on your letter is $2,000 or less (checked November 8, 2026). If Yes, you do not need to complete the rest of this form. Please call 1-800-772-1213 or your local field office and your waiver request may be processed quickly over the phone. If No, continue completing the rest of the form.
Your reason for requesting a waiver

Check all that apply as your reason for requesting a waiver: The overpayment was not my fault. I cannot afford to pay the money back. The overpayment is unfair for other reasons. Please explain.
The notice date and the amount to waive

Enter the date of the notice for the overpayment that you are asking to waive (MM/DD/YYYY).
Check Yes or No: you are requesting that the entire overpayment be waived, including money that you have already paid back. If No, check Yes or No to say if you are requesting that only the remaining amount of money that you owe be waived.
Why the overpayment may have happened

Tell what you know about why the overpayment may have happened. If there was a reason you did not understand or were not able to report the change, please explain why.
Needs based assistance

Check Yes or No: you or any dependent household family member currently receive any of the following: Supplemental Security Income (SSI) payments, Temporary Assistance for Needy Families (TANF), Pension based on need from the Department of Veterans Affairs (VA), Supplemental Nutrition Assistance Program (SNAP), Medicare Part D Extra Help.
A dependent is a person who depends on you for support and whom you can claim on your tax return.
If Yes, check all that apply, then go to page 9, sign, date, and provide your address and phone number. Please provide proof of TANF, VA pension, or SNAP. If No, complete the rest of the form.
Cash and financial accounts
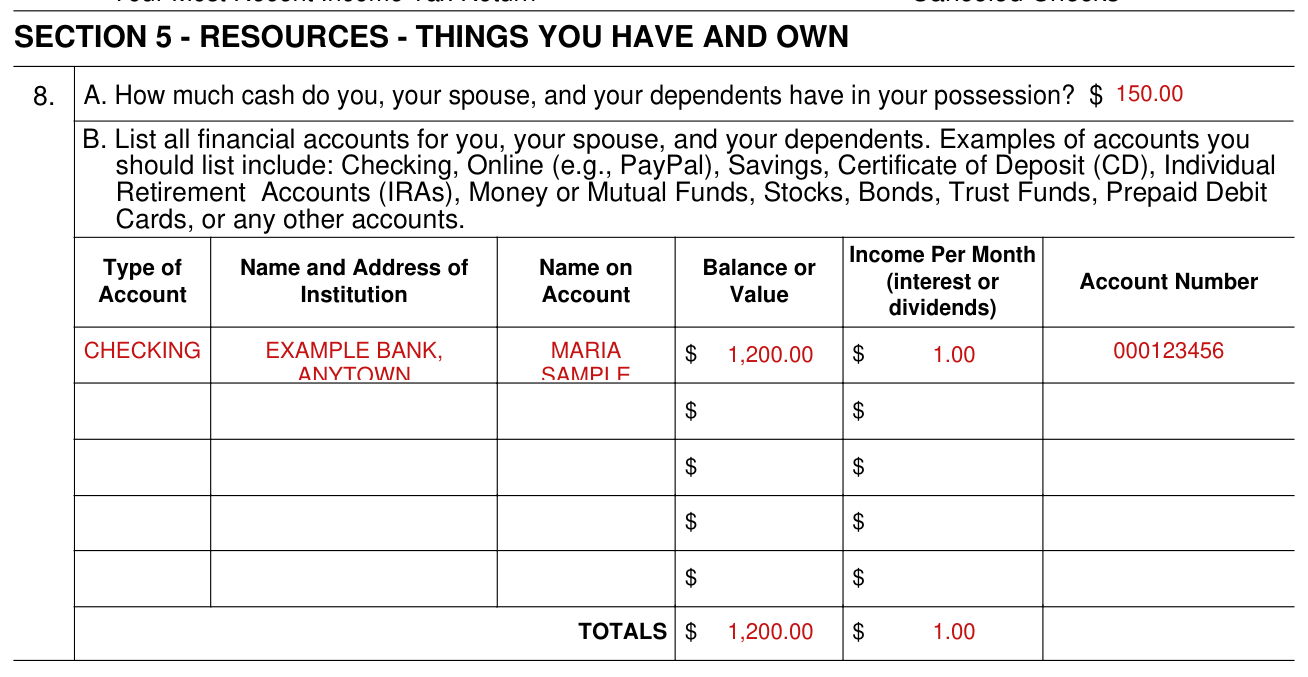
Enter how much cash you, your spouse, and your dependents have in your possession.
List all financial accounts for you, your spouse, and your dependents: Type of Account, Name and Address of Institution, Name on Account, Balance or Value, Income Per Month (interest or dividends), Account Number, and the TOTALS.
Monthly household income
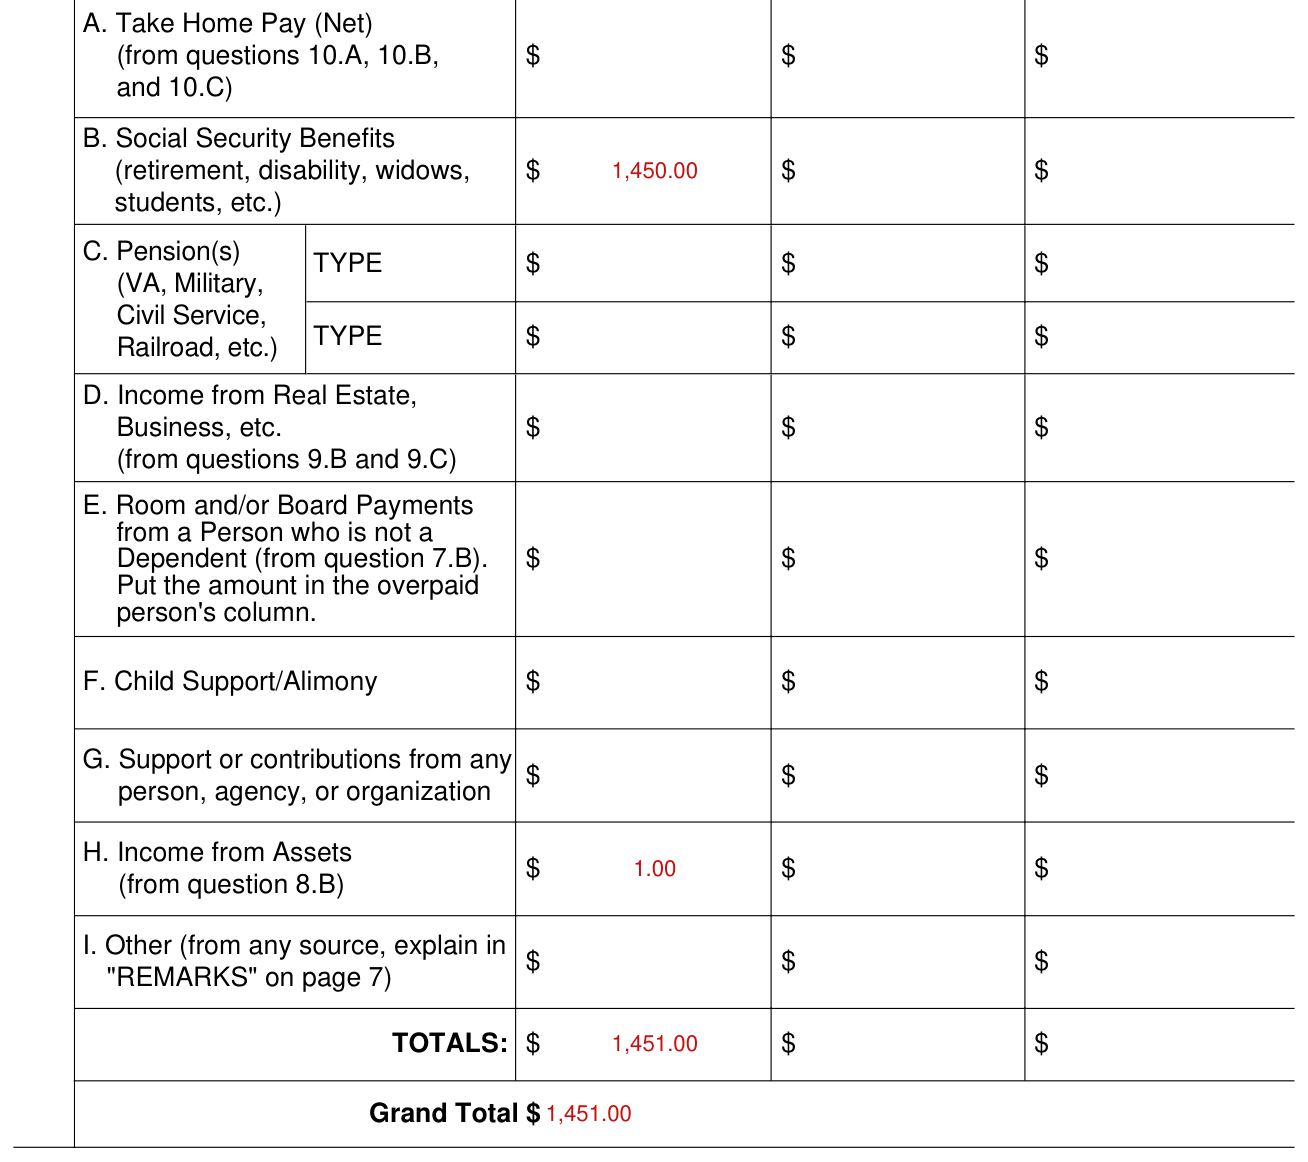
Show monthly amounts under Overpaid person's income, Spouse of Overpaid Person, or Dependent(s) of Overpaid Person (Total).
Enter Social Security Benefits (retirement, disability, widows, students, etc.), Income from Assets (from question 8.B), the TOTALS and the Grand Total.
Monthly household expenses
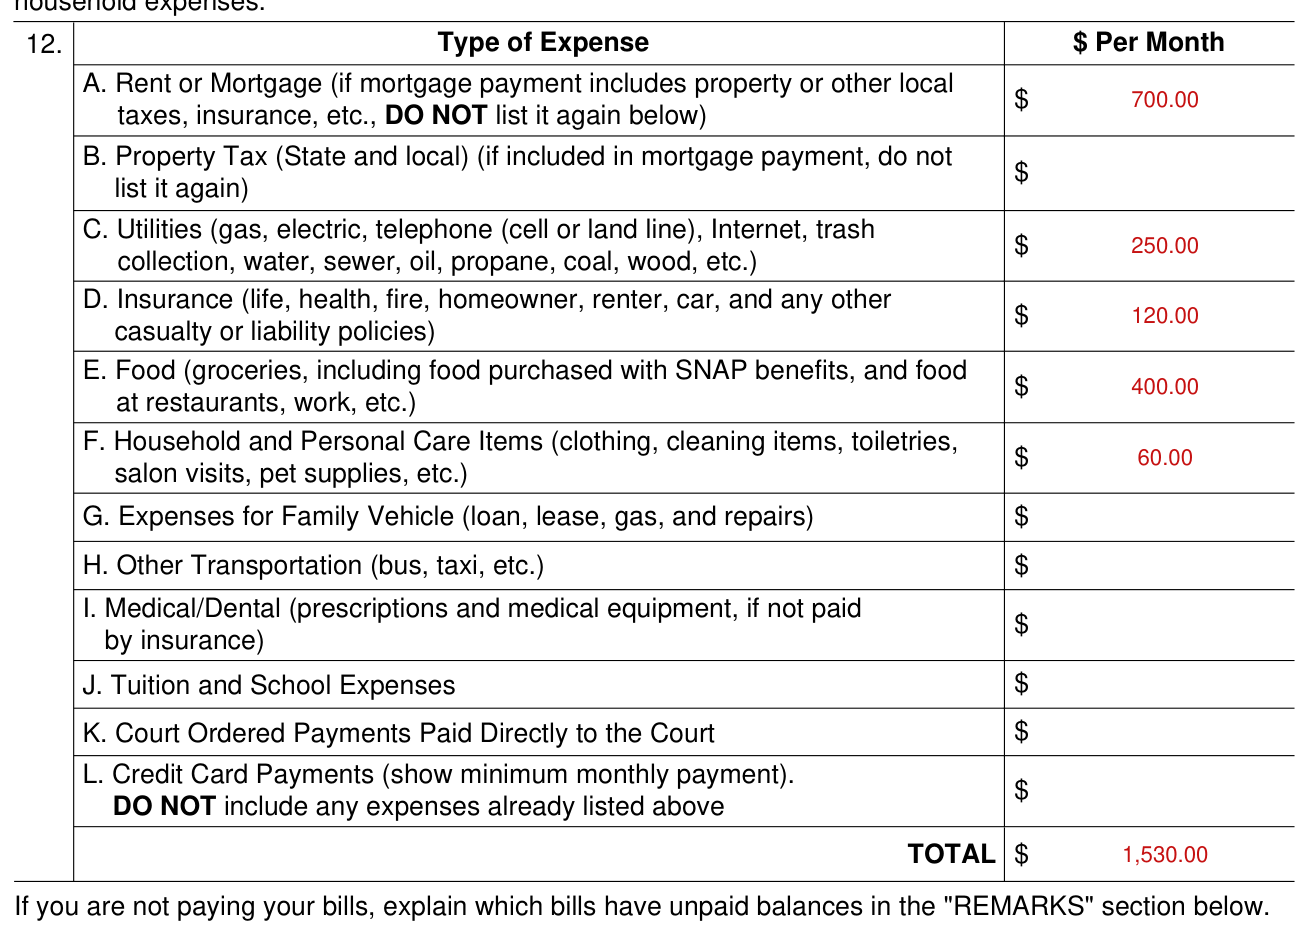
Do not list an expense that is withheld from your paycheck (such as medical insurance, child support, alimony, wage garnishments, etc.). You do not need to provide supporting documents for your household expenses.
Enter the $ Per Month for each Type of Expense: Rent or Mortgage (if mortgage payment includes property or other local taxes, insurance, etc., DO NOT list it again), Utilities, Insurance, Food, Household and Personal Care Items, and the TOTAL.
Authorization to obtain account records
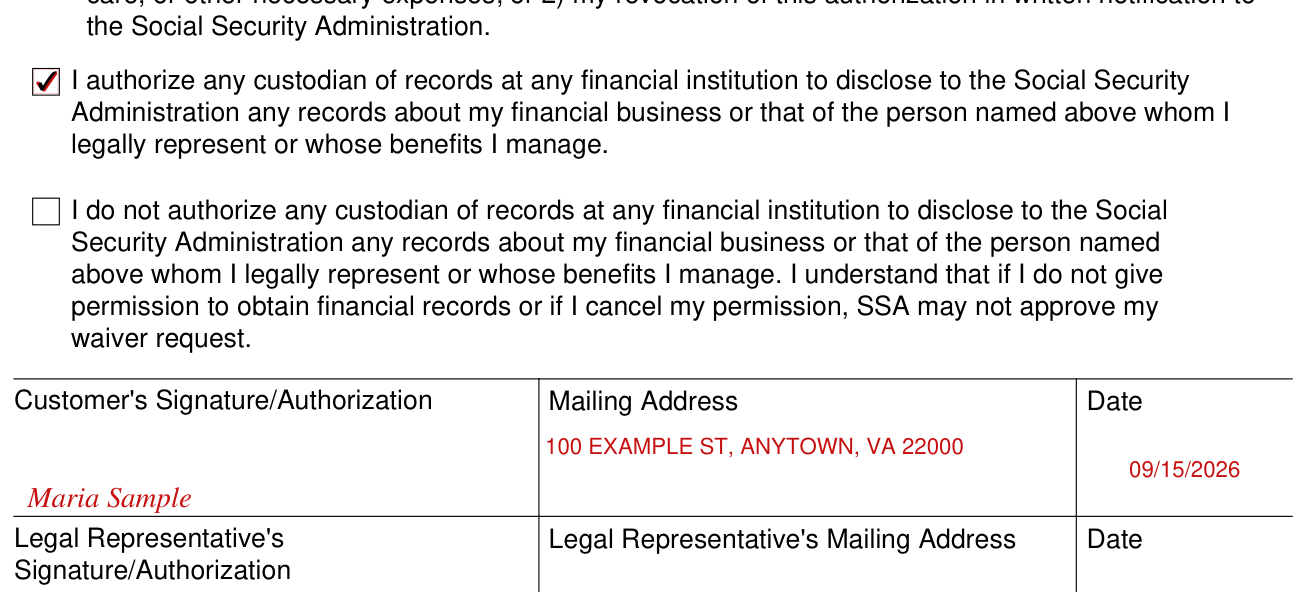
Please review the following, make selection, and sign: I authorize any custodian of records at any financial institution to disclose to the Social Security Administration any records about my financial business or that of the person named whom I legally represent or whose benefits I manage. I do not authorize any custodian of records at any financial institution to disclose to the Social Security Administration any records about my financial business or that of the person named whom I legally represent or whose benefits I manage. I understand that if I do not give permission to obtain financial records or if I cancel my permission, SSA may not approve my waiver request.
Sign the Customer's Signature/Authorization line and enter the Mailing Address and Date. A legal representative signs the Legal Representative's Signature/Authorization line.
Signature and witnesses
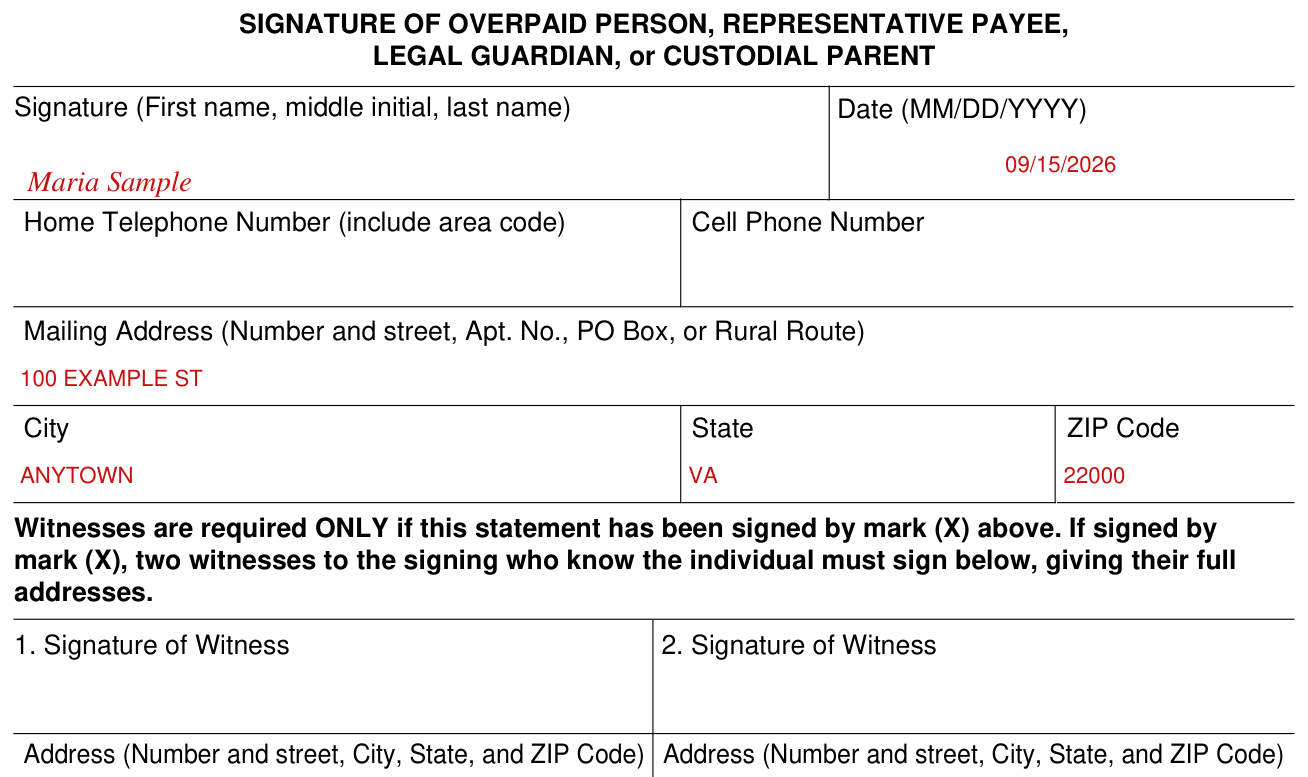
By signing you declare under penalty of perjury that you have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of your knowledge. Anyone who knowingly gives a false statement about a material fact in this information, or causes someone else to do so, commits a crime and may be subject to a fine or imprisonment.
The overpaid person, representative payee, legal guardian, or custodial parent signs: Signature (First name, middle initial, last name) and Date (MM/DD/YYYY).
Witnesses are required ONLY if this statement has been signed by mark (X). If signed by mark (X), two witnesses to the signing who know the individual must sign, giving their full addresses.
If your situation is different
When Not To Complete This Form
Do not complete this form if you think that you are not at fault and your overpayment is $2,000 or less (checked November 8, 2026). Instead, please request a waiver by calling 1-800-772-1213 or your local field office. Your request may be processed quickly over the phone. Do not complete it if you think a mistake was made when it was decided that you were overpaid, or if you disagree with the amount of your overpayment. Instead, please complete the SSA-561, Request for Reconsideration. Do not complete it if you are requesting a hearing before an Administrative Law Judge. Instead, please complete the HA-501-U5, Request for Hearing by Administrative Law Judge. Do not complete it if you only want to change the amount of money you must pay back each month. Instead, please complete the SSA-634, Request for Change in Overpayment Recovery Rate. Do not complete it if you have been convicted of fraud relating to this overpayment.
Common questions about Form SSA-632-BK
Where do I file it?
Send or bring the completed form to your local Social Security office.
Sources
[1] Form SSA-632-BK (06-2025), Request for Waiver of Overpayment Recovery, Social Security Administration (the Official source link on this page).