


Written Authorization for a Stepparent to Access the Medical Record of a Minor Child at a glance
What it is: Written Authorization for a Stepparent to Access the Medical Record of a Minor Child is a request for written permission, required by state and federal law.
Who signs: Sign at Natural Parent/Guardian Signature and Stepparent Signature, with a Date for each.
Where and when to file: Mail to: Patient Services Contact Center (877) 607-6484, ATTN: My Health Online Proxy, P.O. Box 255386 Sacramento, CA 95865-5386.
A filled-in Written Authorization for a Stepparent to Access the Medical Record of a Minor Child example: a parent authorizes a stepparent
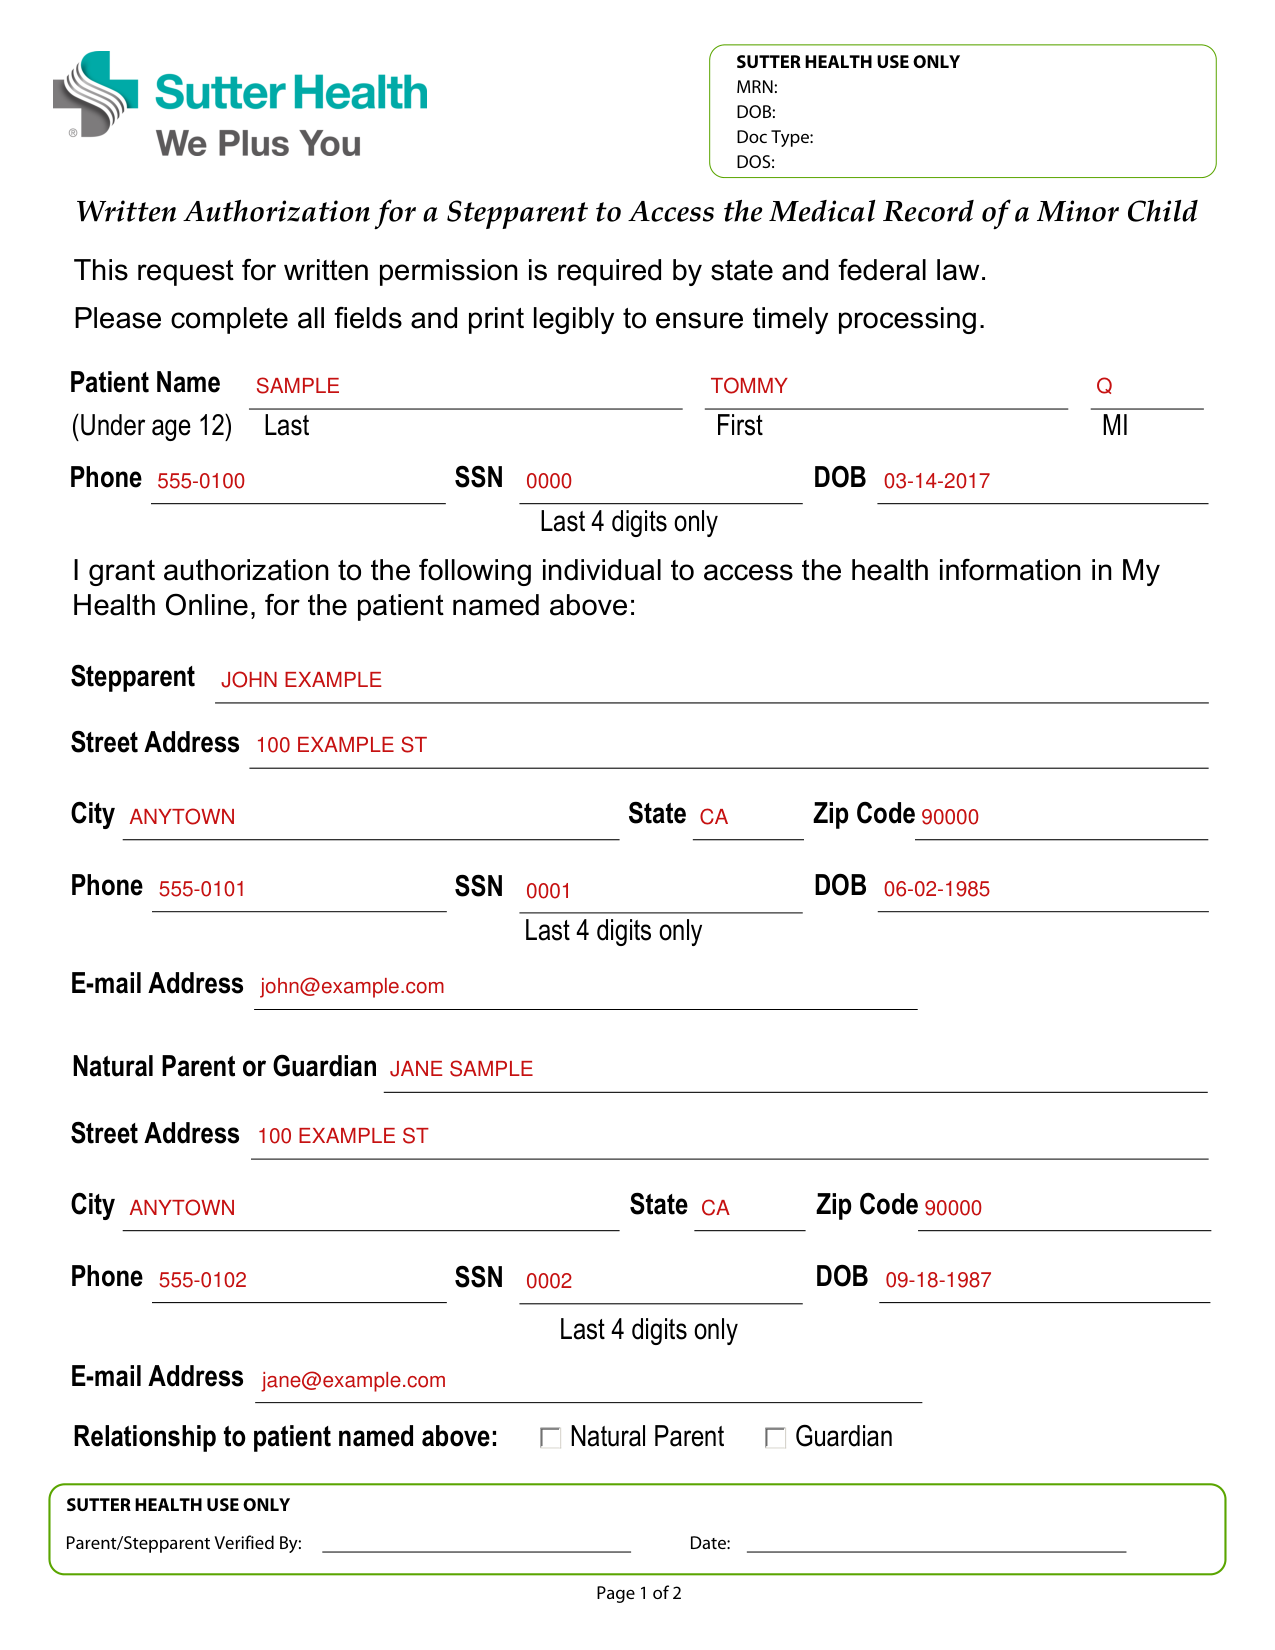
How to fill out Written Authorization for a Stepparent to Access the Medical Record of a Minor Child, box by box
Patient Name

The patient must be under age 12: enter the patient's Last name and First name, then MI, then Phone, SSN (Last 4 digits only) and DOB.
Stepparent
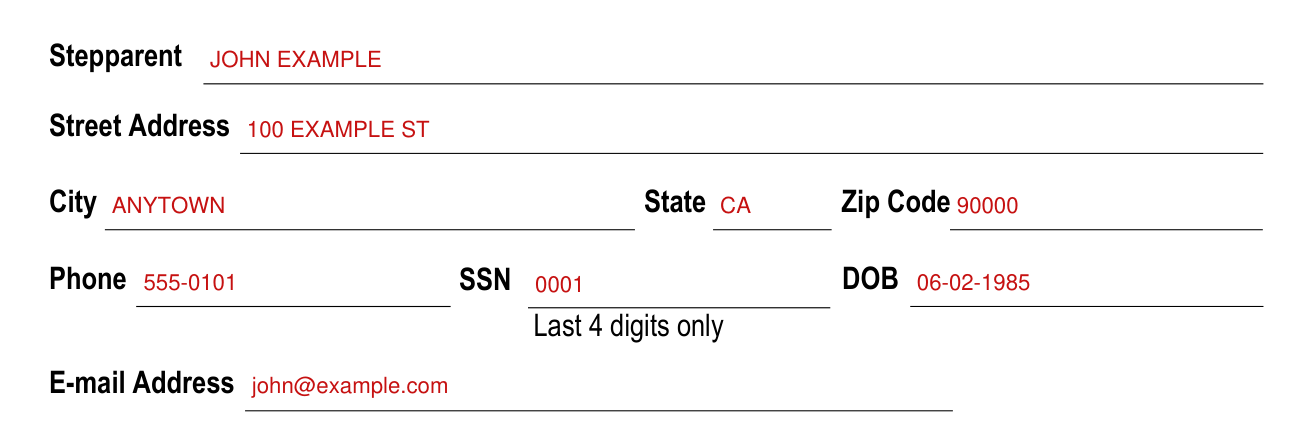
I grant authorization to the following individual to access the health information in My Health Online, for the patient named in Patient Name.
For the Stepparent, enter the Street Address, City and State Zip Code.
For the Stepparent, enter Phone, SSN (Last 4 digits only), DOB and E-mail Address.
Natural Parent or Guardian
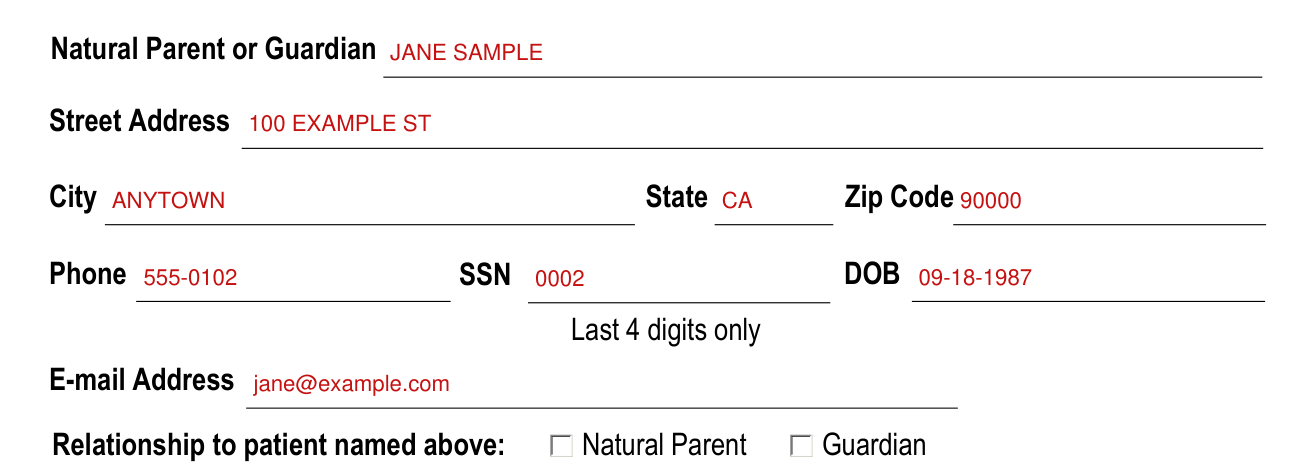
Under Natural Parent or Guardian, enter the Street Address, City and State Zip Code.
For the Natural Parent or Guardian, enter Phone, SSN (Last 4 digits only), DOB and E-mail Address.
Mark Natural Parent or Guardian as the relationship to the patient named in Patient Name.
More rules for Written Authorization for a Stepparent to Access the Medical Record of a Minor Child
I HAVE A RIGHT TO A COPY OF THIS AUTHORIZATION.
If written, the revocation must be signed on the patient's behalf and sent to the Patient Services Contact Center. The revocation is effective upon receipt, but will have no impact on uses or disclosures made while the authorization was valid.
Please complete all fields and print legibly to ensure timely processing.
The recipient may use the health information only for the following purpose: To access medical information and services on behalf of a minor child via My Health Online.
This authorization does NOT allow the proxy representative to access the patient's health information other than via My Health Online.
I may refuse to sign this authorization and my refusal will not affect my ability to obtain treatment.
This authorization shall remain valid until terminated electronically or in writing by My Health Online, the proxy representative or once the child reaches 12 years of age, whichever comes first.
Restriction: California law prohibits the proxy representative from making further disclosure of your health information unless the recipient obtains another authorization from you or unless the disclosure is required or permitted by law. This protection does not extend to recipients outside the state of California.
Common questions about Written Authorization for a Stepparent to Access the Medical Record of a Minor Child
Who signs it?
Sign at Natural Parent/Guardian Signature and Stepparent Signature, with a Date for each.
Where do I file it?
Mail to: Patient Services Contact Center (877) 607-6484, ATTN: My Health Online Proxy, P.O. Box 255386 Sacramento, CA 95865-5386.
Sources
[1] Written Authorization for a Stepparent to Access the Medical Record of a Minor Child (served file; no issuer file found) (the Official source link on this page).