


Authorization for Release of Health Information (Rev. 10/15) at a glance
What it is: This form is the Authorization for Release of Health Information.
Who signs: Print Name and Signature (Patient, Parent, Guardian).
A filled-in Authorization for Release of Health Information (Rev. 10/15) example: a patient sends records to a doctor

How to fill out Authorization for Release of Health Information (Rev. 10/15), box by box
Patient and ID verification

Fill in DATE, PATIENT NAME, BIRTHDATE, ID VERIFICATION (TYPE) and ID VERIFIED BY.
Who releases to whom
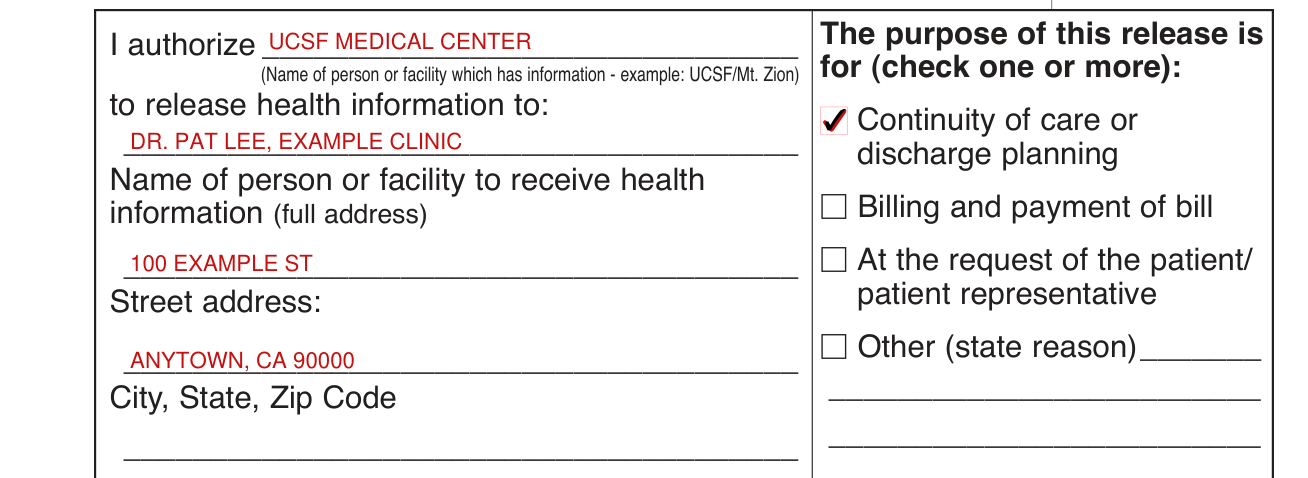
After "I authorize", write the Name of person or facility which has information (example: UCSF/Mt. Zion) to release health information to.
Write the name of the person or facility to receive health information, with the full address: Street address and City, State, Zip Code.
The purpose of this release

The purpose of this release is for (check one or more): Continuity of care or discharge planning; Billing and payment of bill; At the request of the patient/ patient representative; Other (state reason).
Health information to release

Please specify the health information you authorize to be released: Type(s) of health information and Date(s) of treatment.
Information released only if you mark it

This information will not be released unless you specifically authorize it by marking the relevant box(es): drug and alcohol abuse, diagnosis or treatment (42 C.F.R. §§2.34 and 2.35); mental health diagnosis or treatment (Welfare and Institutions Code §§5328, et seq.); HIV/AIDS test results (Health and Safety Code §120980(g)); genetic testing information (Health and Safety Code §124980(j)).
Expiration of authorization

Unless otherwise revoked, this Authorization expires on the applicable date or event you insert. If no date is indicated, the Authorization will expire 12 months after the date of my signing this form.
Signing and the requested format

Under SIGN, enter the Date, the Time and the Relationship to Patient (Parent, Guardian, Conservator, Patient Representative). Requested format: Paper or CD.
More rules for Authorization for Release of Health Information (Rev. 10/15)
Treatment, payment, enrollment or eligibility for benefits may not be conditioned on signing this Authorization except in the following cases: (1) to conduct research-related treatment, (2) to obtain information in connection with eligibility or enrollment in a health plan, (3) to determine an entity's obligation to pay a claim, or (4) to create health information to provide to a third party.
This Authorization may be revoked at any time. The revocation must be in writing, signed by you or your patient representative, and delivered to Health Information Management Services. The revocation will take effect when UCSF receives it, except to the extent UCSF or others have already relied on it.
You are entitled to receive a copy of this Authorization.
UCSF and many other organizations and individuals such as physicians, hospitals and health plans are required by law to keep your health information confidential. If you have authorized the disclosure of your health information to someone who is not legally required to keep it confidential, it may no longer be protected by state or federal confidentiality laws.
Common questions about Authorization for Release of Health Information (Rev. 10/15)
Where do I file it?
Return Completed Authorization To: Health Information Management Services UCSF Medical Center 400 Parnassus Ave., Room A88 San Francisco, CA 94143-0308. This Authorization to release health information is voluntary.
Sources
[1] UCSF Authorization for Release of Health Information, 756-020Z (Rev. 10/15) (the served file; no issuer file found) (the Official source link on this page).