
Ultimate Health Insurance Claim Form at a glance
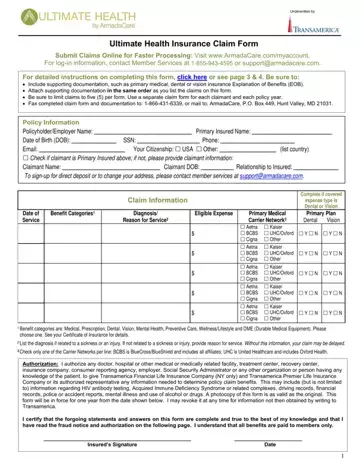
What it is: Ultimate Health Insurance Claim Form: file online instead of using the form for faster processing (page 3).
Where and when to file: Fax completed claim form and documentation to: 1-866-431-6339, or mail to: ArmadaCare, P.O. Box 449, Hunt Valley, MD 21031. Submit Claims Online for Faster Processing: Visit www.ArmadaCare.com/myaccount. For log-in information, contact Member Services at 1-855-943-4595 or support@armadacare.com.
What to bring and attach to Ultimate Health Insurance Claim Form
Include supporting documentation, such as primary medical, dental or vision insurance Explanation of Benefits (EOB).
Attach supporting documentation in the same order as you list the claims on this form.
Be sure to limit claims to five (5) per form. Use a separate claim form for each claimant and each policy year.
Use one form per member and policy year. The primary member and spouse/dependent(s) cannot list claims on the same form. Policy year isn't necessarily the same as calendar year. If you are not sure what your policy year is for Ultimate Health, ask your HR administrator or contact Member Services.
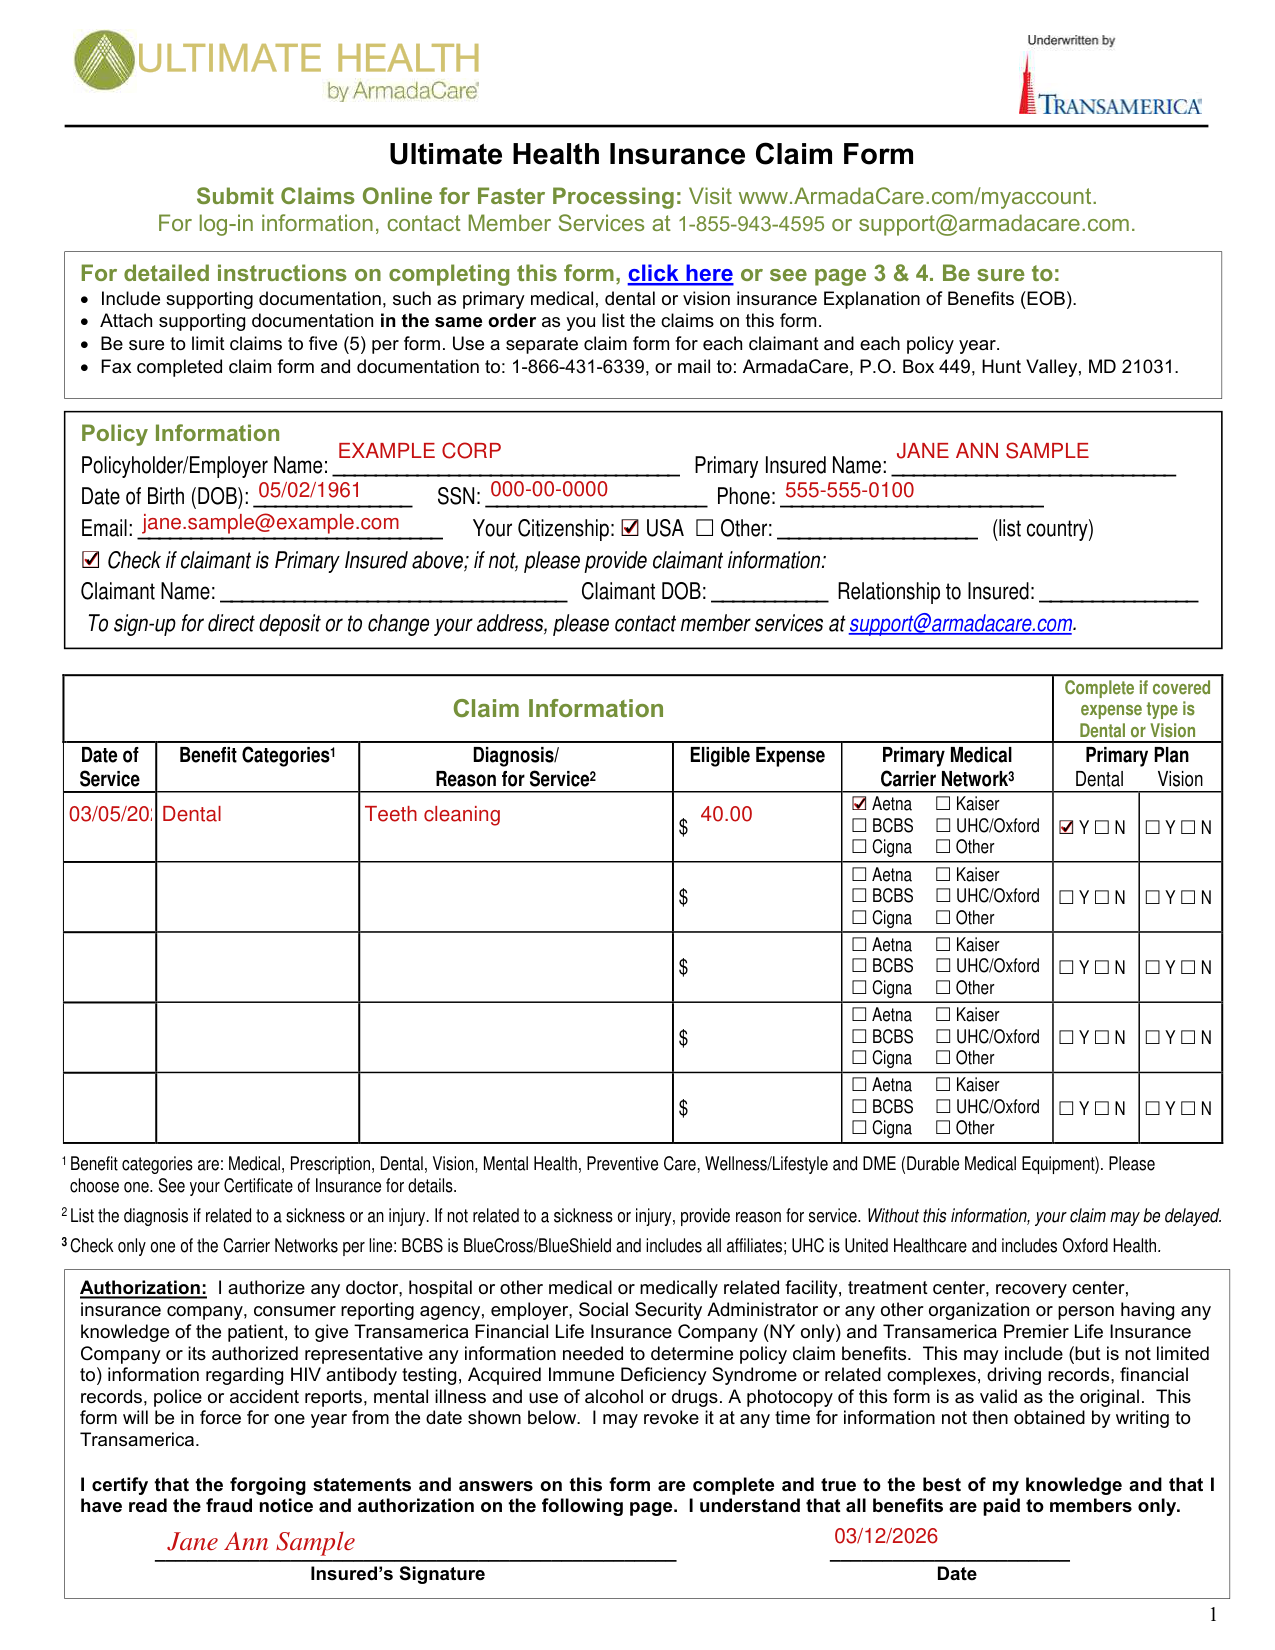
A filled-in Ultimate Health Insurance Claim Form example: a dental claim by the primary insured
How to fill out Ultimate Health Insurance Claim Form, box by box
Policy Information
Policyholder/Employer Name, Primary Insured Name, Date of Birth (DOB), SSN, Phone, Email.
Your Citizenship
Your Citizenship: USA or Other: (list country).
Claimant information
Check if claimant is the Primary Insured; if not, please provide claimant information: Claimant Name, Claimant DOB, Relationship to Insured.
To sign-up for direct deposit or to change your address, please contact member services at support@armadacare.com.
Claim Information
Claim Information: Date of Service, Benefit Categories, Diagnosis/ Reason for Service, Eligible Expense.
Write the claim amount (amount that you owe) under Eligible Expense. This is the amount you are responsible for-not the total charged amount. Do not write “See Attached.”
Benefit categories are: Medical, Prescription, Dental, Vision, Mental Health, Preventive Care, Wellness/Lifestyle and DME (Durable Medical Equipment). Please choose one. See your Certificate of Insurance for details.
Some examples of items that are generally eligible under Wellness/Lifestyle may include chiropractic treatment, acupuncture and prescribed massage therapy. Preventive Care typically may include Executive Physical tests, routine exams and lab screenings. Examples of durable medical equipment (DME) items generally eligible for reimbursement are wigs, hearing aids and orthotics. Your primary resource for what is covered under each category is your Certificate of Insurance provided to you by your employer.
List the diagnosis if related to a sickness or an injury. If not related to a sickness or injury, provide reason for service. Without this information, your claim may be delayed.
Primary Medical Carrier Network
Primary Medical Carrier Network: Aetna, Kaiser, BCBS, UHC/Oxford, Cigna, Other.
Check only one of the Carrier Networks per line: BCBS is Bluecross/Blueshield and includes all affiliates; UHC is United Healthcare and includes Oxford Health.
Complete if covered expense type is Dental or Vision
Complete if covered expense type is Dental or Vision: Primary Plan Dental, Vision.
Do you have primary dental coverage, and is the expense a dental expense? Check “Y” under Dental, and attach a dental EOB. Do you have primary vision coverage and is the expense a vision expense? Check “Y” under Vision and attach a vision EOB. Otherwise, check “N” to indicate no primary dental or vision coverage.
Insured's Signature and Date
Be sure to sign with an actual signature, not your name in a “signature font”. Be sure to date the claim as well.
A photocopy of this form is as valid as the original. This form will be in force for one year from the date shown. I may revoke it at any time for information not then obtained by writing to Transamerica. “I certify that the forgoing statements and answers on this form are complete and true to the best of my knowledge and that I have read the fraud notice and authorization on the following page.” I understand that all benefits are paid to members only.
Claim Fraud Warning (page 2): Any person who knowingly presents a false or fraudulent claim for payment of a loss or benefit or knowingly presents false information in an application for insurance is guilty of a crime and may be subject to fines and confinement in prison.
Documentation
All Claims: Submit an Explanation of Benefits (EOB) from your primary insurance as documentation for most all claims. Include all EOB pages (with footnotes and YTD deductible summary) even if denied by your primary plan.
Detailed receipts must show date service provided, description of service and amount owed, provider name and patient name. Do not submit statements that are not itemized and say “Balance Forward,” “Previous Balance Due,” or “Paid on Account” or pre-treatment estimates.
Doctor Co-Pays: Submit detailed receipt (no EOB required).
Out-of-Network (OON) Provider: Submit balance bill invoice along with primary plan's EOB and indicate OON on claim form.
Prescriptions: Submit Rx receipt that includes patient name, drug name, filled date and charged amount. No cash or credit card receipts or cancelled checks accepted. Do not black out the name of the drug on the Rx receipt.
Over-the-Counter Medications and Massage Therapy: Prescription required; submit prescription and detailed receipt.
Vision: Submit EOB if you have primary vision insurance; if not, submit detailed receipt. Dental: Submit EOB if you have primary dental insurance; if not, submit detailed receipt.
Executive Physicals: If self-pay/not covered by primary insurance, submit contract and invoice. If accepted (even partially) by primary insurance, submit EOB.
Common questions about Ultimate Health Insurance Claim Form
Where do I file it?
Fax the completed claim form and documentation to 1-866-431-6339, or mail it to ArmadaCare, P.O. Box 449, Hunt Valley, MD 21031. Either mail or fax your paper claim form-not both.
Sources
[1] Ultimate Health Insurance Claim Form, ArmadaCare (the Official source link on this page).
