

VA Form 21-0304 at a glance
What it is: VA Form 21-0304 is the Application for Benefits for a Qualifying Veteran's Child Born with Disabilities.
Where to get it: VA forms are available at www.va.gov/vaforms.
Use this form to determine your eligibility for benefits for children with certain disabilities who are born of Vietnam veterans or certain Thailand or Korea service veterans.
Completion of VA Form 21-0304 is required.
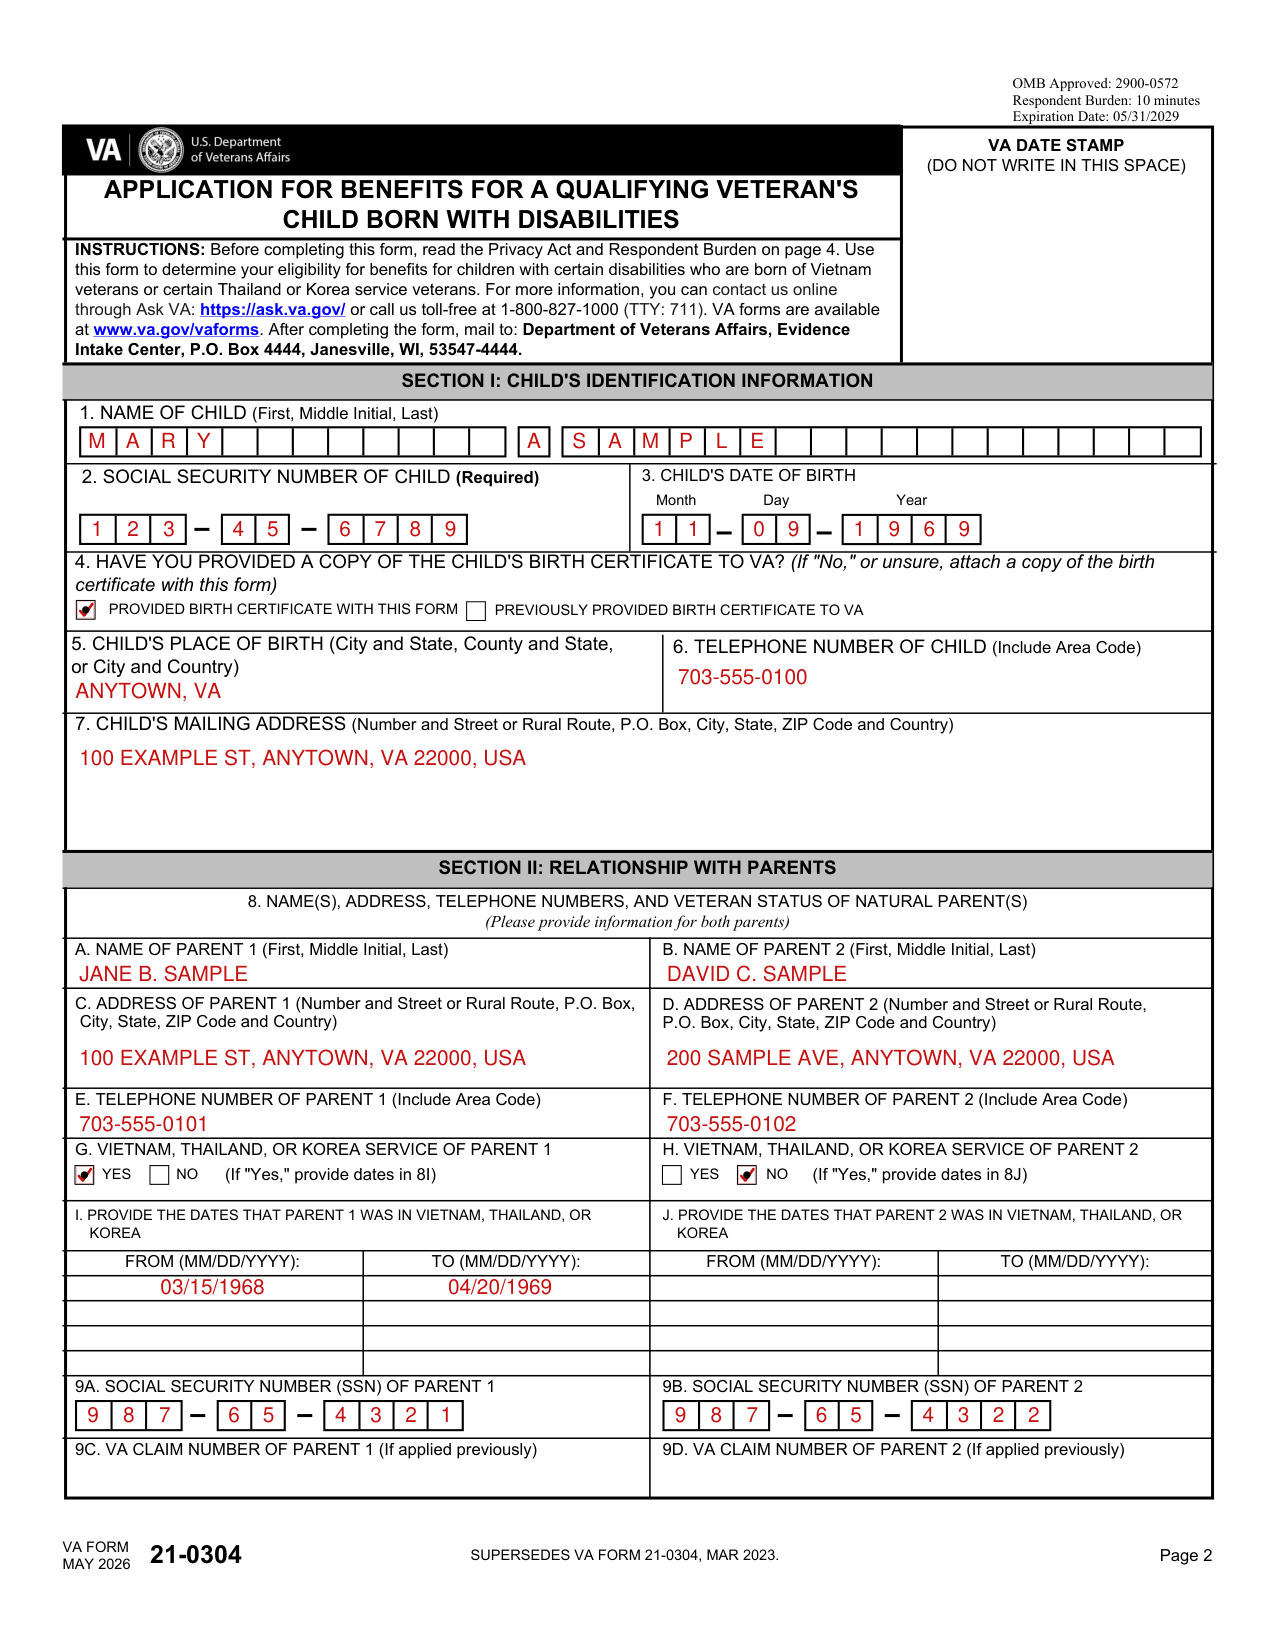
A filled-in VA Form 21-0304 example: an adult child applies for herself
How to fill out VA Form 21-0304, box by box
Section I: Child's identification information
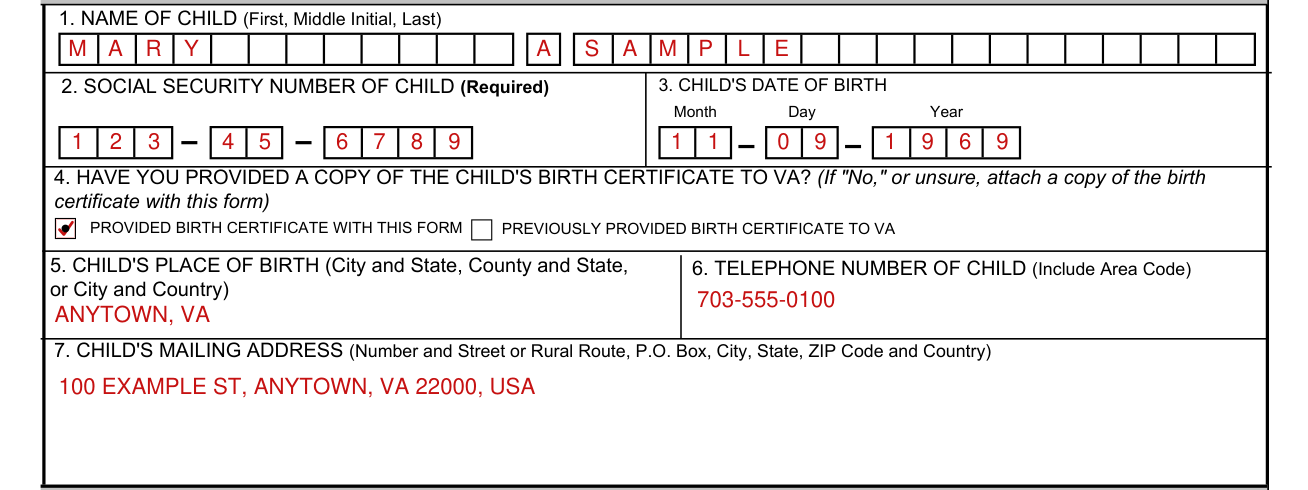
Under 1. NAME OF CHILD, enter the First, Middle Initial and Last name of the child.
Under 2. SOCIAL SECURITY NUMBER OF CHILD (Required), enter the number.
Under 3. CHILD'S DATE OF BIRTH, enter the Month, Day and Year.
Under 4. HAVE YOU PROVIDED A COPY OF THE CHILD'S BIRTH CERTIFICATE TO VA?, mark one of the two boxes. If "No," or unsure, attach a copy of the birth certificate with this form.
Under 5. CHILD'S PLACE OF BIRTH, enter City and State, County and State, or City and Country.
Under 6. TELEPHONE NUMBER OF CHILD, enter the number (Include Area Code).
Under 7. CHILD'S MAILING ADDRESS, enter Number and Street or Rural Route, P.O. Box, City, State, ZIP Code and Country.
Section II: Relationship with parents
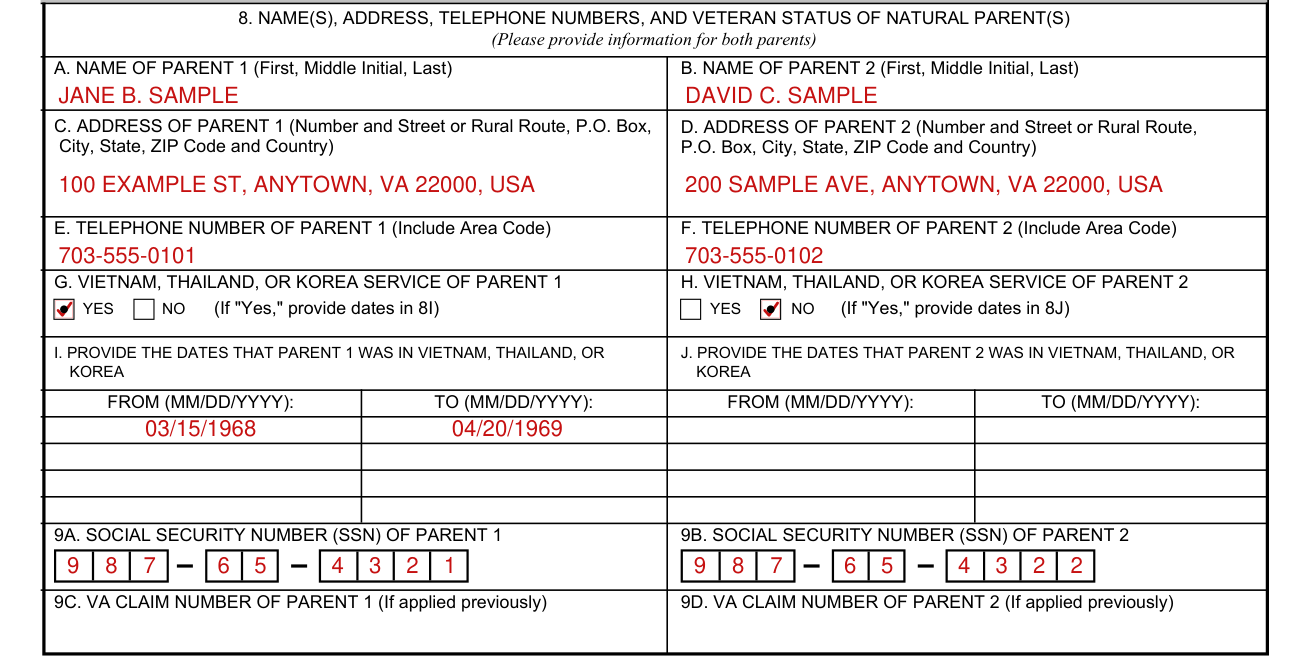
Under 8. Name(s), address, telephone numbers, and veteran status of natural parent(s), provide information for both parents.
Under A. NAME OF PARENT 1 and B. NAME OF PARENT 2, enter First, Middle Initial, Last.
Under C. ADDRESS OF PARENT 1 and D. ADDRESS OF PARENT 2, enter Number and Street or Rural Route, P.O. Box, City, State, ZIP Code and Country.
Under E. TELEPHONE NUMBER OF PARENT 1 and F. TELEPHONE NUMBER OF PARENT 2, enter the number (Include Area Code).
Under G. VIETNAM, THAILAND, OR KOREA SERVICE OF PARENT 1, mark YES or NO. If "Yes," provide dates in 8I.
Under H. VIETNAM, THAILAND, OR KOREA SERVICE OF PARENT 2, mark YES or NO. If "Yes," provide dates in 8J.
Under I. PROVIDE THE DATES THAT PARENT 1 WAS IN VIETNAM, THAILAND, OR KOREA, enter FROM (MM/DD/YYYY) and TO (MM/DD/YYYY).
Under J. PROVIDE THE DATES THAT PARENT 2 WAS IN VIETNAM, THAILAND, OR KOREA, enter FROM (MM/DD/YYYY) and TO (MM/DD/YYYY).
Under 9A. SOCIAL SECURITY NUMBER (SSN) OF PARENT 1 and 9B. SOCIAL SECURITY NUMBER (SSN) OF PARENT 2, enter the number.
Under 9C. VA CLAIM NUMBER OF PARENT 1 and 9D. VA CLAIM NUMBER OF PARENT 2, enter the number (If applied previously).
Item 10: Custodian/guardian other than natural parent

Under 10. IF CHILD IS UNDER AGE 18 & CUSTODIAN/GUARDIAN IS OTHER THAN NATURAL PARENT, complete Items 10A, 10B, 10C, & 10D.
Under A. NAME OF CUSTODIAN/GUARDIAN OF CHILD, enter the name. Under B. RELATIONSHIP TO CHILD, mark ADOPTIVE PARENT, GUARDIAN or OTHER (Specify). Under C. ADDRESS OF CUSTODIAN/GUARDIAN OF CHILD, enter the address.
Under D. HAVE YOU PROVIDED A COPY OF THE DECREE OF ADOPTION OR ADOPTIVE PLACEMENT AGREEMENT TO VA?, mark one of the two boxes. If "No," or unsure, please attach a copy of the decree of adoption or adoptive placement agreement with this form.
Item 11: Child age 18 or older
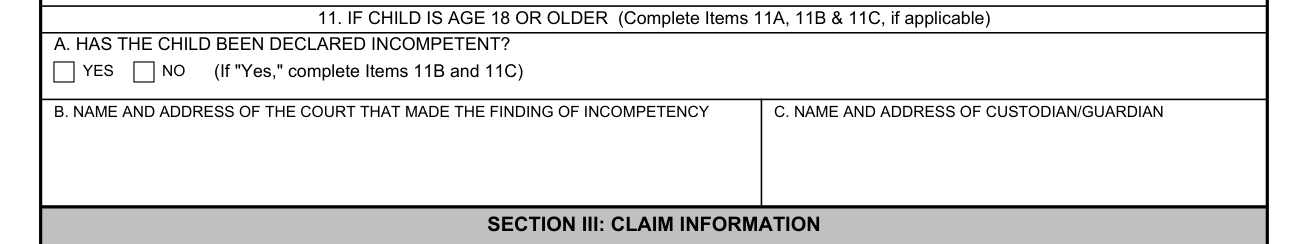
Under 11. IF CHILD IS AGE 18 OR OLDER, complete Items 11A, 11B & 11C, if applicable.
Under A. HAS THE CHILD BEEN DECLARED INCOMPETENT?, mark YES or NO. If "Yes," complete Items 11B and 11C.
Under B. Name and address of the court that made the finding of incompetency and C. Name and address of custodian/guardian, enter each name and address.
Section III: Claim information
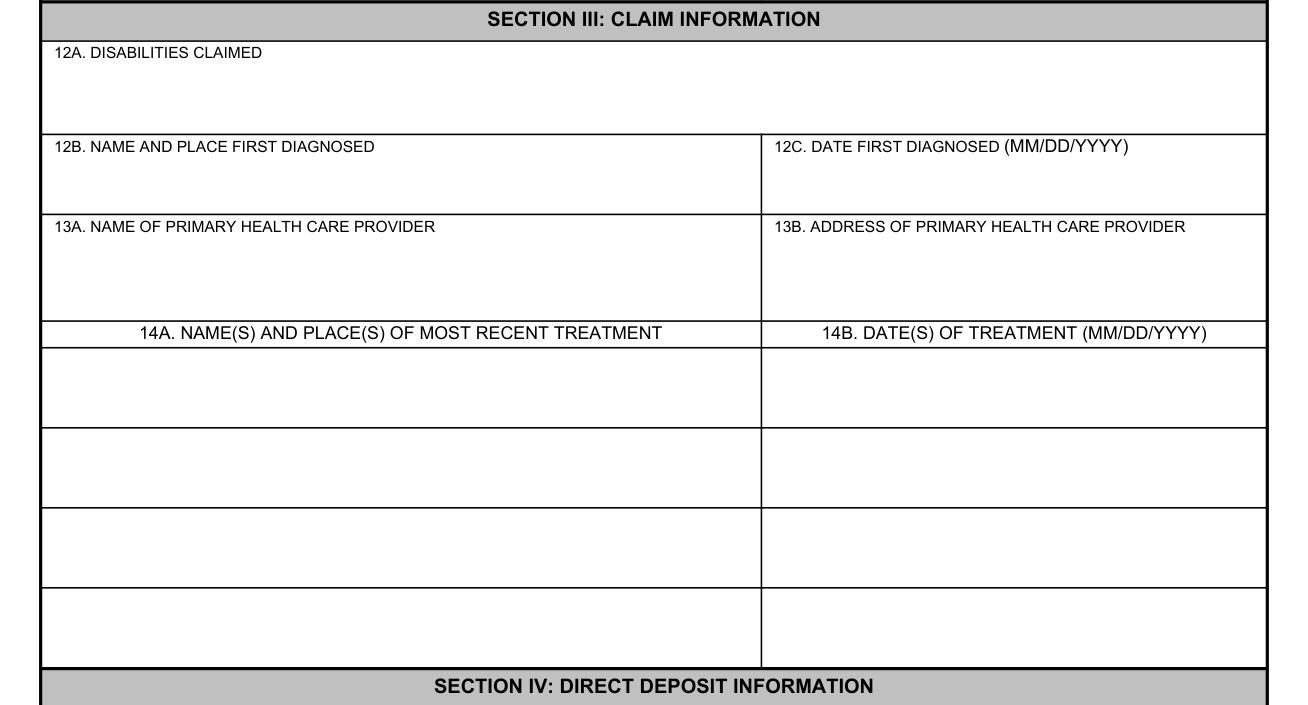
Under 12A. DISABILITIES CLAIMED, enter the disabilities.
Under 12B. NAME AND PLACE FIRST DIAGNOSED and 12C. DATE FIRST DIAGNOSED (MM/DD/YYYY), enter the name, place and date.
Under 13A. NAME OF PRIMARY HEALTH CARE PROVIDER and 13B. ADDRESS OF PRIMARY HEALTH CARE PROVIDER, enter the name and address.
Under 14A. NAME(S) AND PLACE(S) OF MOST RECENT TREATMENT and 14B. DATE(S) OF TREATMENT (MM/DD/YYYY), enter the names, places and dates.
Section IV: Direct deposit information

The Department of the Treasury requires all Federal benefit payments to be made by electronic funds transfer (EFT), also called direct deposit.
Under 15. BY CHECKING THE BOX I CERTIFY THAT I DO NOT HAVE AN ACCOUNT WITH A FINANCIAL INSTITUTION OR CERTIFIED PAYMENT AGENT, check the box. If you check this box you may skip to Section V.
Under 16A. ACCOUNT NUMBER, check only one box, CHECKING or SAVINGS, and provide the account number under Account No.
Under 16B. NAME OF FINANCIAL INSTITUTION, provide the name of the bank where you want your direct deposit.
Under 16C. ROUTING OR TRANSIT NUMBER, enter the first nine numbers located at the bottom left of your check.
Section V: Claim certifications and signatures
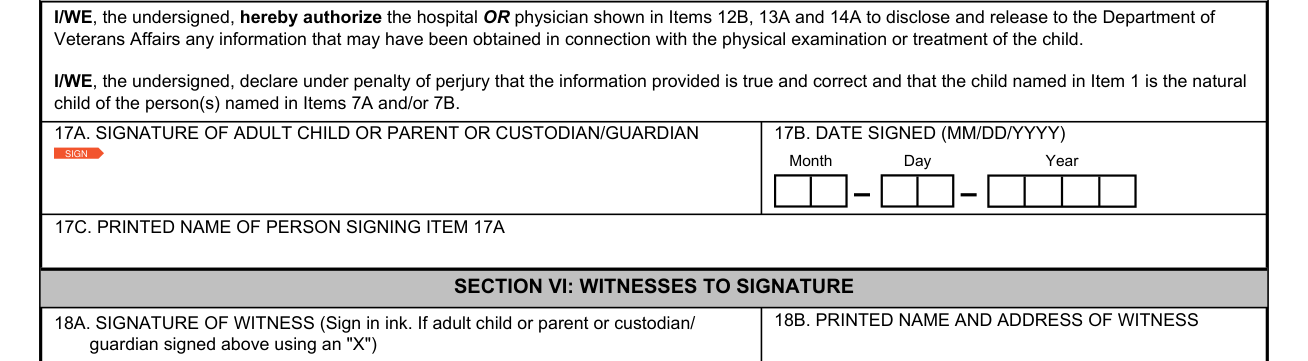
The undersigned hereby authorize the hospital OR physician shown in Items 12B, 13A and 14A to disclose and release to the Department of Veterans Affairs any information that may have been obtained in connection with the physical examination or treatment of the child.
The undersigned declare under penalty of perjury that the information provided is true and correct and that the child named in Item 1 is the natural child of the person(s) named in Items 7A and/or 7B.
Under 17A. SIGNATURE OF ADULT CHILD OR PARENT OR CUSTODIAN/GUARDIAN, the adult child or parent or custodian/guardian signs.
Under 17B. DATE SIGNED (MM/DD/YYYY), enter the date. Under 17C. PRINTED NAME OF PERSON SIGNING ITEM 17A, enter the printed name.
Section VI: Witnesses to signature
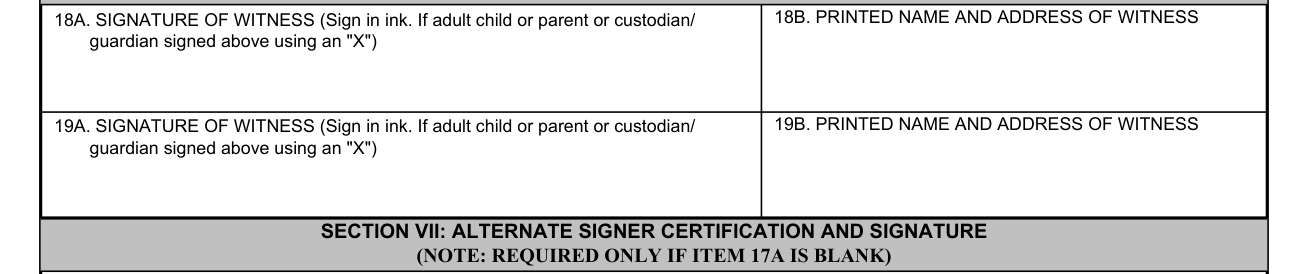
Under 18A. and 19A. SIGNATURE OF WITNESS, sign in ink if the adult child or parent or custodian/guardian signed using an "X".
Under 18B. and 19B. PRINTED NAME AND ADDRESS OF WITNESS, enter the printed name and address.
Section VII: Alternate signer certification and signature
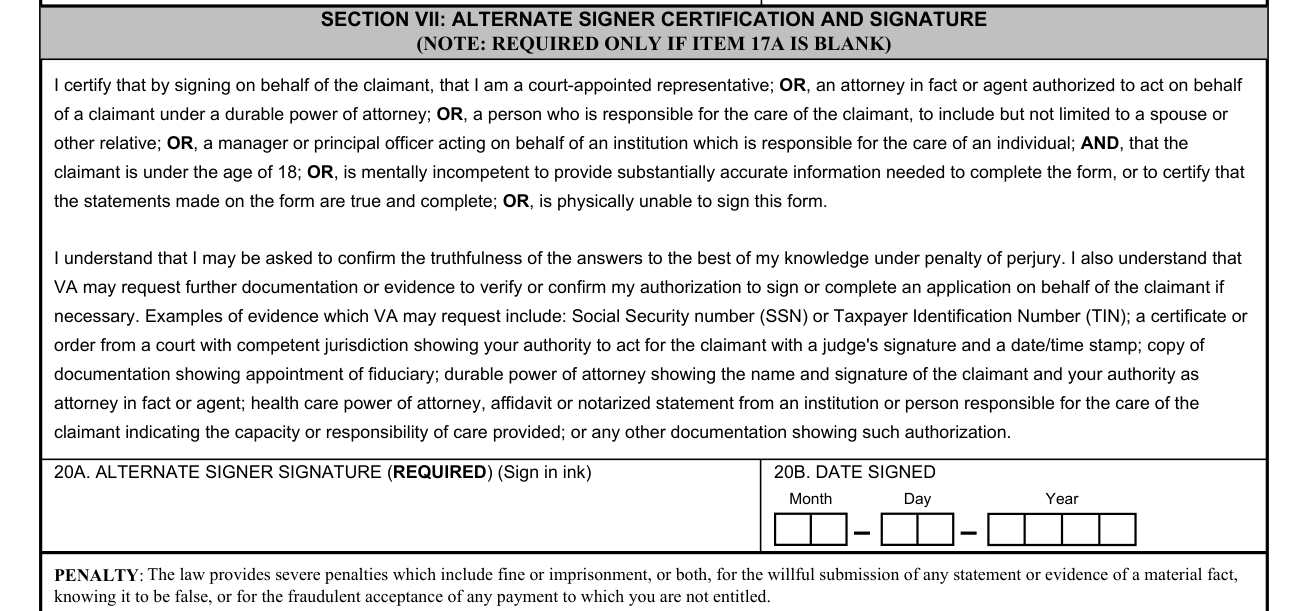
SECTION VII: ALTERNATE SIGNER CERTIFICATION AND SIGNATURE is REQUIRED ONLY IF ITEM 17A IS BLANK.
VA may request further documentation or evidence to verify or confirm authorization to sign or complete an application on behalf of the claimant if necessary. Examples include a health care power of attorney, affidavit or notarized statement from an institution or person responsible for the care of the claimant indicating the capacity or responsibility of care provided.
Under 20A. ALTERNATE SIGNER SIGNATURE (REQUIRED) (Sign in ink), sign in ink. Under 20B. DATE SIGNED, enter the date.
More rules for VA Form 21-0304
Children of Women Vietnam Veterans Born with Certain Birth Defects (38 U.S.C. 1815): to be eligible, the child must be the biological child of a woman veteran who served in the Republic of Vietnam (RVN), have been conceived after the date the veteran first served in the RVN during the period 2/28/61 to 5/7/75, and have certain birth defects identified by the Secretary of Veterans Affairs as resulting in permanent physical or mental disability.
Also, the law does not include conditions that are a familial disorder, a birth-related injury, or a fetal or neonatal infirmity with well-established causes.
The law does not allow payment of both benefits at the same time. If entitlement exists under both laws, benefits will be paid under 38 U.S.C. 1815.
Before you go
Before completing this form, read the Privacy Act and Respondent Burden on page 4.
Common questions about VA Form 21-0304
Where do I file it?
After completing the form, mail it to the Department of Veterans Affairs, Evidence Intake Center, P.O. Box 4444, Janesville, WI, 53547-4444.
Is there a penalty?
The law provides severe penalties which include fine or imprisonment, or both, for the willful submission of any statement or evidence of a material fact, knowing it to be false, or for the fraudulent acceptance of any payment to which you are not entitled.
Where to get help with VA Form 21-0304
For more information, you can contact VA online through Ask VA at https://ask.va.gov/ or call toll-free at 1-800-827-1000 (TTY: 711).
Sources
[1] VA Form 21-0304 (MAY 2026), Application for Benefits for a Qualifying Veteran's Child Born with Disabilities, Department of Veterans Affairs (the Official source link on this page).