
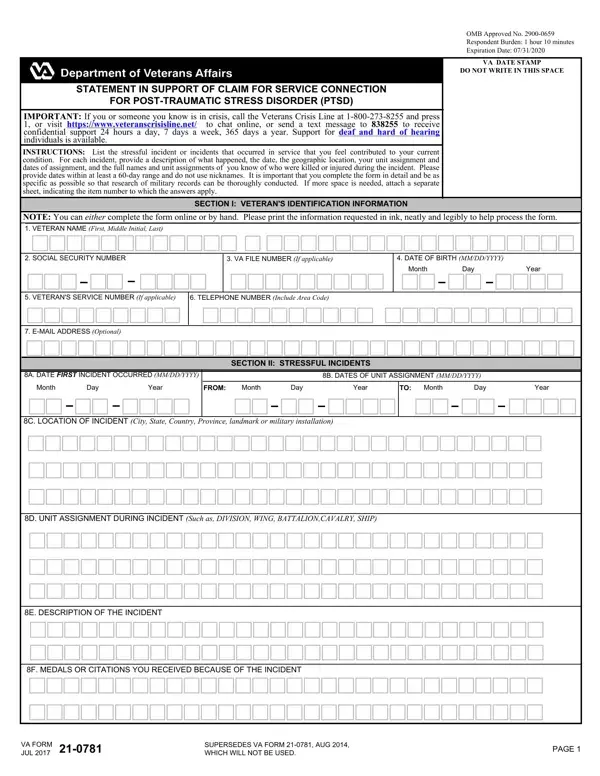

VA Form 21-0781 at a glance
What it is: VA Form 21-0781 is the Statement in Support of Claimed Mental Health Disorder(s) Due to an In-Service Traumatic Event(s); this form is optional and not required.
Where and when to file: If you are mailing your completed form, send it to: Department of Veterans Affairs Evidence Intake Center P.O. Box 4444 Janesville, WI 53547-4444 (VA FORM 21-0781, MAR 2024 PAGE 2).
Use this form to provide a statement in support of a claimed mental health disorder(s) due to an in-service traumatic event(s).
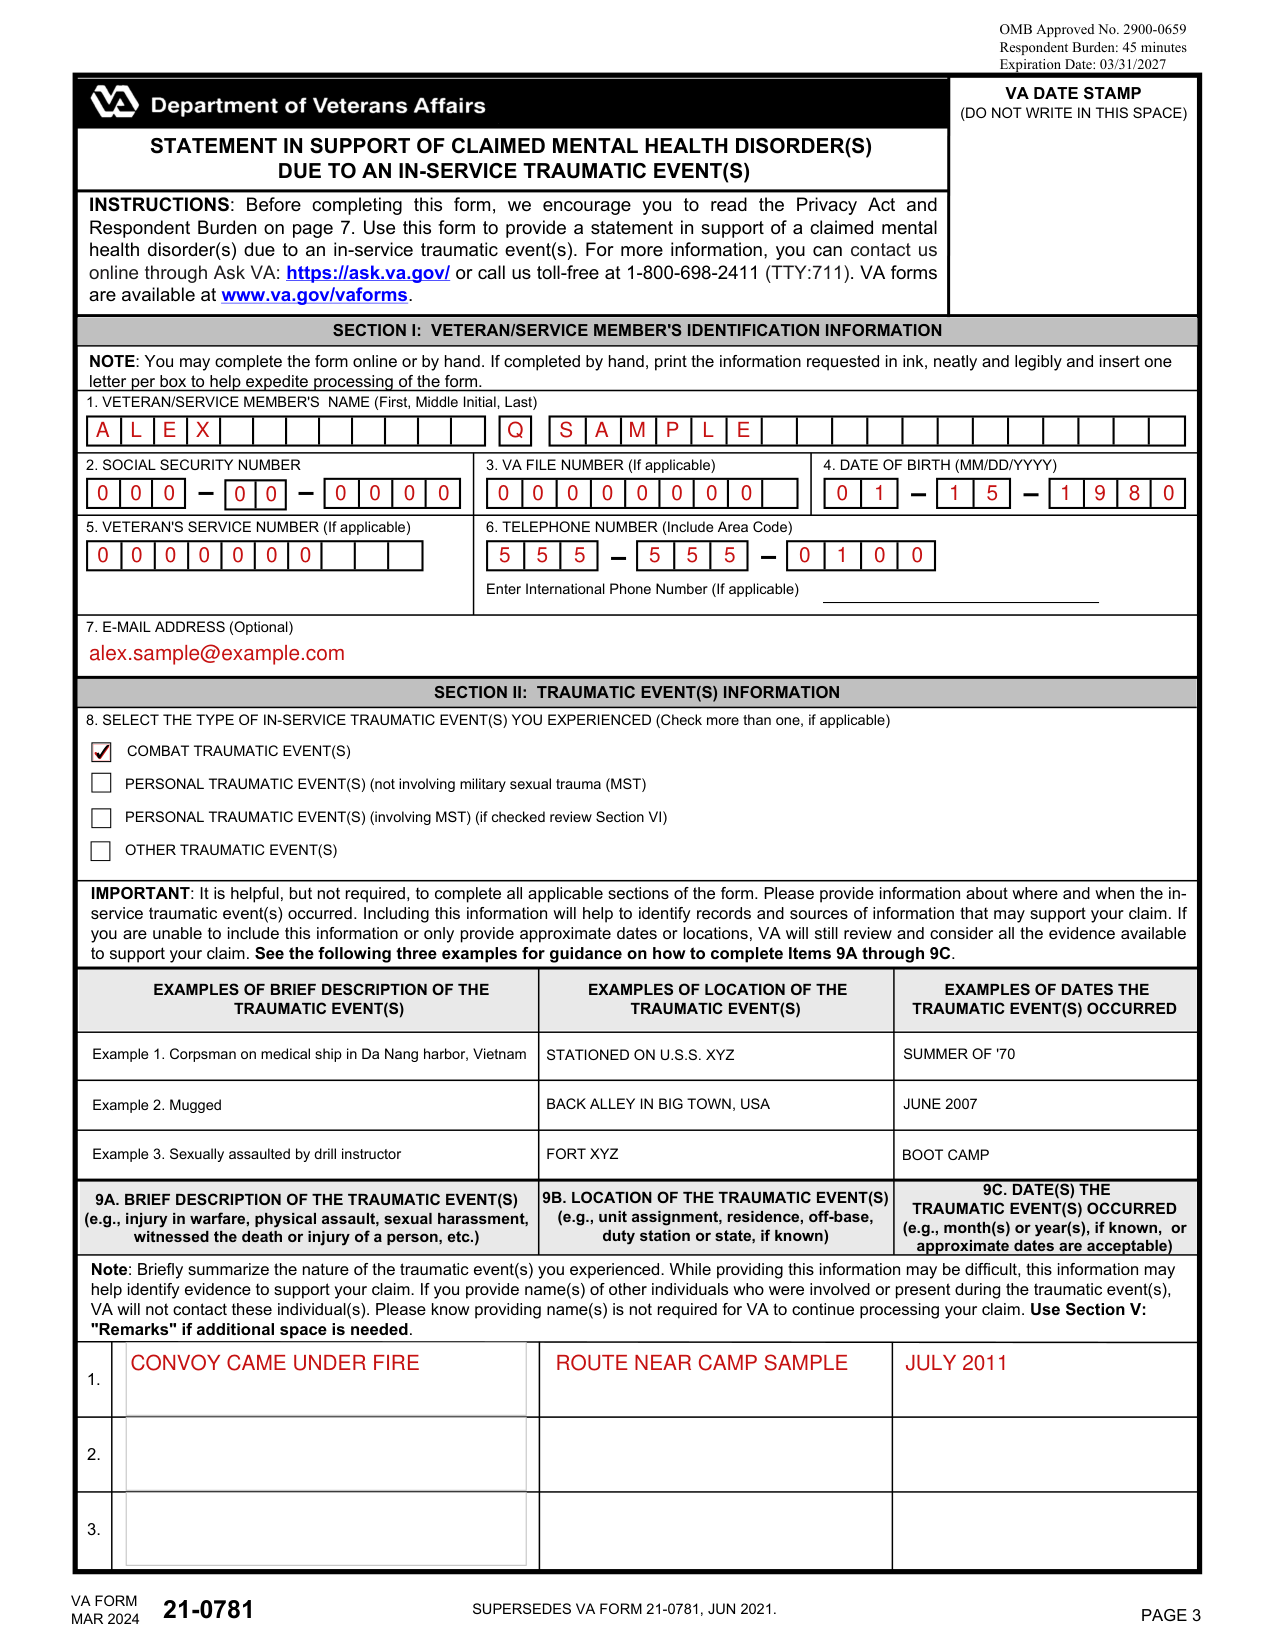
A filled-in VA Form 21-0781 example: a veteran describes a combat event
How to fill out VA Form 21-0781, box by box
SECTION I: VETERAN/SERVICE MEMBER'S IDENTIFICATION INFORMATION

If completed by hand, print the information requested in ink, neatly and legibly and insert one letter per box to help expedite processing of the form.
Enter 1. Veteran/Service Member's Name (First, Middle Initial, Last).
Enter 2. Social Security Number, 3. VA File Number (If applicable), 4. Date of Birth (MM/DD/YYYY) and 5. Veteran's Service Number (If applicable).
Enter 6. Telephone Number (Include Area Code), the International Phone Number (If applicable) and 7. E-Mail Address (Optional).
8. SELECT THE TYPE OF IN-SERVICE TRAUMATIC EVENT(S) YOU EXPERIENCED

8. Select the type of in-service traumatic event(s) you experienced (Check more than one, if applicable): Combat Traumatic Event(s), Personal Traumatic Event(s) (not involving military sexual trauma (MST)), Personal Traumatic Event(s) (involving MST) (if checked review Section VI) or Other Traumatic Event(s).
Brief description, location and date(s) of the traumatic event(s)

It is helpful, but not required, to complete all applicable sections of the form. Please provide information about where and when the in-service traumatic event(s) occurred. Including this information will help to identify records and sources of information that may support your claim.
If you are unable to include this information or only provide approximate dates or locations, VA will still review and consider all the evidence available to support your claim.
Enter 9A. Brief Description of the Traumatic Event(s) (e.g., injury in warfare, physical assault, sexual harassment, witnessed the death or injury of a person, etc.) and 9C. Date(s) the Traumatic Event(s) Occurred (e.g., month(s) or year(s), if known, or approximate dates are acceptable). Briefly summarize the nature of the traumatic event(s) you experienced.
Enter 9B. Location of the Traumatic Event(s) (e.g., unit assignment, residence, off-base, duty station or state, if known).
While providing this information may be difficult, this information may help identify evidence to support your claim. If you provide name(s) of other individuals who were involved or present during the traumatic event(s), VA will not contact these individual(s). Providing name(s) is not required for VA to continue processing your claim.
Use Section V: "Remarks" if additional space is needed.
SECTION III: ADDITIONAL INFORMATION ASSOCIATED WITH THE IN-SERVICE TRAUMATIC EVENT(S)
VA understands that in-service traumatic event(s) may not have been reported or documented. In these situations, other information, such as behavioral changes and/or sources of evidence, may be used to support the in-service traumatic event(s).
10. Indicate any behavioral changes following the in-service personal traumatic event(s). Behavioral changes can include but are not limited to the examples listed in Items 10A through 10C. If your traumatic event(s) is combat only, you may skip to Item 11. A. Behavioral changes experienced following the traumatic event(s) (Check any box that applies).
B. Additional information about the behavioral changes (If applicable), e.g., approximate time change occurred, documentation, or record.
C. As needed, list any additional behavioral changes following the in-service personal traumatic event(s) that were not listed in Item 10A.
11. WAS AN OFFICIAL REPORT FILED?
11. Was an official report filed? Yes (If "Yes," check the appropriate box below indicating which type of report was filed) or No (If "No," skip to Item 12). The boxes are Restricted, Unrestricted, Neither, Police Report (Provide location, if known) and Other.
12. POSSIBLE SOURCES OF EVIDENCE FOLLOWING THE TRAUMATIC EVENT(S)
12. Possible sources of evidence following the traumatic event(s) (Check all that apply). The following sources of evidence may provide additional information for your claim. This list is not all inclusive.
If you have any individual(s)/witness(es) who know(s) about the in-service traumatic event(s) or would have knowledge of a behavioral change you experienced after the personal traumatic event(s), and wants to provide a statement on your behalf, use VA Form 21-10210, Lay/Witness Statement.
SECTION IV: TREATMENT INFORMATION
13A. Have you received treatment related to the impact of the traumatic event(s) listed in Item 9A? Yes (If "Yes," complete Items 13B through 13E) or No (If "No," skip to Item 14).
13B. Identify where you have received treatment (Check all that apply).
VA has access to VAMC, CBOC, and MTF records. A consent form is not needed. However, if you would like VA to attempt to obtain your private provider (excluding community care (paid for by VA)) or VA Vet Center health records, VA requires your consent by completing VA Form 21-4142, and VA Form 21-4142a.
Enter 13C. Name and Location of the Treatment Facility.
Enter 13D. Date(s) of Treatment (Approximate dates are acceptable) (MM-YYYY). If VAMC, CBOC, or MTF treatment began from 2005 to present, you do not need to provide dates in Item 13D.
13E. Check the box if you do not have date(s) of treatment.
SECTION V: REMARKS
14. Remarks (If any): this section is optional and can be left blank. However, if additional space is needed to fully answer a previous question or if needed, use this section to provide any additional information that may support your claim.
SECTION VI: OPTION FOR VBA TO NOTIFY VHA ABOUT CERTAIN UPCOMING EVENTS
This section only applies if you checked personal traumatic event(s) (involving MST) in Item 8. 15. If you are filing a claim for compensation for a condition due to a personal traumatic event(s) (involving MST) and you are registered and/or enrolled for VHA health care, you have the option for VBA to electronically notify VHA about certain upcoming event(s) during your claim and/or appeal process.
SECTION VII: CERTIFICATION AND SIGNATURE
You certify that the statement(s) on this form are true and correct to the best of your knowledge and belief. Sign 16A. Veteran/Service Member's Signature and enter 16B. Date Signed (MM/DD/YYYY).
SECTION VIII: WITNESSES TO SIGNATURE
Only use this section if the veteran/service member signed Item 16A with an "X". Sign 17A. Signature of Witness and enter 17B. Printed Name and Address of Witness.
SECTION IX: ALTERNATE SIGNER CERTIFICATION AND SIGNATURE
Only required if Item 16A is blank. An alternate signer signature will not be accepted unless a valid VA Form 21-0972, Alternate Signer Certification, is of record or attached to this request. Sign 19A. Alternate Signer's Signature and enter 19B. Date Signed (MM/DD/YYYY).
VA may request further documentation or evidence to verify or confirm authorization to sign or complete an application on behalf of the claimant if necessary, such as a durable power of attorney showing authority as attorney in fact or agent, or an affidavit or notarized statement from an institution or person responsible for the care of the claimant.
SECTION X: POWER OF ATTORNEY (POA) SIGNATURE
Only required if Item 16A is blank. A POA's signature will not be accepted unless at the time of submission of this claim a valid VA Form 21-22 or VA Form 21-22a indicating the appropriate POA is of record with VA.
More rules for VA Form 21-0781
VA forms are available at www.va.gov/vaforms.
Before you go
Whether or not you complete this form, you must submit one of the following based on the type of claim sought. If you are filing a new claim or a claim for increased disability compensation, submit VA Form 21-526EZ, Application for Disability Compensation and Related Compensation Benefits. If you disagree with a prior decision or an evaluation and have new and relevant evidence, submit VA Form 20-0995, Decision Review Request: Supplemental Claim.
Common questions about VA Form 21-0781
Can you fill out VA Form 21-0781 online?
You may complete the form online or by hand.
What is VA form 21 0781 used for?
VA Form 21-0781 is the Statement in Support of Claimed Mental Health Disorder(s) Due to an In-Service Traumatic Event(s); this form is optional and not required. The requested information is important to assist VA in thoroughly researching your military record and other sources to obtain supporting evidence of traumatic event(s) in service.
Where do I file it?
You can apply online at www.va.gov. Get started at https://www.va.gov/disability/how-to-file-claim/.
Where to get help with VA Form 21-0781
For a list of accredited veterans service organizations go to https://www.va.gov/ogc/recognizedvsos.asp.
If you have any questions concerning your claim, you may call 1-800-698-2411.
Sources
[1] VA Form 21-0781 (MAR 2024), Statement in Support of Claimed Mental Health Disorder(s) Due to an In-Service Traumatic Event(s), Department of Veterans Affairs (the Official source link on this page).