How to Fill Out VSP Member Reimbursement Form

VSP Member Reimbursement Form at a glance

What it is: The VSP Member Reimbursement Form: to request reimbursement, complete this form.

Who signs: Sign on the Claimant Signature line and enter the Date.

A filled-in VSP Member Reimbursement Form example: a member requests reimbursement for new glasses
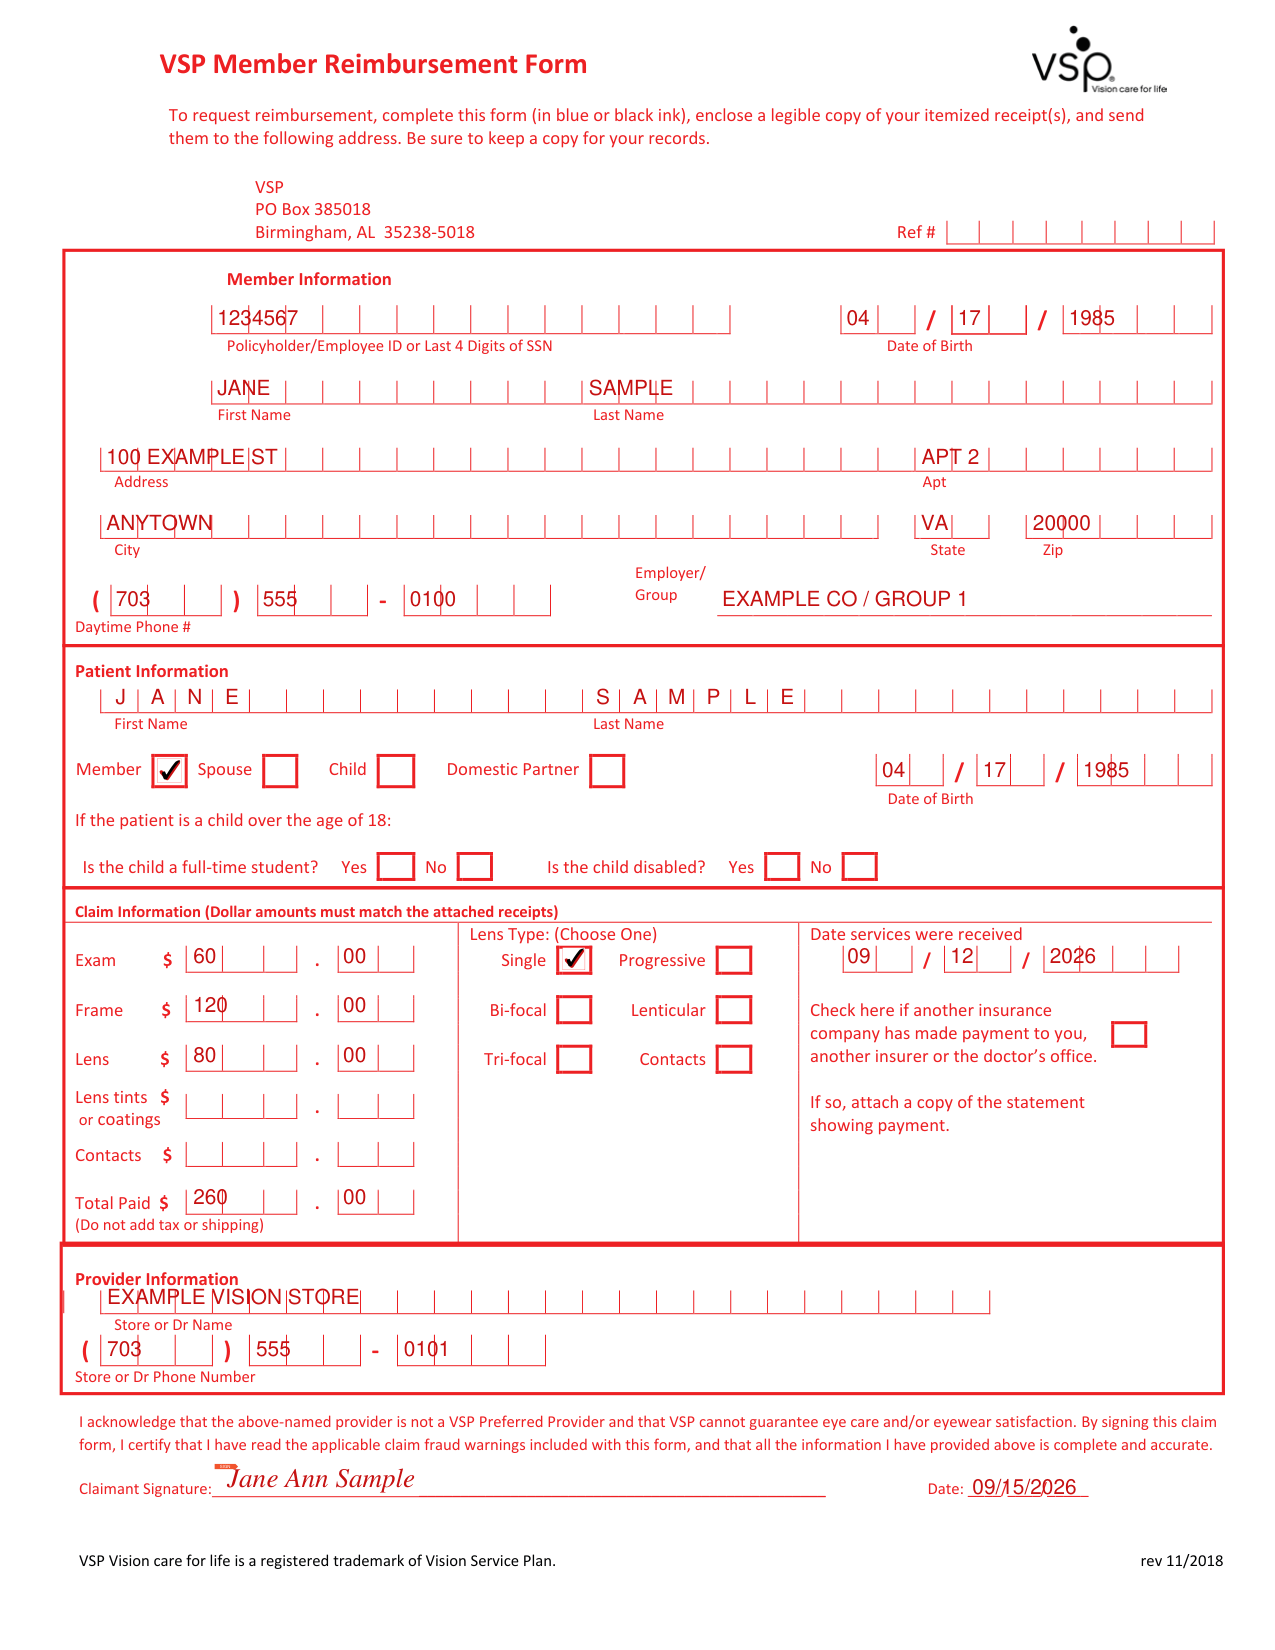
VSP Member Reimbursement Form example filled out, example: a member requests reimbursement for new glasses
Jane Ann Sample requests reimbursement on the VSP Member Reimbursement Form for her own new glasses. She paid for an exam, a frame and single vision lenses, and the receipts show no tints, coatings or contacts. The picture shows the finished form, and every value in it is made up. The patient is the member herself, so Member is ticked and Spouse, Child and Domestic Partner stay empty. The patient is an adult, so the child questions stay empty. The lenses are single vision, so Single is ticked and Bi-focal, Tri-focal, Progressive and Lenticular stay empty. Nothing goes in Lens tints or Contacts because the receipts list none. No other insurer paid, so the other insurer box stays empty. Total Paid adds the exam, frame and lens amounts without tax or shipping.

How to fill out VSP Member Reimbursement Form, box by box

Member Information
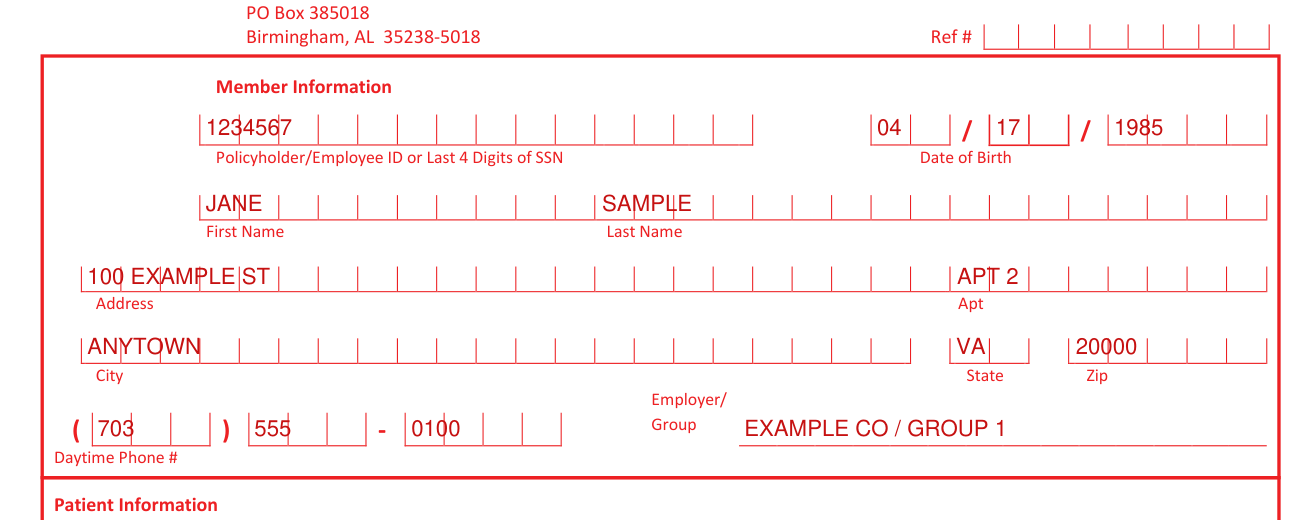
VSP Member Reimbursement Form example filled out, member Information

Under Member Information, enter the Policyholder/Employee ID or Last 4 Digits of SSN, Date of Birth, First Name, Last Name, Address, Apt, City, State, Zip, Daytime Phone # and Employer/ Group.

Patient Information
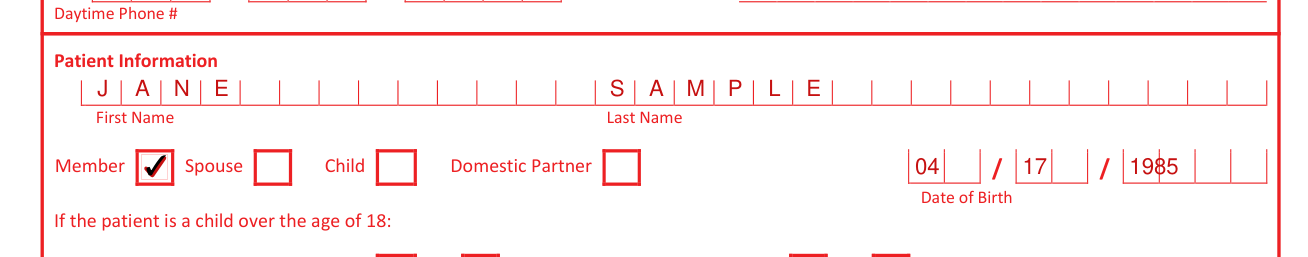
VSP Member Reimbursement Form example filled out, patient Information

Under Patient Information, enter First Name, Last Name, Member, Spouse, Child or Domestic Partner, and Date of Birth.

Claim Information
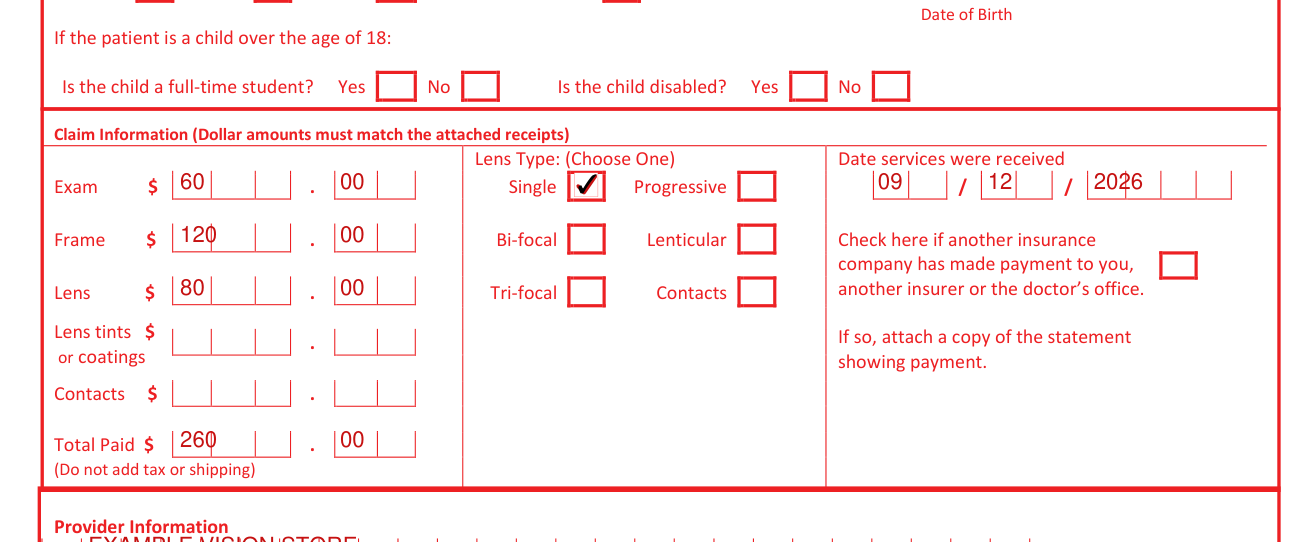
VSP Member Reimbursement Form example filled out, claim Information

If the patient is a child over the age of 18: Is the child a full-time student? Yes No Is the child disabled? Yes No. Claim Information (Dollar amounts must match the attached receipts). Lens Type: (Choose One) Single, Progressive, Bi-focal, Lenticular, Tri-focal, Contacts. Date services were received. Enter Exam $, Frame $, Lens $, Lens tints $ or coatings, Contacts $ and Total Paid $. (Do not add tax or shipping) Check here if another insurance company has made payment to you, another insurer or the doctor's office. If so, attach a copy of the statement showing payment.

Provider Information

VSP Member Reimbursement Form example filled out, provider Information

Under Provider Information, enter the Store or Dr Name and the Store or Dr Phone Number.

SIGN

VSP Member Reimbursement Form example filled out, sIGN

By signing this claim form, you certify that you have read the applicable claim fraud warnings included with this form, and that all the information you have provided is complete and accurate.

You acknowledge that the named provider is not a VSP Preferred Provider and that VSP cannot guarantee eye care and/or eyewear satisfaction.

Sign on the Claimant Signature line and enter the Date.

More rules for VSP Member Reimbursement Form

Be sure to keep a copy for your records.

Common questions about VSP Member Reimbursement Form

Where do I file it?

To request reimbursement, complete this form (in blue or black ink), enclose a legible copy of your itemized receipt(s), and send them to VSP PO Box 385018 Birmingham, AL 35238-5018.

Is there a penalty?

Pennsylvania and all other states: Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance or a statement of claim containing any materially false information or conceals for the purpose of misleading, information concerning any fact material thereto commits a fraudulent insurance act, which is a crime and subjects such person to criminal and civil penalties.

Sources

[1] VSP Member Reimbursement Form (rev 11/2018), Vision Service Plan (the Official source link on this page).

Vsp Reimbursement Form PDF Details

Navigating the world of insurance claims can often feel like a maze, especially when it comes to health benefits like vision care. This is where the VSP Member Reimbursement Form comes into play, a crucial document for those seeking reimbursement for out-of-pocket vision care expenses not directly covered by their provider. When utilizing this form, it's important to fill it out meticulously, using blue or black ink, and to include all necessary itemized receipts for your expenses. The form requires members to provide comprehensive information, including policyholder details, patient information — specifying the relationship to the member, and a detailed breakdown of costs related to vision care services and products. Additionally, the form accommodates claims involving other insurers, asking members to disclose if another insurance company has already processed a payment. It is crucial to acknowledge that the form carries severe warnings against false claims, with different states listing specific consequences for fraudulent submissions. Completing this form accurately ensures a smoother reimbursement process from VSP, a significant player in the vision insurance sector, helping members manage their vision care costs more efficiently.

QuestionAnswer
Form NameVsp Reimbursement Form
Form Length4 pages
Fillable?No
Fillable fields0
Avg. time to fill out1 min
Other namesvsp claim form printable, vsp member, out of network reimbursement form vsp, vsp claim forms