


Form WKC-16-B-E at a glance
What it is: WKC-16-B-E is the Practitioner's Report on Accident or Industrial Disease in Lieu of Testimony, filed on behalf of the employee or the employer or insurance carrier.
Who signs: Sign on the Signature of Practitioner line and enter the Date Signed.
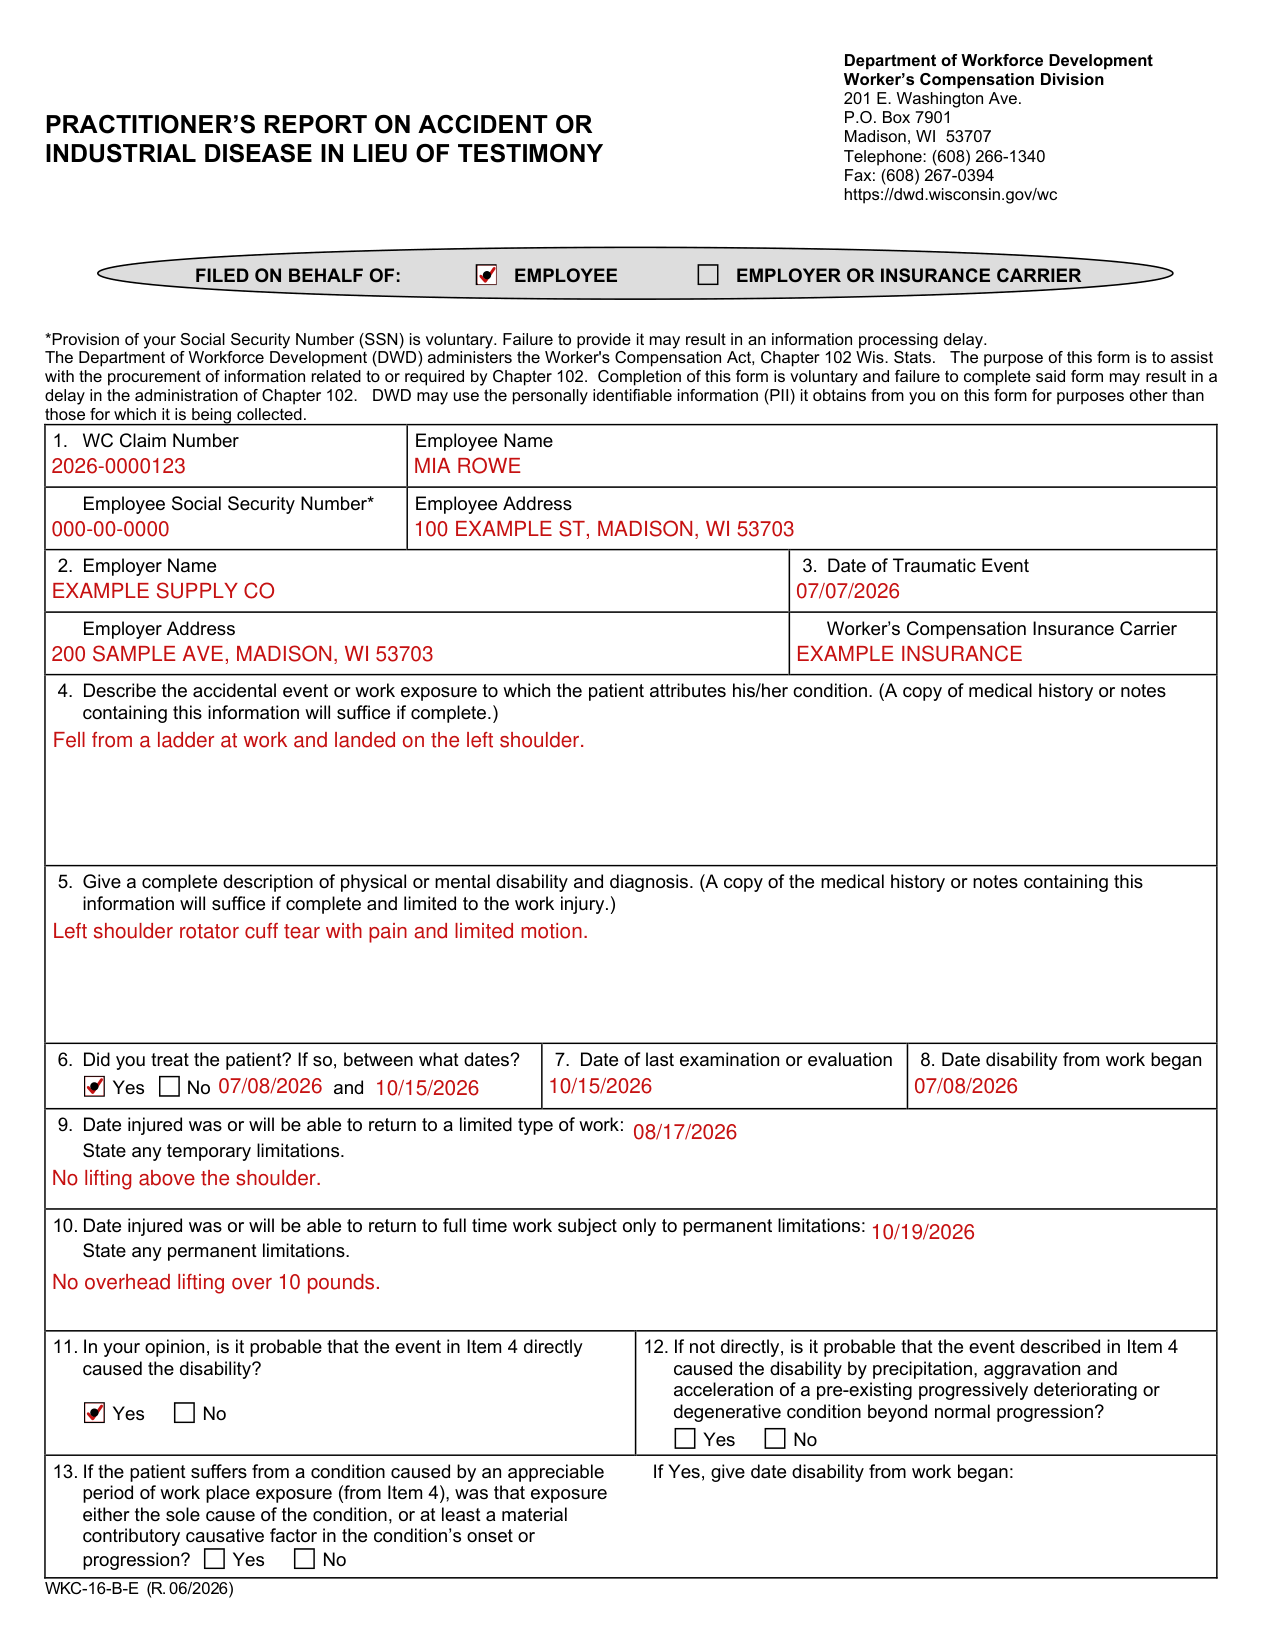
A filled-in Form WKC-16-B-E example: a practitioner reports a shoulder injury
How to fill out Form WKC-16-B-E, box by box
Filed on behalf of

Mark FILED ON BEHALF OF: EMPLOYEE or EMPLOYER OR INSURANCE CARRIER.
Claim, employee, employer and date of traumatic event

Enter the WC Claim Number, Employee Name, Employee Social Security Number and Employee Address; provision of the Social Security Number is voluntary and failure to provide it may result in an information processing delay. The Department of Workforce Development administers the Worker's Compensation Act, Chapter 102 Wis. Stats.
Enter the Employer Name, the Date of Traumatic Event, the Employer Address and the Worker's Compensation Insurance Carrier.
Describe the event and the disability: 4 and 5
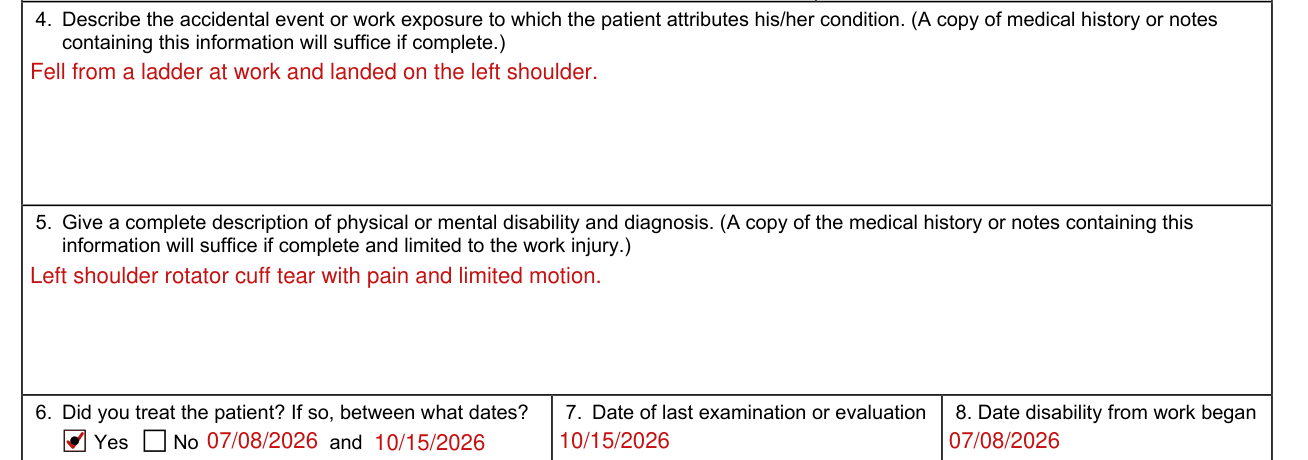
Describe the accidental event or work exposure to which the patient attributes his/her condition; a copy of medical history or notes containing this information will suffice if complete.
Give a complete description of physical or mental disability and diagnosis; a copy of the medical history or notes containing this information will suffice if complete and limited to the work injury.
Did you treat the patient, dates and limitations: 6 to 10
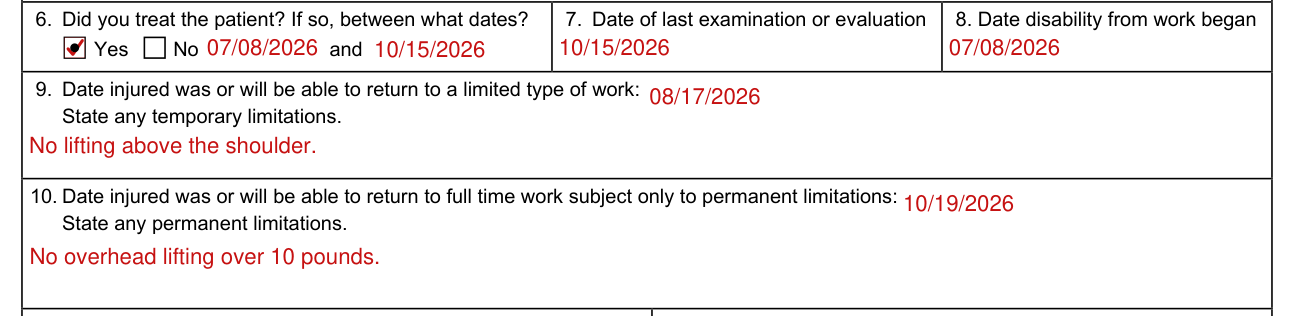
Mark Yes or No to Did you treat the patient, and if so, enter between what dates.
Enter the Date of last examination or evaluation and the Date disability from work began.
Enter the date injured was or will be able to return to a limited type of work, and state any temporary limitations.
Enter the date injured was or will be able to return to full time work subject only to permanent limitations, and state any permanent limitations.
Items 11, 12 and 13: the cause

Mark Yes or No: in your opinion, is it probable that the event in Item 4 directly caused the disability?
If not directly, mark Yes or No: is it probable that the event described in Item 4 caused the disability by precipitation, aggravation and acceleration of a pre-existing progressively deteriorating or degenerative condition beyond normal progression?
If the patient suffers from a condition caused by an appreciable period of work place exposure (from Item 4), mark Yes or No: was that exposure either the sole cause of the condition, or at least a material contributory causative factor in the condition's onset or progression? If Yes, give date disability from work began.
Items 14 to 19: permanent disability and further treatment
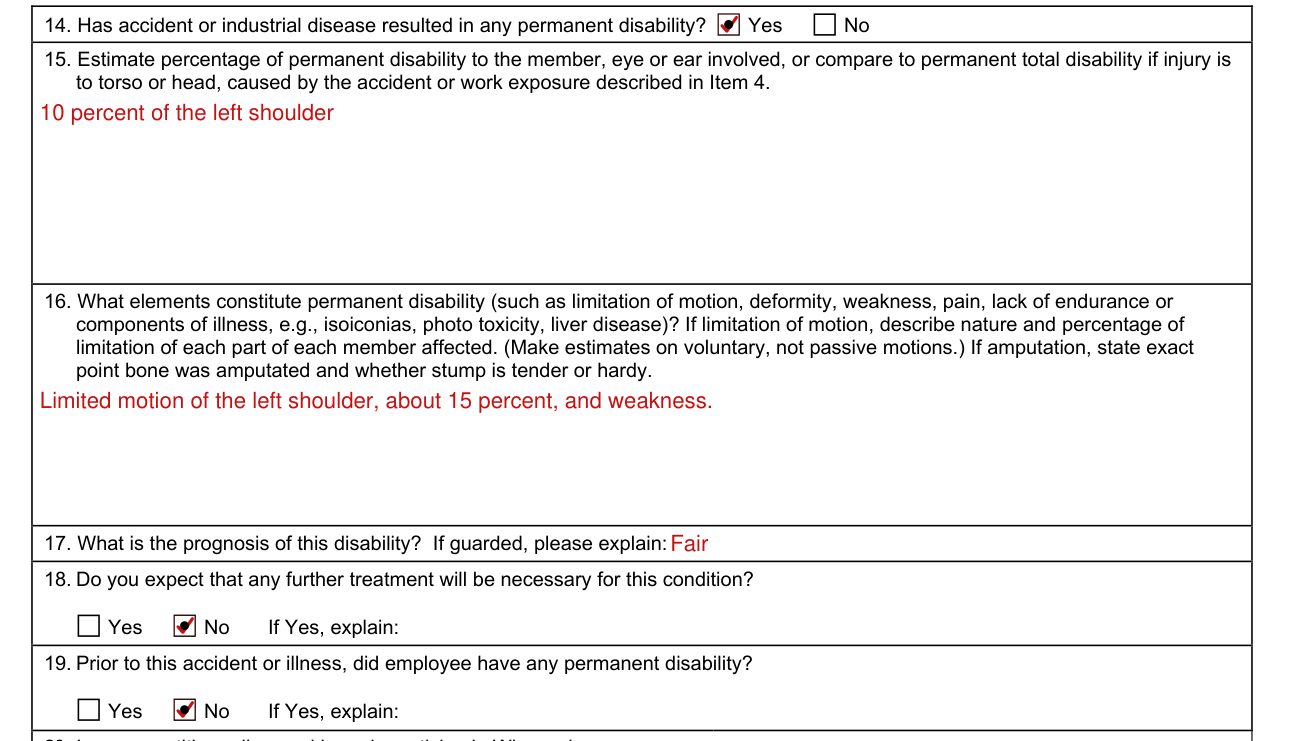
Mark Yes or No: has accident or industrial disease resulted in any permanent disability?
Estimate percentage of permanent disability to the member, eye or ear involved, or compare to permanent total disability if injury is to torso or head, caused by the accident or work exposure described in Item 4.
What elements constitute permanent disability (such as limitation of motion, deformity, weakness, pain, lack of endurance or components of illness, e.g., isoiconias, photo toxicity, liver disease)? If limitation of motion, describe nature and percentage of limitation of each part of each member affected. (Make estimates on voluntary, not passive motions.)
If amputation, state exact point bone was amputated and whether stump is tender or hardy.
What is the prognosis of this disability? If guarded, please explain.
Mark Yes or No: do you expect that any further treatment will be necessary for this condition? If Yes, explain.
Mark Yes or No: prior to this accident or illness, did employee have any permanent disability? If Yes, explain.
Practitioner certification and signature: 20

I am a practitioner licensed in and practicing in Wisconsin. If not licensed and practicing in Wisconsin, state where practitioner is licensed and practicing.
CERTIFICATION: certify, subject to the penalty of fine and/or imprisonment, as provided in Sec. 943.39 of the Wisconsin Statutes, that the report truly and correctly sets forth the history, my findings, diagnosis and opinion.
Enter the Practitioner Typed or Printed Name, Practitioner Address (Street or P.O. Box), Practitioner Address (City, State and Zip Code), Practitioner Phone Number and College.
More rules for Form WKC-16-B-E
Section 102.17(1)(d) of the Wisconsin Statutes provides that the contents of certified medical and surgical reports presented by parties shall constitute prima facie evidence as to the matter contained therein.
Common questions about Form WKC-16-B-E
Is there a deadline?
Reports must be filed with the department and the other parties fifteen days prior to the date of hearing to be acceptable as evidence. If not so filed, it will be necessary to produce the doctor to give oral testimony at the time of hearing.
Sources
[1] Form WKC-16-B-E (R. 06/2026), Practitioner's Report on Accident or Industrial Disease in Lieu of Testimony, Wisconsin Department of Workforce Development (the Official source link on this page).