
Updated:
Get Form Now
VA Form 10-5345, titled “Request for and Authorization to Release Medical Records or Health Information,” allows veterans to authorize the release of their medical records and health information to external entities, such as private health care providers, insurance companies, or legal representatives. This form is particularly important for ensuring continuity of care when a veteran receives medical treatment outside the VA system or when records are needed for personal, insurance, or legal purposes. By completing VA Form 10-5345, veterans facilitate the secure and efficient transfer of their health information, respecting privacy laws and ensuring that their health data is handled appropriately.
Other VA Forms
If you’d like to find more VA PDFs you can edit and fill in online, listed here are examples of the more popular forms among our users. Also, do not forget that you can actually upload, fill out, and edit any PDF form at FormsPal.
What it is: VA Form 10-5345 is the Request for and Authorization to Release Health Information.
Who signs: Patient: sign in ink on PATIENT SIGNATURE and enter the DATE (MM/DD/YYYY). If applicable, the legal representative signs in ink on LEGAL REPRESENTATIVE SIGNATURE and enters the DATE (MM/DD/YYYY).


Enter the Name and Location of the VA Health Care Facility under TO: DEPARTMENT OF VETERANS AFFAIRS.
Enter the LAST NAME, FIRST NAME and MIDDLE NAME, then the DATE OF BIRTH (MM/DD/YYYY).
Enter the PATIENT'S MAILING ADDRESS, including City, State and Zip Code.
Enter the NAME AND ADDRESS OF ORGANIZATION, INDIVIDUAL, OR TITLE OF INDIVIDUAL TO WHOM INFORMATION IS TO BE RELEASED.

Under PURPOSE(S) OR NEED, check TREATMENT, BENEFITS, LEGAL, EMPLOYMENT or OTHER for what the requestor will use the information, and for OTHER write the purpose after (Please specify other).
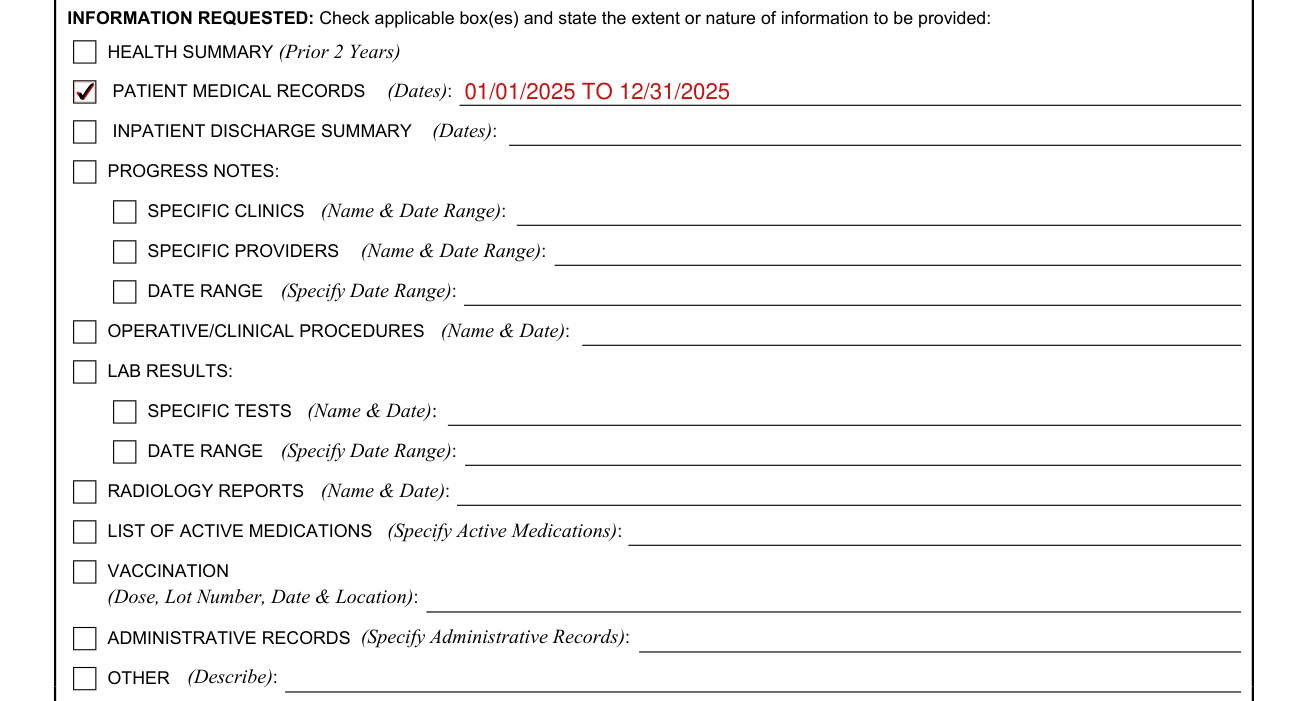
Check the applicable box(es) and state the extent or nature of information to be provided.
Check HEALTH SUMMARY (Prior 2 Years).
Check PATIENT MEDICAL RECORDS and enter the Dates.
Check INPATIENT DISCHARGE SUMMARY and enter the Dates.
Check PROGRESS NOTES, then SPECIFIC CLINICS (Name & Date Range), SPECIFIC PROVIDERS (Name & Date Range) or DATE RANGE (Specify Date Range).
Check OPERATIVE/CLINICAL PROCEDURES and enter the Name & Date.
Check LAB RESULTS, then SPECIFIC TESTS (Name & Date) or DATE RANGE (Specify Date Range).
Check RADIOLOGY REPORTS and enter the Name & Date.
Check LIST OF ACTIVE MEDICATIONS and Specify Active Medications.
Check VACCINATION and enter the Dose, Lot Number, Date & Location.
Check ADMINISTRATIVE RECORDS and Specify Administrative Records.
Check OTHER and Describe it.

Review and, if appropriate, complete SENSITIVE DIAGNOSES when release is for any purpose other than treatment.
Check DRUG ABUSE, ALCOHOLISM OR ALCOHOL ABUSE, SICKLE CELL ANEMIA or HUMAN IMMUNODEFICIENCY VIRUS (HIV).
Information on these sensitive diagnoses may be released for treatment purposes without checking the boxes, and will be released even if the boxes are unchecked unless you indicate by checking the box for this specific disclosure that you do not want sensitive diagnoses released for treatment purposes under this specific authorization.
This does not impact other future requests unrelated to this authorization.

Without your express revocation, the authorization will automatically expire. Select one of the following.
AFTER ONE-TIME DISCLOSURE, IF ALL NEEDS ARE SATISFIED.
ON (Date) (MM/DD/YYYY): enter a future date other than date signed by patient.
Mark Under condition(s) and fill in Specify Condition(s).
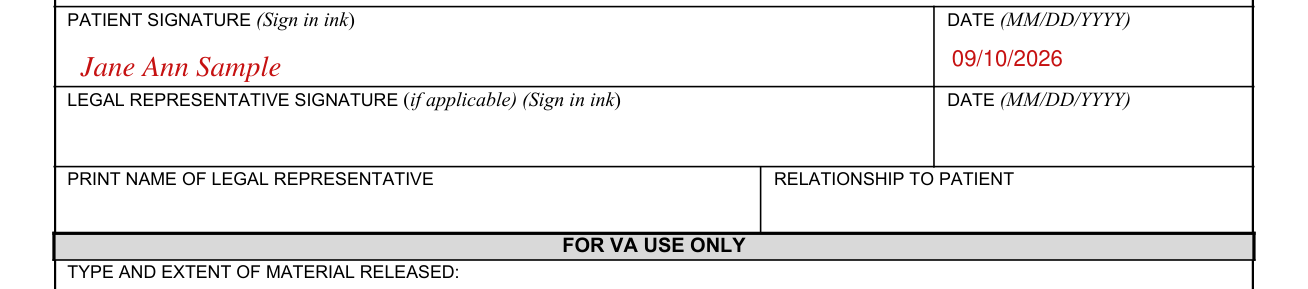
You certify that this request has been made freely, voluntarily and without coercion and that the information given is accurate and complete to the best of your knowledge.
Patient: sign in ink on PATIENT SIGNATURE and enter the DATE (MM/DD/YYYY).
If applicable, the legal representative signs in ink on LEGAL REPRESENTATIVE SIGNATURE and enters the DATE (MM/DD/YYYY).
If the legal representative signs, enter the PRINT NAME OF LEGAL REPRESENTATIVE and RELATIONSHIP TO PATIENT.
You will receive a copy of this form after you sign it.
You may revoke this authorization in writing, at any time except to the extent that action has already been taken to comply with it. Written revocation is effective upon receipt by the Release of Information Unit at the facility housing records.
Any disclosure of information carries with it the potential for unauthorized redisclosure, and the information may not be protected by federal confidentiality rules.
The VA health care provider's opinions and statements are not official VA decisions regarding whether you will receive other VA benefits or, if you receive VA benefits, their amount. They may, however, be considered with other evidence when these decisions are made at a VA Regional Office that specializes in benefit decisions.
VA Form 10-5345 is the Request for and Authorization to Release Health Information. The FOR VA USE ONLY part is for the type and extent of material released, the date released and who released it.
[1] VA Form 10-5345 (MAY 2026), Request for and Authorization to Release Health Information, Department of Veterans Affairs (the Official source link on this page).