

Ab 1424 at a glance
What it is: Alameda County Behavioral Health Care Services form for family members and other interested parties to communicate the client's mental health history pursuant to AB 1424.
Where and when to file: If available, this document should accompany the 5150 to the receiving facility.
A filled-in Ab 1424 example: a sister reports her brother's history

How to fill out Ab 1424, box by box
Name of Consumer, Date of Birth and Phone
Enter the Name of Consumer, Date of Birth and Phone.
Address, Primary Language and Religion

Enter the Address, Primary Language and Religion.
Medi-Cal, Medicare and Name of Private Medical Insurer

For Medi-Cal and Medicare, mark Yes or No. Enter the Name of Private Medical Insurer.
Authorization, emergency contact and WRAP or Advance Directive

Mark Yes or No: Please ask the consumer to sign an authorization permitting Alameda County mental health providers to communicate with me about his/her care.
Mark Yes or No: I wish to be contacted as soon as possible in case of emergency, transfer or discharge.
Mark Yes or No: The consumer has a Wellness Recovery Action Plan (WRAP) or Advance Directive. If yes, and a copy is available, attach a copy to form.
Brief History of mental illness

Under Brief History of mental illness, enter the age of onset, prior 5150's, prior hospitalizations, history of violence, history of self harm and history of unstable living situations. Attach additional pages, if necessary. Enter the Age illness began.
Mark No or Yes for Prior 5150's. If yes, enter how many.
Mark No or Yes for Prior hospitalizations. If yes, enter how many.
Conservator, diagnosis and substance abuse

Mark No, Yes or Don't know: Does consumer have a conservator?
If yes, enter the name and phone. Mark No, Yes or Don't know: Do you know consumer's diagnosis? Please explain. Mark No, Yes or Don't know: Do you know of any substance abuse problem? Please explain.
Current medications (Psychiatric and Medical)

Under Current medications (Psychiatric and Medical), enter Names. Enter the Medications consumer has responded well to and the Medications that did not work for the consumer.
Treating Psychiatrist and Case Manager

Under Treating Psychiatrist and Case Manager, enter the Psychiatrist and Phone, and the Case Manager and Phone.
Medical

Under Medical, enter Significant Medical Conditions, Allergies to Medications, Food, Chemicals, Other, and the Primary Care Physician and Phone.
Current Living Situation

Under Current Living Situation, mark Family, Independent, Homeless, Transitional, Board & Care or SIL. Is this a stable situation for consumer?
Information submitted by

Under Information submitted by, enter Name (print), Relationship to consumer, Address (city) (state) (zip), Phone, Signature and Date.
History of Consumer's Decompensation
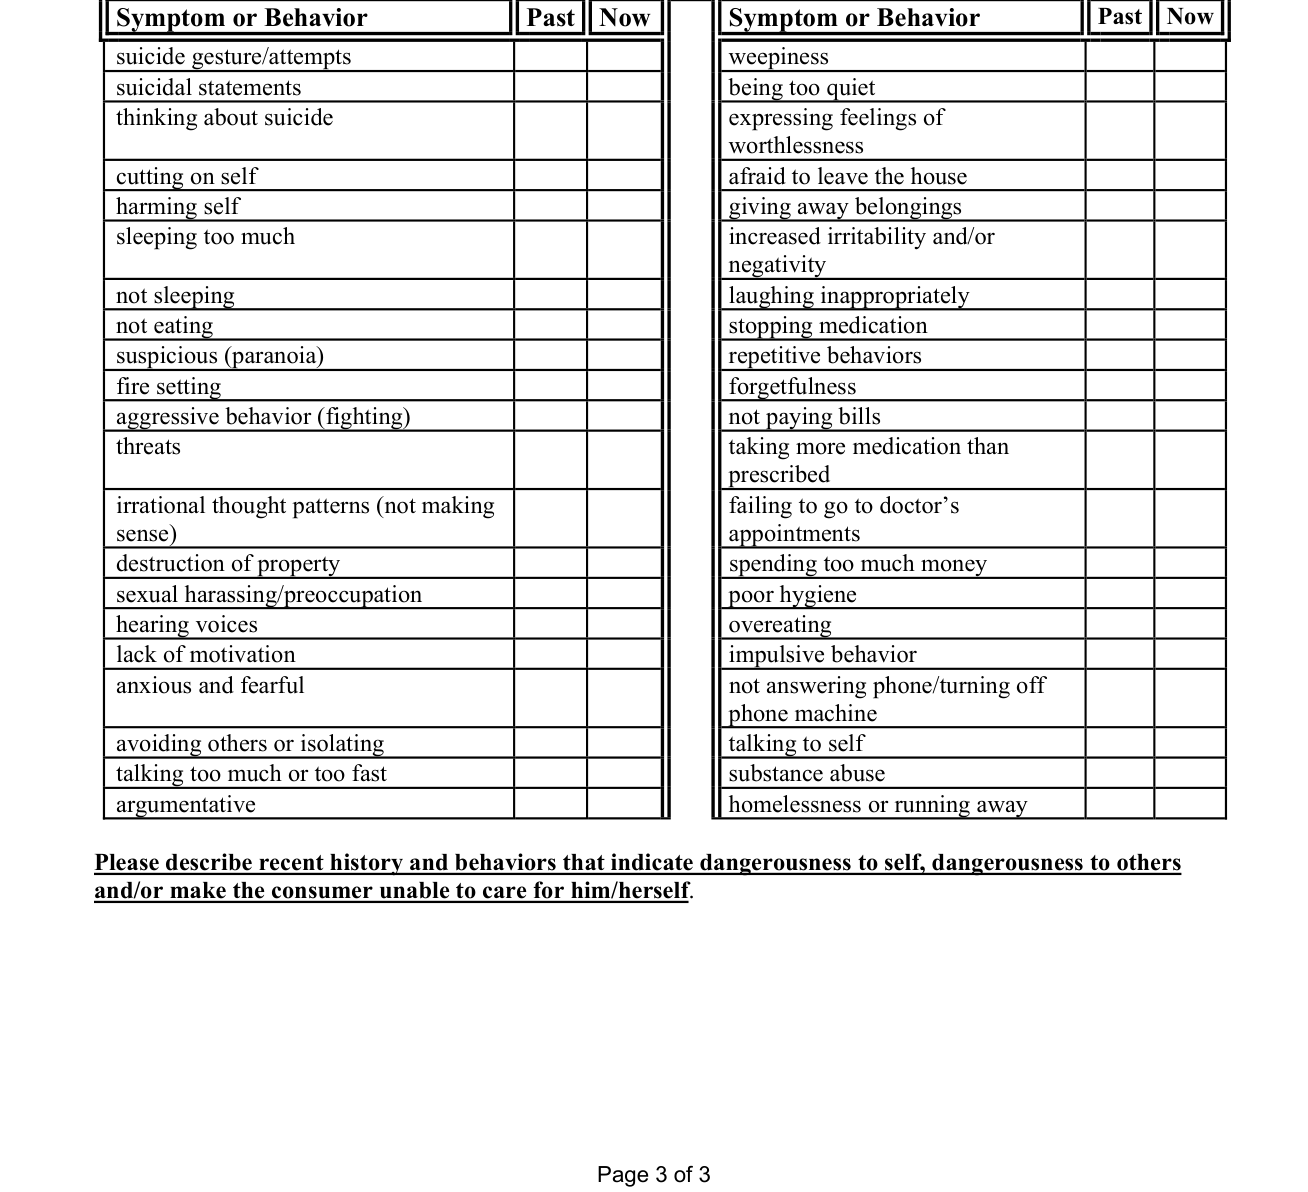
Please check off symptoms or behaviors that consumer has had in past when decompensating and indicate which ones you are observing with the consumer now. Mark Past or Now for each Symptom or Behavior.
Please describe recent history and behaviors that indicate dangerousness to self, dangerousness to others and/or make the consumer unable to care for him/herself.
More rules for Ab 1424
Mental health staff will place this form in the consumer's mental health chart. Under California and Federal law, consumers have the right to view their chart.
The Family member completing this form has the right to withdraw consent to release information given by them and have the information regarded as confidential (Welfare & Institutions Code 5328(b)).
California Assembly Bill 1424 (2001), now a law, requires all individuals making decisions about involuntary treatment to consider information supplied by family members and other interested parties.
Common questions about Ab 1424
Is there a penalty?
A person shall be liable in a civil action for intentionally giving any statement that he or she knows to be false (Welfare & Institutions Code, Section 515.05(d)).
Sources
[1] AB 1424 form rev. 10/2006, Historical Information Provided by Family Member or Other Interested Party, Alameda County Behavioral Health Care Services (the Official source link on this page).