
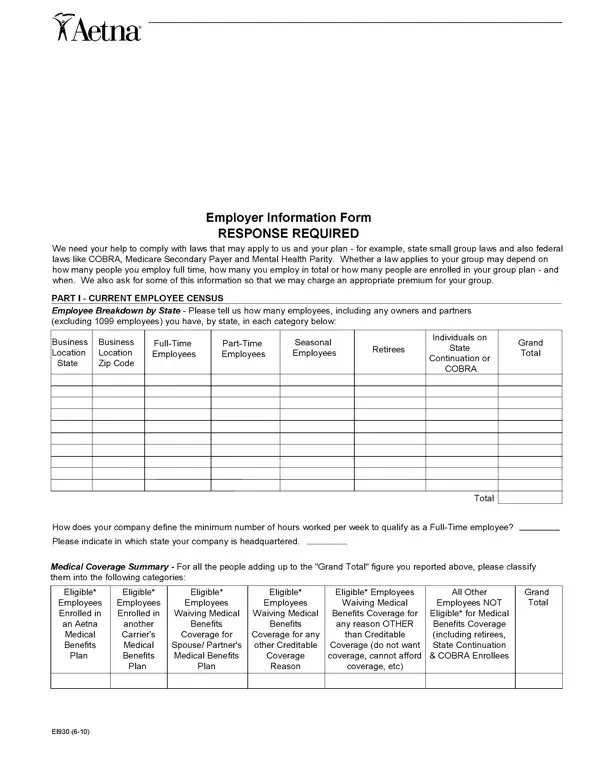

Employer Verification Form (EI930) at a glance
What it is: Employer Verification Form: RESPONSE REQUIRED.
Who signs: Enter the Signature of Owner/Officer or Authorized Representative of the Company, Telephone Number, Tax Identification Number (TIN), Print Name and Date Signed.
Aetna needs your help to comply with laws that may apply to Aetna and your plan - for example, state small group laws and also federal laws like COBRA, Medicare Secondary Payer and Mental Health Parity. Whether a law applies to your group may depend on how many people you employ full time, how many you employ in total or how many people are enrolled in your group plan - and when.
A filled-in Employer Verification Form (EI930) example: a small employer fills in page 1
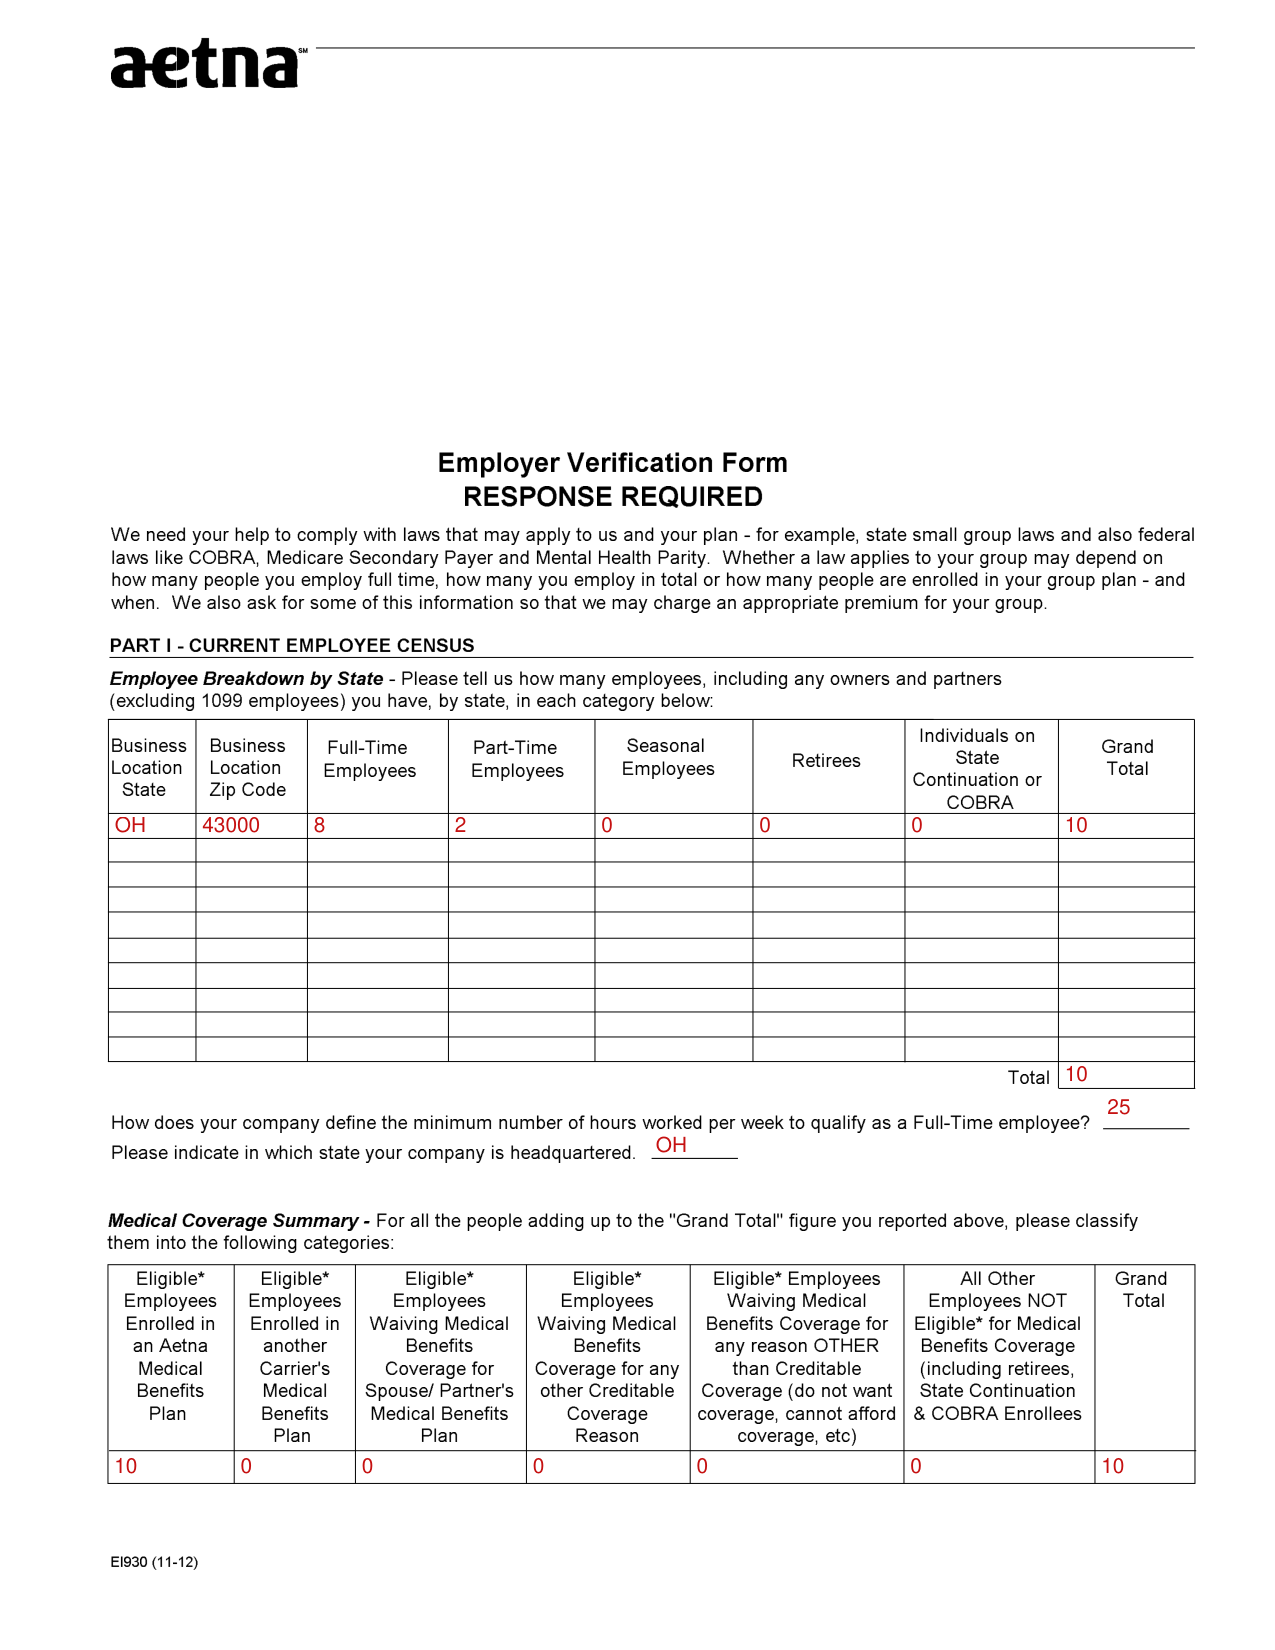
How to fill out Employer Verification Form (EI930), box by box
PART I - CURRENT EMPLOYEE CENSUS
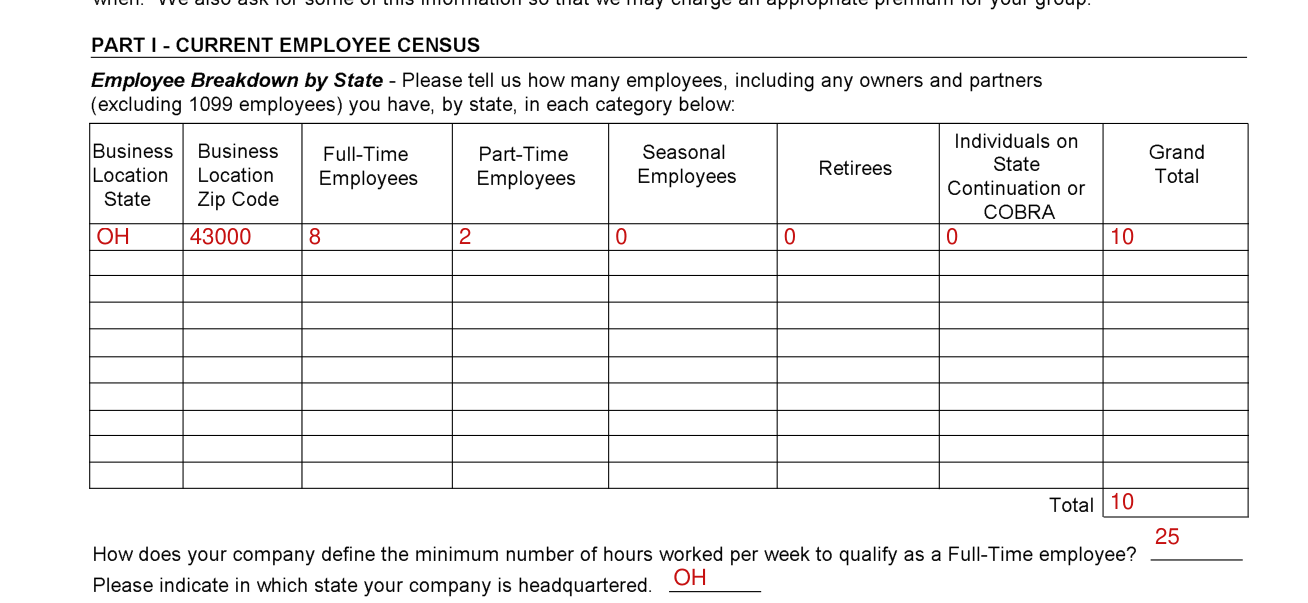
Under Business Location State and Business Location Zip Code, tell Aetna how many employees, including any owners and partners (excluding 1099 employees) you have, by state, in each category: Full-Time Employees, Part-Time Employees, Seasonal Employees, Retirees and Individuals on State Continuation or COBRA, with the Grand Total.
Full-Time employee hours and headquarters state

How does your company define the minimum number of hours worked per week to qualify as a Full-Time employee? Please indicate in which state your company is headquartered.
Medical Coverage Summary
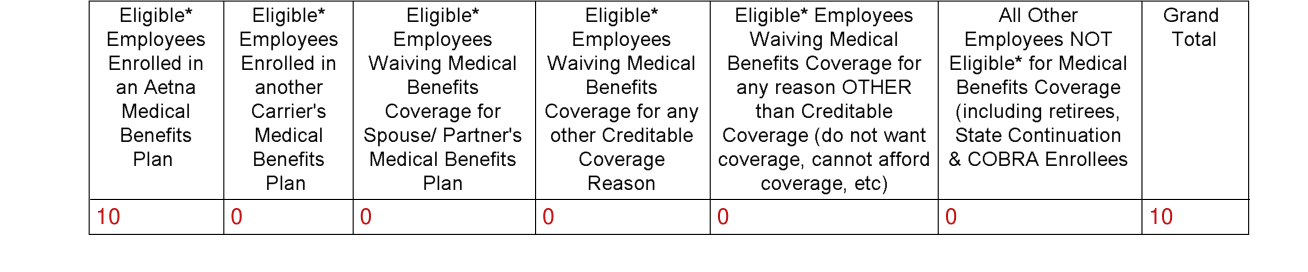
For all the people adding up to the "Grand Total" figure you reported in PART I - CURRENT EMPLOYEE CENSUS, please classify them into the following categories: Eligible* Employees Enrolled in an Aetna Medical Benefits Plan; Eligible* Employees Enrolled in another Carrier's Medical Benefits Plan.
Eligible* Employees Waiving Medical Benefits Coverage for Spouse/ Partner's Medical Benefits Plan; Eligible* Employees Waiving Medical Benefits Coverage for any other Creditable Coverage Reason; Eligible* Employees Waiving Medical Benefits Coverage for any reason OTHER than Creditable Coverage (do not want coverage, cannot afford coverage, etc); All Other Employees NOT Eligible* for Medical Benefits Coverage (including retirees, State Continuation & COBRA Enrollees; then the Grand Total).
PART lI - EMPLOYER INFORMATION: total employees

In total, how many full-time and part-time employees (including any seasonal employees, owners or partners) have you employed: a. for 20 or more weeks during this calendar year or prior calendar year? b. on 50% or more of your business days during the prior calendar year?
(1) How many of the employees that you noted in a. and in b. of 1) are self-employed, independent contractors (or their employees and agents), leased employees, or non-employee directors?
1099 employees and the small employer exemption under Federal Mental Health Parity

Do you have any 1099 employees eligible for coverage? No or Yes; if yes, how many?
Do you qualify for the small employer exemption under Federal Mental Health Parity? No or Yes. If you employed an average of 50 or FEWER total employees (including part-time and seasonal employees) during the preceding calendar year, the plan DOES qualify for the MHPAEA small employer exemption and your plan is NOT SUBJECT to MHPAEA. If you employed an average of 51 or MORE total employees (including part-time and seasonal employees) during the preceding calendar year, the plan DOES NOT qualify for the MHPAEA small employer exemption and your plan IS SUBJECT to MHPAEA.
Yes means you are exempt and MHP does NOT apply. No means MHP does apply.
You may want to consult with legal counsel to determine your status under the mental health parity law.
ERISA Form 5500

Is your plan required to file an ERISA Form 5500? No or Yes.
Your contribution toward your employees' medical coverage

Please indicate your contribution toward your employees' medical coverage: Employee: 0% 25% 50% 75% Other: _____% Other: _____$ Dependent(s): 0% 25% 50% 75% Other: _____% Other: _____$
Worker's Compensation and cost sharing funding

Do you, as an employer, cover your employees under Worker's Compensation? No or Yes. If yes, please provide documentation as proof of coverage in conjunction with your response.
Do you, or any third party on your behalf, in any way fund or subsidize any portion of the member's cost sharing responsibilities (deductibles, coinsurance or copays) under a high deductible health plan (HSA or HRA)? Types of funding arrangements include but not limited to: Gap, Wrap, HSA, HRA, etc. No or Yes; if yes, what percentage?
More rules for Employer Verification Form (EI930)
By signing this form, you represent to Aetna that the information on this form is accurate to the best of your knowledge and belief.
Aetna is relying on what you have stated on this form. Aetna may raise premiums if anything stated on this form is materially incorrect. It is unlawful to defraud an insurer. If you have knowingly misrepresented anything on this form, Aetna may have the right to rescind or cancel your company's insurance. Subject to state and federal law restrictions, Aetna may have the right not to renew coverage if your company does not meet Aetna's contribution and participation requirements as stated in your application/contract.
Sources
[1] Employer Verification Form EI930 (11-12), Aetna (the served file; no issuer file found) (the Official source link on this page).