


Pharmacy Prior Authorization Request Form at a glance
What it is: Pharmacy Prior Authorization Request Form.
Who signs: Prescribing Provider's Signature and Date.
A filled-in Pharmacy Prior Authorization Request Form example: a new medication request
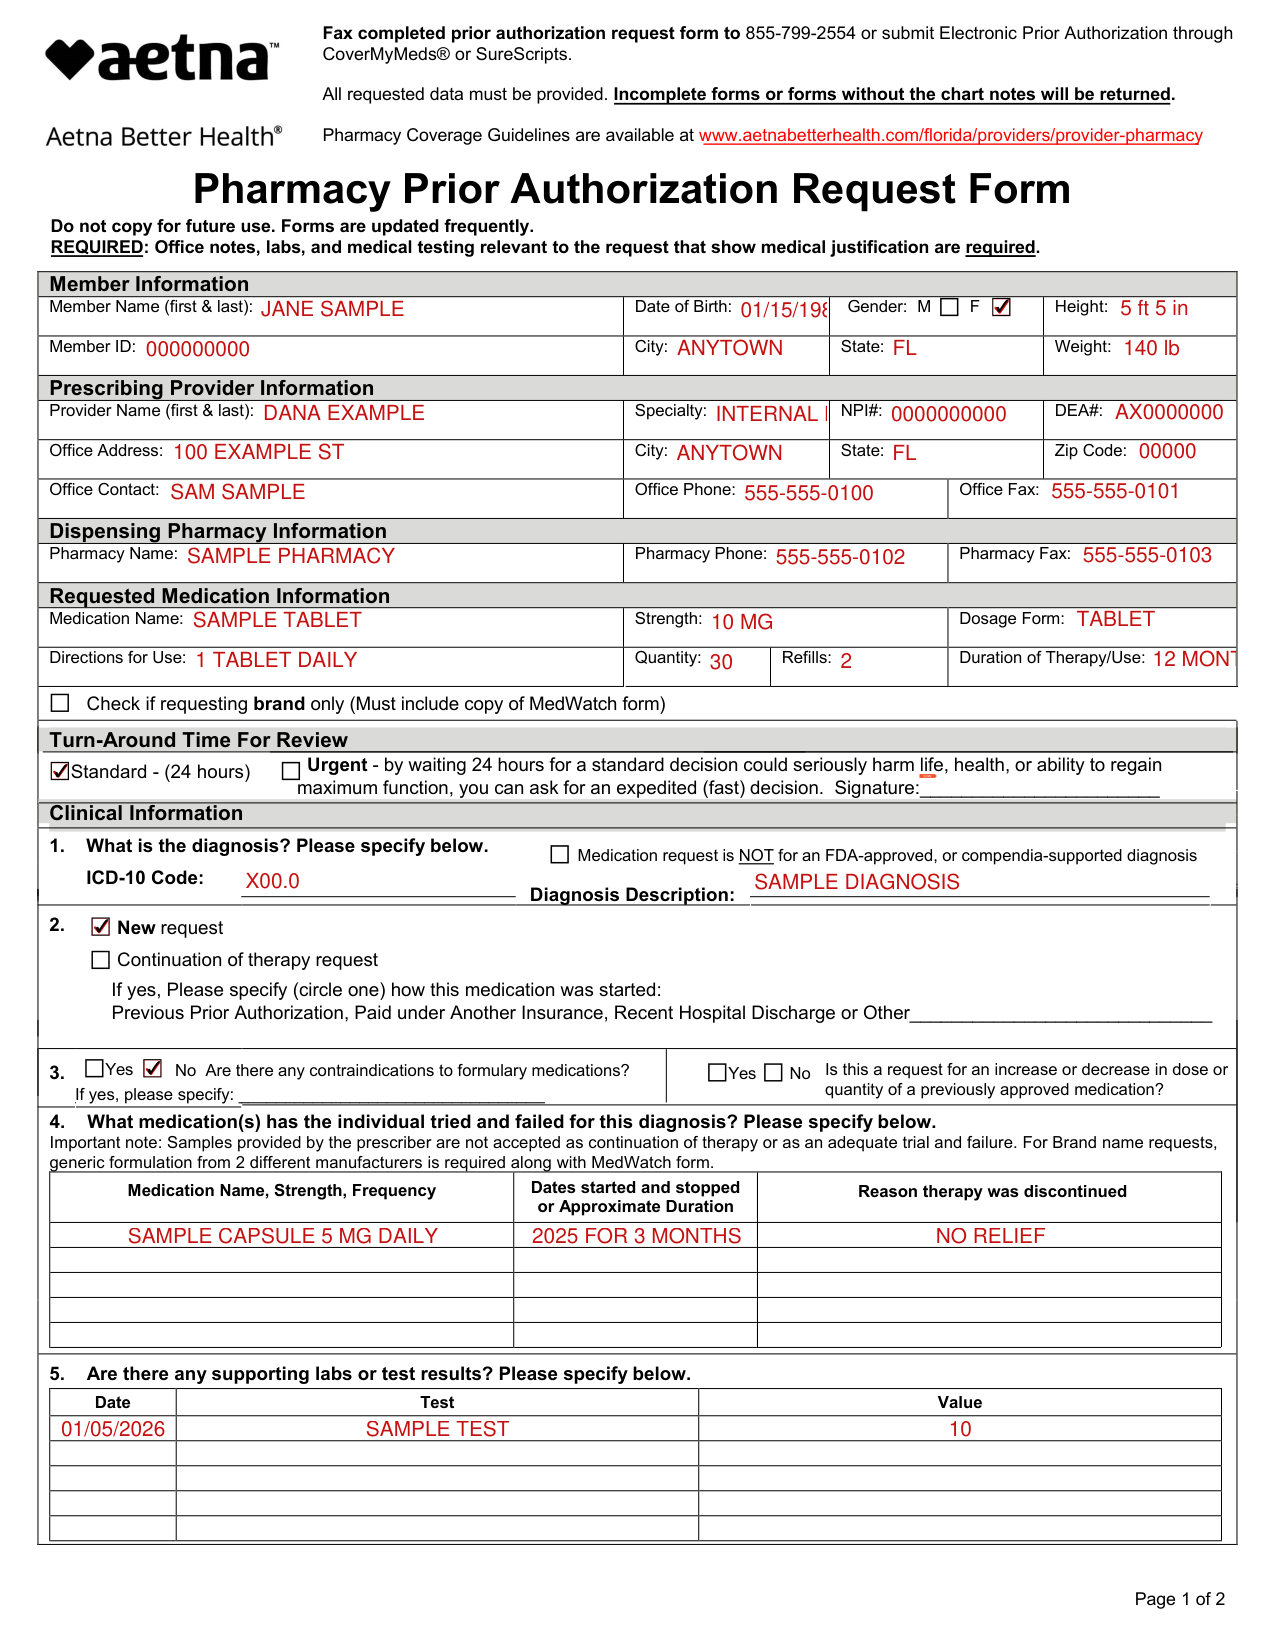
How to fill out Pharmacy Prior Authorization Request Form, box by box
Member Information
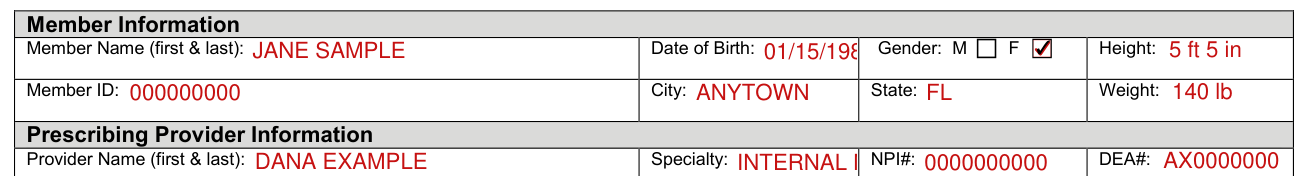
Under Member Information, enter Member Name (first & last), Date of Birth, Gender, Height, Member ID, City, State and Weight.
Prescribing Provider Information
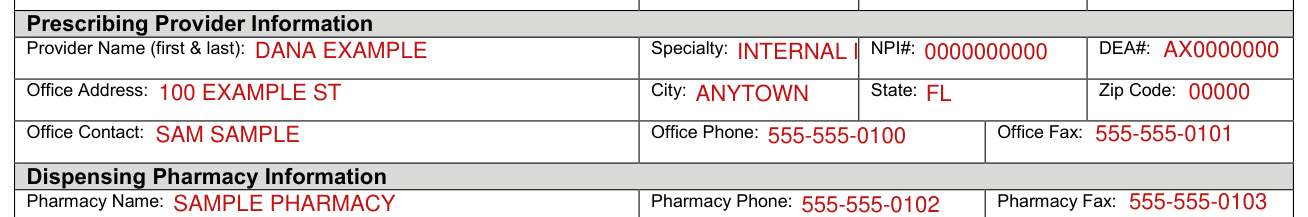
Under Prescribing Provider Information, enter Provider Name (first & last), Specialty, NPI# and DEA#, then Office Address, City, State, Zip Code, Office Contact, Office Phone and Office Fax.
Dispensing Pharmacy Information

Under Dispensing Pharmacy Information, enter Pharmacy Name, Pharmacy Phone and Pharmacy Fax.
Requested Medication Information
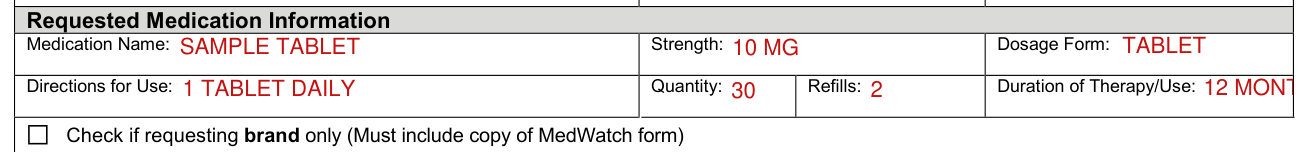
Under Requested Medication Information, enter Medication Name, Strength, Dosage Form, Directions for Use, Quantity, Refills and Duration of Therapy/Use.
Check if requesting brand only (Must include copy of MedWatch form).
Turn-Around Time For Review

Under Turn-Around Time For Review, mark Standard - (24 hours) or Urgent - by waiting 24 hours for a standard decision could seriously harm life, health, or ability to regain maximum function, you can ask for an expedited (fast) decision. Signature line.
What is the diagnosis

For 1. What is the diagnosis? Enter the ICD-10 Code and the Diagnosis Description. Check Medication request is NOT for an FDA-approved, or compendia-supported diagnosis if it applies.
New request or Continuation of therapy request

2. mark New request or Continuation of therapy request. For Continuation of therapy request: If yes, Please specify (circle one) how this medication was started: Previous Prior Authorization, Paid under Another Insurance, Recent Hospital Discharge or Other.
Contraindications to formulary medications

3. Are there any contraindications to formulary medications? If yes, please specify.
Is this a request for an increase or decrease in dose or quantity of a previously approved medication? Mark Yes or No.
Tried and failed medications

4. What medication(s) has the individual tried and failed for this diagnosis? Important note: Samples provided by the prescriber are not accepted as continuation of therapy or as an adequate trial and failure. For Brand name requests, generic formulation from 2 different manufacturers is required along with MedWatch form. Enter Medication Name, Strength, Frequency, Dates started and stopped or Approximate Duration, and Reason therapy was discontinued.
Supporting labs or test results
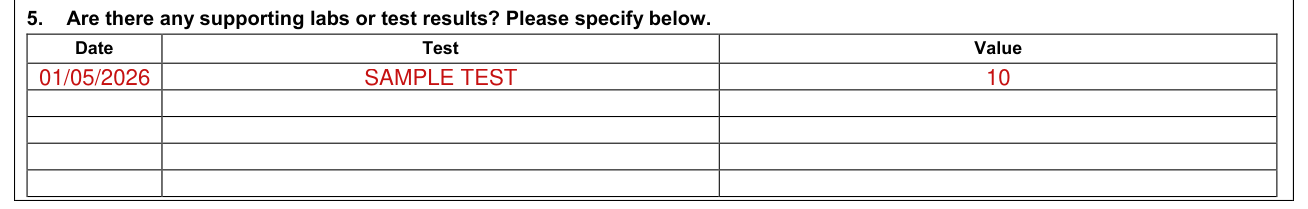
For 5. Are there any supporting labs or test results? Enter Date, Test and Value.
Prescribing Provider's Signature

Prescribing Provider's Signature and Date.
More rules for Pharmacy Prior Authorization Request Form
All requested data must be provided. Incomplete forms or forms without the chart notes will be returned.
Do not copy for future use. Forms are updated frequently. REQUIRED: Office notes, labs, and medical testing relevant to the request that show medical justification are required.
6. Is there any additional information the prescribing provider feels is important to this review? Please specify or submit medical records. For example, explain the negative impact on medical condition, safety issue, reason formulary agent is not suitable to a specific medical condition, expected adverse clinical outcome from use of formulary agent, or reason different dosage form or dose is needed.
7. Is request for a patient that is on an insulin pump? Yes No Make and Model: Note: One Touch products are formulary.
Some medications may require completion of a drug-specific request form. Please refer to plan website at www.aetnabetterhealth.com/florida/providers/provider-pharmacy for drug-specific criteria forms.
Standard turnaround time is 24 hours. You can call to check the status of a request. Medicaid: 800-441-5501 Florida Healthy Kids: 844-528-5815
Common questions about Pharmacy Prior Authorization Request Form
Where do I file it?
Fax completed prior authorization request form to 855-799-2554 or submit Electronic Prior Authorization through Covermymeds® or Surescripts.
Sources
[1] Pharmacy Prior Authorization Request Form, Aetna Better Health of Florida (the served file; no issuer file found) (the Official source link on this page).