

Maryland Medicaid Antipsychotic Prior Authorization Form at a glance
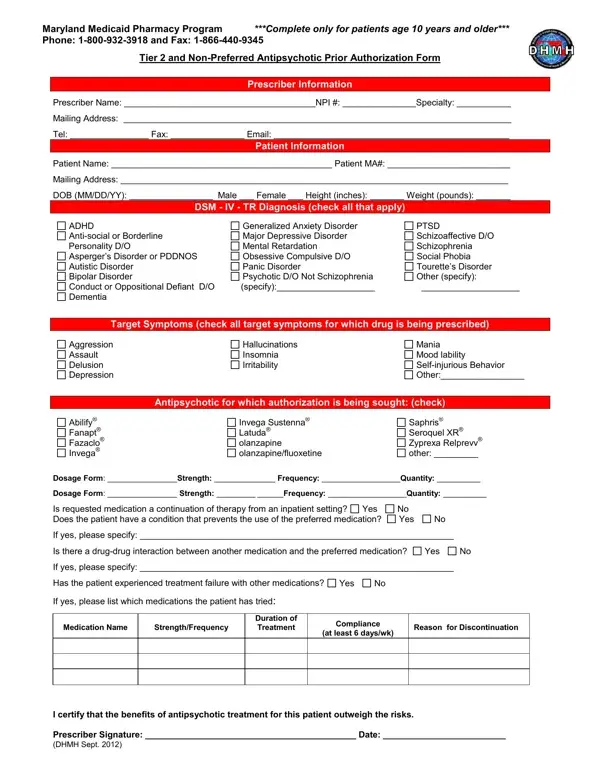
What it is: This is the Maryland Medicaid Antipsychotic Prior Authorization Form.
Who signs: Sign at Prescriber Signature and enter the Date (MM/DD/YYYY).
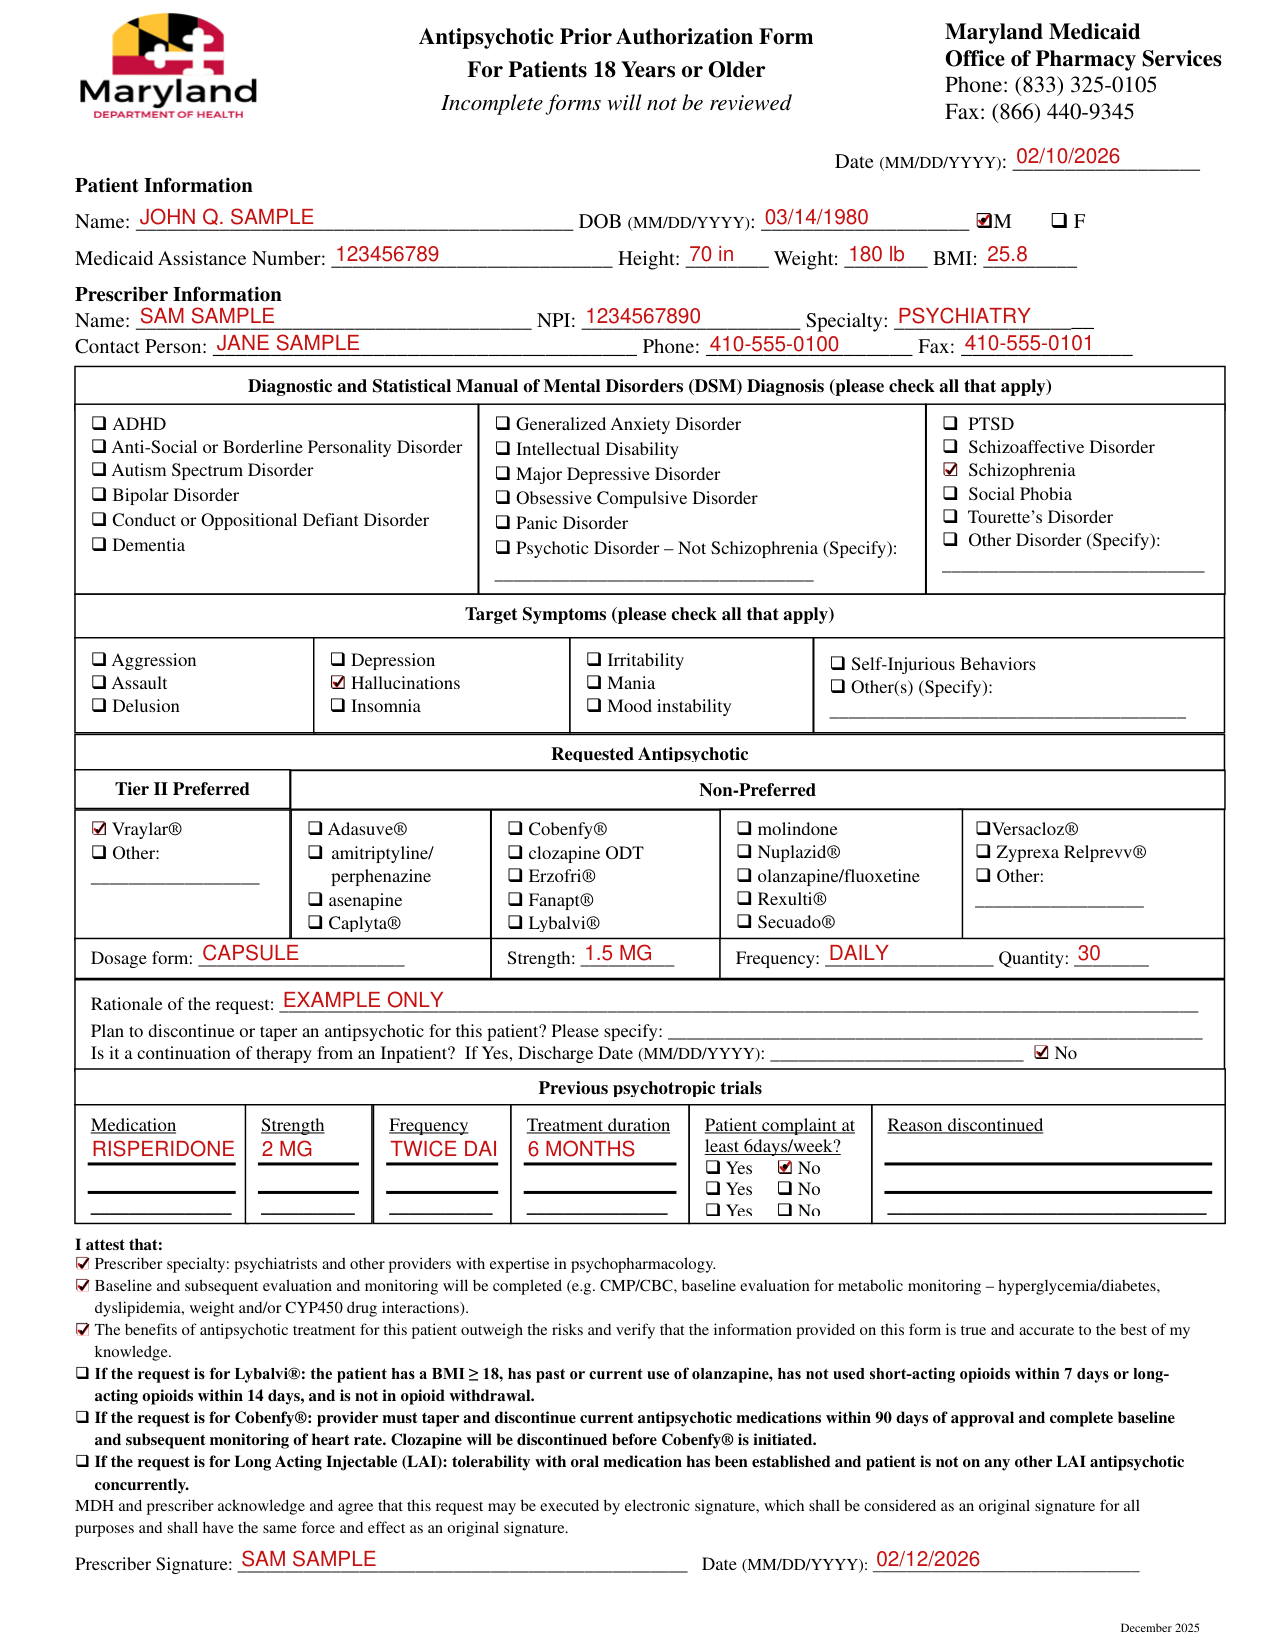
A filled-in Maryland Medicaid Antipsychotic Prior Authorization Form example: a prescriber requests Vraylar
How to fill out Maryland Medicaid Antipsychotic Prior Authorization Form, box by box
Patient Information

Enter the Date (MM/DD/YYYY) under Patient Information.
Enter the Name and DOB (MM/DD/YYYY), and mark M or F.
Enter the Medicaid Assistance Number, Height, Weight and BMI.
Prescriber Information

Under Prescriber Information, enter Name, NPI, Specialty, Contact Person, Phone and Fax.
DSM Diagnosis
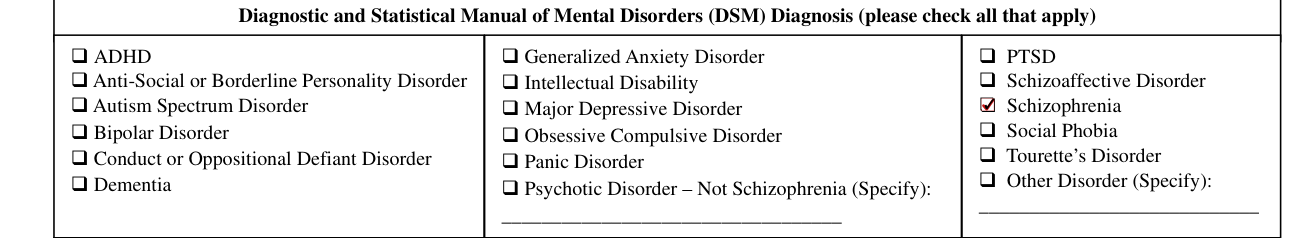
Check all that apply under the Diagnostic and Statistical Manual of Mental Disorders (DSM) Diagnosis.
Check Other Disorder (Specify) or Psychotic Disorder - Not Schizophrenia (Specify) and write it after (Specify).
Target Symptoms

Check all that apply under Target Symptoms.
Check Other(s) (Specify) and write it after (Specify).
Requested Antipsychotic
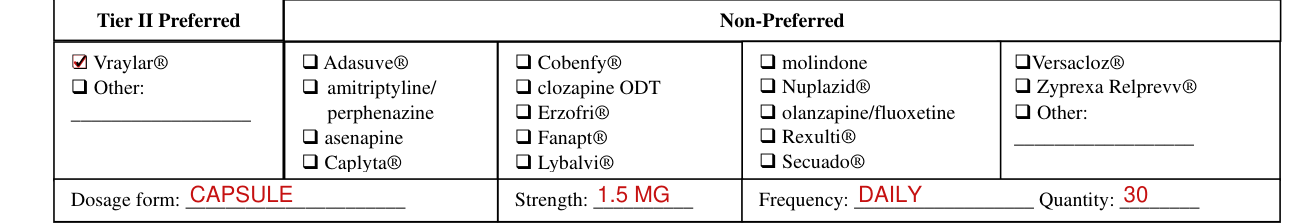
Under Requested Antipsychotic, check one under Tier II Preferred or Non-Preferred.
Enter the Dosage form, Strength, Frequency and Quantity.
Rationale of the request

Enter the Rationale of the request, specify a Plan to discontinue or taper an antipsychotic for this patient, and for Is it a continuation of therapy from an Inpatient? mark Yes or No; if Yes, enter the Discharge Date (MM/DD/YYYY).
Previous psychotropic trials
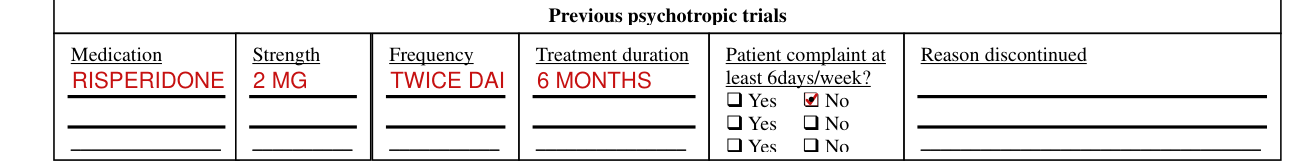
Under Previous psychotropic trials, enter Medication, Strength, Frequency and Treatment duration, and mark Yes or No for Patient complaint at least 6days/week?
Enter the Reason discontinued.
I attest that
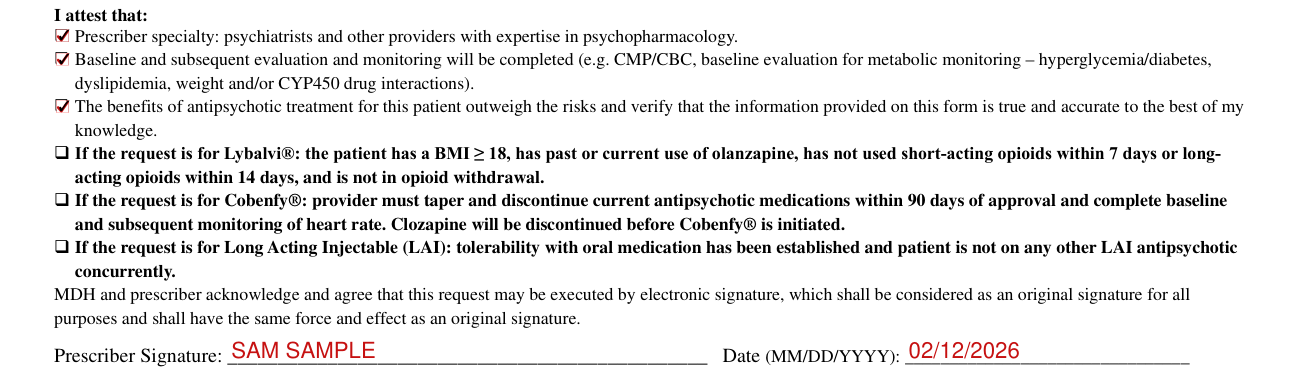
Under I attest that, each line has its own check box. Prescriber specialty: psychiatrists and other providers with expertise in psychopharmacology. Baseline and subsequent evaluation and monitoring will be completed (e.g. CMP/CBC, baseline evaluation for metabolic monitoring - hyperglycemia/diabetes, dyslipidemia, weight and/or CYP450 drug interactions). The benefits of antipsychotic treatment for this patient outweigh the risks and verify that the information provided on this form is true and accurate to the best of my knowledge. If the request is for Lybalvi®: the patient has a BMI ≥ 18, has past or current use of olanzapine, has not used short-acting opioids within 7 days or long-acting opioids within 14 days, and is not in opioid withdrawal. If the request is for Cobenfy®: provider must taper and discontinue current antipsychotic medications within 90 days of approval and complete baseline and subsequent monitoring of heart rate. Clozapine will be discontinued before Cobenfy® is initiated. If the request is for Long Acting Injectable (LAI): tolerability with oral medication has been established and patient is not on any other LAI antipsychotic concurrently. MDH and prescriber acknowledge and agree that this request may be executed by electronic signature, which shall be considered as an original signature for all purposes and shall have the same force and effect as an original signature.
Common questions about Maryland Medicaid Antipsychotic Prior Authorization Form
Where do I file it?
For Patients 18 Years or Older. Incomplete forms will not be reviewed. Office of Pharmacy Services Phone: (833) 325-0105 Fax: (866) 440-9345.
Sources
[1] Maryland Medicaid Antipsychotic Prior Authorization Form (December 2025), Maryland Department of Health (the Official source link on this page).