


CCP Prior Authorization Request Form (F00012) at a glance
What it is: The CCP Prior Authorization Request Form is the form to submit this prior authorization request, by the Provider or by a Prior Authorization Request Submitter specifically authorized by the Provider.
Who signs: Sign the Signature of requesting physician or allowed practitioner line and enter the Date.
A filled-in CCP Prior Authorization Request Form (F00012) example: a provider requests an ABA evaluation
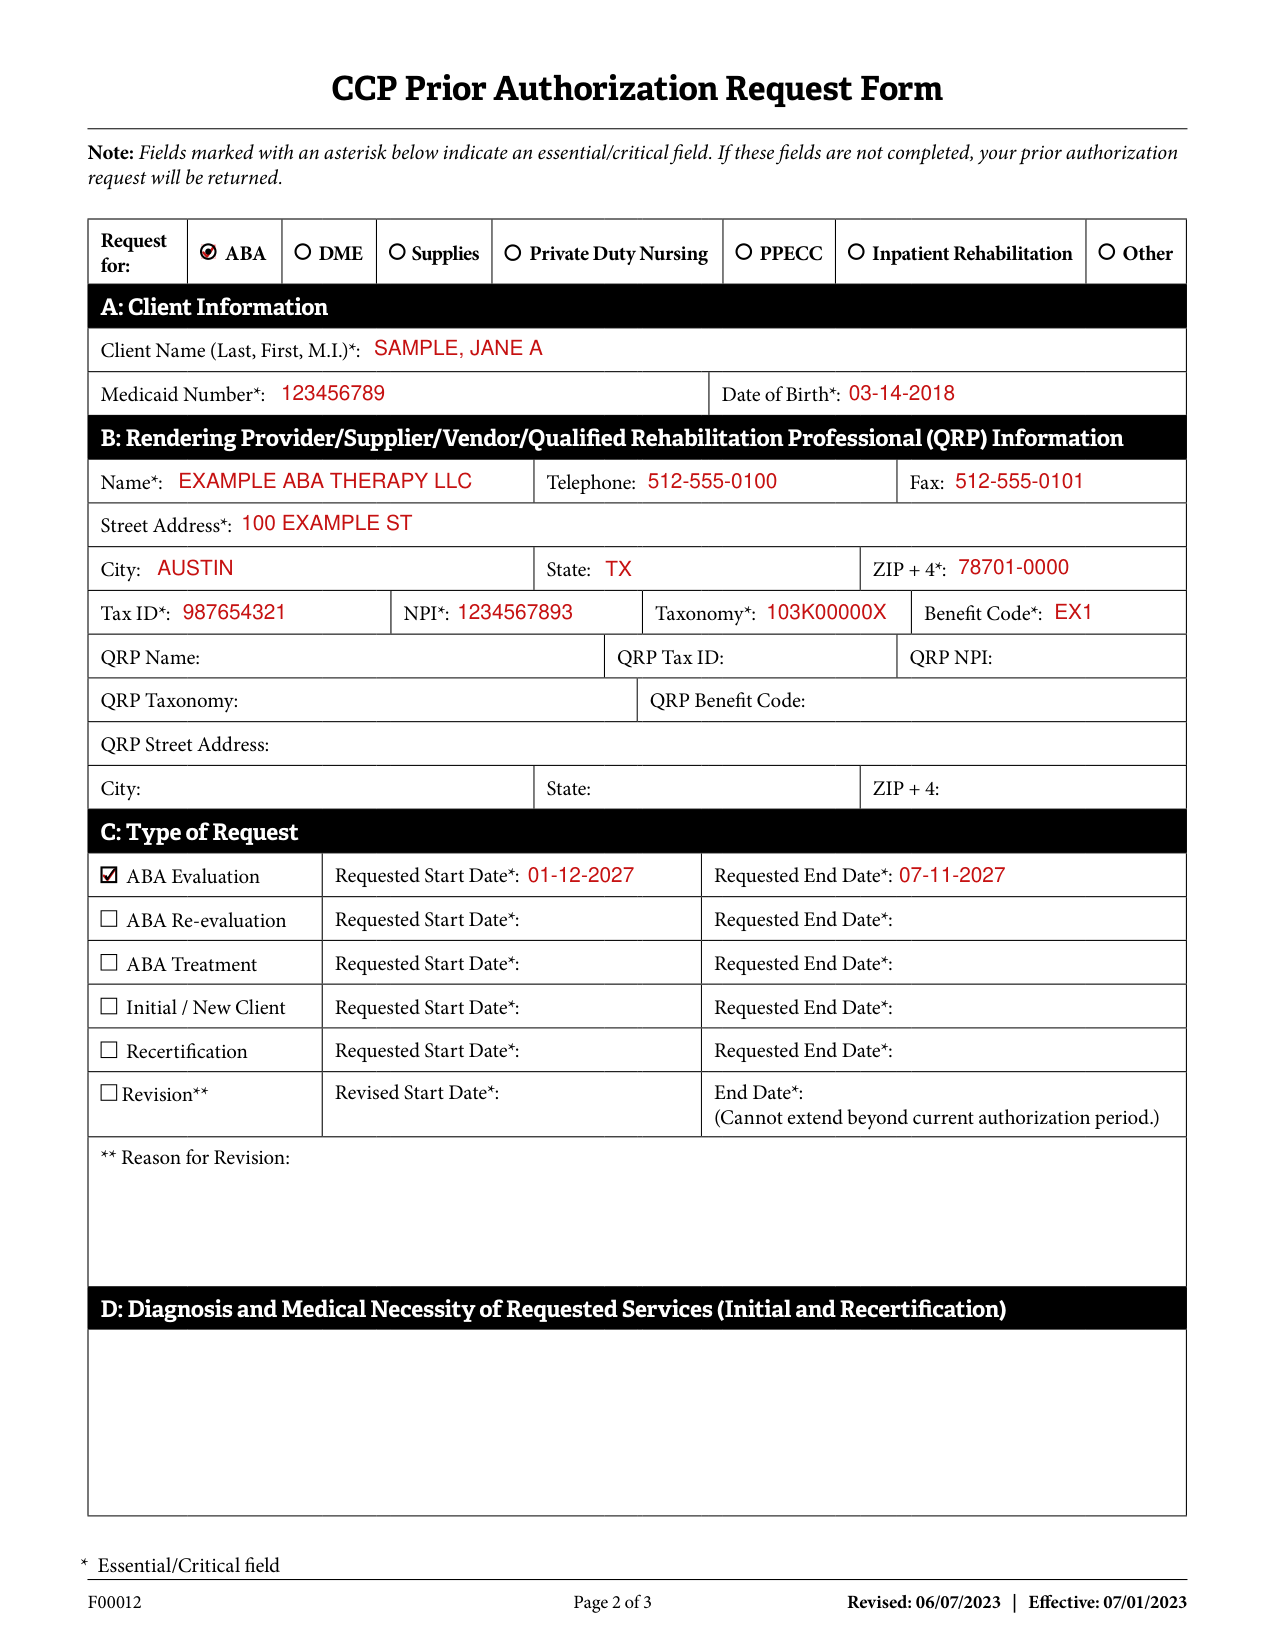
How to fill out CCP Prior Authorization Request Form (F00012), box by box
Request for

Under Request for: ABA, DME Supplies, Private Duty Nursing, PPECC, Inpatient Rehabilitation or Other.
A: Client Information

In A: Client Information, enter the Client Name (Last, First, M.I.), the Medicaid Number and the Date of Birth.
B: Rendering Provider/Supplier/Vendor/Qualified Rehabilitation Professional (QRP) Information
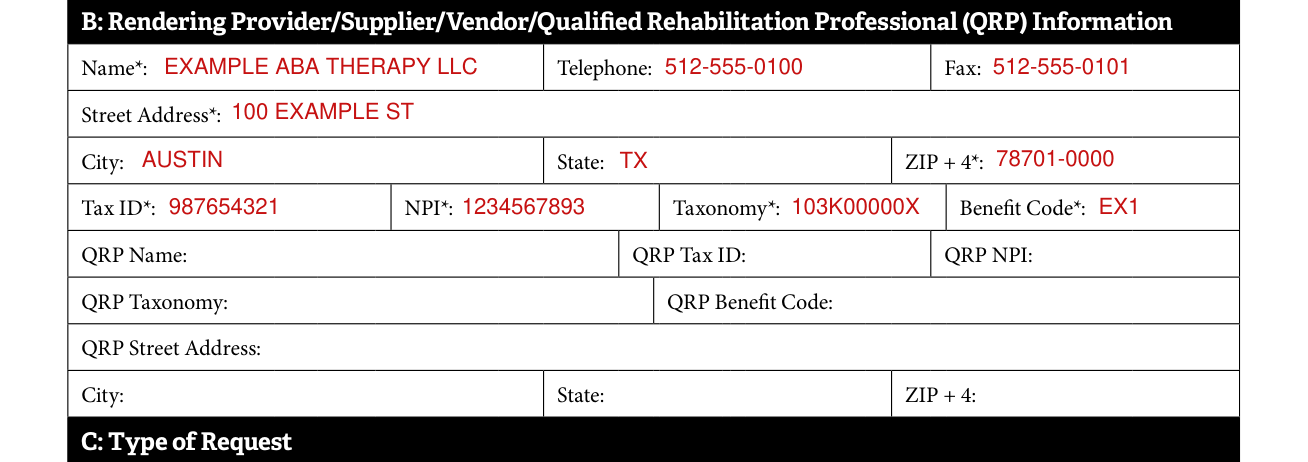
In B, enter the Rendering Provider Name, Telephone, Fax, Street Address, City, State, ZIP + 4, Tax ID, NPI, Taxonomy and Benefit Code.
Enter the QRP Name, QRP Tax ID, QRP NPI, QRP Taxonomy, QRP Benefit Code, QRP Street Address, City, State and ZIP + 4.
C: Type of Request
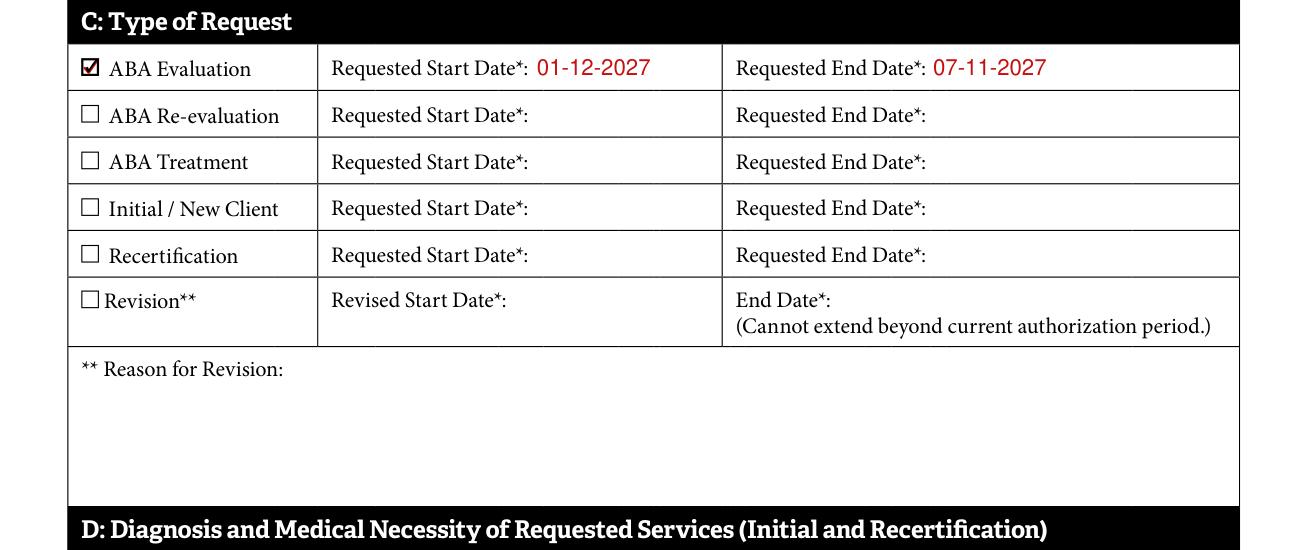
For ABA Evaluation, ABA Re-evaluation or ABA Treatment, enter the Requested Start Date and the Requested End Date.
For Initial / New Client or Recertification, enter the Requested Start Date and the Requested End Date.
Only for Revision, enter the Revised Start Date and End Date (Cannot extend beyond current authorization period.) and the Reason for Revision.
D: Diagnosis and Medical Necessity of Requested Services (Initial and Recertification)

D: Diagnosis and Medical Necessity of Requested Services (Initial and Recertification).
E: Dates of Service and HCPCS Code
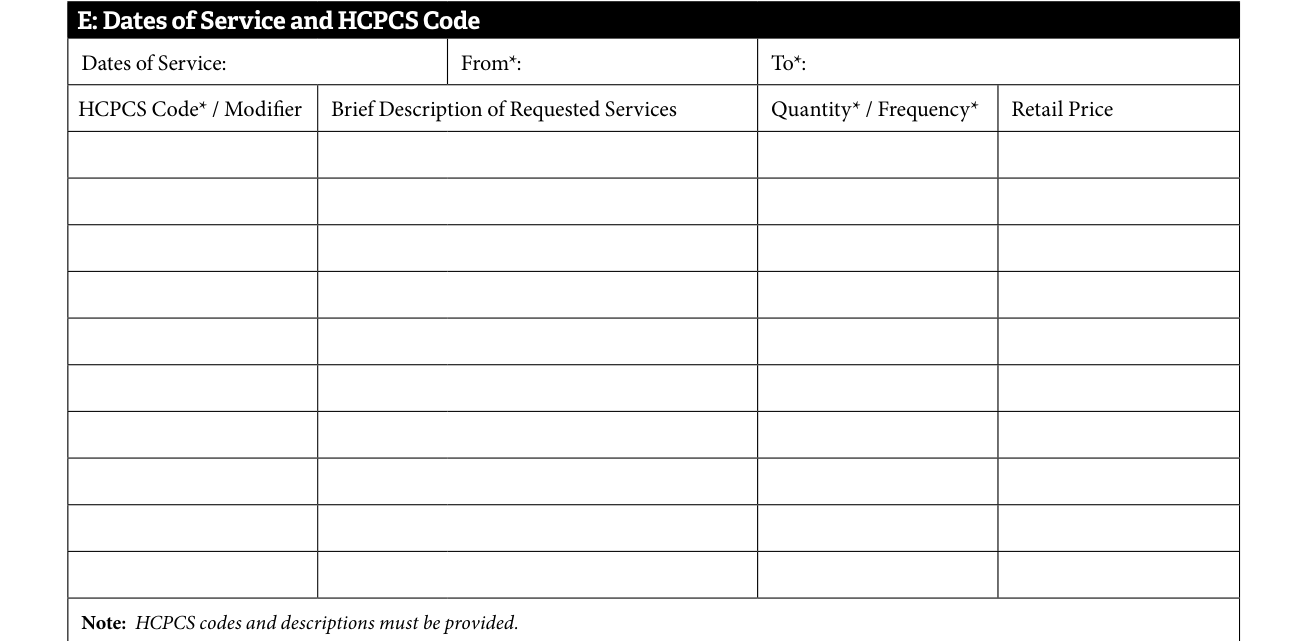
In E, enter the Dates of Service From and To.
For each service, enter the HCPCS Code / Modifier, the Brief Description of Requested Services, the Quantity / Frequency and the Retail Price. HCPCS codes and descriptions must be provided.
F: Primary Practitioner's Certifications (To be completed by the requesting physician or allowed practitioner)

By requesting ABA evaluation or treatment, you certify: the client is under 21 years of age AND the client has a diagnosis of Autism Spectrum Disorder AND ABA services are or may be clinically indicated.
By requesting the identified DME and/or medical supplies, you certify: the client is under 21 years of age AND the prescribed items are appropriate and can safely be used by the client when used as prescribed.
By requesting Private Duty Nursing, you certify: the client is under 21 years of age AND the client's medical condition is sufficiently stable to permit safe delivery of private duty nursing as described in the plan of care.
By requesting PPECC services, you certify: the client is under 21 years of age AND the client's medical condition is sufficiently stable to permit safe delivery of PPECC services as described in the PPECC plan of care.
Sign the Signature of requesting physician or allowed practitioner line and enter the Date.
Enter the Printed or typed name of physician or allowed practitioner, the Primary Practitioner NPI and the License No.
Signatures from chiropractors and doctors of philosophy (PhDs) will not be accepted. Signature stamps and date stamps are not acceptable.
More rules for CCP Prior Authorization Request Form (F00012)
If any portion of this form is incomplete, it may result in your prior authorization request being pended for additional information.
Fields marked with an asterisk indicate an essential/critical field. If these fields are not completed, your prior authorization request will be returned.
Prior authorization is a condition of reimbursement and is not a guarantee of payment.
Any false claims, statements or documents, concealment of a material fact, or omitting relevant or pertinent information may constitute fraud and may be prosecuted under applicable federal and/or State laws. Failure to provide true and accurate information, omit information, or provide notice of changes to the information previously provided may result in termination of the provider's Medicaid enrollment and/or personal exclusion from Texas Medicaid.
Certified Nurse Midwife (CNM), Clinical Nurse Specialist (CNS), Nurse Practitioner (NP) and Physician Assistant (PA) providers may sign on behalf of the physician for Applied Behavior Analysis (ABA) services, Private Duty Nursing, Physical, Occupational, and Speech Therapy Services when the physician delegates this authority.
Common questions about CCP Prior Authorization Request Form (F00012)
Where do I file it?
Submit your prior authorization using TMHP's PA on the Portal and receive request decisions more quickly than faxed requests. Fax requests must be scanned and data entered before the PA Department receives them, which can take up to 24 hours. To access PA on the Portal, go to www.tmhp.com, select “Prior Authorization” from the Topics drop-down menu, click the PA on the Portal button and enter your TMHP Portal Account user name and password. To submit by fax, send to 512-514-4212.
Is there a penalty?
The Provider and Prior Authorization Request Submitter certify and affirm under penalty of perjury that the information supplied on the prior authorization form is true, correct, complete and accurate; does not contain any misrepresentations; and does not fail to include any information that might be deemed relevant or pertinent to the decision on which a prior authorization for payment would be made.
What am I certifying when I sign?
The Provider and Prior Authorization Request Submitter certify, affirm and agree that by checking the Prior Authorization Certification box they have read and understand the Prior Authorization Agreement requirements as stated in the relevant Texas Medicaid Provider Procedures Manual and they agree and consent to the Certification and to the Texas Medicaid & Healthcare Partnership (TMHP) Terms and Conditions.
Sources
[1] Form F00012, CCP Prior Authorization Request Form (Revised 06/07/2023), Texas Medicaid & Healthcare Partnership (the Official source link on this page).