How to Fill Out Inpatient Prior Authorization Fax Form

Inpatient Prior Authorization Fax Form at a glance

What it is: Inpatient Prior Authorization Fax Form.

Who signs: Urgent requests must be signed by the requesting physician to receive priority.

A filled-in Inpatient Prior Authorization Fax Form example: a clinic fills out page 1
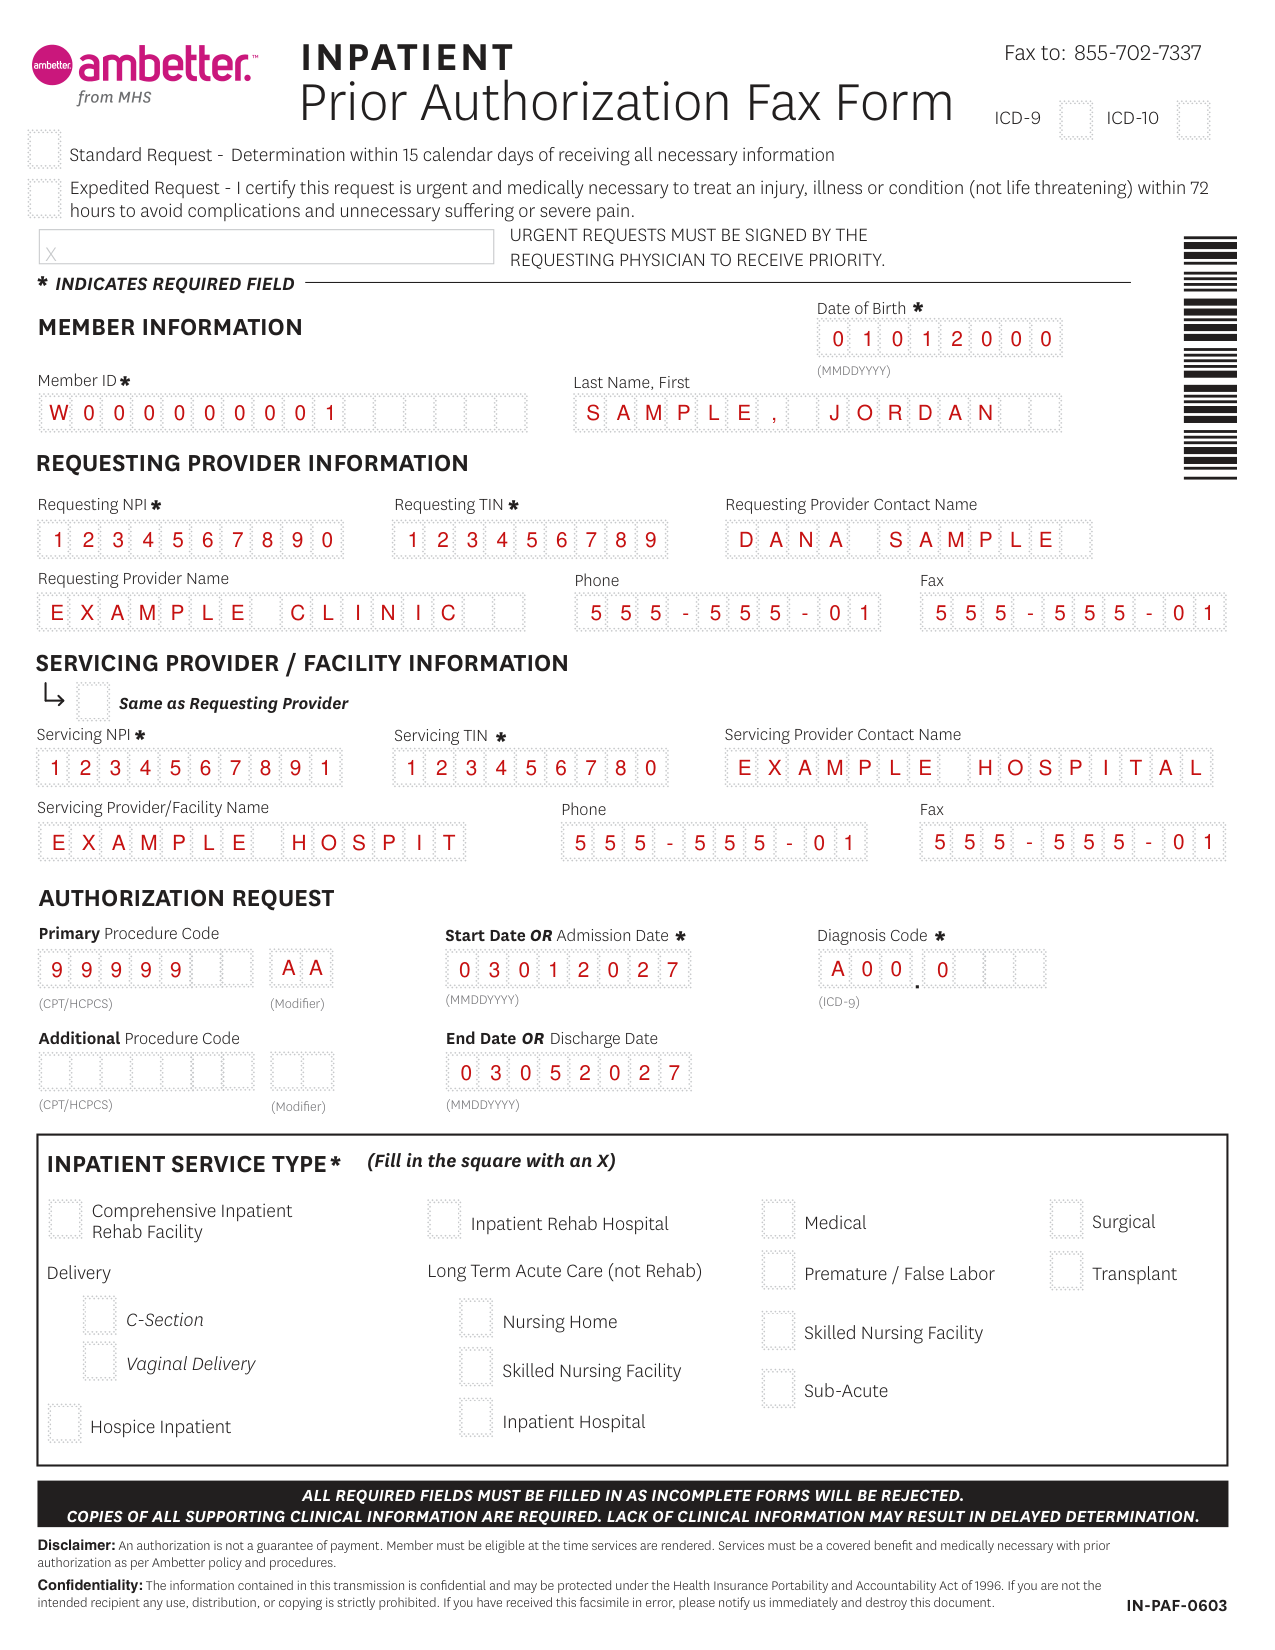
Inpatient Prior Authorization Fax Form example filled out, example: a clinic fills out page 1
Dana Sample, a clinic nurse, fills out the inpatient prior authorization form. Servicing provider / facility information is filled in separately. The picture shows page 1 only, and none of its entries is real.

How to fill out Inpatient Prior Authorization Fax Form, box by box

Standard or expedited request

Standard Request - Determination within 15 calendar days of receiving all necessary information.

Expedited Request - I certify this request is urgent and medically necessary to treat an injury, illness or condition (not life threatening) within 72 hours to avoid complications and unnecessary sufering or severe pain.

Member information

Inpatient Prior Authorization Fax Form example filled out, member information

Under MEMBER INFORMATION, enter Last Name, First, Member ID * and Date of Birth (MMDDYYYY).

INDICATES REQUIRED FIELD.

Requesting provider information

Inpatient Prior Authorization Fax Form example filled out, requesting provider information

Under REQUESTING PROVIDER INFORMATION, enter Requesting NPI *, Requesting TIN *, Requesting Provider Contact Name, Requesting Provider Name, Fax and Phone.

Servicing provider / facility information

Inpatient Prior Authorization Fax Form example filled out, servicing provider / facility information

Under SERVICING PROVIDER / FACILITY INFORMATION, mark Same as Requesting Provider, or enter Servicing NPI *, Servicing Provider Contact Name, Servicing TIN *, Servicing Provider/Facility Name, Fax and Phone.

Authorization request
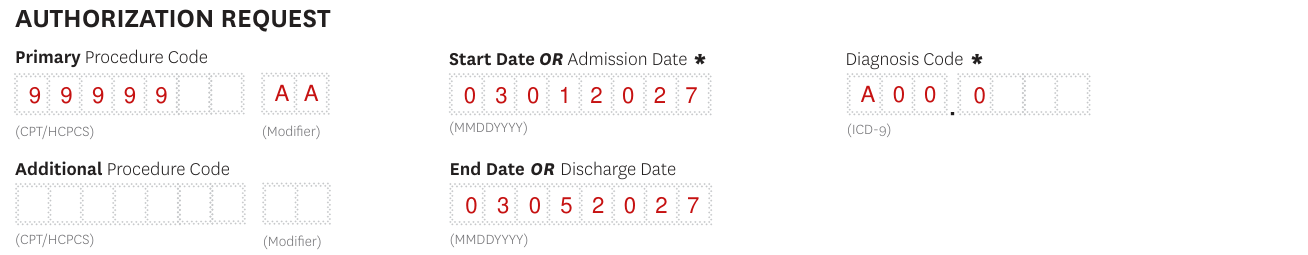
Inpatient Prior Authorization Fax Form example filled out, authorization request

Under AUTHORIZATION REQUEST, enter the Start Date OR Admission Date * and the End Date OR Discharge Date (MMDDYYYY).

Enter the Diagnosis Code *, and mark ICD-9 or ICD-10.

Enter the Primary Procedure Code and the Additional Procedure Code (CPT/HCPCS), each with its (Modiier).

Inpatient service type

INPATIENT SERVICE TYPE* (Fill in the square with an X): Surgical, Medical, Delivery, Transplant, C-Section, Vaginal Delivery, Premature / False Labor, Comprehensive Inpatient Rehab Facility, Inpatient Rehab Hospital, Long Term Acute Care (not Rehab), Nursing Home, Skilled Nursing Facility, Sub-Acute, Inpatient Hospital, Hospice Inpatient.

More rules for Inpatient Prior Authorization Fax Form

All required fields must be filled in as incomplete forms will be rejected. Copies of all supporting clinical information are required. Lack of clinical information may result in delayed determination.

Disclaimer: An authorization is not a guarantee of payment. Member must be eligible at the time services are rendered. Services must be a covered beneit and medically necessary with prior authorization as per Ambetter policy and procedures.

Common questions about Inpatient Prior Authorization Fax Form

Where do I file it?

Fax to: 855-702-7337.

Sources

[1] Inpatient Prior Authorization Fax Form (IN-PAF-0603), Ambetter (the Official source link on this page).

Ambetter Inpatient Prior Authorization Form PDF Details

The Ambetter Inpatient Prior Authorization form is a crucial document in the healthcare process, ensuring that inpatient services provided to members are approved and in line with Ambetter's policies and procedures. It serves a dual purpose, facilitating both standard and expedited requests for inpatient treatment. For standard requests, a determination is made within 15 calendar days after receiving all the necessary information. Expedited requests, which must be signed by the requesting physician, aim for a 72-hour turnaround to prevent complications, unnecessary suffering, or severe pain for conditions that, while urgent, are not life-threatening. The form requires comprehensive information, including member details, provider information, and specifics about the requested inpatient service, such as procedure codes and diagnosis. It emphasizes the importance of completing all required fields and providing supporting clinical information to avoid delays in the determination process. Notably, an authorization does not guarantee payment as it is subject to the member's eligibility and the medical necessity of the services at the time they are rendered. The form also underscores the confidentiality of the information contained within, protected under the Health Insurance Portability and Accountability Act of 1996. Incomplete submissions or lack of necessary clinical data can lead to a rejected request, underscoring the importance of meticulousness in filling out the form.

Providers who handle related authorization requests may also need the Ambetter Outpatient Prior Authorization form for ambulatory services, the Care 1st Arizona Prior Authorization form for managed care plans, or the Antipsychotic Prior Authorization form for behavioral health cases.

QuestionAnswer
Form NameAmbetter Inpatient Prior Authorization Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesambetter illinois prior authorization form, ambetter inpatient prior pdf, ambetter inpatient prior form, ambetter health insurance