

Form AN-PAF-6309 at a glance
What it is: Arizona Care1st Medicaid Outpatient Authorization, AN-PAF-6309.
Where and when to file: Physical Health Fax to: 833-618-1979. Behavioral Health Requests Fax to: 833-592-1301. Biopharmacy Fax to: 833-417-0447.
A filled-in Form AN-PAF-6309 example: a clinic requests physical therapy
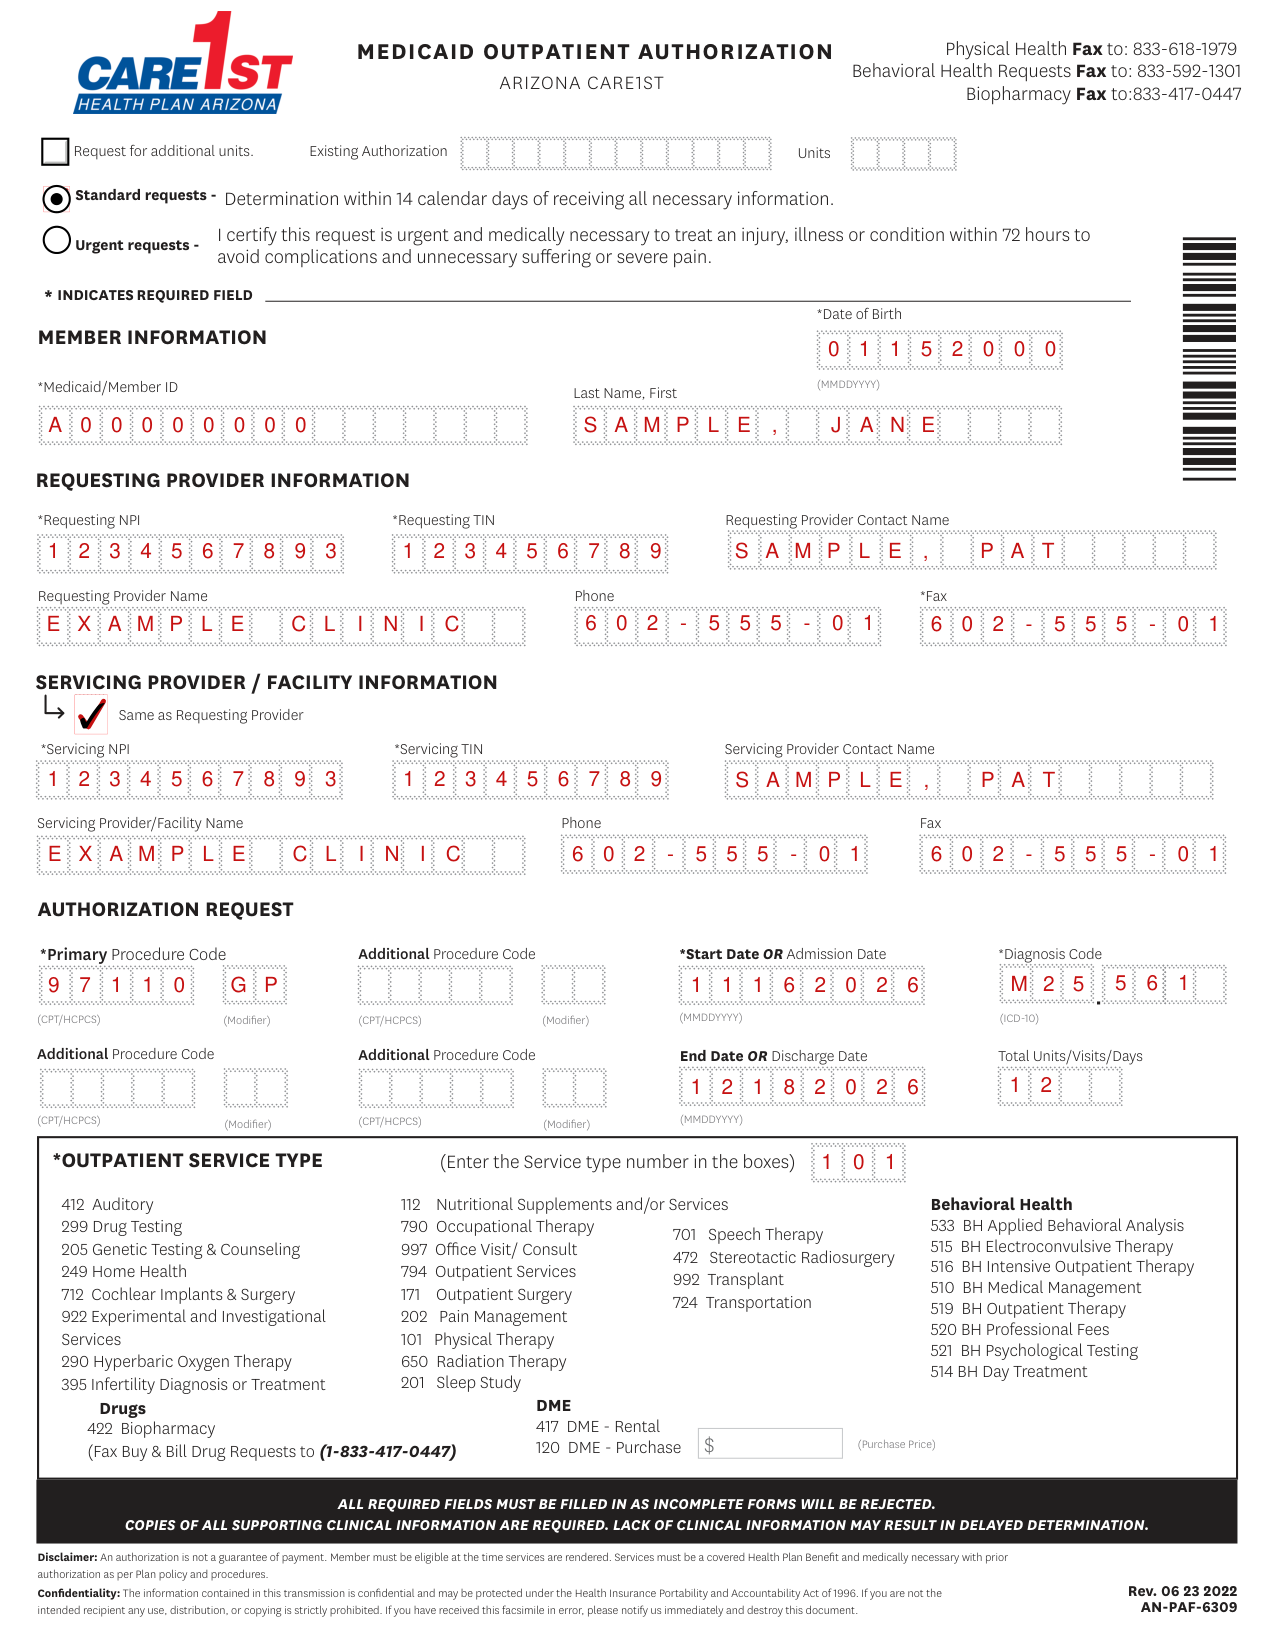
How to fill out Form AN-PAF-6309, box by box
Standard requests or urgent requests

Standard requests: determination within 14 calendar days of receiving all necessary information.
Urgent requests: "I certify this request is urgent and medically necessary to treat an injury, illness or condition within 72 hours to avoid complications and unnecessary suffering or severe pain."
Request for additional units

For a Request for additional units, mark Request for additional units and enter the Existing Authorization and the Units.
Member information

Under MEMBER INFORMATION, enter the Date of Birth as MMDDYYYY. The Date of Birth is marked with a *, as is the Fax of the Requesting Provider.
Enter the Medicaid/Member ID. The Medicaid/Member ID is marked with a *, as is the Fax of the Requesting Provider.
Enter the Last Name, First.
Requesting provider information

Under REQUESTING PROVIDER INFORMATION, enter the Requesting NPI, the Requesting TIN and the Requesting Provider Contact Name.
Enter the Requesting Provider Name, the Fax and the Phone.
Servicing provider / facility information
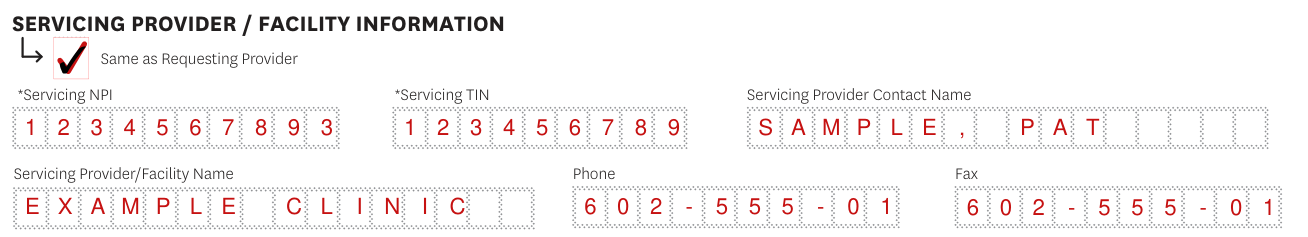
Under SERVICING PROVIDER / FACILITY INFORMATION, if the servicing provider is the Same as Requesting Provider, mark Same as Requesting Provider.
Enter the Servicing NPI, the Servicing Provider Contact Name and the Servicing TIN. The Servicing NPI is marked with a *, as is the Fax of the Requesting Provider.
Enter the Servicing Provider/Facility Name, the Fax and the Phone.
Primary Procedure Code

Under AUTHORIZATION REQUEST, enter the Primary Procedure Code (CPT/HCPCS) and the (Modifier). The Primary Procedure Code is marked with a *, as is the Fax of the Requesting Provider.
Additional Procedure Code
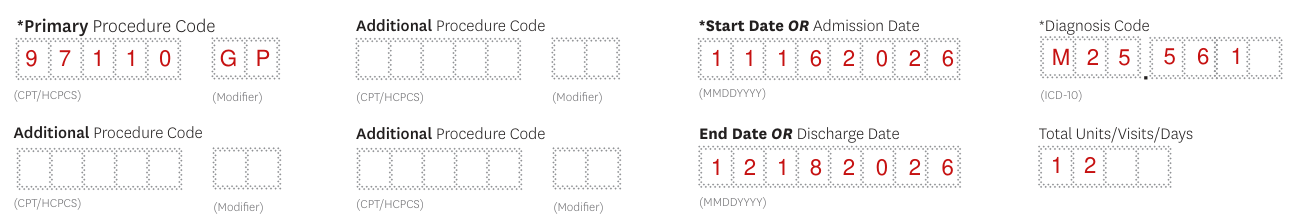
If you add another procedure, enter the Additional Procedure Code (CPT/HCPCS) and the (Modifier).
Dates, Diagnosis Code and Total Units/Visits/Days
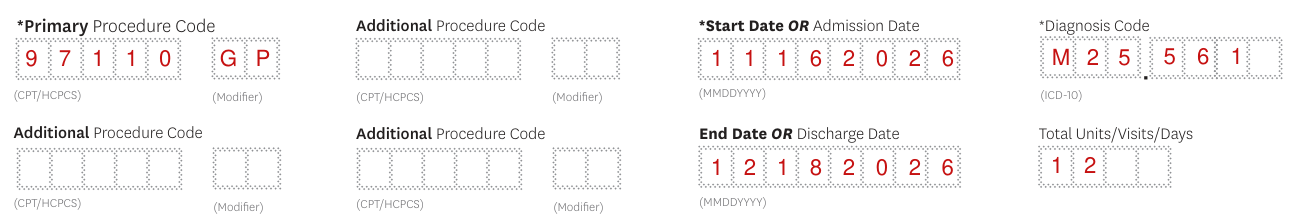
Enter the Start Date OR Admission Date as MMDDYYYY. The Start Date OR Admission Date is marked with a *, as is the Fax of the Requesting Provider.
Enter the End Date OR Discharge Date as MMDDYYYY.
Enter the Diagnosis Code (ICD-10). The Diagnosis Code is marked with a *, as is the Fax of the Requesting Provider.
Enter the Total Units/Visits/Days.
Outpatient service type and Purchase Price
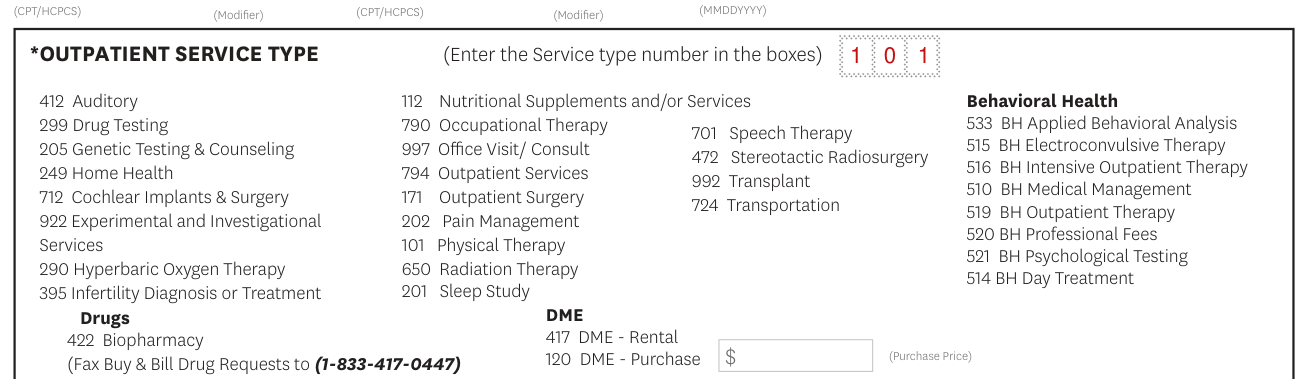
Enter the Service type number in the boxes for the OUTPATIENT SERVICE TYPE. The OUTPATIENT SERVICE TYPE is marked with a *, as is the Fax of the Requesting Provider.
412 Auditory, 299 Drug Testing, 205 Genetic Testing & Counseling, 249 Home Health, 712 Cochlear Implants & Surgery, 922 Experimental and Investigational Services, 290 Hyperbaric Oxygen Therapy, 395 Infertility Diagnosis or Treatment.
112 Nutritional Supplements and/or Services, 790 Occupational Therapy, 997 Office Visit/ Consult, 794 Outpatient Services, 171 Outpatient Surgery, 202 Pain Management, 101 Physical Therapy, 650 Radiation Therapy, 201 Sleep Study. Drugs: 422 Biopharmacy (Fax Buy & Bill Drug Requests to (1-833-417-0447).
Behavioral Health: 533 BH Applied Behavioral Analysis, 515 BH Electroconvulsive Therapy, 516 BH Intensive Outpatient Therapy, 510 BH Medical Management, 519 BH Outpatient Therapy, 520 BH Professional Fees, 521 BH Psychological Testing, 514 BH Day Treatment.
701 Speech Therapy, 472 Stereotactic Radiosurgery, 992 Transplant, 724 Transportation.
DME: 417 DME - Rental, 120 DME - Purchase (Purchase Price).
More rules for Form AN-PAF-6309
All required fields must be filled in as incomplete forms will be rejected. Copies of all supporting clinical information are required. Lack of clinical information may result in delayed determination.
Common questions about Form AN-PAF-6309
Where do I file it?
Physical Health Fax to: 833-618-1979. Behavioral Health Requests Fax to: 833-592-1301. Biopharmacy Fax to: 833-417-0447.
Sources
[1] Form AN-PAF-6309, Medicaid Outpatient Authorization, Arizona Care1st (the Official source link on this page).
