

Medication Prior Authorization Form at a glance
What it is: This is the Medication Prior Authorization Form.
Where and when to file: Fax the completed form to (855) 840-1678.
A filled-in Medication Prior Authorization Form example: a standard request after a generic
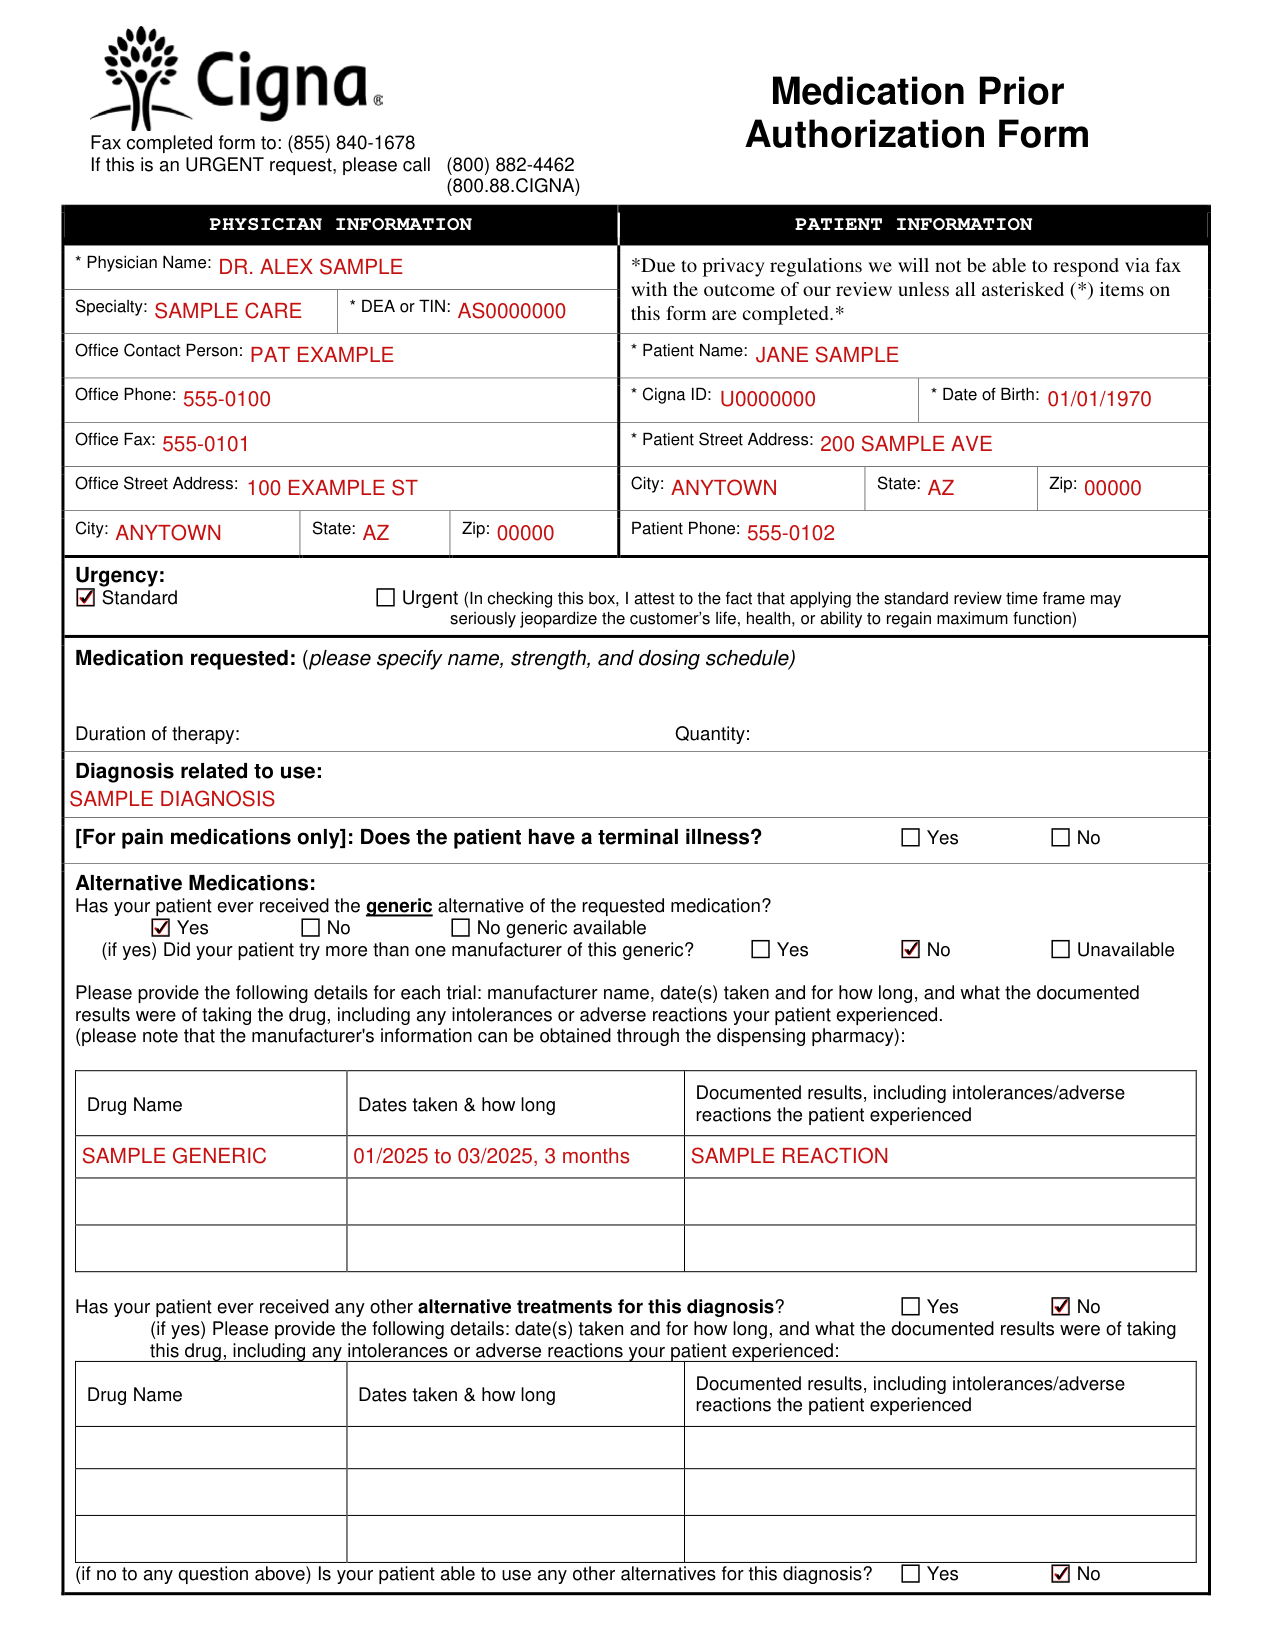
How to fill out Medication Prior Authorization Form, box by box
Physician information and patient information
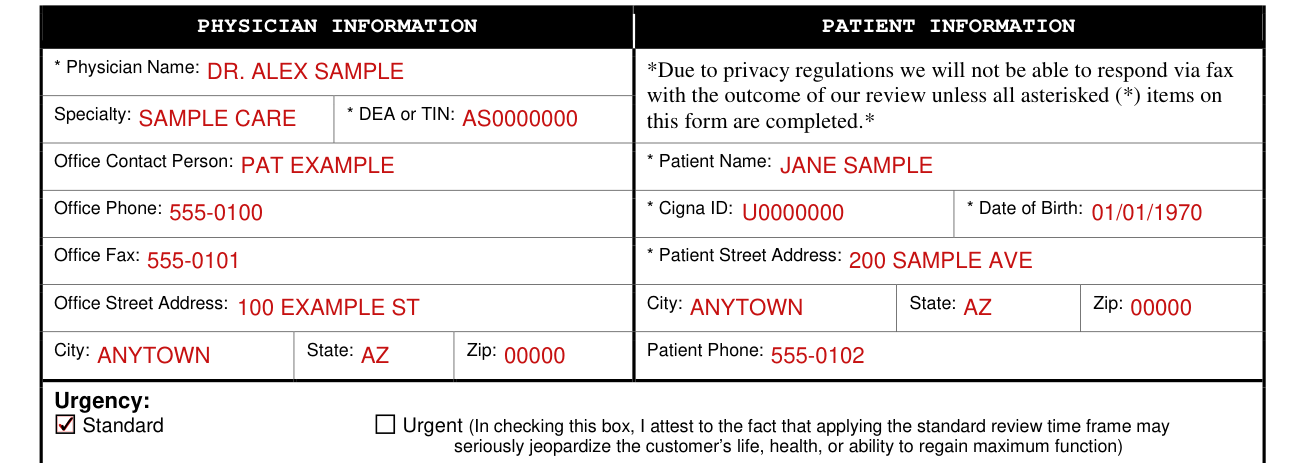
Enter the PHYSICIAN INFORMATION and the PATIENT INFORMATION: Physician Name, Specialty, DEA or TIN, Office Contact Person, Office Phone, Office Fax, Office Street Address, City, State and Zip, then Patient Name, Cigna ID, Date of Birth, Patient Street Address, City, State and Zip, and Patient Phone. Due to privacy regulations Cigna will not be able to respond via fax with the outcome of the review unless all asterisked (*) items on this form are completed.
Urgency

Urgency: check Standard or Urgent. In checking the Urgent box, you attest to the fact that applying the standard review time frame may seriously jeopardize the customer's life, health, or ability to regain maximum function.
If this is an URGENT request, call (800) 882-4462 (800.88.CIGNA).
If your request is urgent, it is important that you call to expedite the request.
Medication requested and diagnosis related to use

Medication requested: please specify name, strength, and dosing schedule. Enter the Duration of therapy and the Quantity.
Under Diagnosis related to use, enter the diagnosis.
Pain medications only: terminal illness

For pain medications only: does the patient have a terminal illness? Check Yes or No.
Alternative medications: the generic alternative
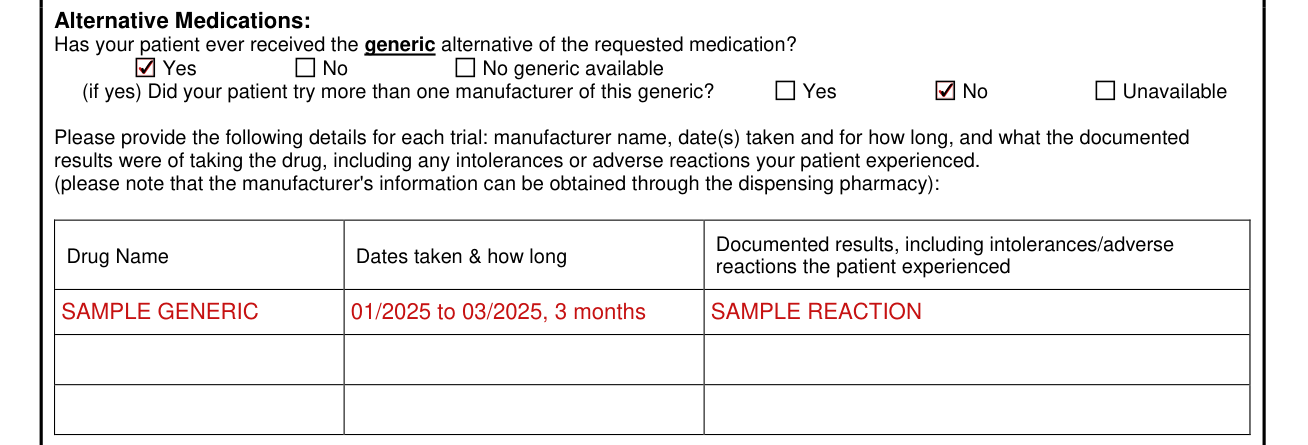
Alternative Medications: has your patient ever received the generic alternative of the requested medication? Check Yes, No or No generic available. If yes, did your patient try more than one manufacturer of this generic? Check Yes, No or Unavailable. Please provide the following details for each trial: manufacturer name, date(s) taken and for how long, and what the documented results were of taking the drug, including any intolerances or adverse reactions your patient experienced. Please note that the manufacturer's information can be obtained through the dispensing pharmacy.
Write the Drug Name, the Dates taken & how long, and the Documented results, including intolerances/adverse reactions the patient experienced.
Other alternative treatments for this diagnosis
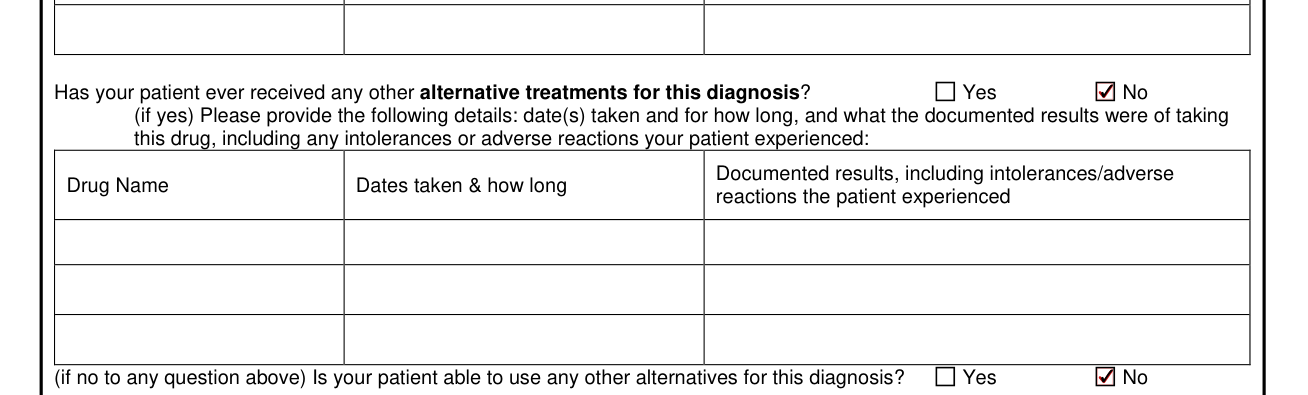
Has your patient ever received any other alternative treatments for this diagnosis? Check Yes or No. If yes, write the Drug Name, the Dates taken & how long, and the Documented results, including intolerances/adverse reactions the patient experienced.
Is your patient able to use any other alternatives

If no to any question on alternatives: is your patient able to use any other alternatives for this diagnosis? Check Yes or No.
If no, please provide the reason(s) why your patient is unable to use the available alternative(s). Under Additional pertinent information, please include other clinical reasons for drug, relevant lab values, etc.
Common questions about Medication Prior Authorization Form
How long does a pre-authorization usually take?
The standard response time for prescription drug coverage requests is 5 business days.
Where do I file it?
Fax the completed form to (855) 840-1678. Submit Online at: www.covermymeds.com/main/prior-authorization-forms/cigna/ or via SureScripts in your EHR.
Sources
[1] Medication Prior Authorization Form, Cigna (the Official source link on this page).
