
Prior Authorization Form PDF Details

At the heart of ensuring that patients receive the necessary medical care while navigating the complexities of health insurance coverage lies the Prior Authorization form, a critical document used across the healthcare industry. Emblematic of the intricate dance between healthcare providers, insurance companies, and patients, the form serves multiple pivotal roles. It acts as a referral mechanism, signaling to specialists that a primary care physician deems a consultation or treatment necessary. Furthermore, it underscores the importance of network adherence, particularly for patients under specific health plans, such as those affiliated with Banner Health Network, by stipulating that care should be sought from contracted providers to leverage benefits effectively. Besides facilitating the referral process, the Prior Authorization form plays a crucial role in the administrative side of healthcare, ensuring that all procedural and diagnostic services are pre-approved to avoid unwelcome financial surprises for patients. This process involves detailing the planned date of service, patient information, details of the requested provider including their Tax Identification Number (TIN), and the specifics of the treatment or consultation needed, along with relevant codes such as the International Classification of Diseases (ICD) and the Current Procedural Terminology (CPT). It also highlights the importance of complete and accurately filled forms, warning that any omission could lead to processing delays or outright refusal to see the patient, emphasizing the form's role in streamlining patient care coordination while adhering to policy requirements.

QuestionAnswer
Form NamePrior Authorization Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesbanner university family care prior auth form, university family care prior authorization form, university family care prior auth form, banner university family care prior auth

How to Fill Out Banner Health Network referral/prior authorization form

Banner Health Network referral/prior authorization form at a glance

What it is: The Banner Health Network referral/prior authorization form is the referral form that the specialist may refuse to see a patient without.

Who signs: After the Submit Information for request lines, the provider signs on the Provider Signature line and enters the Date.

A filled-in Banner Health Network referral/prior authorization form example: a primary care office asks for a cardiology visit

Banner Health Network referral/prior authorization form example filled out, example: a primary care office asks for a cardiology visit
Dr. Casey Sample's office fills out the referral form for a patient. The patient needs one outpatient cardiology visit, and the provider signs on 03-01-2026. The picture shows page 1 only, and its names and figures are sample values. The office asks the specialist only to confirm the diagnosis, so the Referral boxes under Requested Action by Specialist stay empty. The visit is outpatient and in network, so Out of Network, Inpt and Office stay empty. Banner fills in For Banner Use Only, so it stays empty.

How to fill out Banner Health Network referral/prior authorization form, box by box

Planned Date of Service

Banner Health Network referral/prior authorization form example filled out, planned Date of Service

Enter the Planned Date of Service; the form recommends not scheduling until authorization is obtained.

Patient and health plan

Banner Health Network referral/prior authorization form example filled out, patient and health plan

Enter the Patient, the DOB, the Patient's Health Plan and the ID#.

Requested Provider
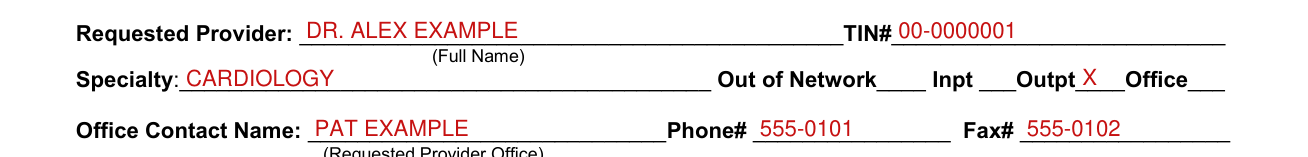
Banner Health Network referral/prior authorization form example filled out, requested Provider

For the Requested Provider, enter the Full Name and the TIN#, then the Specialty, then Out of Network, Inpt, Outpt and Office.

For the Requested Provider Office, enter the Office Contact Name, the Phone# and the Fax#.

Place of Service

Banner Health Network referral/prior authorization form example filled out, place of Service

For the Place of Service, enter the Facility Name and the TIN#.

Referring Provider

Banner Health Network referral/prior authorization form example filled out, referring Provider

For the Referring Provider, enter the Full Name, the Phone# and the Fax#, then the Office Contact Name with the Phone# and the Fax# of the Referring Provider Office.

Requested Action by Specialist

Banner Health Network referral/prior authorization form example filled out, requested Action by Specialist

Requested Action by Specialist is optional for the PCP to complete.

Under Consultation (Please send the patient back for follow-up and treatment), mark Confirm Diagnosis, Advise as to Diagnosis or Suggest Medication or Treatment.

Under Referral (Please provide PCP with summaries of subsequent visits), mark Assume management for this particular problem and return patient after conclusion of care, or Assume future management of patient within your area of expertise.

Diagnosis, treatment and submitted information
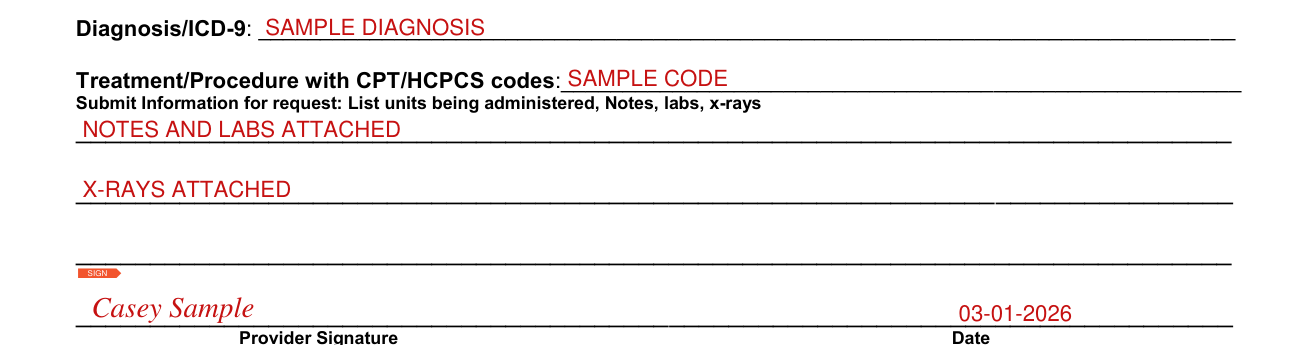
Banner Health Network referral/prior authorization form example filled out, diagnosis, treatment and submitted information

Enter the Diagnosis/ICD-9 and the Treatment/Procedure with CPT/HCPCS codes.

Under Submit Information for request, list units being administered, Notes, labs, x-rays.

After the Submit Information for request lines, the provider signs on the Provider Signature line and enters the Date.

For Banner Use Only

Banner Health Network referral/prior authorization form example filled out, for Banner Use Only

The For Banner Use Only box is for Banner's use only.

More rules for Banner Health Network referral/prior authorization form

Incomplete forms will not be processed and will be returned to the sending provider.

The following applies only to Banner Choice Plus patients: to access the Banner Option Benefit, the Primary Care Physician should refer the patient to a contracted provider.

For Banner Choice Plus patients only: to ensure the recommended provider is contracted, call the Banner Benefits Service Center at 480-684-7070 (within Metro Phoenix area) or at 800-827-2464, or go on the web www.BannerHealthPlans.com.

Common questions about Banner Health Network referral/prior authorization form

Where do I file it?

The BHN Prior Authorization Dept Fax is 480-684-7200 (within Metro Phoenix Area) or 800-697-1441, and its Phone is 480-684-7070.

Sources

[1] BHN Referral Form Revised on 7-6-12 (the served file; no issuer file found) (the Official source link on this page).