


Prior Authorization Request Form at a glance
What it is: Prior Authorization Request Form: A. Member information, B. ICD-10-CM diagnosis code(s), C. Procedure/service/treatment information, D. Provider information and E. General Comments.
Who signs: Expedited request: MD, PA, RN, RD or LPN signature required.
A filled-in Prior Authorization Request Form example: a standard outpatient request
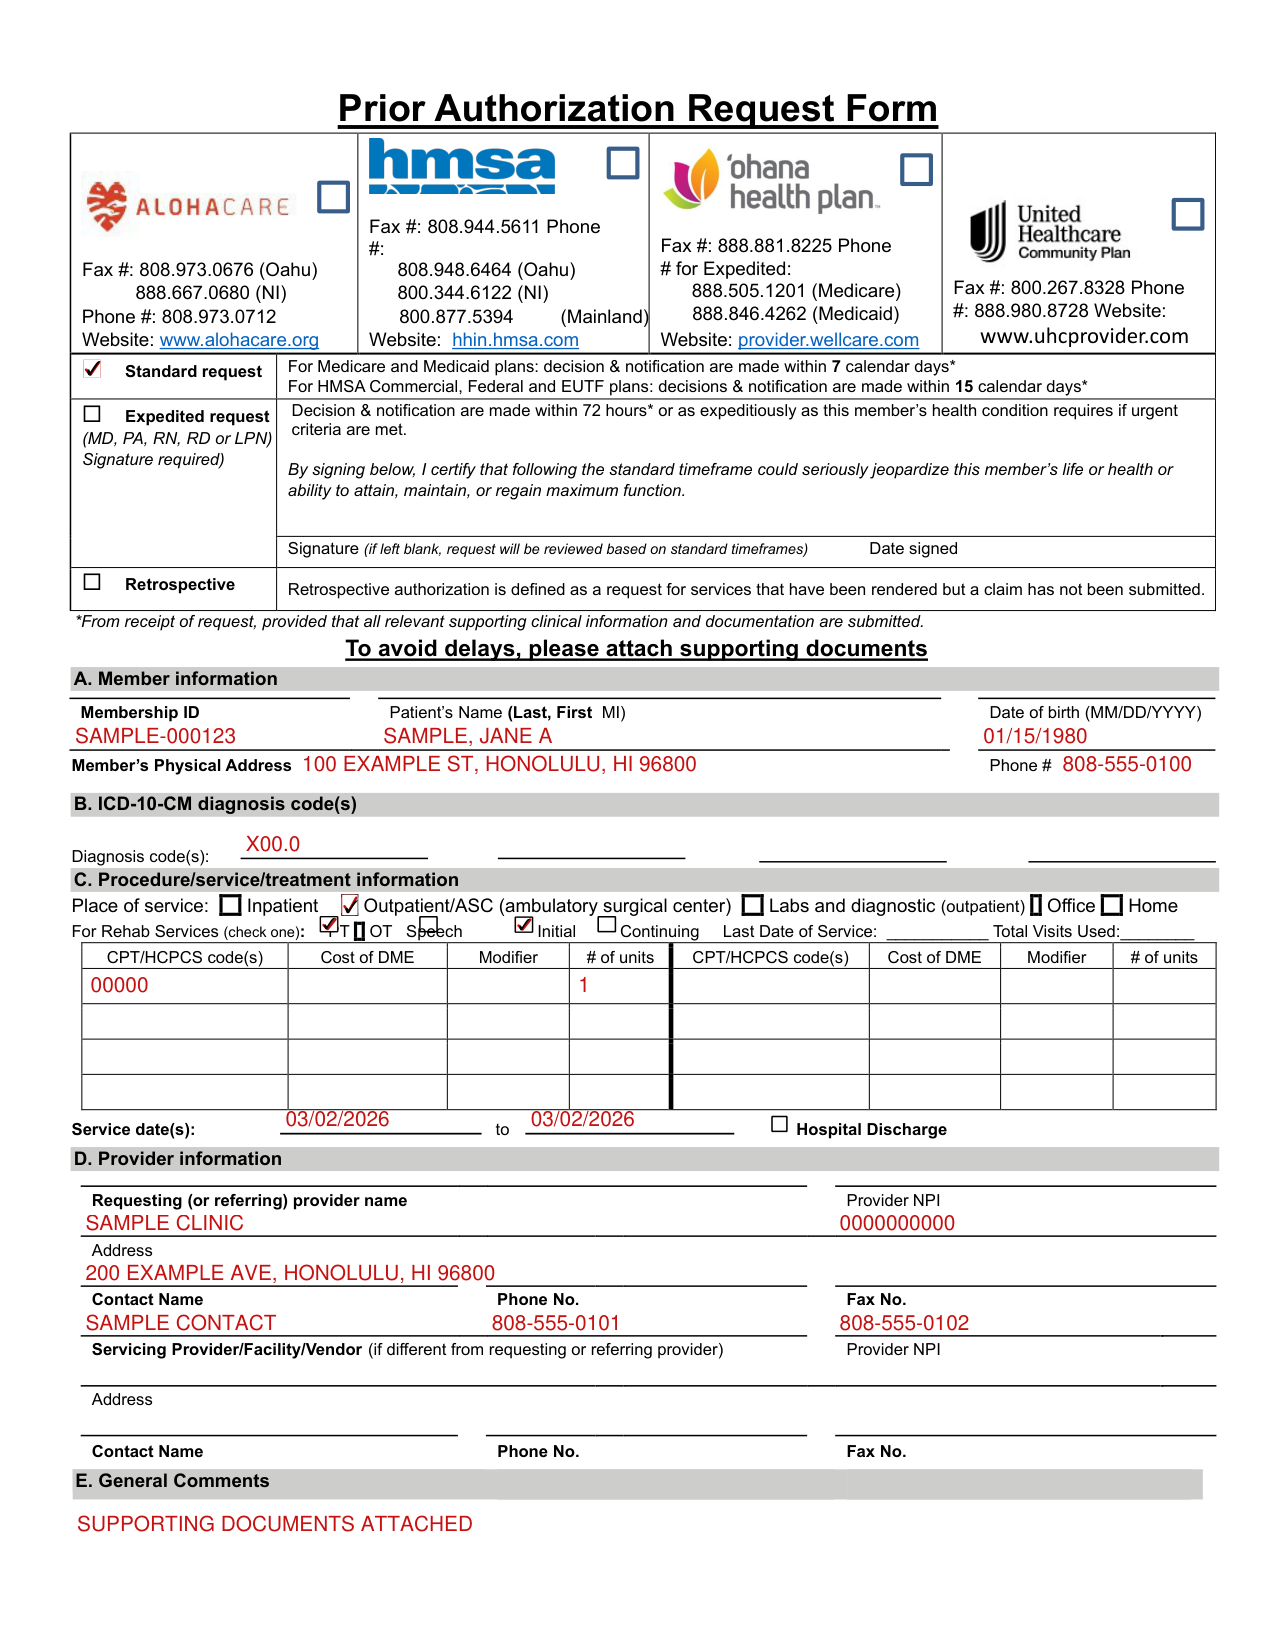
How to fill out Prior Authorization Request Form, box by box
Standard, expedited or retrospective request

For Medicare and Medicaid plans, decision and notification on a standard request are made within 7 calendar days; for HMSA Commercial, Federal and EUTF plans, within 15 calendar days, from receipt of request, provided that all relevant supporting clinical information and documentation are submitted; to avoid delays, please attach supporting documents.
For an expedited request, decision and notification are made within 72 hours or as expeditiously as this member's health condition requires if urgent criteria are met.
Signing certifies that following the standard timeframe could seriously jeopardize this member's life or health or ability to attain, maintain, or regain maximum function; enter the Date signed; if the signature is left blank, the request will be reviewed based on standard timeframes.
Retrospective authorization is defined as a request for services that have been rendered but a claim has not been submitted.
A. Member information
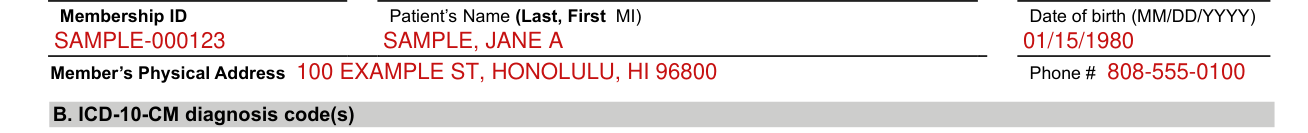
Under A. Member information, enter the Membership ID, Patient's Name (Last, First MI), Date of birth (MM/DD/YYYY), Member's Physical Address and Phone #.
B. ICD-10-CM diagnosis code(s)

Under B. ICD-10-CM diagnosis code(s), enter the Diagnosis code(s).
Place of service and Rehab Services
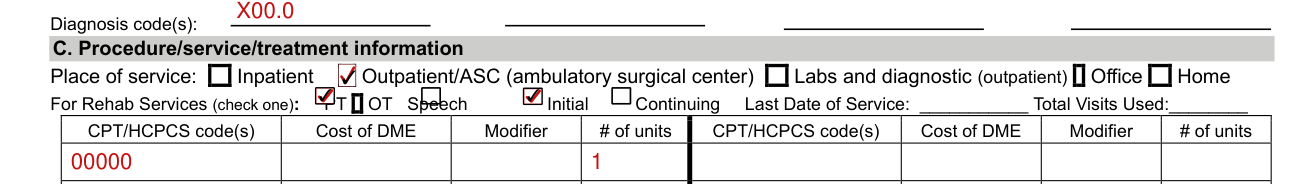
Under Place of service, mark Inpatient, Outpatient/ASC (ambulatory surgical center), Labs and diagnostic (outpatient), Office or Home.
For Rehab Services (check one): PT, OT or Speech, then Initial or Continuing, with Last Date of Service and Total Visits Used.
C. Procedure/service/treatment information
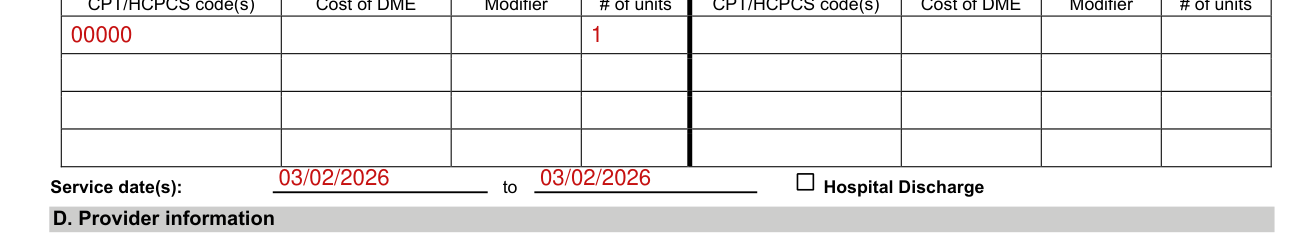
Under C. Procedure/service/treatment information, enter the CPT/HCPCS code(s), Cost of DME, Modifier and # of units.
Enter the Service date(s).
D. Provider information
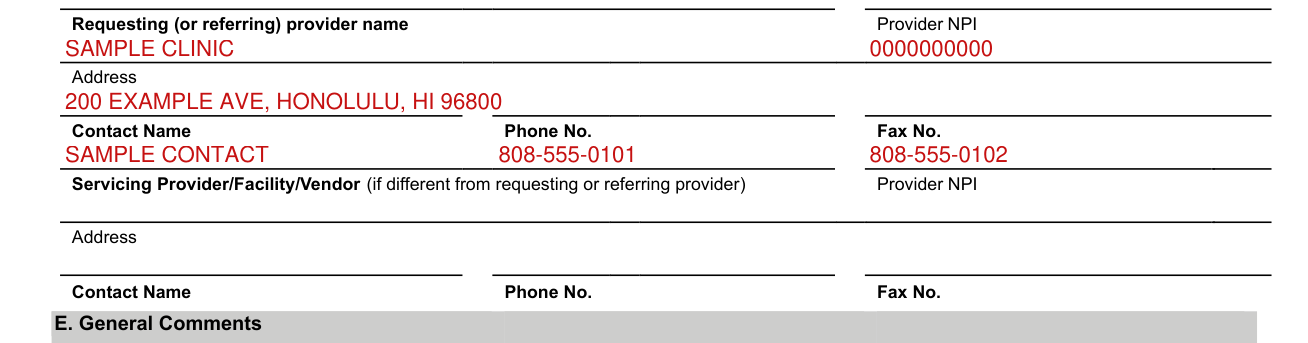
Under D. Provider information, enter the Requesting (or referring) provider name, Provider NPI, Address, Contact Name, Phone No. and Fax No.
Enter the Servicing Provider/Facility/Vendor, Provider NPI, Address, Contact Name, Phone No. and Fax No. if different from requesting or referring provider.
E. General Comments

Write any comments under E. General Comments.
Sources
[1] Prior Authorization Request Form (PriorAuth.Allplan_Form 01/01/2026), UnitedHealthcare Community Plan of Hawaii (the Official source link on this page).