

Request for Prior Authorization at a glance
What it is: Request for Prior Authorization: Complete and Submit Your Request.
Who signs: Sign on the line for Plan Member Signature and enter the Date. Sign on the line for Physician Signature and enter the Date.
Any plan member who is prescribed a medication that requires prior authorization needs to complete and submit this form.
A filled-in Request for Prior Authorization example: a plan member fills out Part A

How to fill out Request for Prior Authorization, box by box
Patient information
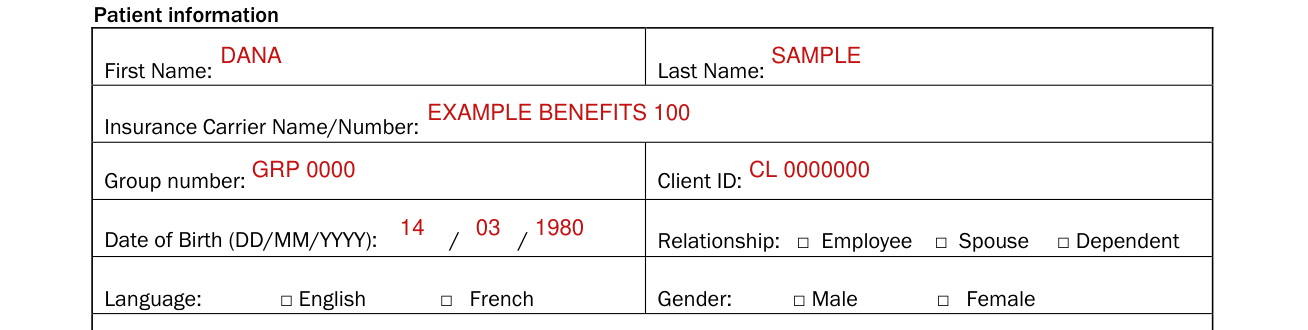
In Part A, enter First Name, Last Name, Insurance Carrier Name/Number, Group number, Client ID and Date of Birth (DD/MM/YYYY).
Relationship: Employee, Spouse or Dependent. Language: English or French. Gender: Male or Female.
Address, email and telephone

Enter Address, City, Province, Postal Code, Email address, Telephone (home), Telephone (cell) and Telephone (work).
Patient Assistance Program

Patient Assistance Program: Is the patient enrolled in any patient support program? Yes or No. Enter the Contact name and Telephone.
Authorization

On behalf of myself and my eligible dependents, I authorize my group benefit provider, and its agents, to exchange the personal information contained on this form. I give my consent on the understanding that the information will be used solely for purposes of administration and management of my group benefit plan.
This consent shall continue so long as my dependents and I are covered by, or are claiming benefits under the present group contract, or any modification, renewal, or reinstatement thereof.
Sign on the line for Plan Member Signature and enter the Date.
More rules for Request for Prior Authorization
Completion and submission of this form is not a guarantee of approval. Plan members will receive reimbursement for the prior authorized drug through their private drug benefit plan only if the request has been reviewed and approved by Express Scripts Canada.
The plan member will be notified whether their request has been approved or denied.
You have the right to appeal the decision made by Express Scripts Canada.
Drugs in the Prior Authorization Program may be eligible for reimbursement only if the patient uses the drug(s) for Health Canada approved indication(s).
All information requested in Part B - Prescribing Doctor is mandatory for the approval process.
Any fields left blank will result in an automatic denial.
Please fill any non-applicable fields with 'N/A'. Supplemental information for this drug reimbursement request will be accepted.
First time Prior Authorization application for this drug: Fill sections 1, 2 and 4. Prior Authorization Renewal for this drug: Fill sections 1, 3 and 4.
Part B - Prescribing Doctor
Section 1 - Drug requested
Under SECTION 1 - DRUG REQUESTED, enter Drug name, Dose, Administration (ex: oral, IV, etc), Frequency, Duration and Medical condition.
Will this drug be used according to its Health Canada approved indication(s)? Yes or No.
Site of drug administration: Home, Doctor office/Infusion clinic, Hospital (outpatient) or Hospital (inpatient).
Section 2 - First-time application
Under SECTION 2 - FIRST-TIME APPLICATION, enter any relevant information of the patient's condition including the severity/stage/type of condition. Example: monthly frequency and duration for migraines, fibrosis status for Hepatitis C patient, lab values such as LDL and IgE levels, BMI, symptoms etc. (please do not provide genetic test information or results)
Enter the therapies (pharmacological/non-pharmacological) that will be used for treating the same condition concomitantly.
Section 2 - Continued, previously tried therapies
Under Section 2 - Continued, list previously tried therapies: Drug, Dosage and administration, Duration of therapy From and To, and Reason for cessation: Inadequate/ Suboptimal response or Allergy/ Drug Intolerance.
Section 3 - Renewal information
Under SECTION 3 - RENEWAL INFORMATION, enter the Date of treatment initiation and the Details on clinical response to requested drug. Example: PASI/BASDAI, laboratory tests, etc. Do not provide genetic test information or results.
If prior approval was not authorized by Express Script Canada, please attach a copy of the approval letter.
Section 4 - Prescriber information
Under SECTION 4 - PRESCRIBER INFORMATION, enter Physician's Name, Address, Tel, Fax, License No. and Specialty.
Sign on the line for Physician Signature and enter the Date.
Common questions about Request for Prior Authorization
What is the Express Scripts prior authorization process?
Plan Member completes Part A. Prescribing doctor completes Part B.
Where do I file it?
Fax or mail the completed form to Express Scripts Canada. Fax: Express Scripts Canada Clinical Services 1 (855) 712-6329. Mail: Express Scripts Canada Clinical Services 5770 Hurontario Street, 10th Floor, Mississauga, ON L5R 3G5.
Sources
[1] Request for Prior Authorization, Express Scripts Canada (the Official source link on this page).
